Mental Matters

Haemophilus influenzae type b

Sick child in bed with a concerned parent checking her forehead for fever

Haemophilus influenzae type b

Haemophilus influenzae type b Haemophilus influenzae type b (Hib) is a serious bacterial infection that can cause life-threatening illnesses such as meningitis, pneumonia, epiglottitis, and bloodstream infections, particularly in children under the age of five. Before the introduction of effective vaccines, Haemophilus influenzae type b was one of the leading causes of bacterial meningitis in young children around the world. Although it no longer poses the same threat in countries with widespread vaccination programmes, it remains a concern in regions with limited healthcare access. Hib is a type of Haemophilus influenzae bacterium, a family of bacteria that can inhabit the upper respiratory tract. While many strains are harmless, type b is particularly aggressive. It has the ability to invade the bloodstream and spread to critical organs, causing severe and sometimes fatal disease. Early detection and prevention through immunisation remain the most effective ways to control this dangerous pathogen. What is Haemophilus influenzae type b? Haemophilus influenzae type b is a gram-negative coccobacillus bacterium that primarily affects infants and young children. It is one of six types (a through f) of encapsulated Haemophilus influenzae. The “type b” designation refers to the specific structure of the bacterium’s outer capsule, which is what makes it more virulent than other strains. Hib is not a virus, and despite its name, it has no relation to influenza (the flu). The confusion arose historically when the bacterium was first identified during an influenza outbreak in the late 19th century. Who is at Risk? Children under five, especially those aged between 6 months and 2 years Unvaccinated infants and toddlers People with weakened immune systems, such as those undergoing chemotherapy or living with HIV/AIDS Indigenous populations in certain countries, where the disease remains more prevalent Elderly adults with underlying health conditions, although this is far less common Without vaccination, Hib can spread rapidly, particularly in crowded settings like day-care centres and schools. How is Hib Transmitted? The bacteria are spread via respiratory droplets when an infected person: Coughs Sneezes Talks at close range Once inhaled, Hib can colonise the upper respiratory tract and either remain harmless or invade deeper tissues. It can spread to the bloodstream and then to the brain, lungs, bones, or joints. Diseases Caused by Hib Haemophilus influenzae type b is responsible for several invasive diseases, including: 1. Meningitis Infection of the membranes surrounding the brain and spinal cord Symptoms: high fever, stiff neck, vomiting, irritability, drowsiness Can lead to permanent brain damage or death if untreated 2. Epiglottitis Swelling of the epiglottis (the flap at the back of the throat) Symptoms: difficulty breathing, drooling, high fever, anxiety Medical emergency requiring immediate intervention 3. Pneumonia Infection of the lungs Symptoms: cough, difficulty breathing, chest pain, fever Common in both children and older adults 4. Sepsis (Bloodstream Infection) Bacteria enter the bloodstream and spread rapidly Symptoms: fever, rapid heartbeat, low blood pressure, confusion Can progress quickly to septic shock 5. Septic Arthritis Infection of a joint, usually the hip or knee Causes pain, swelling, redness, and restricted movement 6. Osteomyelitis Infection of the bone Leads to localised pain, fever, and swelling Even with antibiotics, these conditions can result in long-term complications or death, particularly in young children. Global Impact and Vaccination Success Prior to the introduction of the Hib vaccine: Hib caused an estimated 400,000 deaths annually in children under five Developed countries saw thousands of cases of meningitis and epiglottitis each year Today, in countries with effective immunisation campaigns: Hib disease is rare Routine infant immunisation has reduced incidence by over 95% Outbreaks are largely confined to under-vaccinated communities Unfortunately, in parts of sub-Saharan Africa, Asia, and Latin America, Hib continues to be a public health concern, especially where vaccination coverage is low or interrupted by conflict or poverty. Prevention is Key The most effective way to prevent Hib is through routine vaccination, usually administered as part of a combination vaccine (e.g. DTaP-IPV-Hib). The vaccine is: Given in multiple doses, starting from 6 weeks of age Highly effective, with few side effects Often combined with protection against diphtheria, tetanus, pertussis, and polio Herd immunity plays a significant role in protecting vulnerable populations, such as infants too young to be vaccinated or individuals with immunodeficiencies. Conclusion | Haemophilus influenzae type b Haemophilus influenzae type b is a dangerous bacterial infection that once claimed thousands of lives every year. Thanks to effective vaccines, it is now preventable in most parts of the world. However, ongoing vigilance and sustained immunisation efforts are vital to keeping Haemophilus influenzae type b under control—particularly in low-income regions where children remain at risk. [Next: Causes of Haemophilus influenzae type b →]

Haemophilus influenzae type b Read More »

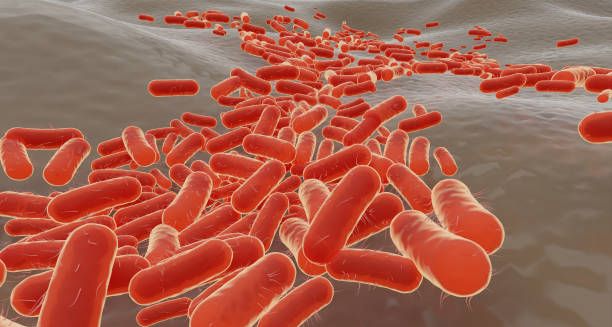
3D illustration of Haemophilus influenzae type b bacteria under magnification.

Causes of Haemophilus influenzae type b

Causes of Haemophilus influenzae type b The causes of Haemophilus influenzae type b disease centre around the bacterium’s ability to enter the body, evade the immune system, and infect vital tissues. Although the causes of Haemophilus influenzae type b illness are well understood in terms of transmission and pathophysiology, certain risk factors can increase the likelihood of severe infection, especially in young children or those with underdeveloped immune defences. Haemophilus influenzae type b (Hib) does not cause disease in everyone it infects. In fact, many people—especially adults—can carry the bacteria in their nose or throat without ever becoming ill. The danger arises when the bacteria penetrate beyond the respiratory tract into areas of the body that are normally sterile, such as the bloodstream, brain, or lungs. 1. Transmission and Entry into the Body Hib spreads from person to person through respiratory droplets. When an infected person sneezes, coughs, or speaks, they release bacteria into the air. These bacteria can then: Colonise the nasopharynx, the upper part of the throat behind the nose Remain harmless in many carriers Cross mucosal barriers under certain conditions, especially when the immune system is compromised Once past the mucosal defences, Hib can: Enter the bloodstream, leading to sepsis Travel to the meninges, causing meningitis Infect the lungs, joints, or bones 2. Capsule-Driven Virulence What sets Hib apart from other types of Haemophilus influenzae is its polysaccharide capsule, known as type b capsule. This capsule: Protects the bacterium from being destroyed by immune cells (phagocytes) Inhibits complement-mediated killing (a key immune system response) Allows the bacteria to survive in the bloodstream and spread throughout the body Strains without this capsule (non-typeable H. influenzae) are less invasive and usually only cause mild respiratory illness or ear infections. 3. Host Factors That Increase Risk Certain individuals are more susceptible to invasive Hib disease due to underlying conditions, such as: a. Young Age Children under five have immature immune systems, making it harder for them to fight off encapsulated bacteria Maternal antibodies may wear off before vaccines take full effect b. Lack of Vaccination Unvaccinated children are at high risk, especially in regions with poor immunisation coverage Delayed or missed vaccine doses reduce protection c. Immunodeficiency Children and adults with conditions like HIV, cancer, or those undergoing immunosuppressive therapy These individuals are less able to clear infections from the bloodstream d. Asplenia (No Spleen) The spleen plays a crucial role in removing encapsulated bacteria People without a functioning spleen (due to trauma, surgery, or disease) are highly vulnerable to Hib e. Malnutrition Poor nutritional status weakens the immune response Increases the severity and duration of infections f. Crowded Living Conditions Hib spreads more easily in settings where close contact is common, such as schools, nurseries, and refugee camps 4. Environmental and Geographic Factors Haemophilus influenzae type b disease is more prevalent in: Low-income countries, where vaccination access is limited Areas with poor public health infrastructure Regions with high rates of respiratory infections, which can facilitate bacterial entry In countries with high vaccine uptake, most Hib cases occur in: Unvaccinated individuals Children who are too young to have received the full vaccine course Immigrant populations from countries without routine Hib immunisation 5. Co-Infections and Viral Illness Viral infections like influenza, RSV, or adenovirus can: Damage the respiratory tract lining Create an entry point for bacteria like Hib Suppress immune responses temporarily This sets the stage for secondary bacterial infections, increasing the likelihood that Hib will invade deeper tissues. 6. Genetic Susceptibility (Under Investigation) Some research suggests that genetic differences in immune system regulation may influence: The body’s ability to recognise and destroy Hib Susceptibility to invasive disease in early childhood Response to vaccination Although not yet fully understood, this area remains a focus of ongoing scientific investigation. Summary Table: Key Factors Contributing to Hib Infection Contributing Factor Role in Disease Respiratory droplet exposure Main route of transmission Type b capsule Protects bacteria from immune attack Young age Weaker immune defence in infants Unvaccinated status Lack of protection increases risk Immunodeficiency Reduces ability to fight infection Crowded conditions Facilitates spread of bacteria Viral co-infections Compromise respiratory defences Conclusion | Causes of Haemophilus influenzae type b The causes of Haemophilus influenzae type b infection are multifactorial, involving bacterial virulence, host immune status, and environmental exposure. Understanding these causes of Haemophilus influenzae type b is essential to guide prevention, particularly through timely vaccination and targeted public health strategies in vulnerable populations. [Next: Symptoms of Haemophilus influenzae type b→]

Causes of Haemophilus influenzae type b Read More »

Mother checking the temperature of a sick child wrapped in a blanket.

Symptoms of Haemophilus influenzae type b

Symptoms of Haemophilus influenzae type b Identifying the symptoms of Haemophilus influenzae type b (Hib) promptly is crucial, as this bacterial infection can progress rapidly, leading to severe complications or even death if untreated. Recognising the symptoms of Haemophilus influenzae type b early can significantly improve patient outcomes and reduce the risk of serious long-term effects. Hib typically affects young children under five years old, though it can occasionally occur in adults, particularly those with compromised immune systems. Initial symptoms often appear mild and similar to common infections, making early recognition challenging. In the early stages, patients might experience fever, lethargy, and irritability. These nonspecific symptoms can easily be mistaken for common viral infections or the flu, particularly in children who might not clearly express their discomfort or pain. As the infection progresses, however, the symptoms become more distinctive and severe, often indicating invasive disease. Symptoms of Haemophilus influenzae type b Meningitis caused by Hib is one of the most serious manifestations. Symptoms indicative of meningitis include a stiff neck, severe headache, photophobia (sensitivity to light), vomiting, altered consciousness, and seizures. In young infants, the classic stiff neck might be absent, and they may instead present with poor feeding, inconsolable crying, high fever, and a bulging fontanelle (soft spot on the head). Parents and caregivers should seek immediate medical attention if any of these symptoms are observed. Another common invasive condition caused by Hib is epiglottitis, a severe swelling of the epiglottis that can rapidly obstruct the airway. Patients with epiglottitis typically show sudden onset of symptoms such as difficulty breathing, drooling due to an inability to swallow saliva, a hoarse voice, and a characteristic posture of leaning forward with an extended neck (known as the tripod position) to ease breathing. Epiglottitis is a medical emergency and requires immediate intervention to secure the airway. Symptoms of Haemophilus influenzae type b Pneumonia is also associated with Hib infections, presenting with symptoms including coughing, difficulty breathing, rapid breathing, chest pain, and fever. Unlike mild respiratory illnesses, Hib-related pneumonia can quickly worsen, necessitating prompt medical intervention to prevent severe complications or fatalities. Less commonly, Hib can cause cellulitis, a deep skin infection characterised by redness, warmth, swelling, and tenderness of the skin, usually on the face, particularly around the cheeks and eyes. The infected skin area can expand rapidly, and patients often experience fever and general malaise alongside localised symptoms. Septic arthritis, another possible manifestation, presents as joint swelling, severe pain and redness. Additionally, warmth of the affected joint, typically accompanied by a high fever. Infants may refuse to move the affected limb or become unusually irritable when the joint is touched or moved. Bacteraemia, or bloodstream infection, caused by Hib, can present initially with nonspecific symptoms such as high fever. As well as chills, rapid breathing, and extreme fatigue. If untreated, bacteraemia can lead to sepsis, a life-threatening condition characterised by organ dysfunction and shock. Symptoms of Haemophilus influenzae type b Early recognition of the symptoms of Haemophilus influenzae type b is essential for rapid initiation of treatment. Caregivers, parents, and healthcare professionals must maintain vigilance. Especially in unvaccinated populations or immunocompromised individuals, as Hib infections can rapidly escalate into severe and life-threatening conditions. [Next: Diagnosis of Haemophilus influenzae type b→]

Symptoms of Haemophilus influenzae type b Read More »

Mother caring for sick child lying on sofa with tissues and thermometer.

Diagnosis of Haemophilus influenzae type b

Diagnosis of Haemophilus influenzae type b Accurate and timely diagnosis of Haemophilus influenzae type b infections is critical to ensuring effective treatment and preventing severe outcomes. The diagnosis of Haemophilus influenzae type b primarily relies on laboratory tests, clinical assessment, and patient history. Healthcare professionals must remain alert to potential cases, particularly in unvaccinated or immunocompromised patients, as Hib infections can rapidly progress to severe illness or death if not promptly identified and managed. Initially, clinicians perform a thorough clinical assessment, evaluating symptoms and patient history. Recognising symptoms such as high fever, irritability, stiff neck, respiratory distress, and other specific signs indicative of invasive Hib diseases, such as meningitis or epiglottitis, provides a strong basis for suspicion of Hib infection. Once a clinician suspects Hib, laboratory confirmation is necessary. Blood cultures are among the most commonly utilised diagnostic tests for invasive Hib diseases. These cultures involve drawing blood from the patient and incubating it under conditions favourable for bacterial growth. If Haemophilus influenzae type b is present, it will multiply, allowing identification through microbiological techniques. Blood cultures are particularly useful in diagnosing bacteraemia and other invasive conditions caused by Hib. For suspected meningitis, clinicians often perform a lumbar puncture (spinal tap). Cerebrospinal fluid (CSF) obtained from this procedure undergoes analysis for cell count, glucose levels, protein concentration, and bacterial culture. Typically, Hib meningitis is associated with increased white blood cell counts (predominantly neutrophils), elevated protein levels, and reduced glucose levels in CSF. Bacterial culture of the CSF is essential for definitive diagnosis and antibiotic susceptibility testing. Diagnosis of Haemophilus influenzae type b In cases of suspected pneumonia caused by Hib, clinicians might request chest X-rays alongside blood cultures. Radiographic images can reveal characteristic signs of pneumonia, such as infiltrates, consolidation, or pleural effusion. While chest imaging is supportive, microbiological confirmation through blood or sputum cultures remains essential for definitive diagnosis. Epiglottitis, a life-threatening manifestation of Hib infection, is typically diagnosed clinically due to its rapid progression and severity. Nonetheless, confirmation is frequently obtained through direct visualisation during endoscopy, where a swollen, cherry-red epiglottis is observed. Throat cultures or blood cultures provide microbiological confirmation, though clinical suspicion alone often dictates immediate treatment to secure the airway and stabilise the patient. Rapid antigen detection tests (RADTs) and polymerase chain reaction (PCR) tests for Hib are increasingly utilised due to their speed and accuracy. PCR assays can detect Hib DNA directly from clinical specimens such as blood, CSF, or respiratory secretions, offering quicker results compared to traditional cultures, particularly important for critically ill patients. In less severe presentations, such as cellulitis or septic arthritis, diagnosis usually involves aspirating fluid from affected areas, such as joint fluid in arthritis or pus from cellulitis lesions, for Gram staining, culture, and PCR testing. Identifying Hib directly from these sites can confirm the diagnosis promptly. Diagnosis of Haemophilus influenzae type b Laboratory identification of Haemophilus influenzae type b typically involves examining bacterial colonies cultured on specialised media. Hib bacteria grow optimally on chocolate agar, a nutrient-rich medium containing factors required by the organism. Colonies typically appear smooth, round, and slightly convex, often producing a distinct odour. Further biochemical tests or serotyping confirm the identification. Prompt and accurate diagnosis of Haemophilus influenzae type b ensures timely initiation of appropriate antibiotic therapy, significantly improving patient outcomes. Early diagnosis not only facilitates rapid treatment but also helps implement public health measures, such as contact tracing and vaccination strategies, to prevent further spread of the infection. [Next: Treatment of Haemophilus influenzae type b→]

Diagnosis of Haemophilus influenzae type b Read More »

Medical professional administering vaccine to a patient’s arm

Treatment of Haemophilus influenzae type b

Treatment of Haemophilus influenzae type b Prompt and effective treatment of Haemophilus influenzae type b (Hib) infections is essential to prevent severe complications or death. The cornerstone of treatment of Haemophilus influenzae type b involves antibiotic therapy, supportive care, and occasionally surgical interventions depending on the clinical presentation and severity of the disease. Immediate medical attention and aggressive management can dramatically improve patient outcomes. Antibiotic therapy is crucial in managing Hib infections. Initial empirical antibiotic therapy often involves broad-spectrum antibiotics such as ceftriaxone or cefotaxime, effective against Hib strains. Doctors give these antibiotics through a vein so they can work quickly. This fast action helps the medicine reach the blood and tissues in time. As a result, it becomes easier to treat serious Hib infections like meningitis, epiglottitis, or blood infections.. Once laboratory results identify Hib and antibiotic sensitivity testing is available, clinicians might tailor antibiotic therapy accordingly, often continuing intravenous treatment for at least 7–14 days to ensure eradication of the bacteria. Treatment of Haemophilus influenzae type b For Hib meningitis, prompt initiation of antibiotic therapy significantly reduces mortality and neurological complications. Alongside antibiotics, corticosteroids like dexamethasone are sometimes administered shortly before or concurrently with antibiotics to reduce inflammation and minimise potential hearing loss and neurological damage. Close monitoring in a hospital setting is necessary to manage potential complications like seizures, cerebral oedema, or increased intracranial pressure. Epiglottitis requires immediate airway management alongside antibiotics. Patients typically require urgent hospitalisation and are often admitted to intensive care units for close observation. Due to potential airway obstruction, clinicians might perform immediate endotracheal intubation or tracheostomy to secure the airway before administering antibiotics. Supportive therapies, such as intravenous fluids and oxygen therapy, are essential to stabilise and manage patients effectively. Patients with Hib pneumonia or cellulitis typically receive antibiotics intravenously initially, with supportive therapies tailored according to symptoms such as respiratory support, hydration, and analgesics to manage pain. Early intervention prevents the progression to severe complications like sepsis or extensive tissue damage. Septic arthritis caused by Hib requires prompt drainage of infected joint fluid combined with antibiotic treatment. Orthopaedic interventions might involve repeated joint aspirations or surgical drainage procedures. To remove infected material effectively and alleviate pressure and pain in the joint. Treatment of Haemophilus influenzae type b Effective management of Hib infections also involves public health interventions. Such as prophylactic antibiotics administered to close contacts, particularly in household settings, to prevent secondary infections. Rifampicin is commonly recommended for chemoprophylaxis to eradicate nasopharyngeal carriage of Hib and prevent further transmission. [Next: Complications of Haemophilus influenzae type b→]

Treatment of Haemophilus influenzae type b Read More »

Three young children lying on a bed with tissues, showing cold or flu symptoms

Complications of Haemophilus influenzae type b

Complications of Haemophilus influenzae type b Identifying and managing potential complications of Haemophilus influenzae type b infections early can significantly impact long-term outcomes and survival rates. The complications of Haemophilus influenzae type b are often severe, affecting multiple organ systems, and require diligent clinical monitoring and intervention to minimise lasting damage or fatality. One of the most serious complications associated with Hib infections is meningitis. Even with appropriate treatment, meningitis can lead to severe neurological sequelae, including permanent hearing loss, intellectual disability, seizures, and cerebral palsy. Prompt antibiotic therapy and corticosteroids significantly reduce the incidence and severity of these neurological complications, but residual impairments may still persist in some patients, necessitating ongoing rehabilitation and supportive care. Epiglottitis, another severe complication of Hib, carries the immediate risk of airway obstruction, potentially leading to respiratory failure and death if untreated. Even after successful acute management, patients may suffer from prolonged hoarseness, difficulty swallowing, or chronic respiratory issues due to structural damage to the airway. Complications of Haemophilus influenzae type b Pneumonia resulting from Hib infection may escalate rapidly, leading to complications such as pleural effusion, empyema (accumulation of pus in the pleural space), lung abscesses, or respiratory failure. These complications require extensive medical and sometimes surgical interventions, prolonged hospital stays, and intensive rehabilitation efforts to restore pulmonary function fully. Bacteraemia, if not swiftly managed, can progress to sepsis, characterised by systemic inflammation, organ dysfunction, shock, and potential multi-organ failure. Sepsis necessitates aggressive intravenous fluid management, antibiotics, supportive therapies such as vasopressors, and close monitoring in intensive care units. Despite optimal treatment, severe sepsis can result in significant morbidity and mortality. Septic arthritis and cellulitis caused by Hib can also have serious long-term implications. Septic arthritis, if inadequately managed, might result in irreversible joint damage, chronic pain, and impaired mobility. Early surgical intervention and antibiotic therapy can minimise joint destruction and improve functional outcomes. Similarly, untreated or inadequately treated cellulitis can lead to widespread skin and soft tissue damage, scarring, and recurrent infections. Complications of Haemophilus influenzae type b Other potential long-term consequences of Hib infections include growth and developmental delays in children who experience severe systemic illness. Nutritional support, physiotherapy, occupational therapy, and psychological interventions may be necessary components of comprehensive care and recovery strategies. Preventing these complications primarily relies on vaccination against Hib, which has significantly reduced the incidence of invasive Hib diseases globally. Nonetheless, awareness and rapid intervention remain critical, especially in unvaccinated or immunocompromised populations. [Next: Back to Overview→]

Complications of Haemophilus influenzae type b Read More »

Scroll to Top