Mental Matters

Health & Wellness

Blood test sample labelled Anti C1q Antibody held by gloved hand

Diagnosis of Giant Cell Arteritis

Diagnosis of Giant Cell Arteritis The diagnosis of giant cell arteritis requires a combination of clinical evaluation, blood tests, imaging, and—when needed—biopsy. Because giant cell arteritis can cause irreversible complications such as vision loss or stroke, early and accurate diagnosis is vital. Treatment is often initiated based on strong clinical suspicion even before confirmation, due to the high risk of delay. This condition most commonly affects people over the age of 50, and the diagnostic process often begins when a patient presents with symptoms such as new-onset headache, jaw pain, or visual disturbances. Clinical Evaluation A detailed history and physical examination are the first steps. Key features that suggest GCA include: New, persistent headaches in people over 50 Jaw claudication Tenderness or thickening of the temporal arteries Scalp sensitivity Visual symptoms, such as blurred or double vision Symptoms of polymyalgia rheumatica On examination, doctors may find: Thick, tender, or pulseless temporal arteries Asymmetry in arterial pulses Bruits (abnormal whooshing sounds) over large vessels Signs of ischaemia, such as pale retina or afferent pupillary defect Blood Tests Although not diagnostic on their own, blood tests provide crucial supporting evidence. 1. Erythrocyte Sedimentation Rate (ESR) Often markedly elevated (typically over 50 mm/hr) Reflects systemic inflammation 2. C-Reactive Protein (CRP) Sensitive marker for inflammation May be raised even if ESR is normal 3. Full Blood Count May show normochromic, normocytic anaemia Thrombocytosis (elevated platelet count) is also common These results support a clinical diagnosis and help rule out other causes. Temporal Artery Biopsy The gold standard for diagnosis is a temporal artery biopsy, which involves removing a small section of artery from the temple for microscopic examination. Key findings include: Granulomatous inflammation Multinucleated giant cells Intimal thickening and vessel wall disruption While this is a highly specific test, false negatives can occur due to “skip lesions”, where inflammation affects segments of the artery unevenly. To reduce this risk, longer biopsy samples (2–3 cm) are preferred. Biopsy should be performed within 1–2 weeks of starting steroids, as treatment can begin to reduce inflammatory changes quickly. Imaging Studies Modern imaging techniques have become valuable in both diagnosing and monitoring giant cell arteritis, especially in cases where biopsy is not possible. 1. Ultrasound (Colour Doppler) Can detect the “halo sign”—a dark, hypoechoic ring around the artery indicating inflammation Non-invasive, fast, and increasingly used as a first-line test 2. MRI or CT Angiography Used to visualise larger arteries, such as the aorta or subclavian arteries Helps assess extent of vessel involvement and detect complications like aneurysms 3. FDG-PET Scan Useful in systemic or atypical cases Detects increased metabolic activity in inflamed arteries Expensive and less widely available Diagnostic Criteria The American College of Rheumatology (ACR) criteria for diagnosis include: Age over 50 New-onset localised headache Tenderness or decreased pulse in temporal artery ESR > 50 mm/hr Abnormal biopsy Meeting three or more of these criteria yields high diagnostic accuracy, though real-world diagnosis often relies on a combination of clinical judgement and test results. Differential Diagnosis Conditions that can mimic GCA include: Tension or migraine headaches Dental infections Trigeminal neuralgia Carotid artery dissection Meningitis or subarachnoid haemorrhage These possibilities must be ruled out, especially when symptoms are non-specific or when typical GCA features are absent. Initiating Treatment Before Confirmation Due to the risk of permanent vision loss, treatment with high-dose corticosteroids should begin immediately if GCA is strongly suspected—even before biopsy or imaging confirmation. Diagnosis of Giant Cell Arteritis Delaying treatment can result in devastating consequences, and early steroid use does not invalidate a biopsy for at least 7–10 days. [Next: Treatment of Giant Cell Arteritis→]

Diagnosis of Giant Cell Arteritis Read More »

Doctor giving medication and water to elderly patient in hospital bed

Treatment of Giant Cell Arteritis

Treatment of Giant Cell Arteritis The treatment of giant cell arteritis is aimed at reducing arterial inflammation, preventing irreversible complications such as vision loss and stroke, and minimising long-term treatment side effects. Because giant cell arteritis is a medical emergency when visual symptoms appear, treatment typically begins immediately, even before the diagnosis is confirmed. Corticosteroids are the mainstay of treatment, but newer therapies now offer more options for long-term disease control and steroid reduction. With prompt and appropriate management, most people can achieve disease remission and avoid the most serious consequences. Immediate Treatment Goals The urgent priorities in treating GCA are: Preserving vision in patients with visual symptoms Preventing stroke or other vascular complications Controlling systemic inflammation Alleviating symptoms such as headache, jaw pain, and fatigue Doctors typically begin treatment on the same day they suspect the diagnosis, especially if the patient presents with: Visual disturbances New-onset headache with elevated inflammatory markers Jaw claudication Corticosteroids: First-Line Therapy 1. High-Dose Prednisolone For patients without vision symptoms: 40–60 mg daily orally For patients with visual symptoms or transient loss: 500–1000 mg of intravenous methylprednisolone daily for 3 days, followed by high-dose oral steroids Corticosteroids typically produce a rapid clinical response, often within 24–72 hours. Inflammatory markers such as ESR and CRP begin to normalise, and systemic symptoms improve. However, the treatment does not cure the disease outright. Doctors use a slow tapering regimen, often lasting 12–18 months or longer, to prevent relapse. 2. Steroid Tapering Once symptoms and lab markers are stable for several weeks: Doctors gradually reduce the dose—for example, by 10 mg every 2 weeks until reaching 20 mg, then taper more slowly Doctors must individualise tapering based on symptom recurrence and inflammatory markers Relapses may occur and require dose adjustment Sudden reduction in steroid dose or rapid withdrawal can lead to flare-ups and increase risk of complications. Managing Steroid Side Effects Long-term steroid use can cause numerous side effects: Weight gain, fluid retention, and mood changes High blood pressure and diabetes Osteoporosis and fractures Increased infection risk Cataracts and glaucoma To counter these risks: Prescribe calcium and vitamin D supplements Consider bisphosphonates for bone protection Monitor blood glucose and blood pressure Schedule regular eye exams Encourage lifestyle changes such as low-sodium diets and physical activity Steroid-Sparing Therapy To reduce long-term steroid exposure, doctors increasingly use immunosuppressive or biologic agents, particularly in: Patients with frequent relapses Those with significant steroid side effects Individuals at high risk of complications from steroids 1. Tocilizumab (Actemra) An interleukin-6 (IL-6) receptor antagonist Administered weekly or monthly (subcutaneous or intravenous) Helps induce remission and allows faster steroid tapering Proven efficacy in clinical trials Tocilizumab is now widely accepted as a first-line steroid-sparing agent in GCA and may be used from the start in selected patients. 2. Methotrexate Taken weekly, often as a tablet or injection Modestly effective at reducing relapse and steroid dose Considered for patients intolerant to tocilizumab or with mild-to-moderate disease Doctors rarely use agents like azathioprine, leflunomide, or cyclophosphamide, reserving them for refractory or atypical cases. Monitoring and Follow-Up Regular follow-up is essential during treatment: Inflammatory markers (ESR and CRP) are checked every few weeks Blood pressure, glucose, and bone health are monitored regularly Eye exams are scheduled, particularly if vision symptoms were present Imaging (e.g. ultrasound or MRI) may be repeated if large-vessel involvement is suspected Doctors define relapse as the recurrence of symptoms and/or a rise in inflammatory markers. Doctors treat it by increasing the steroid dose and reassessing the treatment plan. Patient Education and Lifestyle Support Helping Patients Take Control of GCA Supporting patients is very important when dealing with a long-term illness like Giant Cell Arteritis (GCA). Here are some simple ways to help: Treatment in Different Patient Groups 1. Older Adults 2. People with Polymyalgia Rheumatica (PMR) 3. Large-Vessel GCA They must also keep an eye out for serious problems like aneurysms or vessel damage. This form may need treatment for a longer time. Doctors use scans like CT, MRI, or PET-CT to check blood vessels. Treatment of Giant Cell Arteritis The treatment of giant cell arteritis requires a multidisciplinary, patient-centred approach. With timely intervention and modern therapies, most individuals achieve suspension and retain their quality of life. [Next: Complications of Giant Cell Arteritis →]

Treatment of Giant Cell Arteritis Read More »

Elderly man covering his eyes with hands on blue background

Complications of Giant Cell Arteritis

Complications of Giant Cell Arteritis The complications of giant cell arteritis can be serious, life-altering, and even fatal if the disease is not diagnosed and treated quickly. Giant cell arteritis causes inflammation in large and medium arteries. Furthermore, most often affects the head and neck. However, sometimes this includes major vessels, such as the aorta. Without early treatment, the risk of vision loss, stroke, and aneurysm formation increases significantly. Fortunately, with prompt steroid therapy and careful monitoring, most complications can be avoided or managed effectively. Vision Loss One of the most feared complications of GCA is irreversible blindness, which may occur when: The posterior ciliary arteries become occluded Blood flow to the optic nerve is negatively affected A condition called anterior ischaemic optic neuropathy (AION) develops Vision loss may present as: Sudden, loss of sight in one eye Partial loss or field defects Transient visual blackouts (amaurosis fugax) that may precede permanent damage Once vision is lost, it is usually permanent. Therefore, rapid steroid treatment can protect the healthy eye, making early diagnosis essential. Stroke and Transient Ischaemic Attack (TIA) GCA can cause reduced blood flow to the brain, leading to: Stroke, if large arteries such as the carotid or vertebral arteries are narrow or blocked TIA, also known as a “mini-stroke,” involves temporary neurological symptoms These events may present as: Sudden weakness on one side of the body Difficulty speaking or understanding speech Dizziness or loss of coordination Facial Droop Stroke is a less common complication but is more likely in undertreated cases, particularly with large-vessel involvement. Aortic Aneurysm and Dissection In some patients, GCA extends to involve the aorta and its major branches, leading to structural weakening over time. This may result in: Aortic aneurysm—a bulging or dilation of the artery Aortic dissection—a tear in the artery wall, which is a medical emergency These complications often appear months to years after initial diagnosis, making long-term monitoring crucial. Signs may include: Chest or back pain Pulsatile mass in the abdomen Abnormal blood pressure readings in different limbs Regular imaging with CT angiography, MRI, or ultrasound is advised for individuals at a high risk. Relapse and Chronic Inflammation GCA frequently relapses, particularly during steroid tapering. Symptoms of relapse include: Return of headaches or jaw pain Fatigue and low-grade fever Elevated ESR or CRP Chronic, low-level inflammation may lead to: Persistent pain and stiffness Increased cardiovascular risk Ongoing need for immunosuppression Relapses can be managed by adjusting steroid dose or introducing biologic agents like tocilizumab. Osteoporosis and Fractures Long-term steroid use increases the risk of: Bone density loss (osteopenia and osteoporosis) Spinal or hip fractures Prevention includes: Calcium and vitamin D supplementation Bisphosphonates Bone mineral density monitoring via DEXA scans This complication is particularly relevant for elderly patients. Hereby, those who represent the majority of those with GCA. Glucose Intolerance and Hypertension Steroid therapy can cause: High blood sugar, potentially triggering or worsening diabetes Elevated blood pressure, increasing cardiovascular risk Management includes: Regular monitoring of blood glucose and blood pressure Dietary adjustments Medications to control side effects if needed Cataracts and Glaucoma Corticosteroids can increase the risk of: Cataracts, causing blurred or cloudy vision Glaucoma, a condition where increased eye pressure damages the optic nerve Patients on long-term steroids should receive regular eye examinations and report any vision changes promptly. Psychological and Social Effects Living with GCA can impact quality of life: Fear of relapse or blindness Fatigue from chronic inflammation Depression or anxiety Reduced mobility due to pain or joint stiffness Supportive care, counselling, and connection with patient support groups can help reduce the burden of illness. Summary of Key Complications Complication Description Vision loss Sudden, irreversible blindness in one or both eyes Stroke or TIA Neurological symptoms due to artery blockage Aortic aneurysm Arterial wall dilation with rupture risk Osteoporosis Fragile bones from long-term steroid use Diabetes and hypertension Steroid-induced metabolic complications Cataracts and glaucoma Vision problems linked to corticosteroids Relapse Recurrence of symptoms requiring treatment adjustment Complications of Giant Cell Arteritis Preventing the complications of giant cell arteritis requires early treatment, regular follow-up, and a multidisciplinary care approach. With advances in monitoring and biologic therapies, long-term outcomes are improving. Furthermore, offering hope to those living with this serious condition. [Next: Back to Overview →]

Complications of Giant Cell Arteritis Read More »

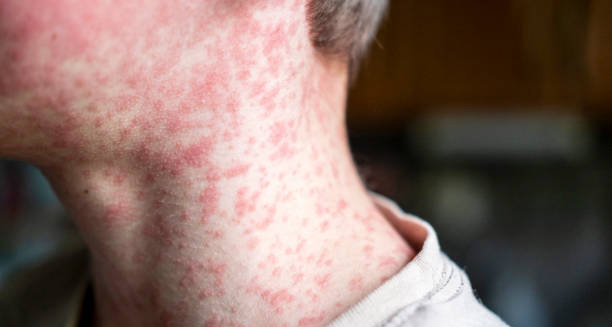
Red rash on the neck and jawline of a person with German Measles

German Measles

German Measles German measles is a contagious viral infection best known for its distinctive red-pink rash and mild flu-like symptoms. Also called rubella, German measles is caused by the rubella virus and typically results in a short, self-limiting illness in children and adults. However, when contracted during pregnancy—particularly in the first trimester—it can have devastating effects on the unborn baby, leading to congenital rubella syndrome (CRS), a serious condition with long-term consequences. Despite the name, German measles is not related to ordinary measles (rubeola), although the two diseases share similar symptoms. Rubella is usually milder and often goes unnoticed in healthy individuals. However, its ability to cause severe birth defects has made it a primary target for vaccination campaigns across the world. Thanks to widespread immunisation, the incidence of rubella has dropped dramatically in many countries, including South Africa. Nevertheless, outbreaks still occur, especially in communities with low vaccination rates or limited access to healthcare. This makes public awareness, early diagnosis, and continued vaccine coverage essential in preventing transmission and protecting vulnerable populations. What Is Rubella? Rubella is caused by the rubella virus, which belongs to the Togaviridae family. The virus spreads through respiratory droplets, meaning it can be passed on by coughing, sneezing, talking, or sharing drinks and utensils. Once inhaled, the virus multiplies in the nose and throat, then spreads through the bloodstream to other parts of the body. The incubation period is usually 14 to 21 days, during which time the person may not have symptoms but can still be contagious. Once symptoms appear, individuals are infectious from about 7 days before the rash appears to 7 days after. Who Is at Risk? Anyone who hasn’t been vaccinated or previously infected can contract rubella. Populations most at risk include: Unvaccinated children Adults who missed immunisation during childhood Pregnant women without immunity Healthcare workers in direct contact with patients Communities with vaccine hesitancy or poor access to healthcare Even in highly vaccinated countries, rubella remains a risk due to international travel and migration from regions where vaccination is less common. Signs and Symptoms Rubella often causes mild or no symptoms, especially in children. When symptoms do appear, they are usually more noticeable in adolescents and adults. Common signs include: Pink or red rash, starting on the face and spreading downward to the trunk and limbs Low-grade fever, typically under 38.5°C Swollen lymph nodes, especially behind the ears and at the back of the neck Mild joint pain, more common in adult women Headache Fatigue and malaise Mild conjunctivitis (red or irritated eyes) The rash usually lasts about three days, which is why rubella is sometimes referred to as “three-day measles.” The rash is not itchy in most cases and may fade without peeling or scabbing. In many cases, the illness is so mild that people do not realise they have it. However, the virus is still contagious during this time, making it important to stay cautious and informed, especially during outbreaks. Rubella in Pregnancy The most serious risk of German measles occurs when a pregnant woman contracts the virus, especially in the first 12 weeks of gestation. The rubella virus can cross the placenta and infect the developing foetus, leading to congenital rubella syndrome (CRS). CRS can cause a range of birth defects, including: Deafness Heart defects Cataracts and other eye abnormalities Intellectual disabilities Growth delays Liver and spleen damage Low birth weight or stillbirth The earlier in pregnancy the infection occurs, the greater the risk of severe outcomes. Because of this, rubella vaccination is strongly recommended for all individuals of childbearing age, and women are advised to wait at least one month after vaccination before conceiving. Global and Local Impact Worldwide, rubella has been largely eliminated in countries with robust immunisation programmes. In South Africa, rubella is not yet part of the routine Expanded Programme on Immunisation (EPI), although it may be introduced in future. Some private healthcare providers include the MMR vaccine (measles, mumps, and rubella) as part of childhood immunisation schedules. In regions where vaccination coverage is poor, rubella remains a leading cause of preventable congenital birth defects. Periodic outbreaks still occur, especially in communities with: Poor vaccination uptake Limited public health infrastructure High population movement Gaps in maternal screening Prevention The best protection against rubella is vaccination. The MMR vaccine is safe, effective, and provides long-lasting immunity. It is usually administered in two doses during childhood, but adults who are unsure of their immunisation status can receive a catch-up dose. Other prevention strategies include: Avoiding contact with people showing symptoms of rubella, especially if you are pregnant or immunocompromised Screening women of childbearing age for rubella immunity Staying home if you suspect you have rubella, to avoid spreading the virus Promoting vaccine education to reduce stigma and misinformation German Measles Rubella is a preventable disease. Ensuring high levels of immunity through public health education and access to vaccines is the key to eliminating outbreaks and protecting unborn babies. [Next: Causes of German Measles →]

German Measles Read More »

Microscopic view of the rubella virus causing German Measles

Causes of German Measles

Causes of German Measles The causes of German measles lie in the rubella virus — a contagious RNA virus that spreads through respiratory droplets and primarily affects the nose, throat, and lymph nodes. German measles, also known as rubella, is considered one of the most preventable childhood infections thanks to the availability of effective vaccines. However, it remains a risk in areas where immunisation coverage is low or inconsistent. Understanding how rubella spreads and what factors contribute to infection helps individuals and public health professionals take appropriate action to prevent outbreaks and reduce complications, especially for pregnant women and vulnerable populations. The Rubella Virus Rubella is caused by the rubella virus, a member of the Togaviridae family, under the genus Rubivirus. It is a single-stranded RNA virus that primarily targets epithelial cells in the upper respiratory tract. After initial replication, the virus enters the bloodstream and spreads throughout the body in a process called viraemia. This systemic spread allows the virus to reach: Lymphatic tissue Skin and mucous membranes Developing foetuses (via the placenta during pregnancy) The virus is highly contagious during the early stages of infection, even before symptoms become apparent. Transmission Pathways The rubella virus is spread from person to person through: Coughing or sneezing Close conversation or breathing shared air Touching contaminated surfaces, then touching the mouth or nose Vertical transmission from mother to baby during pregnancy In general, people with rubella are contagious from about 7 days before the rash appears until 7 days after. During this window, they can transmit the virus even if they don’t feel unwell or show visible symptoms. Incubation and Infectious Period After a person is exposed to the virus, there is typically an incubation period of 14 to 21 days. During this time, the virus replicates and spreads internally without any symptoms. A person becomes infectious about 7 days before symptoms emerge, particularly the rash, and may continue to shed the virus for a week afterward. Infants born with congenital rubella syndrome (CRS) can shed the virus in their urine or respiratory secretions for up to one year, making them a long-term source of infection if not carefully managed. Contributing Risk Factors While anyone who hasn’t been vaccinated or previously infected can contract rubella, some risk factors make transmission more likely or consequences more severe: 1. Lack of Immunisation Individuals who have not received the MMR vaccine or who missed childhood vaccinations are at greatest risk In many parts of Africa, including some regions of South Africa, rubella is not yet part of the public EPI, making vaccination status uneven 2. High Population Density Schools, universities, refugee camps, or overcrowded homes facilitate rapid spread Close contact in shared environments increases exposure to respiratory droplets 3. Travel and Migration Travellers from areas with low vaccination coverage may introduce rubella into communities with waning immunity Migrants or displaced populations may miss key childhood vaccinations 4. Pregnancy Without Immunity Women who are pregnant and not immune to rubella face the highest personal risk, as the infection can cause foetal malformations Prenatal screening is crucial to identify susceptibility before conception or early in pregnancy Congenital Rubella Transmission In pregnant individuals, the rubella virus can cross the placenta and infect the foetus. The earlier in pregnancy the infection occurs, the greater the chance of serious birth defects. Congenital rubella syndrome (CRS) is caused by: Direct viral damage to developing foetal organs Inflammation and reduced blood supply to foetal tissues Persistent infection that disrupts normal growth CRS remains one of the most serious consequences of rubella transmission and is entirely preventable through preconception screening and vaccination. Natural Immunity and Reinfection Once someone has had rubella, their body usually develops lifelong immunity. Reinfection is extremely rare, although mild reinfections have been documented, usually without significant symptoms. Immunity may come from: Natural infection MMR vaccination, which offers long-lasting protection Serology tests can check for rubella-specific IgG antibodies, which indicate immunity. This is especially useful for: Women planning pregnancy Healthcare workers Teachers and childcare providers Community and Global Spread Rubella tends to spread quietly because: Many cases are asymptomatic or very mild The contagious period begins before symptoms appear Individuals may not realise they are infected and continue their normal activities Global eradication efforts have made significant progress, but outbreaks still occur. The World Health Organization recommends maintaining vaccine coverage above 95% to prevent resurgence. In South Africa, there are ongoing discussions about incorporating rubella vaccination into the public programme to close existing gaps. Causes of German Measles Understanding the causes of German measles allows public health systems to build better vaccination strategies, inform at-risk populations, and prevent the devastating effects of congenital infection. [Next: Symptoms of German Measles→]

Causes of German Measles Read More »

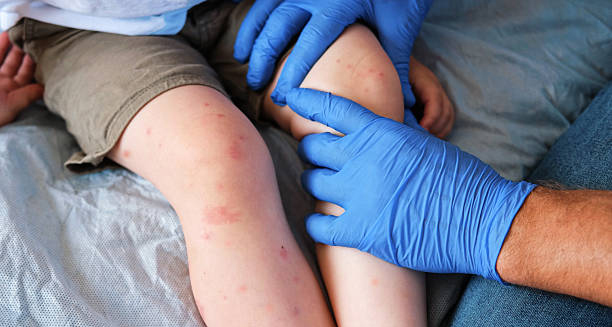
Child with rash on legs being examined by a doctor for symptoms of German measles

Symptoms of German Measles

Symptoms of German Measles The symptoms of German measles can vary significantly depending on age, immune status, and whether the person has previously been vaccinated. In many cases, especially in children, German measles—also known as rubella—presents with mild or even unnoticed symptoms. However, in adults, and particularly in pregnant women, symptoms can be more pronounced and carry serious consequences for the unborn child. Understanding the signs of rubella is critical for timely diagnosis, infection control, and—most importantly—prevention of transmission to those at risk. While often mistaken for other viral infections, rubella has distinct features that help differentiate it from illnesses such as measles, scarlet fever, or mild respiratory infections. Early Signs and General Onset The incubation period for rubella typically ranges from 14 to 21 days after exposure. During this time, the virus replicates in the respiratory tract and lymph nodes before entering the bloodstream. Individuals may begin to feel slightly unwell in the days leading up to visible symptoms. Common early symptoms include: Low-grade fever (usually under 38.5°C) Mild headache Sore throat Malaise or general fatigue Loss of appetite Red, irritated eyes (mild conjunctivitis) These early signs are non-specific and easily confused with other minor viral illnesses. However, they typically precede the hallmark rash by one or two days. The Rubella Rash One of the most identifiable symptoms of German measles is its characteristic rash, which usually appears first on the face, particularly around the hairline and behind the ears, before spreading downward to the trunk, arms, and legs. Key features of the rash include: Pink to red spots, often small and slightly raised Spreading in a downward pattern from the head Non-itchy or only mildly itchy in most cases Lasting approximately three days This is why rubella is sometimes referred to as “three-day measles.” The rash typically fades in the order it appeared and may disappear without any peeling or scabbing. Lymph Node Swelling A distinguishing symptom of German measles is lymphadenopathy, or swelling of the lymph nodes. This tends to affect: The back of the neck (posterior cervical nodes) Behind the ears (postauricular nodes) Under the jaw or in the armpits in some cases These swollen glands are often tender to the touch and may remain enlarged for several days after the rash resolves. Joint Pain and Arthritis In adolescents and adults, especially women, rubella may cause joint pain, swelling, and stiffness. This condition most often affects: Fingers and wrists Knees and ankles The joint symptoms can mimic mild arthritis and may last a week or more, even after the rash subsides. In some individuals, joint pain may be the only noticeable symptom of infection. Respiratory and Eye Involvement Other symptoms that may accompany rubella include: Mild cough Nasal congestion or runny nose Sore red eyes, which may be mistaken for conjunctivitis Photophobia, or light sensitivity, in more pronounced cases These upper respiratory symptoms are generally mild and self-limiting, resolving within a few days without treatment. Asymptomatic Infections It is estimated that up to 50% of people infected with the rubella virus may show no obvious symptoms at all, particularly in children. Despite the absence of symptoms, they can still spread the virus to others during the infectious period. This high rate of asymptomatic infection is one of the main reasons rubella can silently circulate within communities, making vaccination critical in controlling outbreaks. Duration and Recovery The typical rubella illness lasts around three to seven days, with the rash and fever usually resolving within that time frame. Fatigue or joint discomfort may linger slightly longer. Full recovery is expected in the vast majority of healthy individuals. There are rarely any lasting effects once the virus has run its course, provided the person is not pregnant or immunocompromised. Rubella in Adults Adults often experience a more pronounced illness than children. Symptoms such as: More noticeable joint involvement Greater fatigue Stronger immune responses, including swollen lymph nodes and fever Though still classified as a mild illness in most adults, the discomfort can be greater, and work or daily activities may be interrupted. Rubella in Pregnancy The most serious consequences of German measles occur when it infects a pregnant woman, particularly during the first trimester. Symptoms in the mother may be mild or even unnoticed, but the virus can cause: Miscarriage Stillbirth Congenital Rubella Syndrome (CRS) in the baby CRS can include a range of devastating outcomes, such as deafness, cataracts, heart defects, growth retardation, and intellectual disability. This is why rubella infection during pregnancy is considered a medical emergency, even if the symptoms seem trivial. Summary of Key Symptoms Symptom Frequency Facial/trunk rash Very common Swollen lymph nodes Common Low fever Common Sore throat Occasional Joint pain (adults) Fairly common Eye redness Mild and occasional Headache/fatigue Common Cough or runny nose Occasional     Symptoms of German Measles Recognising the symptoms of German measles allows for early intervention, helps reduce spread, and ensures that vulnerable individuals—particularly pregnant women—are protected. [Next: Diagnosis of German Measles →]

Symptoms of German Measles Read More »

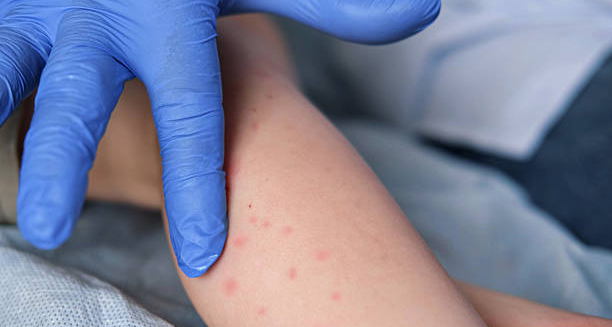
Close-up of a child's rash on the arm being examined for German measles diagnosis

Diagnosis of German Measles

Diagnosis of German Measles The diagnosis of German measles is based on a combination of clinical presentation, patient history, and—when necessary—laboratory testing. Since German measles (rubella) often presents with mild or non-specific symptoms, accurate diagnosis can be challenging, particularly in areas where the condition is rare due to widespread vaccination. However, in populations with lower vaccine coverage or among individuals with uncertain immunisation histories, healthcare providers must maintain a high index of suspicion—especially when exposed individuals include pregnant women. Clinical Diagnosis Rubella is most often diagnosed clinically, based on the typical progression of symptoms. Doctors will consider: Appearance and distribution of the rash Swollen lymph nodes, particularly behind the ears and in the neck Mild fever and joint pain, especially in adult women The timing of onset and how quickly symptoms spread Recent exposure to someone with a similar illness or history of travel to an outbreak area A thorough patient history is critical, particularly to determine: Vaccination status Possible contact with infected individuals Pregnancy status or plans to conceive The presence of postauricular and posterior cervical lymphadenopathy, combined with a facial rash that spreads to the body, is highly suggestive of rubella. Laboratory Confirmation Due to the overlap of rubella symptoms with other illnesses like measles, scarlet fever, roseola, and enteroviral rashes, laboratory testing is sometimes needed to confirm the diagnosis. This is especially true during outbreak investigations or in high-risk settings. 1. Rubella IgM Antibody Test Detects rubella-specific IgM antibodies in the blood IgM becomes detectable within 4–5 days after the rash appears A positive IgM result confirms recent infection 2. IgG Antibody Test Measures rubella-specific IgG antibodies Can distinguish between past infection or vaccination immunity Often used in prenatal screening or epidemiological studies A fourfold increase in IgG titres between paired samples collected two weeks apart can also indicate recent infection. 3. RT-PCR (Reverse Transcription Polymerase Chain Reaction) Detects rubella virus RNA in a throat swab, blood, or urine Used in settings where precise viral identification is required Most useful in early infection or in suspected congenital rubella cases RT-PCR is highly sensitive but may not be widely available outside specialised or reference laboratories. Differentiating Rubella from Other Conditions Many conditions present with similar symptoms to rubella, especially in children. A correct diagnosis must exclude: Measles – higher fever, more severe symptoms, and Koplik spots Scarlet fever – associated with streptococcal throat infection and “strawberry tongue” Roseola – fever precedes rash and typically affects infants Drug reactions – allergic rashes may resemble rubella but lack systemic signs In areas with widespread rubella vaccination, it is crucial to verify that a rash illness isn’t due to other more common viruses. Special Considerations for Pregnant Women If a pregnant woman presents with a rubella-like illness or is exposed to a confirmed case, she should undergo immediate testing to determine: Whether she is immune (IgG positive) Whether she has a current infection (IgM positive and/or viral RNA present) A confirmed rubella infection in pregnancy requires urgent obstetric and infectious disease consultation, as the risks to the developing foetus are significant. Even without symptoms, routine prenatal screening for rubella immunity is recommended to ensure protection before or during early pregnancy. Public Health Notification Rubella is a notifiable disease in many countries. Healthcare providers must report suspected or confirmed cases to public health authorities to: Prevent further transmission Track outbreaks Ensure protection of pregnant individuals who may have been exposed This surveillance allows for timely vaccination campaigns, educational efforts, and community containment measures. Screening and Immunity Testing Routine serological screening is recommended for: Women planning to conceive Healthcare workers and child-care staff People migrating from countries without universal vaccination programmes Seronegative individuals (those without protective antibodies) should be offered rubella vaccination unless contraindicated. Diagnosis of German Measles Knowing how to confirm the diagnosis of German measles helps clinicians act swiftly and protect high-risk populations from serious complications, particularly congenital infections. [Next: Treatment of German Measles→]

Diagnosis of German Measles Read More »

Young girl with cream on her face for German measles treatment

Treatment of German Measles

Treatment of German Measles The treatment of German measles is primarily supportive, as there is no specific antiviral medication that cures rubella. Since German measles (rubella) is usually a mild and self-limiting illness in children and adults, the focus of treatment is on alleviating symptoms, preventing complications, and reducing the spread of the virus — especially to pregnant individuals. Most people recover within a week with rest and basic care. However, special attention is required in certain cases, particularly among pregnant women, immunocompromised individuals, or those experiencing severe symptoms. General Treatment Approach Rubella is generally treated at home, and most individuals do not require hospitalisation unless complications arise. The goals of treatment are to: Reduce fever and discomfort Ease muscle aches or joint pain Encourage hydration and rest Prevent transmission to others Monitor for complications in high-risk groups Home Care and Symptom Relief The following strategies are commonly used to manage the symptoms of German measles: 1. Rest and Isolation Resting helps the body recover more efficiently Avoiding contact with others, especially pregnant women, during the infectious period is crucial Individuals should stay at home for at least 7 days after the rash appears to prevent further spread 2. Fever and Pain Management Paracetamol (acetaminophen) or ibuprofen can be used to relieve: Low-grade fever Headache Joint and muscle pain Aspirin should be avoided in children due to the risk of Reye’s syndrome 3. Fluids and Nutrition Encourage adequate fluid intake to prevent dehydration Light meals and comfort foods can help maintain energy In cases of sore throat or swollen glands, soft foods may be easier to consume 4. Eye Care If conjunctivitis or eye irritation is present: Use a clean, damp cloth to gently wipe discharge Avoid bright lights if photophobia is an issue Artificial tears may offer relief 5. Skin Comfort The rash typically causes minimal itching, but if discomfort occurs: A cool bath or non-perfumed moisturiser can soothe the skin Avoid scratching or using harsh soaps Treating Joint Pain Joint pain, particularly in adolescent girls and adult women, may persist for several days or even weeks. To manage this: Use non-steroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen Apply warm compresses to affected joints Encourage gentle movement and stretching In rare cases, persistent arthritis-like symptoms may develop. Long-term joint problems are uncommon, but follow-up may be needed if pain continues beyond several weeks. When to Seek Medical Help While most rubella cases are mild, medical attention should be sought if: Fever exceeds 38.5°C and persists beyond a few days Severe headache, stiff neck, or vomiting occurs (signs of possible meningitis) Persistent joint swelling interferes with mobility Bleeding or bruising without injury occurs, which may indicate a rare complication such as thrombocytopaenia Immediate care is also essential if: A pregnant woman is exposed to or diagnosed with rubella An individual has a weakened immune system, such as those undergoing cancer treatment or living with advanced HIV Treatment During Pregnancy Rubella infection during pregnancy requires specialist management. Unfortunately, there is no treatment that can prevent the virus from affecting the foetus once maternal infection occurs. Steps include: Serological confirmation of infection Serial ultrasound scans to monitor foetal development In some cases, amniocentesis may be performed to detect the virus in the amniotic fluid A multidisciplinary team including obstetricians, neonatologists, and infectious disease specialists will guide ongoing care If the infection occurs in the first trimester, the risk of severe birth defects is highest. Counselling may be offered to discuss the prognosis and potential outcomes. Avoiding Unnecessary Medication Since rubella is caused by a virus: Antibiotics are not effective unless a secondary bacterial infection develops Unnecessary medications should be avoided, particularly during pregnancy Patients are advised to avoid self-medicating and to consult a healthcare provider for guidance. Preventing Spread During Treatment Even if symptoms are mild, individuals must take steps to prevent further transmission: Remain isolated for 7 days after the rash begins Practise good hand hygiene and cough etiquette Avoid sharing utensils, towels, or bedding Inform employers, schools, and close contacts as necessary Anyone caring for someone with rubella—particularly healthcare or childcare workers—should confirm their immunisation status and take appropriate precautions. Long-Term Management Most people recover from rubella without lasting effects. No specific long-term treatment is required unless complications occur. Individuals who have had rubella gain lifelong immunity, but documentation of the illness or vaccination may be required in certain professions or healthcare settings. Treatment of German Measles The best protection remains prevention through vaccination, which reduces the need for treatment and stops the virus from circulating in communities. The treatment of German measles focuses on comfort, containment, and monitoring for rare complications. With early detection and proper care, recovery is typically swift and complete. [Next: Complications of German Measles →]

Treatment of German Measles Read More »

Complications of German Measles

Complications of German Measles

Complications of German Measles The complications of German measles are uncommon in the general population but can be extremely serious in specific groups, particularly pregnant women and individuals with compromised immune systems. German measles, or rubella, is typically a mild illness in healthy children and adults. However, under certain conditions, it can lead to long-term health consequences, disability, or even death. Understanding the possible complications allows healthcare providers and the public to act swiftly in managing infection, initiating treatment where necessary, and prioritising prevention. Congenital Rubella Syndrome (CRS) The most severe and well-documented complication of rubella is congenital rubella syndrome (CRS), which occurs when a pregnant woman becomes infected, especially during the first trimester. The rubella virus crosses the placenta and disrupts the development of the foetus. Potential outcomes of CRS include: Sensorineural deafness (most common defect) Congenital heart defects, such as patent ductus arteriosus or pulmonary artery stenosis Cataracts and other eye abnormalities (e.g. retinopathy) Microcephaly and intellectual disabilities Liver and spleen damage Low birth weight or growth restriction Bone lesions Endocrine disorders, including diabetes and thyroid dysfunction The risk of CRS is highest if infection occurs: Within the first 12 weeks of pregnancy – risk exceeds 80% Between 13–16 weeks – moderate risk After 20 weeks – risk significantly declines, though not eliminated Babies born with CRS may require lifelong care, including hearing aids, heart surgeries, special education, and physical therapy. In severe cases, stillbirth or neonatal death may occur. Miscarriage and Stillbirth Rubella infection during pregnancy increases the risk of: Spontaneous abortion Foetal death in utero Preterm labour These outcomes are particularly likely when infection occurs during early pregnancy and are part of the reason rubella is classified as a high-priority illness in maternal care settings. Encephalitis Rubella can, in rare cases, cause inflammation of the brain (encephalitis). Symptoms include: Severe headache Altered consciousness or confusion Seizures Neurological deficits Rubella-related encephalitis affects approximately 1 in 6,000 adult cases and is more common in adult males. While rare, it can be fatal or lead to long-term disability. Thrombocytopaenic Purpura Another rare but serious complication is thrombocytopaenic purpura, a condition where the number of platelets in the blood falls dangerously low. This can result in: Unexplained bruising Nosebleeds or gum bleeding Blood in urine or stool This complication is more commonly seen in children and usually resolves with supportive care, but in some cases, medical intervention is required to stabilise the blood clotting process. Arthralgia and Arthritis Joint pain is a common symptom, especially in adult women, but in some cases, it may develop into persistent arthritis-like symptoms, including: Swelling and stiffness in multiple joints Reduced mobility Chronic discomfort Although this condition is usually self-limiting, some individuals may experience prolonged symptoms lasting weeks or months. Otitis Media and Respiratory Complications While rubella primarily affects the skin and lymphatic system, secondary complications can include: Ear infections (otitis media) Bronchitis or mild pneumonia These are more common in young children or individuals with pre-existing respiratory issues but are usually treatable. Impact on Public Health Rubella outbreaks can cause considerable disruption, especially when they: Affect schools, childcare centres, or maternity wards Expose unvaccinated pregnant women to infection Trigger travel advisories or mass immunisation campaigns As rubella often causes mild or unnoticed symptoms, identifying the source of an outbreak can be challenging. This underscores the need for routine immunisation and public health vigilance. Psychological and Social Complications Being diagnosed with rubella during pregnancy can be distressing and may lead to: Anxiety and fear over foetal outcomes Depression or guilt Difficult reproductive decisions, including termination of pregnancy in severe cases Parents of children born with CRS may experience: Financial strain Caregiver fatigue Social isolation Access to mental health support and community resources is crucial for families navigating these challenges. Preventing Complications Most complications of rubella are entirely preventable through: Routine MMR vaccination in childhood Booster doses or catch-up immunisation for adults Preconception screening and vaccination for women of childbearing age Timely diagnosis and public health response during outbreaks Complications of German Measles Maintaining high vaccination rates and proactive healthcare policies remains the best defence. Recognising and managing the complications of German measles ensures better outcomes for individuals and communities, and reinforces the importance of sustained global vaccination efforts. [Next: Back to Overview →]

Complications of German Measles Read More »

Child with rubella rash on chest being examined for complications

Genital Warts

Genital Warts Genital warts are one of the most common types of sexually transmitted infections (STIs), caused by certain strains of the human papillomavirus (HPV). These small, fleshy growths appear on or around the genital and anal areas and can affect anyone who is sexually active. Although genital warts are typically painless, they may cause itching, discomfort, and emotional distress, particularly due to their location and appearance. In South Africa and globally, genital warts remain a widespread public health concern. They are most commonly diagnosed in individuals aged 17 to 33 and are especially prevalent among those with multiple sexual partners or inconsistent use of protection. While they are not dangerous in most cases, some strains of HPV associated with genital warts have been linked to other health complications, particularly in women. Because of the visible nature of the condition and the association with sexual activity, genital warts are often surrounded by stigma. This can lead to shame, anxiety, and a reluctance to seek medical help. But it’s important to understand that they are a medical condition, not a moral failing — and they are both manageable and treatable. What Do Genital Warts Look Like? Genital warts can vary in appearance. They may be: Small, skin-coloured or grey growths Raised or flat Smooth or cauliflower-like in texture Found singly or in clusters Moist or dry, depending on their location In men, genital warts most commonly appear on: The shaft or tip of the penis The scrotum Around or inside the anus The groin or upper thighs In women, they may appear on: The vulva or around the vaginal opening The cervix (inside the vagina, requiring a speculum to detect) The anus and surrounding skin The upper thighs or groin area They can also occur in the mouth or throat following oral sex with an infected partner. Who Is at Risk? Anyone who is sexually active can contract genital warts, but some factors increase the likelihood: Unprotected sex with multiple partners Starting sexual activity at an early age A weakened immune system (e.g. from HIV or certain medications) Previous or existing STI infections Smoking, which reduces the body’s ability to fight off HPV Warts can be passed between heterosexual and same-sex partners, and even through skin-to-skin genital contact where penetration does not occur. This means condoms, while helpful, do not provide 100% protection. How Long After Exposure Do Warts Appear? HPV has a long incubation period, so genital warts can appear weeks, months, or even years after exposure. Some people carry the virus without ever developing visible warts, while others might have a sudden outbreak without warning. This unpredictability makes it difficult to determine exactly when the infection was contracted or who passed it on, which can complicate relationships and lead to unnecessary blame. Are Genital Warts Dangerous? In most cases, genital warts are benign and do not cause long-term health issues. However, the HPV types that cause genital warts (mainly types 6 and 11) are different from the high-risk HPV types (like 16 and 18) that are linked to cancers of the cervix, anus, penis, and throat. That said, the presence of genital warts indicates that a person has been exposed to HPV, so it’s important to: Have regular cervical smear (Pap) tests if you’re a woman Consider HPV vaccination, especially if you’re under age 26 Seek regular check-ups if you are immunocompromised Emotional and Psychological Impact Though not physically dangerous, genital warts can have a significant emotional impact. Individuals may experience: Embarrassment or shame Anxiety about transmitting the virus to partners Fear of rejection or being stigmatised Guilt, especially when warts appear during a monogamous relationship It’s essential to understand that HPV is extremely common — most people will contract it at some point in their lives. Genital warts do not reflect on a person’s hygiene, character, or behaviour. They are a treatable condition that many people experience and overcome. Prevention Strategies Preventing genital warts involves reducing exposure to HPV: Use condoms or dental dams during all forms of sexual contact Limit the number of sexual partners and maintain open, honest conversations about sexual health Get vaccinated — the HPV vaccine (such as Gardasil) protects against the strains most likely to cause genital warts and HPV-related cancers Attend regular sexual health screenings if sexually active Although no prevention method is completely foolproof, combining multiple strategies significantly lowers risk. When to See a Doctor for Genital Warts You should seek medical advice if you: Notice any new growths, lumps, or bumps in the genital or anal area Experience itching, bleeding, or discomfort during sex Are unsure about whether a skin lesion might be a wart Have been informed that a current or past partner has HPV or genital warts Early intervention allows for easier treatment and reduces the risk of transmission. If warts are located inside the body (e.g. on the cervix or inside the anus), they may only be detected through a pelvic exam or anoscopy. Genital warts can be frustrating, but with proper diagnosis, treatment, and emotional support, most people are able to manage the condition effectively and return to a normal, healthy sex life. [Next: Causes of Genital Warts →]

Genital Warts Read More »

Scroll to Top