
Mental Matters

Huntington’s Disease

Graphic representation of Huntington’s disease with a stylised brain illustration and bold text.

Huntington’s Disease – Overview

Huntington’s disease is a progressive and inherited neurodegenerative disorder that affects the brain’s ability to control movement, cognition, and behaviour. Huntington’s disease happens because of a mutation in the HTT gene. This causes slow damage to nerve cells in parts of the brain like the basal ganglia and cerebral cortex. As the damage grows, people lose motor skills, have emotional problems, and experience cognitive decline. The disease usually starts in middle age but can sometimes begin in childhood. It worsens over 10 to 25 years. Genetic Cause and Inheritance The disease is named after George Huntington, who first described it in 1872. Huntington’s disease is autosomal dominant. This means a person needs only one faulty gene from a parent to develop the disease. Each child of an affected parent has a 50% chance of inheriting the mutation. The HTT gene, on chromosome 4, has a CAG repeat section. People with Huntington’s have an abnormally high number of repeats. More repeats usually mean earlier symptoms and faster worsening. Main Symptoms and Their Progression Huntington’s disease symptoms fall into three groups: motor, cognitive, and psychiatric. Motor symptoms often start small. People may have involuntary movements called chorea, clumsiness, or coordination problems. These movements get worse and make walking, talking, and swallowing very hard. Eventually, full-time care is needed. Cognitive symptoms appear early and get worse slowly. People find it harder to plan, organise, multitask, or concentrate. Memory stays okay at first but declines later. Language problems also grow, making communication difficult. Later, dementia may develop, but it looks different from Alzheimer’s disease. Psychiatric symptoms are common and may show before movement problems. Depression often appears early. Other issues include irritability, anxiety, lack of interest (apathy), obsessive thoughts, and sometimes psychosis. These symptoms can hurt relationships and daily life, even before diagnosis. Variations in Age of Onset Symptoms usually start between ages 30 and 50. Some people show signs much earlier or later. Juvenile Huntington’s disease begins before age 20 and accounts for 5–10% of cases. It progresses faster, with stiffness, learning problems, and seizures more common than chorea. Late-onset Huntington’s is rare but can happen, often in families with milder gene expansions. Treatment and Support No cure exists for Huntington’s disease. Treatment focuses on managing symptoms and improving quality of life. Medicines like tetrabenazine help control chorea. Antidepressants and antipsychotics treat mental health symptoms. Speech, occupational, and physical therapy help maintain function and independence. Genetic counselling is vital for people at risk or planning families. Emotional and Social Impact Huntington’s disease affects whole families, not just the person with the disease. Many live with anxiety and hard decisions about genetic testing for years. Symptoms strain relationships, and caregivers face big challenges. Support groups, mental health services, and long-term care ease the burden. Global Impact and Research Worldwide, Huntington’s disease affects 3 to 10 people per 100,000. It is more common in people of European descent but occurs everywhere. Genetic testing has improved diagnosis and family planning. Research on gene-silencing and neuroprotective treatments offers hope. New trials using RNA interference and CRISPR gene-editing may change the future. Awareness and Stigma Awareness has grown due to advocacy and public cases. This helps with funding and better care. However, stigma remains, especially when psychiatric symptoms appear early, causing misdiagnosis or delayed help. People in early stages may face discrimination or stop activities due to fear or misunderstanding. Educators and employers should know that symptoms come from brain changes, not laziness or unwillingness. Early support can reduce these problems. Life Changes After Diagnosis A Huntington’s diagnosis often marks a big life shift. Once symptoms appear and genetic testing confirms the mutation, people face managing a serious illness and the knowledge they might pass the gene to children. Support services, including counselling and peer groups, help patients and families cope with this reality. Summary of Huntington’s Disease Overview In conclusion, Huntington’s disease is a complex inherited brain disorder affecting body, mind, and emotions. While it is fatal, early diagnosis, good care, and emotional support can improve life quality. Science is making progress, giving hope for future treatments. Until then, a team approach and kind care are the best help for those living with Huntington’s disease. [Next: Causes of Huntington’s Disease →]
Huntington’s Disease – Overview Read More »

Causes of Huntington’s Disease

Causes of Huntington’s Disease

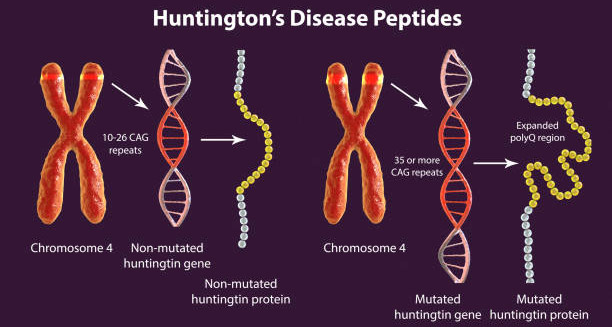
The causes of Huntington’s disease are entirely genetic in nature, making this neurodegenerative condition both unique and devastating. Huntington’s disease happens because of a single inherited mutation. It is an autosomal dominant disorder. This means if one parent has the faulty gene, each child has a 50% chance of getting the disease. This pattern causes the disease to show up in many family generations, often leading to a sad cycle of decline. The Genetic Mutation Behind Huntington’s Disease The main cause is a change in the HTT gene on chromosome 4. This gene makes a protein called huntingtin. Huntingtin is important for nerve cells, especially in the brain, to work well. In people without Huntington’s, the HTT gene has a DNA sequence where three nucleotides — cytosine (C), adenine (A), and guanine (G) — repeat 10 to 35 times. This sequence is called a CAG trinucleotide repeat. In people with Huntington’s disease, this CAG part repeats 36 times or more. The number of repeats affects how bad the disease gets and when it starts. If the repeats are between 36 and 39, some may or may not show symptoms. When repeats reach 40 or more, the disease will almost always develop. How the Mutation Causes Damage The long CAG repeats make the huntingtin protein abnormally long and weak. This broken protein splits into pieces that build up inside nerve cells. This mainly happens in brain areas that control movement, behavior, and thinking, like the basal ganglia and cerebral cortex. These pieces stop normal cell processes, leading to nerve cell death, brain shrinkage, and the worsening symptoms of Huntington’s disease. One worrying feature is called anticipation. This means the number of CAG repeats can grow larger when passed from parent to child, especially from the father. Because of this, symptoms may appear earlier and worsen faster in the next generation. For example, a parent with 42 repeats might pass on a gene with 50 or more repeats, causing a more severe and early form called juvenile-onset Huntington’s disease. Inheritance and Risk Because the mutation is dominant, inheriting one faulty HTT gene from either parent causes the disease. The disease does not skip generations unless the faulty gene is not passed on. People who inherit two normal HTT genes — one from each parent — will not get the disease and cannot pass it on. Causes of Huntington’s Disease and Environment Environmental factors like diet, exercise, smoking, or pollution do not cause Huntington’s disease. But once the disease is present, lifestyle and care can affect how symptoms are managed and improve quality of life. No known outside factor can trigger or stop the genetic mutation causing Huntington’s disease. Genetic Modifiers and Disease Progression Scientists study other genes called genetic modifiers. These may change how fast the disease moves or when symptoms start. These modifiers do not cause Huntington’s but may explain why people with the same CAG repeats have different disease speeds. Genetic Testing and Counseling Because inheritance is certain in affected families, genetic testing is very important. A simple blood test counts the number of CAG repeats in the HTT gene, giving a very accurate diagnosis. However, testing brings hard emotional and ethical choices, especially for those with no symptoms but who are at risk. Many people struggle with whether to get tested, knowing a positive result affects mental health, family planning, and insurance in some places. To help with these choices, genetic counseling is strongly advised. Counselors explain Huntington’s disease, risks of passing it on, and reproductive options. They also offer support to prepare for the emotional effects of knowing the likely future. Reproductive Options People planning families may choose preimplantation genetic diagnosis (PGD). PGD tests embryos made through IVF for the HTT mutation before implantation. Parents can then select embryos without the faulty gene. Prenatal testing is another option, but positive results can lead to difficult decisions. Some countries have legal limits on abortion, which may complicate this testing. Research and Hope for the Future We now fully understand the causes of Huntington’s disease, but we cannot yet fix or cure the gene mutation. Still, researchers work on treatments targeting the genetic cause. These include gene-silencing therapies like RNA interference and CRISPR gene-editing. These aim to lower or block the harmful huntingtin protein. Though still experimental, these treatments offer hope for future generations. Social Impact and Awareness Awareness campaigns and support groups have helped research, testing access, and reduced stigma. However, the emotional and social effects of Huntington’s disease are still very strong. Many people live for years knowing they carry the faulty gene before symptoms appear, causing anxiety, depression, and tough talks with family. Summary of Causes of Huntington’s Disease In conclusion, the causes of Huntington’s disease come from a genetic mutation in the HTT gene. This mutation leads to a harmful protein that damages brain cells. The disease passes from generation to generation and affects people worldwide. While there is no current cure or way to stop it, knowing the genetic cause allows for early diagnosis, smart family planning, and ongoing research into new treatments. [Next: Symptoms of Huntington’s Disease →]

Causes of Huntington’s Disease Read More »

Symptoms of Huntington’s Disease

Symptoms of Huntington’s Disease

The symptoms of Huntington’s disease usually appear gradually and progress over time as the condition damages specific areas of the brain. Because the disease affects both movement and mental function, its symptoms vary widely from person to person. Most people develop symptoms between ages 30 and 50, although earlier or later onset is possible. The condition typically worsens over 10 to 25 years, eventually leading to complete loss of independence. There are three main categories of symptoms: These symptoms may develop in any order, and in some cases, behavioural changes appear long before movement problems begin. Motor Symptoms Motor symptoms are often the first signs of Huntington’s disease. The most recognisable feature is chorea — sudden, involuntary movements affecting the face, arms, and legs. Initially, these may look like restlessness or fidgeting, but they worsen over time and interfere with walking, eating, and speaking. Other motor symptoms include: As the disease progresses, movements become slower and stiffer, leading to bradykinesia (slowness) and dystonia (muscle rigidity). In advanced stages, most people require full assistance for daily activities. Cognitive Symptoms Cognitive decline in Huntington’s disease primarily affects executive function — the brain’s ability to plan, organise, and control behaviour. Unlike Alzheimer’s, memory loss is not the first symptom but develops later. Common cognitive issues include: Eventually, cognitive decline leads to confusion, disorientation, and an inability to manage daily tasks like finances or medication. Psychiatric and Emotional Symptoms Psychiatric symptoms are common and may appear before motor signs. These emotional changes often have the most significant impact on quality of life. The most frequent psychiatric symptoms are: Severe psychiatric symptoms such as psychosis, hallucinations, or delusions may occur, especially in juvenile or late stages. Variability and Progression Symptom progression varies widely. Higher CAG repeat counts in the HTT gene usually mean earlier onset, but severity and progression still vary. Impact on Daily Life As symptoms worsen, individuals lose independence in work, driving, and self-care. Speech issues, cognitive decline, and mood changes often cause social withdrawal and strain family relationships. Caregivers face high levels of stress, especially in later stages when full-time care is required. Palliative care and community support are essential for maintaining dignity and comfort. Early Detection is Key Early recognition of Huntington’s symptoms enables proactive treatment and planning. While there is no cure, therapies such as physiotherapy, speech therapy, occupational support, and psychiatric care help maintain function and improve quality of life. [Next: Diagnosis of Huntington’s Disease →]

Symptoms of Huntington’s Disease Read More »

Diagnosis of Huntington’s disease with medical tools and brain model

Diagnosis of Huntington’s Disease

The diagnosis of Huntington’s disease involves clinical assessments, family history analysis, neurological evaluations, and genetic testing. Because the condition is hereditary, diagnosis often begins when symptoms appear in someone with a family history of the disorder. For individuals without known genetic risk, medical evaluations and testing can still confirm the condition. Early diagnosis matters. It gives individuals and families time to plan, begin treatment, and access support before symptoms worsen. Clinical Evaluation The first step in diagnosing Huntington’s disease is a neurological examination. Doctors look for: Emotional symptoms such as depression, anxiety, and mood swings are also assessed. Because symptoms can mimic other conditions (e.g., Parkinson’s disease or psychiatric disorders), accurate evaluation is essential. Family members often provide observations about behavioural or memory changes to help clarify the clinical picture. Medical and Family History Huntington’s disease follows an autosomal dominant inheritance pattern, meaning a 50% chance of transmission if one parent carries the gene. Clinicians review family medical history to identify patterns of neurological decline. If family history is unclear — for example, in adoption cases or early parental deaths — doctors may recommend genetic testing based on symptoms alone. Neurological and Cognitive Testing Doctors may perform structured tests to measure: These tests do not confirm Huntington’s disease on their own but help establish a baseline for symptom progression. Psychiatric Assessment Mental health symptoms often appear early and can resemble unrelated psychiatric disorders. A psychiatric evaluation checks for depression, irritability, obsessive behaviour, or psychosis, ensuring accurate diagnosis and avoiding mislabeling the condition as a primary mental illness. Brain Imaging Brain scans such as MRI or CT can reveal changes in the caudate nucleus and putamen — brain regions most affected by Huntington’s disease. Imaging helps rule out other causes but cannot replace genetic confirmation. Genetic Testing – The Definitive Diagnosis A blood test counts the number of CAG repeats in the HTT gene: Genetic testing is highly accurate but carries emotional and ethical implications. Genetic counselling is essential before and after testing to discuss results, family planning, and support options. Prenatal and Preimplantation Testing Families with a known history of Huntington’s can opt for: These options help break the cycle of transmission but require careful ethical consideration and expert guidance. Challenges in Diagnosis Diagnosis can be delayed if symptoms are subtle, mimic other conditions, or occur in rare juvenile or late-onset forms. Fear, stigma, or denial may also prevent individuals from seeking testing. Public education and improved access to genetic services remain essential. Key Takeaway The diagnosis of Huntington’s disease relies on a combination of clinical evaluation and genetic testing, supported by counselling and family involvement. While genetic testing provides certainty, the emotional weight of knowing one’s status makes professional support critical. [Next: Treatment of Huntington’s Disease →]

Diagnosis of Huntington’s Disease Read More »

Conceptual illustration of Huntington’s disease treatment with brain functions and support

Treatment of Huntington’s Disease

The treatment of Huntington’s disease focuses on managing symptoms and improving quality of life. While there is no cure, a combination of medication, therapy, and supportive care can help individuals maintain independence for as long as possible. Because the disease progresses gradually, treatment must adapt over time. A multidisciplinary approach — involving neurologists, psychiatrists, physiotherapists, speech therapists, and dietitians — is considered the gold standard. Medications for Motor Symptoms Chorea, the involuntary jerking movements, is one of the main symptoms of Huntington’s disease. Treatment options include: Antipsychotics (e.g., haloperidol, olanzapine, risperidone) can help control chorea when behavioural symptoms coexist. However, these drugs must be used carefully to avoid worsening rigidity. For stiffness and muscle spasms, medications like baclofen, benzodiazepines, or amantadine may provide relief. Managing Emotional and Psychiatric Symptoms Psychological symptoms are common and require prompt attention. Treatment may include: Therapies such as Cognitive Behavioural Therapy (CBT), counselling, and support groups help individuals and families cope with emotional challenges. Physical and Occupational Therapy Physiotherapy helps maintain mobility, balance, and strength, reducing fall risk. Occupational therapists assist with: Speech therapy supports communication and swallowing, introducing assistive tools when speech declines. Nutritional Support Weight loss is common due to increased energy use and swallowing problems. Strategies include: Regular monitoring by a dietitian is essential throughout the disease. Emerging and Experimental Treatments Research offers hope for slowing or stopping disease progression. Key areas include: These treatments are still in clinical trials, but progress is promising. Long-Term and Palliative Care Advanced stages require full-time care. Planning should cover: Hospice services may be needed when swallowing difficulties, severe cognitive decline, or recurrent infections develop. The Role of Support Networks Emotional and practical support is as vital as medical care. Families benefit from: Summary The treatment of Huntington’s disease aims to control symptoms, maintain independence, and support emotional wellbeing. Although no cure exists yet, ongoing research brings hope for therapies that may slow or even halt the disease in the future. [Next: Complications of Huntington’s Disease →]

Treatment of Huntington’s Disease Read More »

Elderly man struggling to swallow due to complications of Huntington’s disease

Complications of Huntington’s Disease

The complications of Huntington’s disease develop gradually and affect nearly every aspect of life — from movement and cognition to emotional health and social relationships. These complications place a heavy burden on both individuals and their caregivers. Understanding them is essential for planning care and improving quality of life. Movement-Related Complications One of the most noticeable complications of Huntington’s disease is chorea — involuntary, jerky movements. At first, these movements are mild, but over time they become severe, leading to: As mobility declines, the risk of fractures and injuries increases significantly. Swallowing and Nutrition Problems Difficulty swallowing (dysphagia) often appears in the later stages. Patients may choke on food or liquids, which can cause aspiration pneumonia — a leading cause of death in Huntington’s disease.Other related issues include: In advanced stages, some patients require feeding tubes for adequate nutrition. Cognitive Decline Cognitive problems often start early and worsen over time. These include: As cognition declines, individuals lose the ability to manage finances, healthcare, and personal care without assistance. Mental Health Complications Mental health issues are extremely common. They can appear even before physical symptoms. The most frequent include: Suicide risk is especially high in early stages when patients fully understand their diagnosis. Continuous psychological support is essential. Speech and Communication Issues Huntington’s disease affects muscles used for speaking, leading to dysarthria (slurred speech). Over time, speech becomes hard to understand, causing frustration and social withdrawal. Eventually, patients may need communication devices. Other Common Complications Social and Family Challenges The complications of Huntington’s disease extend beyond health. They include: Managing Complications A multidisciplinary approach offers the best care. Teams often include neurologists, psychiatrists, dietitians, therapists, and social workers. Regular check-ups, nutritional support, and therapy can help manage complications and maintain dignity for as long as possible. Future Outlook Research is ongoing to reduce complications and slow disease progression. Promising approaches include: While no cure exists yet, these treatments may transform Huntington’s care in the future. In summary: The complications of Huntington’s disease affect every area of life — physical, emotional, and social. Recognising these issues early and planning ahead with professional support can ease the journey for both patients and families. [Next: Outlook for Huntington’s Disease →]

Complications of Huntington’s Disease Read More »

Silhouette of child fading into birds symbolising the outlook of Huntington’s disease

Outlook for Huntington’s Disease

The outlook for Huntington’s disease depends on its progressive nature, genetic origin, and symptom complexity. While new research offers hope for future treatments, the current outlook involves a gradual decline in physical, mental, and emotional abilities. However, early care, emotional support, and a strong healthcare team can make a big difference in quality of life. Life Expectancy and Disease Progression People with Huntington’s disease usually live 15–20 years after symptoms start. This varies based on age at onset, overall health, and care quality. Juvenile Huntington’s disease, which starts before age 20, progresses faster and shortens life expectancy. The disease has three main stages: Complications like pneumonia, malnutrition, and infections are the most common causes of death—not the disease itself. Good palliative care helps maintain comfort and dignity in advanced stages. Emotional and Psychological Impact The outlook for Huntington’s disease also includes emotional challenges. Learning you have the disease—or could pass it on—can cause fear, guilt, and depression. Loss of independence and changing relationships add to the burden. Supportive care helps. Counselling, therapy, and support groups improve emotional health. Family therapy and genetic counselling guide decision-making and help relatives cope. Predictive Genetic Testing Huntington’s is unique because genetic testing can predict its onset. A child of an affected parent has a 50% chance of inheriting the gene. Predictive testing reveals this risk before symptoms appear. For some, knowing brings anxiety. For others, it offers control and planning opportunities—such as career choices, financial security, and family planning. Options like preimplantation genetic diagnosis (PGD) help parents avoid passing on the mutation. Treatments and Prognosis There is no cure, but treatments improve quality of life and slow symptom progression. Medicines control chorea, depression, and mood swings. Therapies—physical, occupational, and speech—help maintain function. A strong care plan can keep people independent for years. Teams often include dietitians, social workers, and palliative specialists. Planning ahead for advanced stages ensures dignity and reduces stress for families. Research and Future Hope Research is bringing hope for better treatments: While no cure exists yet, trials show promise. Global research efforts may transform the outlook for Huntington’s in the coming decades. The Role of Support Networks Strong support systems improve outcomes. Multidisciplinary care teams, financial help, and advocacy groups reduce stress and improve independence. Organisations like the Huntington’s Disease Society of America, European Huntington Association, and national support networks provide education, resources, and emotional guidance. A Realistic But Hopeful Perspective Huntington’s disease remains serious, but the future is brighter than before. Advances in medicine, emotional support, and research offer patients and families a path filled with dignity and meaningful moments. Awareness is growing, and care resources are expanding. With continued progress, tomorrow’s outlook for Huntington’s disease could be far more hopeful than today. [Next: Back to Overview →]

Outlook for Huntington’s Disease Read More »

Scroll to Top



