Mental Matters

Health Conditions

Find information on various health conditions affecting people of all ages. This category covers causes, symptoms, diagnosis, and management options for physical illnesses and chronic diseases. Get insights to help you understand different health challenges and make informed decisions about your wellbeing.

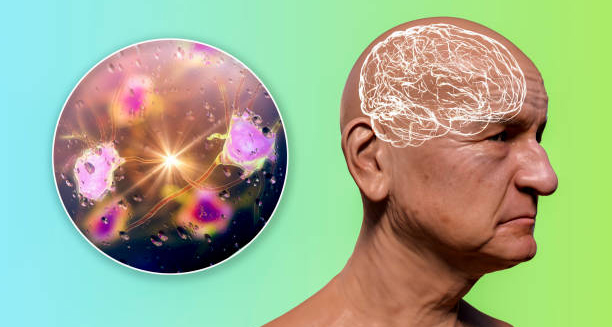
Illustration of an elderly man with neural activity and brain degeneration linked to frontotemporal dementia

Causes of Frontotemporal Dementia

Causes of Frontotemporal Dementia The causes of frontotemporal dementia are related to abnormal deposits of proteins in the brain that damage nerve cells and disrupt normal brain function. Frontotemporal dementia is believed to result from a combination of genetic, molecular, and environmental factors. Protein Buildup in the Brain In FTD, brain cells die because of the accumulation of harmful proteins, including: Tau proteins – linked to neurodegeneration and cell damage TDP-43 proteins – commonly found in both FTD and motor neurone disease (ALS) These proteins interfere with cell communication and lead to brain shrinkage, particularly in the frontal and temporal lobes As the cells in these areas die off, the brain loses its ability to regulate behaviour, language, and movement. Genetic Mutations Around one-third of FTD cases are inherited, meaning the condition runs in families. Mutations in the following genes are known to cause familial FTD: MAPT – affects tau protein production GRN – linked to abnormal progranulin levels C9orf72 – also associated with motor neurone disease If there is a family history of early-onset dementia or neurological decline, genetic testing and counselling may be offered. Sporadic Cases In most people with FTD, there is no known genetic cause. These are referred to as sporadic cases, and the exact triggers remain unclear. Researchers believe that lifestyle factors, inflammation, or cumulative damage may play a role. Risk Factors Age – FTD usually develops between 45 and 65 years Family history – particularly in cases with inherited gene mutations Previous head trauma – long-term effects of repeated injury may contribute Unlike Alzheimer’s disease, FTD is not linked to smoking, heart disease, or high blood pressure in the same way. However, overall brain health is still important in delaying onset and managing progression. Causes of Frontotemporal Dementia Understanding the causes of frontotemporal dementia helps inform care strategies, identify those at higher risk, and guide research into treatments and potential cures. [Next: Symptoms of Frontotemporal Dementia →]

Causes of Frontotemporal Dementia Read More »

Illustration of elderly person with confused expression and brain symbol showing damage

Symptoms of Frontotemporal Dementia

Symptoms of Frontotemporal Dementia The symptoms of frontotemporal dementia depend on which areas of the brain are most affected. Frontotemporal dementia usually causes noticeable changes in personality, behaviour, or language before memory problems appear. These symptoms can be distressing and confusing, both for the person with the condition and for those around them. Behavioural Variant FTD (bvFTD) This is the most common form of FTD. Symptoms include: Apathy or lack of motivation Socially inappropriate behaviour, such as rudeness or impulsiveness Loss of empathy or emotional warmth Compulsive or repetitive actions Poor judgement and risk-taking Changes in eating habits, such as overeating or craving sweet foods These symptoms may be mistaken for depression, bipolar disorder, or midlife crisis in the early stages. Language Variants (Primary Progressive Aphasia) There are two main types: Semantic variant – difficulty understanding words or recognising familiar people/objects Non-fluent variant – slow, effortful speech with poor grammar People with language-based FTD may struggle to: Name everyday objects Follow conversations Express themselves clearly Read or write fluently Despite language problems, memory and thinking skills may remain relatively intact in the early stages. Motor Symptoms Some types of FTD overlap with motor neurone disease (ALS) or conditions like progressive supranuclear palsy (PSP) and corticobasal degeneration (CBD). These can cause: Muscle weakness Difficulty swallowing or speaking Problems with balance or coordination Muscle stiffness or tremors Emotional and Social Changes Lack of emotional response to major events Flat facial expression or limited body language Difficulty recognising other people’s emotions (loss of emotional insight) Later Stages As the disease progresses, symptoms become more widespread and may include: Memory problems Incontinence Immobility Increased dependence on carers Symptoms of Frontotemporal Dementia Identifying the symptoms of frontotemporal dementia early allows families to plan for the future, access support, and explore treatment options that may help manage the condition. [Next: Diagnosis of Frontotemporal Dementia→]

Symptoms of Frontotemporal Dementia Read More »

Digital illustration of brain highlighting frontotemporal lobe damage

Diagnosis of Frontotemporal Dementia

Diagnosis of Frontotemporal Dementia The diagnosis of frontotemporal dementia can be challenging due to the wide variety of symptoms and the fact that frontotemporal dementia often mimics psychiatric disorders or other forms of dementia. Accurate and early diagnosis is essential to ensure appropriate treatment, planning, and support for the individual and their family. Clinical Evaluation The diagnostic process begins with: A detailed history of symptoms, including changes in behaviour, language, or movement Information from close family members or caregivers, who may notice changes the individual doesn’t Neurological and cognitive tests, to assess memory, reasoning, speech, and behaviour patterns Because early-stage FTD doesn’t usually affect short-term memory, standard dementia screening tools may not always detect it. Brain Imaging To confirm the diagnosis and rule out other causes, doctors may order imaging tests such as: MRI (Magnetic Resonance Imaging) – can reveal shrinkage in the frontal and temporal lobes CT scan – may show structural changes in the brain PET or SPECT scans – show how the brain is functioning and highlight areas of reduced activity, even before major shrinkage is visible These scans help differentiate FTD from other conditions like Alzheimer’s disease or vascular dementia. Neuropsychological Testing A neuropsychologist may carry out: Detailed assessments of speech, language, and executive function Tests to evaluate the ability to plan, organise, or interpret social cues Emotional recognition tests, particularly for individuals with behavioural symptoms These tools help identify specific deficits that align with different subtypes of FTD. Blood Tests and Genetic Screening While there is no blood test that confirms FTD, doctors may use blood tests to: Rule out other medical conditions, such as thyroid problems, infections, or vitamin deficiencies In inherited cases, genetic testing may be offered to identify mutations in genes like MAPT, GRN, or C9orf72 Genetic counselling is strongly recommended before and after testing. Differential Diagnosis FTD is often misdiagnosed as: Depression or bipolar disorder Alzheimer’s disease Autism spectrum disorders, particularly in younger adults A team approach involving neurologists, psychiatrists, and speech therapists often leads to more accurate results. Diagnosis of Frontotemporal Dementia A confirmed diagnosis of frontotemporal dementia allows families to access care resources early, plan for the future, and participate in research or clinical trials if appropriate. [Next: Treatment of Frontotemporal Dementia →]

Diagnosis of Frontotemporal Dementia Read More »

Digital illustration of brain highlighting frontotemporal lobe damage

Treatment of Frontotemporal Dementia

Treatment of Frontotemporal Dementia The treatment of frontotemporal dementia focuses on managing symptoms, maintaining quality of life, and supporting the individual and their caregivers. Although there is currently no cure for frontotemporal dementia, a combination of medications, therapies, and supportive strategies can help people live more comfortably and safely. Medications There are no drugs that can stop or reverse the progression of FTD. However, certain medications can ease behavioural and psychological symptoms: Antidepressants such as SSRIs (e.g., sertraline) may reduce compulsive behaviours, anxiety, or irritability Antipsychotic medications may be used cautiously in cases of severe agitation or aggression—but these are prescribed only when absolutely necessary due to risks of side effects Stimulants or mood stabilisers are sometimes trialled for individuals with apathy or disinhibition Unlike Alzheimer’s disease, cholinesterase inhibitors (e.g., donepezil) are not generally effective in FTD and may worsen symptoms in some cases. Speech and Language Therapy For people with primary progressive aphasia (language-based FTD), speech therapy can help maintain communication for as long as possible Strategies may include: Picture boards or writing tools Communication apps Alternative ways to express needs and feelings Regular therapy sessions can slow the loss of verbal skills and support the person’s dignity and independence. Occupational and Physiotherapy Occupational therapists help adapt the home for safety and independence Physiotherapists may be involved in cases with movement disorders, such as those resembling Parkinson’s disease or motor neurone disease These therapies help reduce the risk of falls, maintain mobility, and support daily functioning Lifestyle and Environmental Support Establishing routines can reduce confusion and anxiety Limit environmental stimulation if the person becomes easily overwhelmed Use structured schedules, clear signage, and simplified choices to support independence Carers may need training to understand and respond to challenging behaviours without confrontation or distress. Support for Families Counselling and support groups for carers and family members can reduce emotional strain Respite care, day centres, and in-home assistance may be required as the condition progresses Legal planning, including power of attorney and advance directives, should be addressed early Treatment of Frontotemporal Dementia The treatment of frontotemporal dementia requires a person-centred approach tailored to the subtype and symptoms. With the right support, many people with FTD can continue to live meaningfully and safely for several years after diagnosis. [Next: Complications of Frontotemporal Dementia →]

Treatment of Frontotemporal Dementia Read More »

Elderly man receiving neurological assessment for dementia

Complications of Frontotemporal Dementia

Complications of Frontotemporal Dementia The complications of frontotemporal dementia arise as the condition progresses and increasingly affects the person’s ability to function independently. Frontotemporal dementia can lead to physical, emotional, and social challenges that place strain not only on the individual but also on caregivers and loved ones. Loss of Independence As cognitive and behavioural symptoms worsen: The person may lose the ability to manage daily tasks, such as dressing, cooking, or handling finances They may forget appointments, neglect hygiene, or become unable to use language to express needs 24-hour care may become necessary in the later stages Maintaining dignity and respecting the individual’s autonomy for as long as possible is essential. Behavioural Risks Socially inappropriate actions or poor judgement may lead to embarrassment, legal issues, or strained relationships Some people may develop compulsive eating, putting them at risk of choking or weight gain Wandering, aggression, or disinhibition may require supervision or specialised care environments These behaviours are often misunderstood and can be distressing for families and caregivers. Communication Breakdown Progressive language loss can lead to frustration, isolation, and depression The inability to understand or express thoughts clearly affects relationships and can result in social withdrawal Communication aids and caregiver patience play an important role in preserving connection Physical Decline In certain types of FTD with motor involvement: Muscle stiffness, tremors, or weakness may develop Swallowing difficulties (dysphagia) increase the risk of aspiration pneumonia Individuals may become bed-bound, increasing the risk of pressure sores and infections Nutrition and physiotherapy become more important as physical function declines. Emotional and Mental Health Complications Many individuals experience apathy, depression, or emotional blunting They may appear indifferent to once-important relationships or personal milestones Families may struggle to cope with the emotional loss of the person’s personality before physical decline occurs Support for mental wellbeing is just as important as physical care. Impact on Carers Carers often face emotional exhaustion, isolation, and burnout Financial strain may arise from time off work or costs of private care Access to community resources, support groups, and professional respite is vital Complications of Frontotemporal Dementia The complications of frontotemporal dementia can be managed with early planning, multidisciplinary care, and a strong support system. With the right interventions, the journey can be made more manageable for both the person living with FTD and those who care for them. [Next: Back to Overview →]

Complications of Frontotemporal Dementia Read More »

Elderly person with foot drop using a walker beside a puddle on the floor

Foot Drop

Foot Drop The foot drop condition is a condition in which a person has difficulty lifting the front part of thefoot, causing it to drag or slap against the ground while walking. This condition is not a disease in itself, but rather a symptom of an underlying neurological, muscular, or anatomical problem. It results from weakness or paralysis of the muscles that lift the foot, most often due to nerve injury. People with this condition often adapt by lifting their knees higher than usual while walking, producing a distinctive “steppage gait.” In some cases, the condition is temporary and improves with treatment, while in others, it may be permanent or require long-term support through braces, physical therapy, or surgery. Foot Drop This condition can significantly affect mobility, balance, and confidence. It may lead to tripping or falling, particularly on uneven surfaces or stairs. Early diagnosis and intervention improve outcomes and help patients maintain independence and quality of life. Raising awareness of this condition can help people recognise symptoms early and seek appropriate medical attention to prevent further complications. [Next: Causes of Foot Drop →]

Foot Drop Read More »

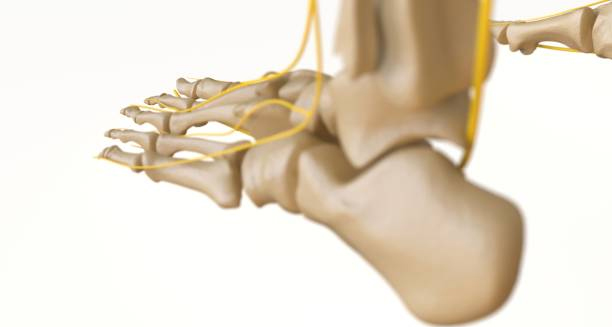
Anatomical illustration showing nerve and bone structures in the foot related to foot drop

Causes of Foot Drop

Causes of Foot Drop The causes of foot drop are generally related to problems with the nerves, muscles, or brain pathways that control movement in the lower leg. Foot drop is often due to injury or compression of the peroneal nerve, which controls the muscles responsible for lifting the foot. Peroneal Nerve Damage The common peroneal nerve runs down the outer part of the knee and controls the muscles that lift the foot and toes It is particularly vulnerable to injury or compression because it lies close to the surface Causes include: Knee or leg trauma, such as fractures or surgery Prolonged leg crossing or squatting Wearing tight casts or braces around the knee or upper leg Rapid weight loss, which may reduce protective fat around the nerve Nerve Root Compression Conditions affecting the spine, such as slipped discs or spinal stenosis, can compress nerve roots in the lower back This may interrupt the signals sent to the foot muscles and result in foot drop Back pain or sciatica may be present alongside foot weakness Neurological Conditions Diseases that affect the brain or spinal cord can disrupt movement control: Stroke Multiple sclerosis (MS) Cerebral palsy Motor neurone disease (ALS) In these cases, foot drop may be part of a broader pattern of weakness or spasticity. Muscle Disorders Certain muscular dystrophies or inherited muscle conditions may weaken the lower leg muscles These are less common but can cause foot drop gradually over time Other Causes Diabetes, which can damage peripheral nerves (diabetic neuropathy) Tumours or cysts compressing nerves in the spine or leg Inflammatory diseases, such as Guillain-Barré syndrome or vasculitis Causes of Foot Drop Identifying the cause of foot drop is essential for proper treatment. While some cases resolve with time and therapy, others may require surgery or long-term management strategies. [Next: Symptoms of Foot Drop →]

Causes of Foot Drop Read More »

Person holding foot while sitting, possibly experiencing foot drop symptoms

Symptoms of Foot Drop

Symptoms of Foot Drop The symptoms of foot drop are typically easy to recognise and affect how a person walks. Foot drop causes difficulty lifting the front part of the foot, leading to compensatory movements and instability. Depending on the underlying cause, symptoms may come on suddenly or develop gradually over time. Gait Abnormalities The most obvious symptom is a high-stepping gait, also known as a steppage gait Individuals lift their knees unusually high to prevent the toes from dragging When walking quickly or climbing stairs, this gait becomes more pronounced In some cases, the foot may slap down onto the floor after each step, due to lack of muscle control Foot and Toe Weakness Difficulty raising the foot or toes (dorsiflexion) Trouble standing on the heel of the affected foot Weakness may worsen with prolonged walking or fatigue Patients may also trip frequently, especially when walking barefoot or on uneven surfaces Numbness or Tingling Some individuals experience numbness, tingling, or a “pins and needles” sensation along the outer shin or top of the foot These are signs of nerve involvement, especially when the peroneal nerve is compressed Muscle Wasting Over time, the muscles in the front of the lower leg may become visibly smaller (atrophied) if the condition persists without treatment This is more common in chronic or untreated cases Bilateral vs. Unilateral Symptoms Foot drop usually affects one side (unilateral), but in rare cases—such as in certain neurological or muscular diseases—it can occur in both feet Associated Symptoms Depending on the cause, other symptoms may include: Back pain or radiating leg pain (if the problem originates in the spine) Balance issues or instability, particularly in the dark or on stairs Spasticity or stiffness in the leg muscles in neurological conditions Symptoms of Foot Drop Recognising the symptoms of foot drop early allows for prompt diagnosis and tailored treatment. This helps prevent falls, joint damage, and further muscle weakening. [Next: Diagnosis of Foot Drop→]

Symptoms of Foot Drop Read More »

Doctor examining patient’s foot during a medical consultation

Diagnosis of Foot Drop

Diagnosis of Foot Drop The diagnosis of foot drop is made through clinical evaluation, neurological testing, and imaging to determine the underlying cause. Because foot drop is a symptom and not a condition itself, accurate diagnosis is crucial to guide effective treatment. Clinical Examination A healthcare provider will begin with: A detailed history of symptom onset and progression Questions about recent injuries, surgeries, or medical conditions Assessment of gait, watching for a high-stepping or slapping pattern Tests of muscle strength, especially dorsiflexion (lifting the foot upwards) Reflex testing and sensory evaluation to check for nerve involvement The inability to walk on the heel or lift the front of the foot suggests muscle weakness or nerve dysfunction. Neurological Testing Nerve conduction studies (NCS) assess how well electrical signals travel through the peroneal nerve Electromyography (EMG) measures muscle activity and detects signs of nerve or muscle damage These tests help pinpoint whether the problem is in the nerve, muscle, or spinal cord Imaging Studies To determine the root cause, doctors may request: MRI of the spine, if a herniated disc or spinal stenosis is suspected Ultrasound or MRI of the knee or leg, if compression of the peroneal nerve is likely Brain imaging (CT or MRI) if neurological diseases such as stroke or multiple sclerosis are suspected Blood Tests Blood tests may help identify: Diabetes or thyroid disorders Vitamin deficiencies (e.g., B12) Autoimmune or inflammatory conditions Specialist Referral | Diagnosis of Foot Drop In complex or unclear cases, referral to a neurologist, orthopaedic surgeon, or physiotherapist may be necessary for further assessment and management planning. The diagnosis of foot drop is a multi-step process involving physical exams, nerve testing, and imaging. Early and accurate diagnosis leads to more effective treatment and improved long-term outcomes. [Next: Treatment of Foot Drop →]

Diagnosis of Foot Drop Read More »

Leg in orthopaedic brace for foot drop treatment

Treatment of Foot Drop

Treatment of Foot Drop The treatment of foot drop depends on its underlying cause, severity, and duration. While some people recover fully, others may need long-term support. Foot drop can often be managed effectively with a combination of physical therapy, bracing, and, in some cases, surgical intervention. Conservative Treatments 1. Ankle-Foot Orthosis (AFO) A lightweight brace worn on the lower leg and foot Helps keep the foot in a neutral position during walking Reduces risk of tripping and allows a more natural gait Widely used in both short-term and long-term management 2. Physiotherapy Strengthens muscles in the leg and improves mobility Focuses on range-of-motion exercises, gait training, and balance improvement May also include electrical stimulation to activate weak muscles 3. Addressing the Underlying Cause Treating a herniated disc may relieve pressure on the nerve Managing diabetes can help prevent further nerve damage Reducing inflammation with medication may help in autoimmune cases Stopping activities that aggravate nerve compression (e.g., prolonged leg crossing) Surgical Options Surgery may be considered when: There is no improvement after several months of conservative treatment A tumour or cyst is compressing the nerve The nerve is severely damaged or torn Surgical procedures may include: Nerve decompression to relieve pressure Tendon transfer surgery, where a working tendon is re-routed to replace the function of the weak dorsiflexor muscles Spinal surgery, if the issue originates in the lower back Assistive Devices and Home Modifications Using a cane or walking aid can improve safety Installing non-slip flooring and stair rails helps reduce fall risk Supportive shoes with firm soles and wide toes can ease movement Treatment of Foot Drop The treatment of foot drop is often multidisciplinary and may involve long-term physiotherapy or supportive devices. With the right interventions, many people regain mobility and independence. [Next: Complications of Foot Drop →] Complications of Foot Drop

Treatment of Foot Drop Read More »

Scroll to Top