Mental Matters

Health Conditions

Find information on various health conditions affecting people of all ages. This category covers causes, symptoms, diagnosis, and management options for physical illnesses and chronic diseases. Get insights to help you understand different health challenges and make informed decisions about your wellbeing.

Teen boy sitting on pavement after falling and grazing his knee

Causes of Grazes

Causes of Grazes Causes of grazes are almost always mechanical, involving the skin scraping against a rough or hard surface. Unlike penetrating wounds, grazes result from friction, which removes the top layers of skin but usually spares deeper tissues. They are often accidental and tend to occur in active individuals or during unexpected falls. Accidental Falls The most common cause of grazes is a fall: Children running and tripping on pavements or school playgrounds Cyclists or skateboarders falling onto gravel, concrete, or tarmac Runners stumbling on uneven surfaces The palms, knees, elbows, and shins are frequent sites of injury due to instinctive reactions to break a fall. Sports and Physical Activities Contact and high-intensity sports often lead to grazes, including: Football, rugby, or hockey where collisions and tackles are common Martial arts or wrestling, where friction with mats causes abrasions Track and field events, particularly during falls or slides on synthetic surfaces Everyday Incidents Falling indoors onto rough carpet or textured flooring Brushing against brick walls or fences Removing adhesive bandages or tape too quickly Occupational Hazards Certain jobs may involve exposure to abrasive surfaces: Construction workers Landscapers and gardeners Delivery personnel navigating uneven terrain Lack of proper protective gear increases the risk. Environmental Factors | Causes of Grazes Wet or slippery conditions can cause sudden slips leading to grazing injuries, particularly when walking or running downhill or on slick surfaces. In conclusion, causes of grazes include falls, sports, occupational exposure, and environmental hazards. Taking safety precautions and using appropriate protective clothing can help minimise the risk. [Next: Symptoms of Grazes →]

Causes of Grazes Read More »

Close-up of a fresh red graze on human skin

Symptoms of Grazes

Symptoms of Grazes Symptoms of grazes are usually immediate and easily recognisable. The pain, appearance, and discomfort associated with grazes reflect the level of surface damage to the skin. While typically not serious, grazes can be very painful due to exposed nerve endings in the outer skin layers. Immediate Symptoms Stinging or burning pain at the site of injury, especially when touched or exposed to air Visible abrasion: The skin looks raw, red, or pink, and in some cases, small specks of dirt or debris may be embedded Bleeding or weeping: Grazes may ooze blood or clear fluid due to capillary disruption Swelling and mild inflammation around the affected area Scab Formation After the initial weeping phase, a scab forms over the graze: Protects the wound as new skin develops underneath Appears brown or reddish Should be left undisturbed to avoid re-injury or infection Itching and Tightness As healing progresses: The area may feel tight, particularly on joints or over muscles Itching is common during scab formation and indicates healing Scratching can lead to reopening the wound or introducing bacteria Signs of Infection While most grazes heal without issue, infection can occur if the wound is not properly cleaned: Increased redness or swelling Pus formation or foul odour Warmth around the site Persistent pain Fever or swollen lymph nodes (in severe cases) Delayed Healing Certain individuals may notice slower recovery due to: Underlying conditions like diabetes Poor blood circulation Repeated trauma to the area Symptoms of Grazes In summary, symptoms of grazes include immediate pain, visible skin loss, and scab formation, with potential signs of infection during recovery. Prompt wound care supports fast healing and minimises complications. [Next: Diagnosis of Grazes →]

Symptoms of Grazes Read More »

Doctor examining a patient's arm for grazes or skin injuries

Diagnosis of Grazes

Diagnosis of Grazes Diagnosis of grazes is usually clinical, meaning it is based on visual inspection and a brief patient history. In most cases, grazes are easily identifiable by their characteristic appearance and do not require specialised testing. However, a thorough examination ensures that no deeper injuries or complications are missed. Clinical Assessment During diagnosis, a healthcare provider will assess: Size and depth of the graze Location (over joints, hands, face, etc.) Signs of contamination (presence of gravel, dirt, or debris) Signs of infection (redness, pus, odour) Associated injuries, such as bruises, swelling, or sprains The goal is to determine whether the graze is superficial or if further treatment, such as wound cleaning, dressing, or antibiotics, is necessary. Wound Classification Healthcare professionals often classify wounds to guide treatment: Superficial grazes: Affect only the epidermis and are the most common Partial-thickness abrasions: Extend into the dermis but do not involve deeper tissues Full-thickness abrasions: Rare, may involve fat or muscle and can require medical attention Tetanus Risk Evaluation For more extensive grazes, especially those contaminated with soil or rust, the doctor will ask about tetanus vaccination history. A booster may be offered if more than 10 years have passed since the last dose, or sooner if the wound is high-risk. Functional Testing (If Over Joints) If the graze is located near or over a joint, the provider may check for: Range of motion: Ensuring movement is not restricted due to pain or swelling Deeper damage: Looking for indications of underlying ligament or tendon injury When Imaging Is Needed Though rare for grazes, an X-ray may be considered if: A foreign body is suspected within the wound There is significant swelling or pain, raising concern about fractures or joint involvement Diagnosis of Grazes In summary, diagnosis of grazes is straightforward and based on appearance, depth, and contamination risk. Early and accurate evaluation helps prevent complications and supports effective healing. [Next: Treatment of Grazes →]

Diagnosis of Grazes Read More »

Treatment of Grazes

Treatment of Grazes

Treatment of Grazes Treatment of grazes focuses on cleaning the wound, protecting it during healing, and preventing infection. Most grazes can be treated at home with basic first aid supplies, but some may need professional care, especially if they are large, contaminated, or slow to heal. Immediate First Aid Wash hands before touching the wound Stop any bleeding with gentle pressure using sterile gauze or a clean cloth Clean the wound under cool, running water; use mild soap around (not in) the wound Remove debris carefully with tweezers sterilised with alcohol Apply antiseptic such as iodine or chlorhexidine to reduce infection risk Avoid using hydrogen peroxide or alcohol directly in the wound, as these may delay healing. Dress the Wound Cover with a non-stick, sterile dressing or hydrocolloid plaster Change the dressing daily or when wet or dirty Apply antibiotic ointment (if advised) to prevent infection and keep the wound moist Keeping the wound moist—not dry—encourages faster healing with reduced scarring. Pain and Inflammation Over-the-counter pain relievers like paracetamol or ibuprofen may help Elevate the area if there is swelling, especially on limbs When to See a Doctor Seek medical attention if: The graze is large, deep, or heavily contaminated Signs of infection develop (pus, redness, warmth) The wound doesn’t improve within a few days There’s concern about tetanus (dirty wound, rusty surface, no recent booster) Avoiding Re-injury Keep the area protected during sports or work Use knee or elbow pads for children involved in high-impact play Treatment of Grazes In summary, treatment of grazes involves careful cleaning, protection, and infection prevention. Most heal quickly with home care, but attention to cleanliness and dressing changes is vital to avoid complications. [Next: Complications of Grazes →]

Treatment of Grazes Read More »

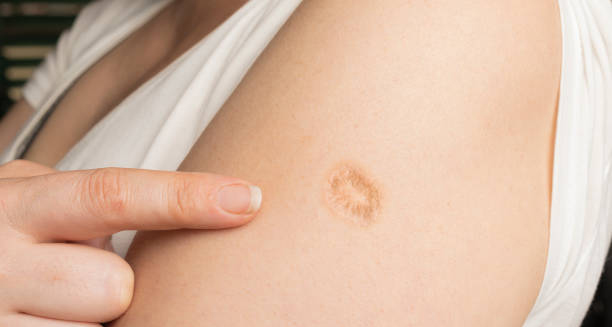
Healed scar from a graze on upper arm

Complications and Recovery from Grazes

Complications and Recovery from Grazes Complications and recovery from grazes are generally minimal, as these injuries involve only the skin’s surface. However, if grazes are not properly cleaned or cared for, they may become infected or result in delayed healing and scarring. Recovery time depends on the size, depth, and location of the graze, as well as the individual’s overall health. Possible Complications Infection: If the wound becomes red, swollen, hot, or filled with pus, this indicates infection and may require antibiotics. Scarring: While superficial grazes usually heal without marks, deeper abrasions may leave scars, especially if picked or scratched. Delayed healing: Caused by re-injury, underlying health conditions (e.g. diabetes), or poor wound hygiene Embedded debris: If not fully removed, particles like gravel or sand can cause inflammation or chronic irritation Signs of Proper Healing Formation of a scab, which protects new skin underneath Reduction in redness and swelling within a few days Itching, which signals tissue repair Return of normal skin colour and texture over time Recovery Timeline Small grazes: Heal in 3–7 days Moderate abrasions: May take 1–2 weeks Deeper abrasions: Require longer, especially if scarring occurs Healing is quicker in young, healthy individuals and when the wound is kept clean, moist, and protected. Scar Prevention Once healed, apply moisturiser or silicone gel to soften scar tissue Protect the area from sun exposure, as new skin is prone to pigmentation changes Aftercare Tips Avoid scratching or disturbing the scab Continue dressing changes until the wound is dry and sealed Monitor for changes that may suggest complications Complications and Recovery from Grazes In conclusion, complications and recovery from grazes are uncommon with good wound care. Most people experience complete healing without long-term effects. Understanding proper aftercare helps ensure fast recovery and minimal scarring. [Next: Back to Overview →]

Complications and Recovery from Grazes Read More »

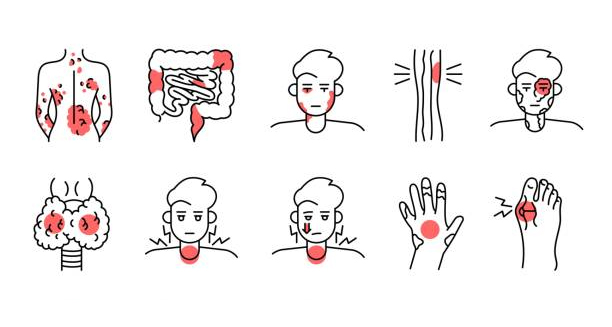
Medical illustration of granulomatosis with polyangiitis symptoms

Granulomatosis with Polyangiitis

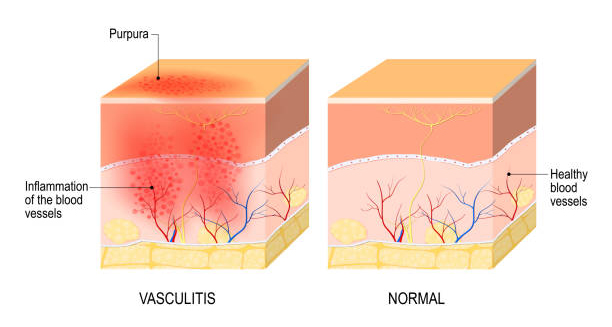
Granulomatosis with Polyangiitis Granulomatosis with polyangiitis is a rare but serious autoimmune disease characterised by inflammation of blood vessels, particularly small- and medium-sized vessels throughout the body. Formerly known as Wegener’s granulomatosis, granulomatosis with polyangiitis often affects the respiratory tract and kidneys, although it can involve many organs. The inflammation can lead to tissue damage, organ dysfunction, and, if left untreated, life-threatening complications. This condition belongs to a group of disorders known as ANCA-associated vasculitides (AAV), named for the presence of anti-neutrophil cytoplasmic antibodies (ANCAs) found in many affected individuals. Granulomatosis with polyangiitis tends to strike adults aged 40–60 but can occur at any age. Early diagnosis and aggressive treatment with immunosuppressive drugs can help achieve remission and prevent permanent damage. Key Characteristics Granulomatosis with polyangiitis is marked by three main pathological features: Granulomatous inflammation – a type of immune response involving clusters of inflammatory cells Vasculitis – inflammation of the blood vessel walls Necrosis – tissue damage resulting from loss of blood supply or immune destruction These features affect organs such as: Sinuses, nose, and upper airways Lungs Kidneys Skin, eyes, joints, and nervous system Symptoms often begin subtly, with fatigue, joint pain, or sinus issues, before progressing to more serious organ involvement. Epidemiology and Risk Granulomatosis with polyangiitis is rare, with an estimated annual incidence of 10–20 cases per million people worldwide. Risk factors include: Middle age (more common in individuals aged 40–65) Slight male predominance Caucasian ethnicity (more prevalent in European populations) Family history of autoimmune disorders (though not directly inherited) It affects people globally and across all demographics, but detection rates vary due to limited awareness and diagnostic capacity in some regions. Early Symptoms Initial symptoms may be vague and resemble common illnesses: Fatigue and general malaise Unexplained weight loss Fever and night sweats Persistent sinus infections or nasal congestion Ear pain or hearing loss Dry cough or shortness of breath Joint and muscle aches Because these symptoms mimic those of respiratory infections, sinusitis, or allergies, the condition is often misdiagnosed in its early stages. Respiratory Involvement The upper and lower respiratory tracts are commonly affected: Sinusitis, nasal crusting, or frequent nosebleeds Saddle-nose deformity due to cartilage destruction Chronic cough, wheezing, or haemoptysis (coughing up blood) Lung nodules or infiltrates, visible on chest imaging These issues can escalate to lung haemorrhage or respiratory failure if not promptly addressed. Kidney Involvement One of the most serious aspects of granulomatosis with polyangiitis is glomerulonephritis, or inflammation of the kidneys’ filtering units: Early signs include blood or protein in the urine May progress silently to kidney failure Renal biopsy is often necessary for definitive diagnosis If untreated, kidney involvement can lead to irreversible damage and the need for dialysis. Other Organ Systems The disease may also affect: Skin – purple spots (purpura), ulcers, or nodules Eyes – inflammation, dryness, pain, or vision loss Nerves – tingling, numbness, or muscle weakness Joints – arthritis-like pain, especially in large joints Multisystem involvement complicates diagnosis and requires a coordinated approach to treatment. Diagnosis Challenges Because of its rarity and non-specific early symptoms, diagnosis is often delayed. The condition must be distinguished from infections, cancers, and other autoimmune diseases. Blood tests, imaging, and biopsy are typically needed for confirmation. Importance of Early Treatment Prompt recognition is critical. Without treatment, granulomatosis with polyangiitis can progress rapidly, causing permanent damage or death. With appropriate therapy, however, long-term remission is possible for many patients. Conclusion | Granulomatosis with Polyangiitis Granulomatosis with polyangiitis is a complex autoimmune vasculitis that causes systemic inflammation and serious organ damage if left untreated. Its early symptoms often mimic common conditions, making awareness and timely diagnosis vital. Despite its severity, with modern immunosuppressive therapy, granulomatosis with polyangiitis is a manageable condition, and many individuals can achieve lasting remission. [Next: Causes of Granulomatosis with Polyangiitis →]

Granulomatosis with Polyangiitis Read More »

Causes of Granulomatosis with Polyangiitis

Causes of Granulomatosis with Polyangiitis

Causes of Granulomatosis with Polyangiitis Doctors still do not fully understand what causes granulomatosis with polyangiitis (GPA). However, they believe it begins with an abnormal immune response that causes inflammation in blood vessels and nearby tissues. Even though the exact cause remains unknown, research points to a mix of genetics, environmental exposure, infections, and autoimmune activity as major contributors. GPA belongs to a group of illnesses called ANCA-associated vasculitides, which involve harmful antibodies called anti-neutrophil cytoplasmic antibodies (ANCAs). These antibodies seem to play a key role in the damage seen in affected organs. 1. Autoimmune Mechanisms First and foremost, GPA behaves like an autoimmune disease. In this condition, the immune system attacks the body’s own tissues by mistake. While the reason for this faulty immune attack isn’t clear, several things happen: This process creates granulomas, blood vessel inflammation (vasculitis), and in some cases, tissue death (necrosis). 1. Autoimmune Mechanisms First and foremost, GPA behaves like an autoimmune disease. In this condition, the immune system attacks the body’s own tissues by mistake. While the reason for this faulty immune attack isn’t clear, several things happen: This process creates granulomas, blood vessel inflammation (vasculitis), and in some cases, tissue death (necrosis). 2. Genetic Factors Although GPA doesn’t pass directly from parent to child, certain genes may make some people more likely to develop it. For example: These genetic factors suggest that some individuals carry an inherited vulnerability. When exposed to the right trigger, their immune system may overreact. 3. Environmental and Occupational Exposures Next, environmental and workplace exposures may also trigger GPA in people who already carry genetic risk. Research has linked the disease to: These substances may damage tissues or overstimulate the immune system, leading to inflammation. 4. Infections Infections may also play an important role. They can either trigger GPA for the first time or make it worse later. Specifically: These infections may set off or maintain harmful immune reactions that damage the blood vessels. 5. Drug-Induced Triggers Although uncommon, certain medications can cause a condition that looks like GPA. These include: Usually, the symptoms go away after stopping the drug. Doctors can often tell drug-induced cases apart from true GPA through blood tests and history. 6. Immune System Triggers Sometimes, GPA may start after the immune system reacts to injury or repeated exposure to certain antigens. For example: This overreaction turns into chronic inflammation unless doctors stop it early. 7. Hormonal and Biological Factors Finally, some differences in age, sex, and hormones may affect who gets GPA. For instance: Although doctors don’t yet understand these patterns fully, they point to a mix of biological influences. Summary of Contributing Factors Category Examples Autoimmune response ANCA antibodies, neutrophil activation Genetic susceptibility HLA genes, PTPN22, SERPINA1 Environmental exposure Silica, solvents, farm chemicals Infections Staphylococcus aureus, viral infections Drug-induced triggers Hydralazine, PTU, levamisole Biological factors Age, sex, immune system behavior Multifactorial Nature of GPA So far, no single cause explains all cases of GPA. Instead, the disease likely results from a mix of factors, such as: This complex picture explains why GPA looks different from one person to another. It also guides doctors to treat the root immune problem—not just the symptoms. Conclusion | Causes of Granulomatosis with Polyangiitis To sum up, GPA results from a combination of genetic, environmental, infectious, and immune-related factors. Even though researchers haven’t found one clear cause, growing evidence points to autoimmune activity driven by ANCAs. By better understanding what causes GPA, doctors can improve how they diagnose it, treat it, and support patients living with this rare but serious condition. [Next: Symptoms of Granulomatosis with Polyangiitis→]

Causes of Granulomatosis with Polyangiitis Read More »

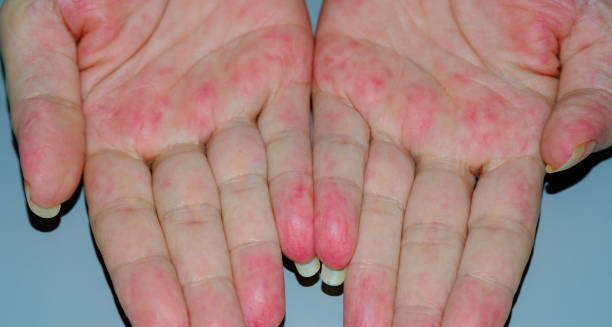
Red rash and inflammation on palms due to granulomatosis with polyangiitis

Symptoms of Granulomatosis with Polyangiitis

Symptoms of Granulomatosis with Polyangiitis The symptoms of granulomatosis with polyangiitis vary widely depending on which organs are affected, but typically include a mix of respiratory, renal, and generalised inflammatory signs. The symptoms of granulomatosis with polyangiitis often start gradually and may initially resemble common illnesses such as sinusitis or the flu, making early diagnosis challenging. However, as the disease progresses, organ damage may become more pronounced, sometimes resulting in life-threatening complications if left untreated. Granulomatosis with polyangiitis (GPA) is a rare autoimmune vasculitis that causes inflammation of small- and medium-sized blood vessels, particularly in the lungs, kidneys, and upper airways. Granulomas—clusters of inflammatory cells—also form in tissues, further contributing to damage. Because GPA can affect virtually any organ system, the symptoms are diverse and may develop over days, weeks, or even months. General Symptoms In the early stages, people often experience non-specific systemic symptoms such as: Fatigue and low energy Weight loss without trying Fever and night sweats Loss of appetite Joint and muscle aches resembling arthritis Mild anaemia or generalised weakness These symptoms often precede more localised organ involvement and are sometimes mistaken for viral infections or chronic fatigue syndrome. Upper Respiratory Tract Involvement The upper respiratory tract is involved in over 90% of cases. Common symptoms include: Chronic sinusitis or persistent nasal congestion Bloody or crusted nasal discharge Nosebleeds (epistaxis) Nasal septal perforation, which may lead to a saddle-nose deformity Hearing loss due to eustachian tube dysfunction Ear pain, fullness, or infections These symptoms are often recurrent and may resist standard treatment with antibiotics or decongestants, raising suspicion of an underlying inflammatory process. Lower Respiratory Tract Symptoms Lung involvement is another hallmark of GPA and may present with: Chronic dry cough Shortness of breath Chest pain, especially on deep breathing Coughing up blood (haemoptysis) Wheezing or crackles on examination Chest X-rays or CT scans may reveal nodules, infiltrates, or cavities—sometimes misinterpreted as infections, tuberculosis, or cancer. In severe cases, lung haemorrhage can occur, requiring urgent treatment. Kidney Involvement Kidney inflammation, or glomerulonephritis, may be silent in early stages but is one of the most serious manifestations: Blood in the urine (haematuria) Protein in the urine (proteinuria) Foamy urine High blood pressure Swelling in the ankles or around the eyes Without treatment, kidney function may deteriorate rapidly, leading to chronic kidney disease or kidney failure. Eye and Vision Problems Inflammation may extend to the eyes, resulting in: Red, painful eyes Blurred vision or double vision Dry eyes Episcleritis or scleritis (inflammation of the white part of the eye) Vision loss in severe cases Prompt ophthalmologic assessment is essential to preserve vision in affected individuals. Skin Lesions Skin symptoms occur in approximately 30–50% of cases. These may include: Reddish or purple spots (purpura), particularly on the legs Ulcers, especially on the extremities Tender nodules or lumps Rashes resembling allergic reactions Skin biopsy may help confirm vasculitis as the cause of these lesions. Nervous System Symptoms The nervous system may also be affected, causing: Peripheral neuropathy (numbness, tingling, or burning in the hands or feet) Muscle weakness Cranial nerve palsies Rarely, stroke-like episodes or central nervous system involvement Neurological symptoms can be subtle or debilitating, depending on the nerves involved. Gastrointestinal Involvement Although less common, the gastrointestinal system can also be affected, leading to: Abdominal pain Nausea or vomiting Gastrointestinal bleeding or ulcers These symptoms may mimic other GI conditions and complicate diagnosis. Symptoms in Children Granulomatosis with polyangiitis is rare in children but presents similarly: Fever, weight loss, and fatigue Ear, nose, and throat infections that do not resolve Joint pain or swelling Haematuria or proteinuria Paediatric diagnosis can be particularly challenging due to overlap with common childhood illnesses. Patterns and Progression There is no fixed sequence for symptom development: Some individuals have isolated respiratory symptoms for months before kidney involvement appears Others may present suddenly with multisystem disease Flare-ups can alternate with periods of remission This unpredictable pattern underscores the need for ongoing monitoring and early specialist referral. Conclusion | Symptoms of Granulomatosis with Polyangiitis The symptoms of granulomatosis with polyangiitis are diverse, ranging from sinus congestion and joint pain to life-threatening kidney failure or lung haemorrhage. Because the symptoms of granulomatosis with polyangiitis often mimic more common conditions, early recognition requires a high index of suspicion, especially in persistent or multisystem disease. Accurate diagnosis and early treatment are essential to reduce the risk of long-term complications and achieve remission. [Next: Diagnosis of Granulomatosis with Polyangiitis →]
Symptoms of Granulomatosis with Polyangiitis Read More »

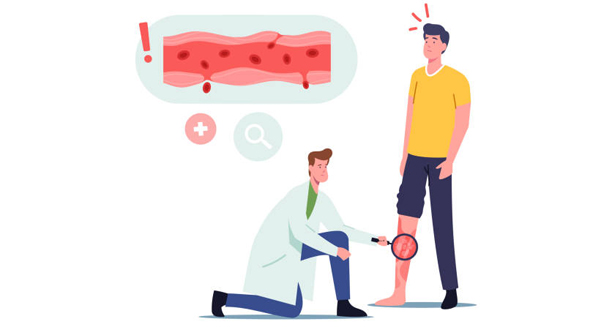
Doctor examining leg rash to diagnose granulomatosis with polyangiitis

Diagnosis of Granulomatosis with Polyangiitis

Diagnosis of Granulomatosis with Polyangiitis The diagnosis of granulomatosis with polyangiitis involves a combination of clinical evaluation, blood tests, imaging, and tissue biopsy. Since the diagnosis of granulomatosis with polyangiitis can be challenging due to its rarity and symptom overlap with other illnesses, it requires a coordinated approach between general practitioners, rheumatologists, nephrologists, and other specialists. Granulomatosis with polyangiitis (GPA) is an ANCA-associated vasculitis that causes inflammation of blood vessels and tissues. Diagnosis is critical to prevent organ damage that cannot be undone, and early treatment improves outcomes significantly. Clinical Evaluation Diagnosis begins with a detailed medical history and physical examination. Key clues include: Chronic sinus, nasal, or ear infections Persistent cough or haemoptysis Blood in the urine or kidney function decline Joint pains, skin lesions, and systemic inflammation Symptoms involving multiple systems (e.g. lungs and kidneys) Because no single symptom is definitive, the pattern of involvement often points toward GPA. Blood Tests Several blood tests support the diagnosis and rule out other conditions: 1. ANCA (Anti-Neutrophil Cytoplasmic Antibody) Test Positive in approximately 80–90% of GPA cases Most patients test positive for c-ANCA (cytoplasmic ANCA), targeting proteinase 3 (PR3) A smaller number have p-ANCA, often targeting myeloperoxidase (MPO) Though not 100% specific, ANCA testing is a valuable tool for diagnosis when interpreted alongside clinical findings. 2. Inflammatory Markers Elevated ESR (erythrocyte sedimentation rate) Raised CRP (C-reactive protein) These non-specific markers indicate active inflammation and help monitor disease activity. 3. Renal Function Tests Serum creatinine and eGFR to assess kidney function Urinalysis to detect blood, protein, or red blood cell casts in the urine Abnormal kidney results often prompt further testing, including biopsy. Imaging Studies Imaging helps identify organ involvement and guide biopsy: Chest X-ray or CT Scan May reveal lung nodules, cavities, infiltrates, or effusions Useful for checking disease severity and monitoring response to treatment Sinus or Ear CT Scans Show mucosal thickening, bone destruction, or fluid build-up Can guide surgical sampling in ENT-related cases Biopsy Tissue biopsy remains the gold standard for diagnosis. Biopsies may be taken from: Kidneys – to identify crescentic glomerulonephritis and confirm vasculitis Lungs – when accessible and safe Skin – in patients with rashes or ulcers Nasal or sinus tissue – often inflamed and easier to access Typical findings include granulomatous inflammation, vasculitis, and necrosis. Diagnostic Criteria and Scoring The American College of Rheumatology (ACR) and European Alliance of Associations for Rheumatology (EULAR) provide classification criteria based on symptoms, ANCA status, imaging, and biopsy results. These criteria help standardise diagnosis in both clinical and research settings. A formal diagnosis often requires several of the following: ANCA positive Upper or lower airway involvement Renal issues or any evidence of glomerulonephritis Histopathological confirmation of granulomas or vasculitis Differential Diagnosis GPA must be distinguished from: Infections (e.g. tuberculosis, fungal lung infections) Other vasculitides, such as microscopic polyangiitis or eosinophilic granulomatosis with polyangiitis Lung cancer or lymphoma Systemic lupus erythematosus Goodpasture’s syndrome Biopsy and ANCA testing are crucial in making these distinctions. Challenges in Diagnosis Diagnosis may be delayed due to: Non-specific early symptoms Misdiagnosis as sinusitis, pneumonia, or asthma Intermittent flares and remissions Negative ANCA test in a small proportion of cases In these scenarios, repeat testing and tissue sampling may be necessary. Importance of Early Diagnosis Early diagnosis allows for prompt initiation of treatment: Reduces risk of permanent organ damage Improves survival rates and quality of life Increases likelihood of achieving remission With current treatments, many patients can lead full and active lives despite the initial severity of disease. Conclusion | Diagnosis of Granulomatosis with Polyangiitis The diagnosis of granulomatosis with polyangiitis requires careful clinical judgment supported by laboratory and histological evidence. Because the diagnosis of granulomatosis with polyangiitis can be difficult in early stages, clinicians must maintain a high index of suspicion in patients with multi-system symptoms. Timely recognition, expert consultation, and comprehensive testing are the foundation for effective management of this complex autoimmune vasculitis. [Next: Treatment of Granulomatosis with Polyangiitis→]

Diagnosis of Granulomatosis with Polyangiitis Read More »

Immunosuppressive medication for granulomatosis with polyangiitis treatment

Treatment of Granulomatosis with Polyangiitis

Treatment of Granulomatosis with Polyangiitis Treating granulomatosis with polyangiitis (GPA) involves two key phases: first, inducing remission and then maintaining it over the long term to prevent relapses. Since GPA treatment lowers the immune system’s defenses, doctors must balance stopping inflammation with minimizing side effects and complications. GPA is a serious autoimmune disease that causes inflammation in blood vessels. Thankfully, treatment has come a long way. Thanks to powerful immune-suppressing medications and newer biologic drugs, many patients now enter remission and live well—especially when treatment starts early and fits the severity of the disease. Phase 1: Induction of Remission The first goal in treatment is to quickly stop active inflammation. This step helps protect vital organs like the kidneys and lungs from lasting damage. 1. Glucocorticoids (Steroids) Doctors usually begin with strong steroids such as prednisolone or methylprednisolone: Although steroids work well, using them for a long time can cause problems such as: To lower these risks, doctors often add other medications that reduce the need for high steroid doses. 2. Immunosuppressive Agents Doctors usually combine steroids with one of these two powerful immune-suppressing drugs: a. Cyclophosphamide b. Rituximab Both treatments need regular blood tests and infection prevention, such as antibiotics to guard against lung infections. Additional Support During Induction During this early treatment phase, patients often need extra care: This support helps reduce side effects and improves the patient’s ability to stay on treatment. Phase 2: Maintenance of Remission Once inflammation is under control, treatment shifts to keeping the disease quiet. This helps prevent flare-ups and limits long-term damage. 1. Azathioprine 2. Methotrexate 3. Mycophenolate Mofetil 4. Rituximab (Maintenance Doses) Most patients stay on maintenance therapy for 18 to 24 months, or longer if they’re at high risk of relapsing. Monitoring and Follow-Up Doctors must check patients often during and after treatment. These checks usually include: Patients also need regular checks for the side effects of their medications, including infections and possible cancers. Lifestyle and Preventive Measures To stay well during treatment, patients should also: Open, honest communication with a team of doctors—including rheumatologists, lung specialists, and mental health experts—helps patients stay on track and feel supported. Pregnancy and Fertility Considerations Treatment may affect the ability to have children, so doctors discuss fertility early on: Women should aim to become pregnant during remission, and specialists should guide treatment before and during pregnancy. Prognosis with Treatment Without treatment, GPA can be deadly. However, today’s treatment offers real hope: Conclusion | Treatment of Granulomatosis with Polyangiitis Treating GPA is complex, but it works well when started early and managed closely. From steroids to biologics to supportive care, every part of treatment must match the patient’s needs and goals. With routine checkups, healthy habits, and strong medical support, most patients can enjoy active, fulfilling lives—even with this rare autoimmune disease. [Next: Complications of Granulomatosis with Polyangiitis →]

Treatment of Granulomatosis with Polyangiitis Read More »

Scroll to Top