Mental Matters

Health & Wellness

Complications of Gonorrhoea

Complications of Gonorrhoea

Complications of Gonorrhoea The complications of gonorrhoea can be severe and long-lasting if the infection is not diagnosed and treated promptly. While gonorrhoea is curable with antibiotics, delayed treatment can lead to serious reproductive, joint, and systemic problems. The most common complications of gonorrhoea involve the genital and pelvic regions, but other body systems can also be affected, especially when the infection spreads through the bloodstream. Because many people with gonorrhoea are asymptomatic, they may unknowingly allow the infection to persist—risking their health and that of their partners. Understanding these complications underscores the importance of early screening, timely treatment, and proper follow-up. In Women 1. Pelvic Inflammatory Disease (PID) PID occurs when gonorrhoea ascends from the cervix into the upper reproductive tract. It may result in: Chronic pelvic pain Tubal scarring, leading to infertility Ectopic pregnancy, a life-threatening condition Menstrual irregularities and painful intercourse PID can be mild or severe, often requiring hospital admission if symptoms are intense or if abscesses form. It is one of the most common causes of infertility in women under 35 worldwide. 2. Infertility Even a single episode of PID can: Block fallopian tubes, preventing fertilisation Increase the risk of future miscarriages or pregnancy complications Prompt treatment of gonorrhoea can prevent PID and protect fertility. In Men 1. Epididymitis An untreated gonorrhoeal infection may spread to the epididymis, the structure that stores and transports sperm. Symptoms include: Scrotal pain and swelling Tenderness along the spermatic cord Fever and chills While usually treatable with antibiotics, severe cases may damage fertility if not addressed early. 2. Urethral Strictures Prolonged infection can cause inflammation and scarring of the urethra, leading to: Difficulty urinating Slowed urinary stream Painful ejaculation These strictures may require surgical correction in advanced cases. Disseminated Gonococcal Infection (DGI) DGI occurs when N. gonorrhoeae enters the bloodstream and spreads to other organs. It may cause: Septic arthritis (painful, swollen joints) Tenosynovitis (inflammation of tendon sheaths) Skin lesions (typically pustules on extremities) Fever and malaise This condition can become life-threatening if not treated with intravenous antibiotics. Hospitalisation is typically required. Complications in Newborns If gonorrhoea is passed from mother to child during delivery: It can cause neonatal conjunctivitis (ophthalmia neonatorum) May lead to permanent blindness if untreated Rarely, systemic infections like sepsis or meningitis may occur Routine eye prophylaxis and antenatal STI screening are key preventive strategies. Increased HIV Risk Gonorrhoea increases the likelihood of acquiring or transmitting HIV: Inflammation increases susceptibility to HIV infection Ulceration or discharge may carry higher viral loads Co-infection with HIV and gonorrhoea is common in high-risk populations Effective STI management can lower the community burden of HIV. Social and Emotional Consequences Chronic or untreated infections can result in: Stigma and shame, especially with visible symptoms Anxiety or depression, particularly after complications like infertility Relationship strain, especially if reinfection occurs Support from healthcare professionals and counselling services can help address emotional impacts. Long-Term Impact on Public Health The wider effects of gonorrhoea complications include: Increased healthcare costs, due to hospitalisations and infertility treatments Reduced quality of life for those with chronic symptoms Burden on fertility clinics, particularly in regions with limited access Public health interventions—like education campaigns, condom distribution, and school-based STI screening—can help reduce this burden. Summary of Key Complications of Gonorrhoea Affected Group Complication Potential Outcomes Women Pelvic Inflammatory Disease (PID) Infertility, ectopic pregnancy, chronic pain Men Epididymitis, urethral strictures Infertility, urinary dysfunction Newborns Conjunctivitis, systemic infection Blindness, neonatal death General Disseminated infection, HIV risk Septic arthritis, increased HIV transmission Conclusion The complications of gonorrhoea can be far-reaching and serious, impacting not only individual health but also community wellbeing and healthcare systems. While easily treatable when caught early, untreated gonorrhoea can lead to infertility, chronic pain, joint damage, and neonatal harm. Raising awareness of the complications of gonorrhoea helps encourage testing, treatment, and prevention—ultimately protecting sexual and reproductive health for all. [Next: Back to Overview →]
Complications of Gonorrhoea Read More »

Molecular structure of glutamic acid related to Glutaric Aciduria Type 1

Glutaric Aciduria Type 1

Glutaric Aciduria Type 1 Glutaric aciduria type 1 is a rare inherited metabolic disorder caused by a deficiency of the enzyme glutaryl-CoA dehydrogenase, which is responsible for breaking down certain amino acids. When this enzyme is absent or malfunctioning, glutaric acid and related compounds accumulate in the body, particularly in the brain, leading to neurological damage. Glutaric aciduria type 1 typically presents in infancy or early childhood and, without early diagnosis and management, can result in severe motor impairment and other lifelong complications. As a disorder of amino acid metabolism, glutaric aciduria type 1 is classified under the group of conditions known as organic acidemias. Although considered rare, its severity and the possibility of preventing neurological damage through early dietary and medical intervention make awareness and timely diagnosis essential. What Happens in the Body? Glutaric aciduria type 1 results from mutations in the GCDH gene, which encodes the enzyme glutaryl-CoA dehydrogenase. This enzyme plays a vital role in breaking down the amino acids lysine, hydroxylysine, and tryptophan. In the absence of normal enzyme function: Toxic compounds like glutaric acid, 3-hydroxyglutaric acid, and glutaconic acid build up in the body These substances accumulate particularly in the basal ganglia—a part of the brain involved in movement control As a result, brain cells become damaged, often leading to dystonia, spasticity, and motor regression The severity of neurological outcomes depends on how early the condition is diagnosed and whether treatment begins before a “metabolic crisis” occurs. How Common Is It? Glutaric aciduria type 1 is estimated to affect approximately 1 in 100,000 people worldwide. However, higher rates have been reported in certain populations, including: The Amish and Mennonite communities of North America Some regions of Sweden Middle Eastern and North African populations where consanguineous marriages are more common In these groups, carrier frequency may be significantly higher, and genetic counselling becomes particularly important. Onset and Presentation There are three general presentations of glutaric aciduria type 1: 1. Asymptomatic (Detected through Screening) Newborn screening identifies elevated markers No signs or symptoms at diagnosis Early treatment can completely prevent damage 2. Infantile-Onset Appears between 3 and 36 months Often triggered by febrile illness, immunisation, or fasting Presents with sudden loss of motor skills, irritability, and hypotonia Progresses to dystonic cerebral palsy if not treated promptly 3. Late-Onset Appears after age 3, sometimes during adolescence May cause milder neurological issues such as learning difficulties or tremors Rare but possible in undiagnosed or mismanaged individuals Key Symptoms and Signs The condition can be variable, but typical symptoms include: Macrocephaly (abnormally large head circumference) Seizures Hypotonia (reduced muscle tone) Delayed development or regression of skills Dystonia (involuntary muscle contractions) Choreoathetosis (irregular movements) In infants who experience a metabolic crisis, symptoms may progress quickly and leave lasting neurological damage. Diagnosis and Screening Most developed countries now include glutaric aciduria type 1 in their newborn screening panels. Diagnosis involves: Tandem mass spectrometry to detect elevated levels of glutaric acid and related metabolites Urine organic acid analysis Molecular genetic testing to confirm mutations in the GCDH gene Enzyme assay (when available) to measure glutaryl-CoA dehydrogenase activity Early detection via newborn screening allows for presymptomatic treatment and dramatically improves outcomes. Treatment Goals The aim of treatment is to: Prevent metabolic crises Avoid neurological deterioration Ensure normal growth and development Manage complications like movement disorders or seizures A coordinated care team typically includes a metabolic specialist, dietitian, neurologist, and paediatrician. Conclusion | Glutaric Aciduria Type 1 Glutaric aciduria type 1 is a serious but manageable metabolic disorder when detected early. With timely diagnosis through newborn screening and prompt initiation of treatment, individuals with glutaric aciduria type 1 can lead significantly healthier lives. Without intervention, however, irreversible neurological damage is likely. Raising awareness among healthcare providers and parents is key to preventing long-term disability. [Next: Causes of Glutaric Aciduria Type 1 →]

Glutaric Aciduria Type 1 Read More »

DNA mutation representing the genetic cause of Glutaric Aciduria Type 1

Causes of Glutaric Aciduria Type 1

Causes of Glutaric Aciduria Type 1 The causes of glutaric aciduria type 1 lie in inherited genetic mutations that affect how the body processes certain amino acids. Glutaric aciduria type 1 is caused by mutations in the GCDH gene, which result in a deficiency or complete lack of the enzyme glutaryl-CoA dehydrogenase. This enzyme is essential for the breakdown of lysine, hydroxylysine, and tryptophan—amino acids that are part of our regular diet and necessary for growth and development. When this enzyme is absent or not functioning correctly, toxic by-products build up in the body, particularly in the brain. The accumulation of these substances, especially glutaric acid and 3-hydroxyglutaric acid, causes damage to brain tissue and impairs motor control. Understanding the causes of glutaric aciduria type 1 is crucial for both treatment and family planning. Genetic Inheritance Pattern Glutaric aciduria type 1 is inherited in an autosomal recessive manner. This means: A child must inherit two copies of the defective gene, one from each parent, to develop the disorder If both parents are carriers (having one normal and one defective copy), there is: A 25% chance the child will have the condition A 50% chance the child will be a carrier A 25% chance the child will inherit two normal genes Carrier parents typically show no symptoms and are unaware they carry the faulty gene until a child is affected. Mutations in the GCDH Gene The GCDH gene provides instructions for producing the enzyme glutaryl-CoA dehydrogenase. This enzyme is active in mitochondria—the energy-producing centres of cells—and is involved in: Breaking down lysine, hydroxylysine, and tryptophan Preventing the build-up of glutaric acid, which is toxic in high amounts Over 200 different mutations in the GCDH gene have been identified. The severity of glutaric aciduria type 1 may depend on the nature of the mutation: Null mutations (producing no enzyme at all) tend to result in more severe outcomes Missense mutations (producing partially functioning enzymes) may result in milder disease Genetic testing allows families to identify the specific mutation involved, which can help with prognosis and inform future pregnancies. Population and Ethnic Factors Certain populations have a higher incidence of glutaric aciduria type 1 due to the founder effect, where a mutation becomes more common in a closed population over generations: Amish and Mennonite communities in the United States Specific regions in Sweden and Turkey North African, Middle Eastern, and South Asian populations with high rates of consanguinity In these groups, routine carrier screening may be offered as part of antenatal or pre-marital counselling programmes. Environmental and Dietary Triggers While the genetic mutation is the underlying cause, environmental stressors often act as triggers for symptoms in children who have not yet been diagnosed or treated. These include: Infections, particularly viral illnesses with fever Vaccinations, if not managed appropriately in undiagnosed children Fasting or poor feeding, especially during infancy High protein intake, which increases the burden of amino acid breakdown These triggers can precipitate a metabolic crisis, characterised by rapid neurological decline, often occurring between 6 and 24 months of age. Role of Newborn Screening In regions where newborn screening is available, glutaric aciduria type 1 can be detected before symptoms develop. Early detection allows: Dietary restrictions to be introduced Emergency regimens during illness to be prepared Neurological outcomes to be significantly improved Parents of affected children are also counselled to seek early care during fevers or infections to prevent metabolic decompensation. Importance of Genetic Counselling When a child is diagnosed with glutaric aciduria type 1, the entire family may benefit from genetic counselling. This involves: Understanding the pattern of inheritance Offering carrier testing to siblings or extended family members Discussing options for prenatal diagnosis in future pregnancies Planning for preimplantation genetic diagnosis (PGD) if desired In populations with higher prevalence, preconception screening programmes may help reduce the incidence of affected births. Summary of Causes Cause Category Description Genetic mutation Mutation in the GCDH gene affects enzyme production Autosomal recessive Requires two defective copies to cause the disease Environmental triggers Illness, fasting, or high-protein diets may trigger symptoms High-risk populations Founder effect increases prevalence in certain groups Inheritance risk 25% if both parents are carriers Conclusion | Causes of Glutaric Aciduria Type 1 The causes of glutaric aciduria type 1 are rooted in genetic mutations that disrupt amino acid metabolism. While the condition itself is rare, its impact can be profound if left untreated. Early diagnosis through newborn screening, coupled with awareness of the causes of glutaric aciduria type 1, allows for preventive strategies that can dramatically improve outcomes and quality of life. [Next: Symptoms of Glutaric Aciduria Type 1→]

Causes of Glutaric Aciduria Type 1 Read More »

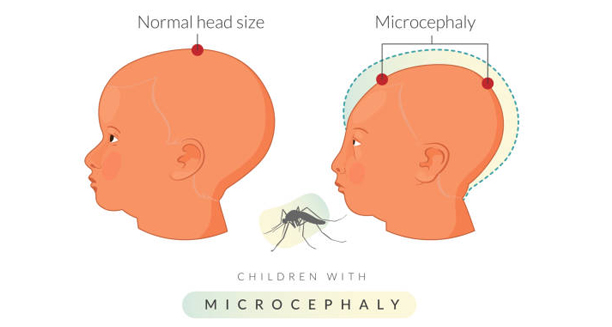
Illustration comparing normal head size to microcephaly in children

Symptoms of Glutaric Aciduria Type 1

Symptoms of Glutaric Aciduria Type 1 The symptoms of glutaric aciduria type 1 can vary widely from person to person, making early detection both crucial and challenging. In most affected children, the symptoms of glutaric aciduria type 1 become apparent during infancy or early childhood, often triggered by common illnesses such as fevers or respiratory infections. Without early diagnosis and management, the disease can cause severe, irreversible neurological damage. Glutaric aciduria type 1 is a metabolic disorder that disrupts the breakdown of certain amino acids, leading to the accumulation of toxic substances in the brain. The parts of the brain most affected are the basal ganglia, which help control movement. As a result, many of the hallmark symptoms involve motor function and coordination, but the condition can also impact growth, cognition, and behaviour. Early Signs in Infancy Some infants may show signs of glutaric aciduria type 1 from birth, while others appear healthy until a “triggering event” causes a sudden deterioration. Early signs include: Macrocephaly (an abnormally large head): Often one of the earliest clues Poor feeding or vomiting during infancy Hypotonia (reduced muscle tone), making the infant appear floppy Mild developmental delays, particularly in motor milestones like sitting or crawling Increased irritability or lethargy, especially during minor illnesses Macrocephaly is especially important to note, as it may precede neurological decline even in otherwise asymptomatic infants. Symptoms Triggered by Metabolic Crises A metabolic crisis is often the event that reveals the condition. These crises typically occur during times of physiological stress, such as infections, immunisations, fasting, or trauma. During a metabolic crisis, symptoms can appear suddenly and escalate rapidly: Loss of motor skills: Previously acquired abilities like sitting, walking, or grasping may regress Dystonia: Involuntary muscle contractions leading to twisted, rigid postures Chorea or athetosis: Jerky or writhing movements Seizures: Common in acute phases, often difficult to control Coma: In severe cases, untreated crises can lead to unconsciousness A single crisis can result in lasting brain damage, with most of the injury occurring in the basal ganglia. This can lead to permanent motor impairment. Long-Term Neurological Manifestations Children who experience a crisis, or those with delayed diagnosis, may develop chronic symptoms such as: Spasticity or stiffness of the limbs Dystonic cerebral palsy, which can impair walking and fine motor skills Poor balance and coordination Swallowing difficulties (dysphagia) and risk of aspiration Speech delays or difficulty speaking clearly In some children, these symptoms are progressive, particularly if the disorder is not managed carefully through diet and medical therapy. Cognitive and Behavioural Features While many individuals with glutaric aciduria type 1 have normal intelligence, cognitive and behavioural concerns can still arise: Learning difficulties, particularly with tasks requiring motor planning or attention Memory issues, especially in those with significant neurological injury Hyperactivity or impulsivity, sometimes misdiagnosed as ADHD Emotional distress, stemming from communication challenges or physical limitations Some children may require special educational support or behavioural therapy to help them reach their full potential. Adult Presentation Though rare, some individuals are not diagnosed until adolescence or adulthood. In these cases, symptoms may be milder or atypical: Mild tremors Subtle balance issues Fatigue or poor exercise tolerance Occasional speech changes or stiffness Adult-onset cases tend to be less severe but still benefit from metabolic management and nutritional intervention. Importance of Early Recognition Prompt recognition of the symptoms of glutaric aciduria type 1 is essential to prevent irreversible damage. Early symptoms such as macrocephaly, feeding difficulties, and developmental delays should prompt metabolic testing. In families with known GCDH mutations, even subtle changes warrant medical review. Neonatal screening has made early detection more achievable, dramatically reducing the number of children who suffer metabolic crises. Monitoring Symptoms Over Time Children with glutaric aciduria type 1 require lifelong monitoring. Healthcare teams track: Growth and head circumference Motor and cognitive development Nutritional status Frequency and severity of illnesses Adherence to dietary restrictions and emergency plans With careful oversight, many children remain stable and avoid further neurological decline. Conclusion | Symptoms of Glutaric Aciduria Type 1 The symptoms of glutaric aciduria type 1 range from early subtle signs like macrocephaly to sudden, life-altering neurological crises. Recognising the early warning signs and intervening before a crisis occurs is key to protecting brain function. Once diagnosed, ongoing attention to the symptoms of glutaric aciduria type 1 helps families and clinicians manage the condition and maintain a good quality of life. [Next: Diagnosis of Glutaric Aciduria Type 1 →]

Symptoms of Glutaric Aciduria Type 1 Read More »

Doctor examining newborn baby with a stethoscope

Diagnosis of Glutaric Aciduria Type 1

Diagnosis of Glutaric Aciduria Type 1 The diagnosis of glutaric aciduria type 1 is essential for preventing serious neurological complications and enabling early treatment. In many countries, the diagnosis of glutaric aciduria type 1 is now possible through routine newborn screening, which has significantly improved outcomes by identifying affected infants before symptoms develop. A deficiency in the enzyme glutaryl-CoA dehydrogenase causes glutaric aciduria type 1, leading to the accumulation of toxic compounds in the body. If undetected, these substances can damage the brain, particularly the basal ganglia, leading to permanent motor disability. Early and accurate diagnosis ensures timely interventions that can prevent irreversible injury. Newborn Screening In countries with comprehensive newborn screening programmes, diagnosis usually begins in the first days of life: Dried blood spot testing (heel prick test) uses tandem mass spectrometry to detect elevated levels of glutaric acid derivatives Screening typically identifies markers such as glutaric acid, 3-hydroxyglutaric acid, and C5DC-carnitine Positive results trigger confirmatory testing and immediate referral to a metabolic specialist Early detection allows treatment to begin before a metabolic crisis occurs, offering the best chance at normal development. Biochemical Testing In addition to screening, diagnostic biochemical tests confirm the presence of the condition: 1. Urine Organic Acid Analysis Performed using gas chromatography–mass spectrometry (GC-MS) Detects elevated glutaric acid, 3-hydroxyglutaric acid, and glutaconic acid 2. Plasma Acylcarnitine Profile Elevated glutarylcarnitine (C5DC) is a hallmark of the condition Supports the urine analysis findings These tests are non-invasive and form the cornerstone of diagnosis in symptomatic individuals and newborns flagged during screening. Enzyme Assay Where available, direct measurement of glutaryl-CoA dehydrogenase activity in: Fibroblasts (from a skin biopsy) White blood cells (leukocytes) Clinicians use this functional assay to confirm the deficiency and possibly predict disease severity, but genetic testing is now more common and less invasive. Genetic Testing Molecular genetic analysis of the GCDH gene: Confirms the presence of pathogenic mutations Can detect carriers within the family Supports prenatal diagnosis in future pregnancies Identifies genotype–phenotype correlations that may influence management Researchers have reported over 200 mutations, with some causing milder or more severe clinical outcomes Neuroimaging For children presenting with symptoms before diagnosis, MRI of the brain can be useful: Shows characteristic changes in the basal ganglia May reveal widening of the Sylvian fissures (open operculum) Helps differentiate glutaric aciduria type 1 from other neurological conditions Doctors typically do not require an MRI if screening confirms the diagnosis and the patient shows no symptoms. Differential Diagnosis Symptoms such as macrocephaly, dystonia, and regression may also occur in other conditions. Therefore, it is important to rule out: Other organic acidurias, such as methylmalonic or propionic aciduria Mitochondrial disorders Perinatal brain injury Cerebral palsy Doctors ensure accurate diagnosis so they can quickly implement targeted dietary and emergency treatment plans. Family Testing and Genetic Counselling Doctors recommend family screening as soon as they confirm a diagnosis: Doctors can test parents and siblings to determine their carrier status Genetic counselling provides information on recurrence risks Genetic counselors can offer prenatal testing or preimplantation genetic diagnosis (PGD) for future pregnancies Counselling also helps families understand the implications of the diagnosis and the importance of treatment adherence. Follow-Up After Diagnosis Following diagnosis: A personalised management plan is developed Regular monitoring of growth, development, and metabolic markers is initiated Emergency protocols are prepared for illness or fasting Nutritional therapy is started immediately Ongoing education for parents, caregivers, and schools ensures the child’s needs are met in all environments. Conclusion | Diagnosis of Glutaric Aciduria Type 1 The diagnosis of glutaric aciduria type 1 is most effective when made early through newborn screening. Furthermore, followed by confirmatory biochemical and genetic testing. Timely and accurate diagnosis of glutaric aciduria type 1 enables intervention before the onset of serious neurological symptoms, improving outcomes and quality of life. With proper diagnosis, families can be empowered to manage the condition confidently and proactively. [Next: Treatment of Glutaric Aciduria Type 1→]

Diagnosis of Glutaric Aciduria Type 1 Read More »

Brain model and reflex hammer used in neurological assessments

Treatment of Glutaric Aciduria Type 1

Treatment of Glutaric Aciduria Type 1 The treatment of glutaric aciduria type 1 focuses on preventing metabolic crises and minimising the accumulation of toxic metabolites that can damage the brain. Because the condition affects how the body breaks down certain amino acids, the treatment of glutaric aciduria type 1 centres around dietary management, emergency protocols, and long-term neurological support. When implemented early—ideally before symptoms appear—this approach can significantly reduce or prevent neurological complications. Glutaric aciduria type 1 is caused by a deficiency of the enzyme glutaryl-CoA dehydrogenase, which is necessary for breaking down lysine, hydroxylysine, and tryptophan. Without proper treatment, toxic compounds like glutaric acid build up and cause damage, especially in the basal ganglia of the brain. However, with early diagnosis and a dedicated management plan, many children can develop normally and lead fulfilling lives. Dietary Management The cornerstone of treatment is a protein-restricted diet that limits the intake of lysine and tryptophan, the amino acids that lead to toxic metabolite production. 1. Amino Acid-Modified Medical Formula Special formulas provide all essential nutrients while limiting lysine and tryptophan These are typically prescribed and adjusted by a metabolic dietitian Often used from infancy through early childhood, and sometimes lifelong 2. Natural Protein Restriction Natural foods high in protein—especially meat, eggs, cheese, and legumes—are restricted The exact amount of allowed protein depends on age, growth rate, and plasma amino acid levels Protein needs are closely monitored to ensure growth and development continue 3. L-Carnitine Supplementation Many patients are prescribed L-carnitine, which helps remove toxic compounds from the body It plays a role in energy production and may reduce the buildup of harmful metabolites Regular blood tests help adjust the dose and monitor for deficiency Diet must be supervised regularly by a specialist team to ensure it remains balanced, effective, and appropriate for the child’s growth and health status. Emergency Illness Protocols Metabolic crises often occur during illness, injury, surgery, or fasting. Therefore, all individuals with glutaric aciduria type 1 must have an emergency treatment plan: Immediate hospitalisation if fever, vomiting, or poor feeding occurs Intravenous glucose to prevent the body from breaking down protein for energy Avoidance of fasting, even for short periods Frequent meals and snacks during illness, with emergency feeds as needed Use of an emergency letter or care plan to inform clinicians unfamiliar with the condition These interventions can prevent acute encephalopathy, the primary cause of neurological damage in untreated children. Monitoring and Follow-Up Successful treatment requires ongoing evaluation by a multidisciplinary team. Routine follow-up includes: Growth measurements and nutritional assessment Plasma amino acid levels to adjust dietary plans Monitoring of carnitine levels and supplementation response Regular developmental assessments and neurological evaluations MRI scans, if needed, to monitor brain structure Careful long-term management improves quality of life and helps detect and address any emerging complications early. Neurological and Supportive Therapies Even with optimal management, some individuals develop neurological symptoms and benefit from additional therapies: Physiotherapy and occupational therapy to improve mobility and coordination Speech and language therapy, particularly if dysarthria or communication delays are present Assistive devices, such as walkers or wheelchairs, if movement is limited Special education support for those with learning difficulties or motor impairments Early and consistent therapeutic intervention can dramatically improve independence and participation in school and daily life. Family Education and Emergency Planning Educating families is vital to effective care. This includes: Training parents and caregivers on emergency feeding plans and when to seek hospital care Ensuring that schools, nurseries, and extended family understand the child’s needs Providing written emergency protocols and alert bracelets Encouraging families to carry a “metabolic emergency pack” with supplies and instructions Empowered families are better prepared to act quickly during critical moments and reduce the risk of serious outcomes. Transition to Adult Care As children grow, treatment evolves. In adolescence and adulthood: The strictest dietary restrictions may be relaxed, depending on clinical history and risk Emergency protocols remain important, especially during surgery or illness Psychological support may be needed during the transition to adult healthcare services Coordination between paediatric and adult metabolic teams ensures continuity of care and reduces the chance of lapses in treatment adherence. Conclusion | Treatment of Glutaric Aciduria Type 1 The treatment of glutaric aciduria type 1 requires a comprehensive, lifelong approach that includes dietary restriction, emergency planning, and close monitoring. With early diagnosis and careful adherence, the treatment of glutaric aciduria type 1 can significantly reduce the risk of neurological complications and enable affected individuals to live healthy, productive lives. Early intervention saves brain function—making awareness, family education, and proactive care essential. [Next: Complications of Glutaric Aciduria Type 1 →]

Treatment of Glutaric Aciduria Type 1 Read More »

Elderly woman holding leg in pain while seated on a couch

Complications of Glutaric Aciduria Type 1

Complications of Glutaric Aciduria Type 1 The complications of glutaric aciduria type 1 can be severe, especially if the condition is undiagnosed or inadequately managed. Most of the serious outcomes are neurological and often irreversible, but with early diagnosis and proper treatment, many of the complications of glutaric aciduria type 1 can be avoided entirely. Glutaric aciduria type 1 is caused by a defect in the enzyme responsible for breaking down certain amino acids, resulting in the build-up of toxic compounds. These substances damage the basal ganglia, the part of the brain responsible for movement control. Preventing or limiting this damage is the primary goal of lifelong management. If missed or mismanaged, however, complications can profoundly affect physical, cognitive, and social functioning. 1. Dystonic Cerebral Palsy One of the most common and debilitating complications is dystonic cerebral palsy, a movement disorder that results from damage to the basal ganglia: Muscle stiffness and twisting movements (dystonia) Involuntary contractions that interfere with mobility Postural abnormalities and joint contractures Pain or discomfort during movement Dystonia typically develops after a metabolic crisis and can be permanent. Physical therapy and medications such as muscle relaxants or botulinum toxin may be required to manage symptoms. 2. Developmental Delays Children who experience metabolic crises may suffer: Delays in walking, speaking, or self-care skills Fine motor difficulties, such as writing or buttoning clothing Intellectual disability, in more severe cases Developmental progress varies widely, but early intervention with therapy and special education often improves outcomes. 3. Seizures Epileptic seizures may occur during or after a metabolic crisis. Seizures can be: Focal or generalised Frequent or rare Responsive or resistant to medication Seizure activity may further impair learning, behaviour, and motor coordination. Long-term neurological follow-up is essential. 4. Swallowing Difficulties and Nutrition Issues Damage to motor control can result in: Dysphagia (difficulty swallowing), increasing the risk of aspiration Feeding problems, which may lead to poor growth The need for feeding tubes in severe cases Nutritional deficits can affect immune function, growth, and overall energy levels. Speech and feeding therapists can offer valuable support. 5. Orthopaedic Problems Over time, muscle imbalance from dystonia and spasticity can lead to: Joint deformities Scoliosis Hip dislocation Orthopaedic management may include physiotherapy, braces, or surgical interventions in more severe cases. 6. Behavioural and Emotional Difficulties Children and adolescents with chronic health conditions may experience: Frustration or depression, particularly if mobility or communication is affected Anxiety, especially about illness or social participation Behavioural issues, such as aggression or withdrawal Support from psychologists, social workers, and peer groups can improve emotional resilience and quality of life. 7. Increased Risk During Illness Even well-managed individuals are vulnerable to complications during: Fever, vomiting, or fasting, which can trigger metabolic decompensation Surgery or trauma, which increases energy demand and stress Delays in emergency treatment, which may lead to permanent damage Every illness must be treated promptly with emergency glucose therapy and metabolic protocols. 8. Reduced Independence in Adulthood Some individuals, especially those with neurological injury, may require: Assisted living or long-term care Support with daily activities, such as dressing or bathing Vocational rehabilitation or specialised education programmes However, many affected individuals can live semi-independently or independently if properly supported and treated from an early age. Preventing Complications While these complications are serious, most are preventable. Prevention includes: Early diagnosis, ideally through newborn screening Strict dietary and emergency management Prompt hospital care during illness Regular monitoring and supportive therapies Family education is key—knowing how to manage illness, recognise danger signs, and communicate with healthcare professionals can change outcomes dramatically. Conclusion | Complications of Glutaric Aciduria Type 1 The complications of glutaric aciduria type 1 can affect physical mobility, cognitive development, emotional wellbeing, and overall independence. But with early detection, proactive management, and lifelong support, many of these complications can be reduced or completely avoided. Understanding and preventing the complications of glutaric aciduria type 1 remains central to improving quality of life and long-term prognosis. [Next: Back to Overview →]

Complications of Glutaric Aciduria Type 1 Read More »

Doctor examining young boy’s ear with an otoscope

Glue Ear

Glue Ear Glue ear is a common condition in children where the middle ear becomes filled with a thick, sticky fluid instead of air. This fluid dampens the movement of the eardrum and the small bones in the ear, leading to temporary hearing loss. Although glue ear is most prevalent in young children, it can also affect adults, especially after infections or upper respiratory issues. The condition is also known as otitis media with effusion (OME) and can occur in one or both ears. It is not usually painful, unlike acute ear infections, which involve inflammation and fever. Despite being painless, glue ear can significantly affect a child’s ability to hear, speak, and learn if it persists for long periods. What Happens Inside the Ear? The ear is divided into three sections: the outer ear, middle ear, and inner ear. The middle ear, located behind the eardrum, normally contains air, which helps conduct sound efficiently to the inner ear. A small tube called the Eustachian tube connects the middle ear to the back of the nose, allowing air to flow in and fluid to drain out. In glue ear: The Eustachian tube becomes blocked or doesn’t function properly Air in the middle ear is replaced with sticky fluid Sound vibrations are muffled by the fluid, reducing hearing clarity The condition may develop slowly over weeks or months Children are more susceptible because their Eustachian tubes are shorter and more horizontal, making drainage less effective. Who Is Affected? Glue ear can affect people of any age but is most common in: Children aged 1 to 6 years Boys more than girls (slightly higher incidence) Children who attend day care or nursery Children with allergies, frequent colds, or family history of ear problems Those with cleft palate, Down’s syndrome, or other craniofacial abnormalities It is estimated that up to 80% of children will experience at least one episode of glue ear before the age of 10. Symptoms of Glue Ear Glue ear often goes unnoticed by parents or caregivers because it doesn’t typically cause pain. However, signs to watch for include: Muffled hearing or selective listening Delayed speech or language development Poor attention or concentration Frustration, behavioural changes, or social withdrawal Balance issues in younger children Talking loudly or turning up the volume on electronic devices In school-aged children, teachers may be the first to notice that a child is not responding appropriately in class. Diagnosis Glue ear is diagnosed through a combination of clinical history and specialised ear examinations: 1. Otoscopy A small lighted scope is used to examine the eardrum The eardrum may appear dull, retracted, or show fluid behind it 2. Tympanometry Measures how well the eardrum moves in response to pressure changes A flat or abnormal curve suggests fluid in the middle ear 3. Hearing Tests Audiometry or age-appropriate hearing assessments evaluate the degree of hearing loss Conductive hearing loss is usually mild to moderate in glue ear Routine hearing checks are especially important for children with speech delays or learning difficulties. Duration and Course of the Condition Glue ear is often self-limiting: Most cases resolve within 6 to 10 weeks If it persists for longer than three months, it may be considered chronic Recurrent episodes are common, particularly during winter or allergy seasons Some children experience glue ear repeatedly, especially during their early school years, but often outgrow the condition as their Eustachian tubes mature. Impact on Development Persistent glue ear can affect: Speech and language development Social interaction Educational performance Children may miss key sounds and words during a critical period of language acquisition, leading to longer-term communication challenges. When to Seek Medical Advice Parents should consult a healthcare provider if: Hearing problems last longer than a few weeks Speech development appears delayed There are concerns about learning or behaviour The child is experiencing frequent ear infections alongside glue ear Early assessment can prevent unnecessary complications and ensure timely intervention if needed. Conclusion | Glue Ear Glue ear is a widespread, often temporary condition that can significantly impact a child’s hearing and development if not identified early. Although glue ear usually resolves without treatment, persistent or recurrent cases require careful monitoring and, in some cases, medical or surgical intervention. Recognising the signs and seeking early advice can ensure children continue to thrive in their communication and learning milestones. [Next: Causes of Glue Ear →]

Glue Ear Read More »

Toddler touching ear with discomfort, showing signs of glue ear

Symptoms of Glue Ear

Symptoms of Glue Ear The symptoms of glue ear can be difficult to detect, particularly in young children who may not be able to describe what they’re experiencing. Many parents and teachers only realise there’s a problem when they observe behavioural changes or delays in communication. Because the symptoms of glue ear often develop gradually and are not painful, they may go unnoticed for weeks or even months. Glue ear (otitis media with effusion) affects the middle ear, where a thick, sticky fluid accumulates behind the eardrum. This fluid prevents sound vibrations from reaching the inner ear effectively, resulting in a mild to moderate hearing loss. Identifying the symptoms early is key to minimising its impact on language development, learning, and social interaction—especially in younger children. Key Indicators in Infants and Toddlers Children under three are the most affected by glue ear, but they are also the least likely to be able to describe what they’re feeling. Parents and caregivers should look for the following signs: Delayed speech or unclear words compared to children of the same age Lack of response when spoken to from behind or in noisy environments Startling only when they see someone, not when they hear them Turning the TV volume up unusually high Frequent tugging or rubbing of the ears, although this is less common than with infections Clumsiness or poor balance, since the middle ear also helps with equilibrium Many of these signs may also be seen in children with general hearing loss, so it’s important to have a proper diagnosis from a healthcare provider. Behavioural Clues in Older Children School-aged children may display a range of subtle behaviours that point to undiagnosed glue ear: Daydreaming or appearing inattentive in class Difficulty following instructions, especially in group settings Speaking loudly or repeating questions unnecessarily Frustration or emotional outbursts due to communication difficulties Mispronunciation of words or avoiding speaking entirely in group settings These behaviours can sometimes be misinterpreted as learning difficulties, ADHD, or oppositional behaviour, when in fact they stem from an undiagnosed hearing impairment. Physical Symptoms Although glue ear itself does not usually cause pain, some physical symptoms can still appear: Muffled hearing, described by older children as having “blocked ears” or “underwater” hearing Tinnitus, or a ringing/buzzing in the ears A feeling of pressure or fullness in the affected ear Mild dizziness or balance problems during movement or play In some cases, a recent cold or upper respiratory infection may have preceded the development of these symptoms, especially during the winter months. Duration and Patterns The symptoms of glue ear can fluctuate: Some children experience them intermittently, especially after viral illnesses Others have persistent issues lasting for several weeks or even months Hearing loss is often bilateral, affecting both ears, although it may be more noticeable in one Parents may find that symptoms are worse during allergy season or when their child has a stuffy nose. Long-Term Impacts If glue ear persists without treatment: Language and speech development can be significantly delayed Children may fall behind in reading, comprehension, and literacy skills Social withdrawal or low confidence may develop Children may struggle with peer interaction or be mislabelled as disruptive The long-term consequences of ignoring the symptoms of glue ear can extend well beyond childhood. That’s why early detection and management are essential. When to Seek Medical Advice You should consult a doctor or audiologist if: Your child has any persistent hearing loss or unclear speech The symptoms have lasted longer than four to six weeks There is evidence of speech delay or learning difficulties Teachers or caregivers have raised concerns about listening or behaviour The child has repeated episodes during the year Referral to an ENT (ear, nose, and throat) specialist may be recommended if symptoms are severe, chronic, or recurrent. Conclusion | Symptoms of Glue Ear The symptoms of glue ear can range from subtle hearing loss to more noticeable speech and behavioural changes. Recognising the early signs allows parents and teachers to seek medical evaluation before the condition affects the child’s development. With close observation and early intervention, the impact of the symptoms of glue ear can be minimised, ensuring better communication and learning outcomes. [Next: Diagnosis of Glue Ear →]

Symptoms of Glue Ear Read More »

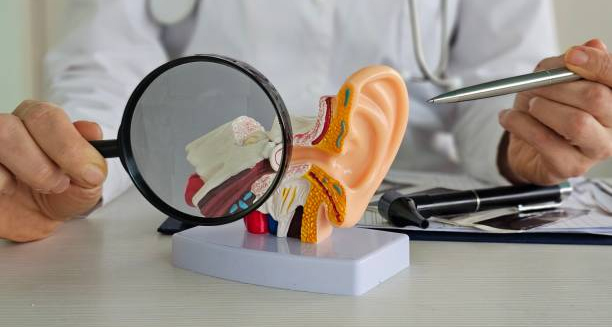
Doctor examining anatomical ear model with magnifying glass to illustrate causes of glue ear

Causes of Glue Ear

Causes of Glue Ear The causes of glue ear primarily involve malfunction or blockage of the Eustachian tube, the channel that connects the middle ear to the back of the nose. When this tube does not work properly, air cannot enter the middle ear, and fluid builds up instead. These mechanical and physiological disruptions are at the heart of most cases of glue ear in both children and adults. While the exact trigger can vary from person to person, several underlying causes contribute to Eustachian tube dysfunction and fluid accumulation. Understanding the causes of glue ear helps guide treatment decisions and prevent recurrent episodes. 1. Eustachian Tube Dysfunction The Eustachian tube plays a key role in balancing air pressure and draining fluid from the middle ear. In children, the tube is shorter, narrower, and more horizontal, making it more likely to become blocked. Common reasons for Eustachian tube dysfunction include: Immaturity of the tube in young children Swelling due to allergies or infections Nasal congestion from colds or flu Adenoid enlargement pressing on or blocking the tube Cleft palate or structural abnormalities interfering with normal function When the tube cannot open properly, negative pressure develops in the middle ear, drawing fluid into the space. 2. Respiratory Infections Frequent upper respiratory tract infections are one of the leading causes of glue ear. These infections inflame the mucous membranes lining the Eustachian tube and middle ear, resulting in: Increased mucus production Swelling and narrowing of the drainage passage Temporary blockage of normal air exchange Children in nursery or school settings are more exposed to colds, which increases their risk of developing glue ear. 3. Allergies Allergic rhinitis (hay fever) and other airborne allergies can lead to chronic inflammation of the nasal passages and Eustachian tubes. This can cause: Persistent fluid build-up in the middle ear Recurring or long-term episodes of glue ear Greater susceptibility to coexisting ear infections In allergic children, symptoms of glue ear may worsen during pollen seasons or when exposed to dust mites, pet dander, or mould. 4. Environmental and Lifestyle Factors Certain environmental exposures can raise the risk of developing glue ear, including: Passive smoking – increases inflammation in the airways and middle ear Bottle feeding in a lying-down position – can allow milk to enter the Eustachian tube Air pollution – irritates the respiratory tract and contributes to inflammation Poor ventilation and damp homes – increase exposure to allergens and infections Lifestyle changes, such as avoiding second-hand smoke and using upright feeding techniques, can help prevent some cases of glue ear. 5. Enlarged Adenoids Adenoids are lymphatic tissue located behind the nasal cavity. In young children, enlarged adenoids can: Physically block the Eustachian tubes Harbour bacteria that increase infection risk Cause chronic nasal obstruction and snoring Surgical removal of the adenoids (adenoidectomy) is sometimes recommended for children with recurrent or persistent glue ear. 6. Recurrent Ear Infections While glue ear itself is not an infection, recurrent ear infections can increase the risk of fluid build-up in the middle ear. Following an infection, the residual inflammation and fluid can persist even after the acute symptoms subside. Children with frequent ear infections may experience cycles of: Infection → fluid retention → temporary improvement → re-infection Breaking this cycle may require antibiotics, grommets, or addressing predisposing factors like allergies or enlarged adenoids. 7. Genetic and Anatomical Factors Some children inherit structural characteristics that make them more prone to glue ear. These may include: Narrow Eustachian tubes Familial tendency toward allergies or sinus issues Craniofacial syndromes such as Down’s syndrome Children with congenital anomalies affecting the skull or palate often require earlier and more proactive ENT (ear, nose, and throat) management. Summary of Key Causes Cause Role in Glue Ear Eustachian tube dysfunction Prevents air flow and fluid drainage Respiratory infections Inflammation and mucus production Allergies Chronic swelling of nasal and ear passages Passive smoking Increases airway inflammation Enlarged adenoids Block drainage and trap bacteria Recurrent ear infections Repeated inflammation and fluid retention Anatomical/genetic predisposition Increased susceptibility due to structure or family history Conclusion | Causes of Glue Ear The causes of glue ear are varied but often involve blockages or inflammation that prevent proper drainage of the middle ear. By identifying and addressing these underlying factors, healthcare professionals can reduce the risk of chronic episodes and help children maintain normal hearing and development. Whether caused by infection, allergy, or anatomy, early recognition of the causes of glue ear supports better outcomes and informed treatment planning. [Next: Symptoms of Glue Ear→]

Causes of Glue Ear Read More »

Scroll to Top