Diagnosis of Glue Ear
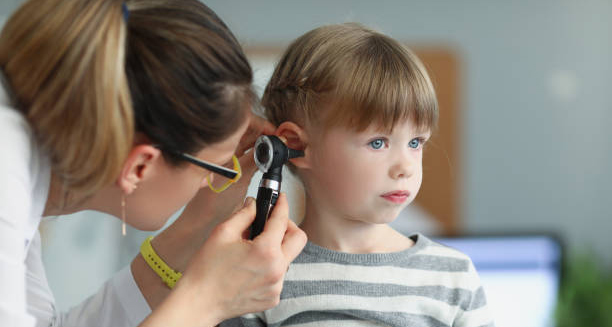
Diagnosis of Glue Ear The diagnosis of glue ear relies on a careful combination of history, clinical examination, and specialised hearing tests. Because many children with this condition appear otherwise healthy, the diagnosis of glue ear is often delayed until a parent, caregiver, or teacher notices something is wrong—typically with hearing, speech, or behaviour. Glue ear (otitis media with effusion) causes a build-up of thick fluid behind the eardrum, reducing its ability to vibrate and conduct sound. Although painless, the condition can significantly affect a child’s ability to hear, especially in noisy settings like classrooms. Early and accurate diagnosis is critical to ensuring timely treatment and preventing long-term developmental issues. First Steps in Clinical Evaluation The diagnosis typically begins with: A detailed medical history, including frequency of colds, allergies, or previous ear infections Observation of any speech delays, listening difficulties, or behavioural concerns Parental and teacher reports regarding academic performance or social interaction A physical examination to check for nasal congestion, mouth breathing, or enlarged tonsils/adenoids These details help determine the likelihood that middle ear fluid is present and affecting hearing. Otoscopy Otoscopy is the first visual tool used by a GP or ENT specialist: A small handheld light is used to view the eardrum (tympanic membrane) In glue ear, the eardrum may appear dull, retracted, fluid-filled, or grey/yellow in colour Air bubbles or fluid levels may also be visible in the middle ear While this method provides immediate clues, it may not confirm the diagnosis on its own. Tympanometry Tympanometry is one of the most important tests for confirming glue ear: It measures how the eardrum responds to changes in air pressure In a healthy ear, the eardrum moves freely, creating a peak in the pressure reading In glue ear, movement is restricted, producing a flat or abnormal trace This test is painless and quick, and it’s suitable for children as young as six months. Audiometry Hearing tests are crucial in determining the degree and type of hearing loss: Pure-tone audiometry is used for children over 3 years The child responds to tones through headphones, allowing the audiologist to map hearing ability across different frequencies In glue ear, the results usually show conductive hearing loss, where sound transmission through the middle ear is impaired For younger children, visual reinforcement audiometry or play audiometry is used to assess hearing in a fun and engaging way. Observation Period Not all cases of glue ear require immediate treatment: If hearing loss is mild and recent, doctors may suggest a “watch and wait” approach for 6–12 weeks In many cases, the fluid clears spontaneously without medical intervention Follow-up appointments and repeat hearing tests help track progress However, prolonged or severe cases often need further evaluation. Additional Investigations If glue ear is persistent or recurrent, additional assessments may include: Speech and language evaluation, especially if the child is underperforming Assessment of the adenoids and tonsils, using nasal endoscopy or X-rays Allergy testing, if seasonal patterns or chronic nasal symptoms are present Children with craniofacial anomalies or developmental conditions may require more comprehensive evaluation and care coordination. When to Refer to a Specialist Referral to an ENT specialist is usually indicated when: Glue ear lasts longer than 3 months Hearing loss exceeds 20–30 decibels There is significant speech delay or academic struggle Episodes recur multiple times a year There is suspicion of anatomical issues (e.g. cleft palate, large adenoids) The specialist may recommend interventions such as grommet insertion or adenoidectomy depending on the severity and recurrence of symptoms. Diagnosis in Adults While less common, glue ear can affect adults, especially following: Air travel or scuba diving Sinus infections or nasal congestion Sudden hearing loss after a cold Diagnosis in adults follows a similar process but may require imaging if symptoms persist or are associated with dizziness or other complications. Conclusion | Diagnosis of Glue Ear The diagnosis of glue ear is based on careful clinical observation, otoscopy, tympanometry, and hearing assessments. Because the condition can affect hearing without causing pain, it is often overlooked. However, an early and accurate diagnosis of glue ear allows for appropriate treatment, minimising the impact on speech, learning, and quality of life. Regular follow-up ensures that temporary hearing loss does not become a long-term barrier to development. [Next: Treatment of Glue Ear→]