Mental Matters

Health Conditions

Find information on various health conditions affecting people of all ages. This category covers causes, symptoms, diagnosis, and management options for physical illnesses and chronic diseases. Get insights to help you understand different health challenges and make informed decisions about your wellbeing.

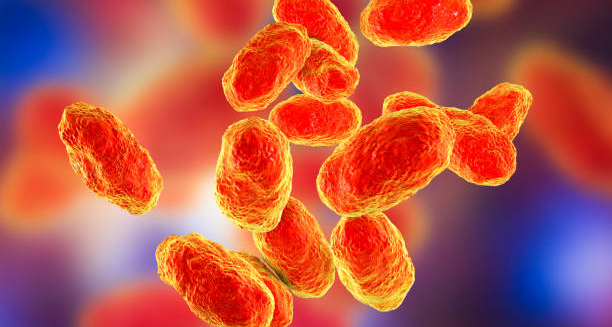
3D illustration of Haemophilus influenzae bacteria, a common cause of epiglottitis

Causes of Epiglottitis

Causes of Epiglottitis The causes of epiglottitis are most often infections, particularly bacterial, but other irritants or injuries can also play a role. Epiglottitis leads to rapid inflammation and swelling of the epiglottis, which can block the upper airway and cause breathing difficulty. Infectious Causes The most common cause is Haemophilus influenzae type b (Hib), especially in children who haven’t been vaccinated. Other bacteria that may cause epiglottitis include: Streptococcus pneumoniae Streptococcus pyogenes (group A strep) Staphylococcus aureus, including MRSA strains In adults, mixed bacterial infections are more frequently observed. Viral infections, such as varicella-zoster or herpes simplex virus, can also trigger inflammation of the epiglottis, though these are less common. Non-Infectious Causes Thermal injury from swallowing very hot food or liquids Chemical burns, often from caustic substances Trauma, such as injury from a foreign object or intubation Allergic reactions, leading to sudden epiglottis swelling, similar to anaphylaxis Risk Factors Incomplete vaccination, especially missing the Hib vaccine Weakened immune system, such as from HIV, cancer, or steroid use Young children, particularly under five years old Older adults, especially those with existing throat or respiratory issues Smoking or alcohol abuse, which may weaken local immune defences Causes of Epiglottitis In South Africa In South Africa, limited access to vaccinations in rural or underserved areas may leave children at higher risk of Hib infection. Additionally, HIV-positive individuals—especially those not on antiretroviral therapy—may be more susceptible to severe bacterial infections like epiglottitis. Improved vaccine coverage, public education, and early medical intervention are key to reducing incidence. Understanding the causes of epiglottitis allows for prevention, rapid diagnosis, and better treatment outcomes—especially when the condition strikes unexpectedly. [Next: Symptoms of Epiglottitis →]

Causes of Epiglottitis Read More »

Woman touching sore throat with red inflammation, showing symptoms of epiglottitis

Symptoms of Epiglottitis

Symptoms of Epiglottitis The symptoms of epiglottitis often come on suddenly and worsen quickly. Since epiglottitis can lead to complete airway blockage, recognising the signs early is essential. In many cases, symptoms may seem like a sore throat or flu at first, but they escalate into a medical emergency within hours. In Children Children typically present with: High fever, often above 38.5°C Severe sore throat, with difficulty swallowing Drooling, as it becomes painful or impossible to swallow saliva Muffled or hoarse voice Stridor, a high-pitched wheezing sound when breathing in Rapid, shallow breathing Tripod position, where the child leans forward with mouth open, chin up, and hands on knees—this helps keep the airway open Anxiety or distress, as the child becomes aware of breathing difficulties Coughing is often minimal or absent, which helps distinguish epiglottitis from croup or other respiratory infections. In Adults Adults may experience: Severe sore throat and neck pain Painful swallowing (odynophagia) Fever and chills Voice changes, including hoarseness or muffling Shortness of breath Difficulty speaking Drooling, especially in severe cases Swollen neck or tenderness in the throat area While adult cases may progress more slowly than in children, airway obstruction is still a real risk and must be treated urgently. Warning Signs of Airway Blockage Seek emergency care immediately if any of the following are present: Gasping or noisy breathing Bluish lips or fingertips (cyanosis) Inability to lie flat Severe restlessness or confusion Fainting or loss of consciousness Symptoms of Epiglottitis In South Africa In South Africa, delayed access to emergency care—especially in rural clinics—can be dangerous for patients with epiglottitis. Prompt referral and emergency transport are essential. Parents and caregivers must be taught to identify symptoms quickly and never delay seeking help for a child with breathing difficulties. Recognising the symptoms of epiglottitis early and acting fast can prevent a fatal airway emergency. Immediate hospital treatment is always required. [Next: Diagnosis of Epiglottitis→]

Symptoms of Epiglottitis Read More »

Doctor examining throat X-ray of a woman with epiglottitis symptoms

Diagnosis of Epiglottitis

Diagnosis of Epiglottitis The diagnosis of epiglottitis must be handled carefully, as any interference with the throat can cause the airway to close completely. Because epiglottitis is a medical emergency, doctors act quickly to confirm the diagnosis while ensuring the airway remains open. In most cases, a clinical diagnosis is made based on symptoms alone. Clinical Evaluation Doctors begin by assessing: Breathing difficulty Stridor (noisy breathing) Drooling Difficulty speaking or swallowing General signs of distress or anxiety In children, the classic “tripod” posture—leaning forward, mouth open, and chin up—is a strong diagnostic clue. The child may also avoid speaking or crying, as both can worsen the airway obstruction. Visual Inspection Direct visual examination of the throat is not recommended in a distressed child, as it could trigger full airway blockage. In a controlled hospital setting, trained specialists may gently examine the throat using a flexible laryngoscope to view the epiglottis. In epiglottitis, the epiglottis appears swollen, red, and “cherry-like.” Imaging If the airway is stable, doctors may use a neck X-ray to look for the “thumb sign,” which indicates swelling of the epiglottis. However, imaging is not always necessary and should never delay treatment. Blood and Swab Tests | Diagnosis of Epiglottitis Once they secure the airway, doctors may take: Blood cultures, to identify the bacteria causing the infection Throat swabs, if safe, to test for bacterial or viral infections Full blood count, to check for raised white blood cells indicating infection In South Africa, rural hospitals may have limited access to ENT specialists. However, trained emergency staff can often recognise the condition and begin life-saving treatment even without advanced testing. The diagnosis of epiglottitis relies on recognising the warning signs and acting fast. A delay in diagnosis can lead to complete airway closure and death. [Next: Treatment of Epiglottitis →]

Diagnosis of Epiglottitis Read More »

Hospitalised patient receiving care for epiglottitis from medical staff

Treatment of Epiglottitis

Treatment of Epiglottitis The treatment of epiglottitis is a medical emergency that focuses on securing the airway, fighting infection, and reducing inflammation. Because epiglottitis can cause sudden and complete airway blockage, treatment must begin as soon as the condition is suspected—often before confirmation. Airway Management The first and most urgent priority is to ensure the patient can breathe. In most cases: The patient is taken to an operating theatre or intensive care unit An anaesthetist or ENT specialist carefully performs intubation, placing a breathing tube through the mouth into the windpipe In extreme cases where intubation isn’t possible, a tracheostomy (a surgical opening in the neck) is performed to bypass the swollen epiglottis Doctors perform this step under controlled conditions to prevent airway collapse. Hospital Admission and Monitoring Doctors admit all patients with epiglottitis to hospital for continuous observation. Doctors usually place children in an intensive care unit for close monitoring and give oxygen if needed. Antibiotic Therapy Once they secure the airway, doctors start IV antibiotics to treat the underlying bacterial infection. The most commonly used antibiotics include: Ceftriaxone or cefuroxime for broad-spectrum coverage Doctors may add vancomycin to treatment if they suspect MRSA Treatment usually lasts for 7–10 days, starting with IV medication and possibly switching to oral antibiotics once stable Anti-Inflammatory Treatment Doctors may give corticosteroids to reduce swelling and speed up recovery. Although some debate their use, doctors often recommend corticosteroids in severe cases or when intubation has been difficult. Fluids and Nutrition While the patient cannot eat or drink due to the swollen airway, IV fluids provide hydration. Once the swelling reduces and doctors remove the tube, they gradually introduce soft foods. Treatment of Epiglottitis In South Africa In South Africa, availability of intensive care units and ENT support varies by region. Some rural hospitals stabilise the patient and then transfer them to better-equipped urban centres. Public awareness and early intervention by clinic staff remain key to survival. The treatment of epiglottitis is almost always successful if given promptly. Most patients recover within a few days to a week if they receive timely and appropriate care. [Next: Complications of Epiglottitis →]

Treatment of Epiglottitis Read More »

Woman recovering from a tracheostomy due to complications of epiglottitis

Complications of Epiglottitis

Complications of Epiglottitis The complications of epiglottitis can be severe and life-threatening. Because epiglottitis directly affects the airway, the greatest risk is complete blockage, which can result in death within hours. With early diagnosis and modern treatment, however, most complications are preventable. Airway Obstruction The most dangerous complication is complete airway blockage. Swelling of the epiglottis and surrounding tissues can seal off the windpipe entirely, making it impossible to breathe. This is why securing the airway is the top priority in all suspected cases. Without rapid intervention, respiratory arrest can occur—particularly in children, whose airways are smaller and more easily blocked. Respiratory Failure If the airway is not opened quickly enough, oxygen levels in the body may drop dangerously. This can lead to: Confusion or unconsciousness Brain injury due to lack of oxygen Cardiac arrest Spread of Infection In untreated or advanced cases, the infection may spread beyond the epiglottis to nearby areas, leading to: Pneumonia Abscess formation in the neck or chest Bacteraemia (bacteria in the bloodstream) Sepsis, a life-threatening body-wide response to infection Prompt antibiotic treatment greatly reduces the risk of these complications. Long-Term Issues After Recovery Most people recover fully from epiglottitis with no lasting effects. However, complications during treatment—especially prolonged intubation or tracheostomy—can occasionally result in: Hoarseness or voice changes Scarring of the throat or windpipe Emotional trauma, especially in children who undergo emergency procedures Follow-up with a paediatrician or ENT specialist may be advised to monitor for any long-term concerns. Complications of Epiglottitis In South Africa In South Africa, delayed treatment or lack of emergency airway access increases the risk of complications. Children in rural areas face greater risk when doctors misdiagnose their symptoms as flu or croup. Strengthening training for clinic staff, ensuring vaccine coverage, and improving referral systems can help reduce poor outcomes. The complications of epiglottitis are largely preventable. With rapid medical care and proper follow-up, doctors can help most patients recover completely and save lives even in emergency scenarios. [Next: Back to Overview →]

Complications of Epiglottitis Read More »

Stylised icon representing male reproductive system with a curved arrow indicating inflammation

Epididymitis

Epididymitis The condition Epididymitis is the inflammation of the epididymis—the long, coiled tube at the back of the testicle that stores and transports sperm. Epididymitis is a common condition that can cause pain, swelling, and tenderness in the scrotum. It can affect males of all ages, but it is most frequently diagnosed in men between the ages of 15 and 35. This condition is usually caused by a bacterial infection, including sexually transmitted infections (STIs) like chlamydia or gonorrhoea in younger men, or urinary tract infections (UTIs) in older men. Less commonly, it may result from trauma, viral infections, or prolonged use of catheters. Symptoms typically begin suddenly and may worsen quickly if left untreated. The scrotum may become swollen, red, and warm to the touch. Pain may radiate to the groin or lower abdomen. Some cases also involve fever, painful urination, or discharge from the penis. Epididymitis In South Africa, epididymitis is regularly seen in both public and private healthcare settings. It is especially important to treat infections early to avoid complications like chronic pain or infertility. Awareness and access to sexual health services can help prevent many cases. Understanding epididymitis ensures early recognition, effective treatment, and protection of long-term reproductive health. [Next: Causes of Epididymitis →]

Epididymitis Read More »

Man holding lower back in pain, indicating possible urinary tract or reproductive infection

Causes of Epididymitis

Causes of Epididymitis The causes of epididymitis vary depending on a person’s age, sexual activity, and overall health. Epididymitis most commonly results from infections—either sexually transmitted or related to the urinary tract—but it can also develop without infection in some cases. Sexually Transmitted Infections (STIs) In men under 35, epididymitis is often caused by sexually transmitted bacteria, including: Chlamydia trachomatis Neisseria gonorrhoeae These infections can travel through the urethra and into the reproductive tract, inflaming the epididymis. STIs are a leading cause among sexually active young men, particularly in areas with limited access to regular screening and sexual health education. Urinary Tract Infections (UTIs) In older men, epididymitis is commonly associated with: Escherichia coli (E. coli) and other common UTI-causing bacteria Enlarged prostate (BPH), which can lead to urine retention and increased risk of infection Catheter use or recent urological procedures Infections from the bladder or prostate may spread backward to the epididymis, causing inflammation and pain. Non-Infectious causes of Epididymitis Less common causes include: Trauma or injury to the groin Heavy lifting or straining, which may cause urine to flow backward (chemical epididymitis) Certain medications, such as amiodarone, a heart drug known to irritate the epididymis in high doses Tuberculosis (TB), which can cause chronic epididymitis in rare cases—more commonly seen in South Africa due to the high TB burden Risk Factors Several factors increase the risk of developing epididymitis: Having multiple sexual partners or unprotected sex History of urinary tract infections Recent prostate or bladder surgery Use of urinary catheters Prolonged sitting (such as long road trips or desk jobs) In South Africa, men in rural communities may delay seeking treatment due to stigma or poor access to healthcare, which increases the risk of complications and further spread of infection. Understanding the causes of epididymitis helps doctors identify the most effective treatment and helps individuals take steps to prevent future episodes. [Next: Symptoms of Epididymitis →]

Causes of Epididymitis Read More »

Man sitting on bed holding his groin in pain, indicating symptoms of epididymitis

Symptoms of Epididymitis

Symptoms of Epididymitis The symptoms of epididymitis typically develop quickly and can cause significant discomfort. Since epididymitis affects the testicles and surrounding structures, it often leads to both local and general symptoms that should never be ignored. Early treatment can prevent severe complications, including infertility or long-term pain. Common Symptoms Scrotal pain – Usually starts on one side and may spread to the groin or lower abdomen. Swelling and redness – The affected side of the scrotum may become visibly larger, red, and warm to the touch. Tenderness – Even gentle touch or movement may cause significant discomfort. Painful urination – A burning sensation or discomfort when passing urine. Increased urinary frequency or urgency – The urge to urinate more often, especially with accompanying discomfort. Discharge from the penis – May be present if the cause is a sexually transmitted infection. Blood in semen – Though uncommon, some men notice pink or red streaks in ejaculate. Fever and chills – Indicate that the infection is more widespread or severe. In Chronic Cases Some men may develop chronic epididymitis, lasting more than six weeks. Symptoms include: Persistent dull pain or heaviness in the scrotum Occasional swelling Discomfort during or after ejaculation Anxiety or distress about fertility or sexual performance Chronic cases may occur after incomplete treatment of an initial infection or due to non-infectious inflammation. Symptoms of Epididymitis in Children In prepubescent boys, epididymitis is rare but can happen due to trauma, urinary reflux, or structural abnormalities. Symptoms may be mistaken for testicular torsion, which is a medical emergency, so urgent evaluation is essential. In South Africa Delayed treatment is a concern in many rural areas. Men may be reluctant to speak up about testicular symptoms due to cultural stigma or fear of being judged. As a result, many present late with advanced infection or complications. Public education and sexual health awareness campaigns can help reduce this stigma and encourage early diagnosis and treatment. Recognising the symptoms of epididymitis and seeking medical attention promptly can prevent further discomfort and long-term damage. [Next: Diagnosis of Epididymitis→]

Symptoms of Epididymitis Read More »

Man consulting with urologist about groin pain, indicating possible epididymitis

Diagnosis of Epididymitis

Diagnosis of Epididymitis The diagnosis of epididymitis is usually based on a physical examination, patient history, and laboratory tests. Because epididymitis can mimic other serious conditions—such as testicular torsion—accurate and timely diagnosis is crucial, especially in younger patients. Medical History and Symptom Review Doctors begin by asking about: The onset and duration of pain Urinary symptoms, such as burning or frequency Any discharge from the penis Recent sexual activity or known STI exposure History of urinary tract infections, catheter use, or trauma This information helps narrow down the likely cause—whether it’s an STI, UTI, or a non-infectious trigger. Physical Examination During the exam, the doctor will: Check for swelling, tenderness, and warmth in the scrotum Examine both testicles and the epididymis Assess for signs of inflammation or discharge Rule out testicular torsion, a condition where the spermatic cord twists and cuts off blood supply—a surgical emergency that requires immediate attention The Prehn’s sign may be used: lifting the scrotum slightly relieves pain in epididymitis but not in testicular torsion. However, this test alone is not always reliable. Urine and Swab Tests Urinalysis – Detects white blood cells, bacteria, or blood in the urine Urine culture – Identifies the bacteria causing infection NAAT (nucleic acid amplification tests) – Detect chlamydia and gonorrhoea Urethral swab – In cases of discharge, swabs help identify the STI organism These tests help guide antibiotic selection and confirm whether the infection is sexually transmitted or related to a urinary cause. Blood Tests | Diagnosis of Epididymitis A full blood count (FBC) may reveal elevated white cells, indicating infection. CRP or ESR levels can also confirm inflammation. Scrotal Ultrasound Ultrasound with Doppler imaging is the most reliable test to confirm epididymitis and rule out torsion. It shows: Blood flow to the testicles Swelling of the epididymis Fluid build-up around the testicles (hydrocele) In South Africa, access to ultrasound may be limited in rural clinics, causing delays in diagnosis. In such cases, clinical assessment becomes even more important. The diagnosis of epididymitis should be made quickly and confidently. Early treatment prevents complications and offers rapid symptom relief. [Next: Treatment of Epididymitis →]

Diagnosis of Epididymitis Read More »

Close-up of antibiotics and pills used in the treatment of epididymitis

Treatment of Epididymitis

Treatment of Epididymitis The treatment of epididymitis depends on the underlying cause—whether it’s bacterial, sexually transmitted, or non-infectious. Epididymitis is highly treatable, especially when caught early. The main goals are to eliminate infection, relieve pain, and prevent complications. Antibiotics Doctors should begin antibiotic treatment as soon as they suspect a bacterial infection. The choice of antibiotic depends on the patient’s age and likely cause: For sexually active men under 35: Ceftriaxone (single injection) for gonorrhoea Plus doxycycline (100 mg twice daily for 7–14 days) for chlamydia For older men or men with UTIs: Ciprofloxacin or levofloxacin (oral fluoroquinolones) Treatment usually lasts 10–14 days Patients should complete the full course of antibiotics even if symptoms improve early. Supportive Care Pain relief – Paracetamol or ibuprofen helps reduce pain and inflammation Scrotal support – Wearing snug underwear or using a scrotal support sling can relieve pressure Rest – Bed rest for the first few days can speed up healing Cold packs – Reduce swelling and provide pain relief Doctors advise patients to avoid sexual activity until they complete treatment and all symptoms have fully resolved. Treating Sexual Partners If a sexually transmitted infection is the cause, doctors must test and treat the patient’s sexual partners as well. Re-infection is common if partners are untreated. In South Africa, public clinics offer free STI treatment and counselling services. Follow-Up | Treatment of Epididymitis Most patients improve within 48–72 hours of starting antibiotics. If symptoms persist or worsen, additional testing may be needed to rule out: Abscess formation Testicular involvement (orchitis) Tuberculosis-related epididymitis In chronic or recurring cases, referral to a urologist is recommended. The treatment of epididymitis is usually successful with antibiotics and self-care. Early intervention helps avoid long-term issues like infertility or chronic pain. [Next: Complications of Epididymitis →]

Treatment of Epididymitis Read More »

Scroll to Top