Mental Matters

Health Conditions

Find information on various health conditions affecting people of all ages. This category covers causes, symptoms, diagnosis, and management options for physical illnesses and chronic diseases. Get insights to help you understand different health challenges and make informed decisions about your wellbeing.

Treatment of Ejaculation Problems

Treatment of Ejaculation Problems

Treatment of Ejaculation Problems The treatment of ejaculation problems depends on the specific issue and its underlying cause. While ejaculation problems may feel overwhelming, most are treatable with a combination of medical, psychological, and behavioural approaches. Premature Ejaculation This condition often responds well to both therapy and medication. Treatment options include: Behavioural techniques, such as the “stop-start” or “squeeze” method Pelvic floor exercises to improve control Topical anaesthetic creams to reduce penile sensitivity Selective serotonin reuptake inhibitors (SSRIs) prescribed at low doses to delay ejaculation Counselling, especially if anxiety or relationship issues are contributing A combination of techniques often works best. Many men benefit from sexual therapy alongside physical interventions. Delayed Ejaculation This condition may be treated by: Reviewing and adjusting medications, especially antidepressants Psychotherapy for anxiety, depression, or past trauma Improved sexual communication and partner involvement Hormone therapy, if low testosterone is found Encouraging self-awareness and changing patterns around arousal and stimulation can also help. Retrograde Ejaculation Treatment focuses on restoring the forward flow of semen. Options include: Alpha-agonist medications, which help close the bladder neck Treating underlying causes such as diabetes or nerve damage Addressing post-surgical complications where possible For men trying to conceive, fertility specialists may extract sperm from urine or use assisted reproductive techniques. Painful Ejaculation Pain during or after ejaculation may be due to infection, inflammation, or nerve sensitivity. Treatment includes: Antibiotics or anti-inflammatories if prostatitis or urethritis is diagnosed Pelvic floor physiotherapy Pain management through medication or local therapies In rare cases, surgery may be considered if an obstruction or structural issue is identified. Anejaculation Treatment depends on whether the issue is psychological or physical. Options include: Medication changes Penile vibratory stimulation or electroejaculation (in specialised fertility settings) Counselling and couple’s therapy Treatment of Ejaculation Problems Only major centres or private fertility clinics in South Africa typically offer specialised treatments like electroejaculation, limiting access in other areas. However, basic treatment and counselling are available through most GPs and urologists. The treatment of ejaculation problems requires patience, openness, and often a combined approach. With proper care, many men experience full recovery or significant improvement. [Next: Complications of Ejaculation Problems →]


Treatment of Ejaculation Problems Read More »

Complications of Ejaculation Problems

Complications of Ejaculation Problems

Complications of Ejaculation Problems The complications of ejaculation problems go beyond sexual performance—they can affect mental health, relationships, and fertility. While ejaculation problems are not usually dangerous, ignoring them can lead to long-term distress and medical consequences. Emotional and Psychological Impact Men experiencing ejaculation difficulties often suffer from: Low self-esteem or confidence Performance anxiety Embarrassment or shame, leading to avoidance of intimacy Depression or frustration, especially if the problem persists These feelings can create a cycle where the psychological burden worsens the original issue. Partners may feel confused or rejected, resulting in communication breakdowns or sexual dissatisfaction within the relationship. Relationship Strain Couples may experience tension if the problem is not openly discussed. Unresolved ejaculation problems may: Lead to less frequent intimacy Trigger misunderstandings or blame Affect emotional closeness Sexual counselling or couple’s therapy can help restore trust and create shared solutions. Fertility Challenges Some ejaculation issues can make it difficult or impossible to conceive naturally. These include: Anejaculation, where no semen is released Retrograde ejaculation, where sperm enters the bladder Severely delayed ejaculation, which may interfere with timing Couples trying to conceive may need fertility assistance, including sperm retrieval or intrauterine insemination (IUI). In South Africa, access to these services varies widely between public and private healthcare sectors. Medical Complications Painful ejaculation or repeated retrograde ejaculation may indicate: Prostate infection or inflammation Nerve damage, especially in men with diabetes or spinal injuries Medication side effects, particularly from antidepressants Ignoring these signs can lead to worsening health. Pain, blood in semen, or drastic changes in ejaculation should always prompt medical assessment. Social Impact | Complications of Ejaculation Problems Stigma around male sexual health prevents many men from seeking help. In South Africa, cultural expectations and masculinity norms often discourage discussion of such topics. As a result, men may delay care until the problem becomes severe. Awareness campaigns, men’s clinics, and inclusive health education can help reduce the stigma. When men feel supported, they’re more likely to speak up and receive the help they need. Addressing the complications of ejaculation problems is not just about improving sex—it’s about protecting mental health, supporting relationships, and improving quality of life. Most cases are treatable, especially when diagnosed early and managed by a supportive healthcare team. [Next: Back to Overview →]

Complications of Ejaculation Problems Read More »

Ehlers-Danlos Syndromes

Ehlers-Danlos Syndromes

Ehlers-Danlos Syndromes Ehlers-Danlos syndromes (EDS) are a group of rare genetic disorders that affect the connective tissues supporting the skin, joints, blood vessels, and internal organs. People with Ehlers-Danlos syndromes typically have overly flexible joints, fragile skin, and an increased risk of bruising, scarring, and other complications due to weakened collagen. Collagen is a key protein in connective tissue. It provides structure and strength throughout the body. In EDS, genetic mutations disrupt collagen production or processing, making tissues unusually stretchy or fragile. There are several different types of EDS, each linked to a specific gene or protein abnormality. The most common form is hypermobile EDS (hEDS), which causes joint instability, frequent dislocations, and chronic pain. Other forms include: Classical EDS, which features skin that stretches easily and heals with distinctive scars Vascular EDS, a rare and life-threatening type affecting blood vessels and organs Kyphoscoliotic EDS, which causes severe spinal curvature and muscle weakness Arthrochalasia and dermatosparaxis types, which are very rare and present in early infancy EDS can range in severity. Some people have mild symptoms, while others experience daily joint pain, fatigue, or serious complications. Diagnosis can be difficult, especially for milder types like hEDS, which may be mistaken for general joint hypermobility or growing pains in children. Ehlers-Danlos Syndromes In South Africa, EDS remains underdiagnosed due to limited awareness among healthcare providers and the public. Access to genetic testing is often restricted to private clinics or university hospitals, making it harder for patients in rural areas to receive confirmation. Living with EDS requires long-term care, often involving physiotherapy, pain management, and support for mental health. Although there is no cure, early recognition and appropriate care can improve quality of life and prevent complications. Understanding Ehlers-Danlos syndromes helps patients, doctors, and families take proactive steps to manage symptoms, reduce injuries, and plan for long-term health. [Next: Causes of Ehlers-Danlos Syndromes →]

Ehlers-Danlos Syndromes Read More »

Causes of Ehlers-Danlos Syndromes

Causes of Ehlers-Danlos Syndromes

Causes of Ehlers-Danlos Syndromes The causes of Ehlers-Danlos syndromes lie in inherited genetic mutations that affect the structure, production, or processing of collagen. Collagen is essential for strong and elastic connective tissue. In Ehlers-Danlos syndromes, defects in collagen-related genes weaken the body’s connective tissues, leading to joint, skin, and vascular problems. EDS is a genetic condition, meaning it is passed down through families. Depending on the type, it can be inherited in one of two ways: Autosomal dominant, where a single copy of the faulty gene from one parent is enough to cause the condition Autosomal recessive, where the child must inherit faulty genes from both parents to be affected For example: Classical EDS is usually inherited in a dominant pattern and involves mutations in the COL5A1 or COL5A2 genes. Vascular EDS is caused by mutations in the COL3A1 gene, affecting the walls of blood vessels. Kyphoscoliotic EDS is typically recessive and caused by mutations in the PLOD1 gene, affecting enzymes needed for collagen modification. In hypermobile EDS, the most common type, no specific gene has yet been identified. Diagnosis is based on clinical features, including joint hypermobility, frequent dislocations, and chronic pain. Research continues to uncover the genetic basis of hEDS and how it relates to other connective tissue disorders. Spontaneous mutations can also cause EDS, even with no family history. In these cases, the gene changes during conception or early development, meaning the affected person is the first in their family to carry the mutation. In South Africa and other countries with limited access to genetic services, confirming the cause of EDS can be challenging. Genetic testing may be expensive or unavailable, and many cases go undiagnosed or misdiagnosed. Awareness among general practitioners and paediatricians is essential to guide patients toward specialist assessment when symptoms suggest a connective tissue disorder. Causes of Ehlers-Danlos Syndromes Environmental factors do not cause EDS, but lifestyle and injury can influence how symptoms appear. For example, frequent dislocations or skin trauma may make EDS more noticeable in people who lead physically active lives or do not know they are affected. Understanding the causes of Ehlers-Danlos syndromes is essential for diagnosis, family planning, and long-term health management. While genetic testing confirms most types, recognising patterns of inheritance and typical symptoms remains a key part of identifying the condition in clinical settings. [Next: Symptoms of Ehlers-Danlos Syndromes →]

Causes of Ehlers-Danlos Syndromes Read More »

Symptoms of Ehlers-Danlos Syndromes

Symptoms of Ehlers-Danlos Syndromes

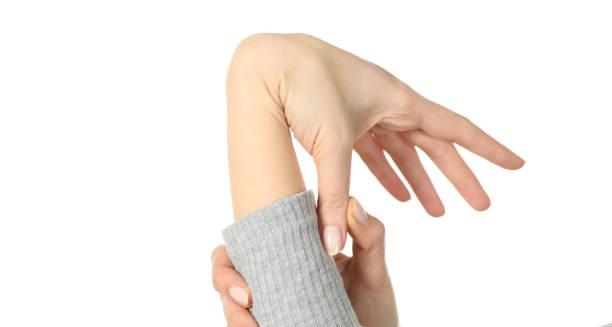
Symptoms of Ehlers-Danlos Syndromes The symptoms of Ehlers-Danlos syndromes vary widely depending on the type. However, all forms involve some level of collagen-related weakness, which leads to problems with the skin, joints, or blood vessels. Recognising the symptoms of Ehlers-Danlos syndromes early can help patients access care, avoid injury, and improve their quality of life. Common general symptoms include: Joint hypermobility – unusually flexible joints that can bend beyond the normal range Frequent joint dislocations or subluxations, especially in the shoulders, knees, and fingers Chronic joint or muscle pain Fatigue, often due to joint instability and poor sleep Soft, stretchy, or fragile skin Easy bruising Poor wound healing, with thin or wide scars In classical EDS, people often have smooth, doughy skin that stretches easily and heals poorly. Scars may appear as thin, “cigarette paper”-like marks on the knees, elbows, or forehead. Hernias and pelvic organ prolapse are also more common. Hypermobile EDS (hEDS) symptoms are centred on joint issues. People may be able to bend their thumbs to their forearms or place their hands flat on the floor without bending their knees. Over time, this flexibility leads to pain, instability, and increased injury risk. Vascular EDS presents with more serious internal symptoms. People with this type may have thin, translucent skin, prominent veins, and a risk of blood vessel or organ rupture. Sudden chest or abdominal pain may signal a medical emergency, requiring immediate attention. Other symptoms seen across EDS types include: Digestive issues such as reflux, bloating, or constipation Gum disease or fragile teeth Poor coordination or proprioception (awareness of body position) Delayed wound healing and surgical complications Symptoms of Ehlers-Danlos Syndromes In children, signs may include frequent bruising, joint dislocations, delayed motor development, or frequent complaints of pain. Parents may notice the child is unusually flexible or struggles with balance. In South Africa, where EDS awareness is still limited, people may be misdiagnosed with other conditions like fibromyalgia, growing pains, or even hypochondria. This can delay appropriate treatment and lead to frustration or mental health strain. Understanding the symptoms of Ehlers-Danlos syndromes helps people advocate for themselves, seek specialist input, and receive supportive care. While the condition cannot be cured, early intervention can make a significant difference in managing its impact. [Next: Diagnosis of Ehlers-Danlos Syndromes→]

Symptoms of Ehlers-Danlos Syndromes Read More »

Diagnosis of Ehlers-Danlos Syndromes

Diagnosis of Ehlers-Danlos Syndromes

Diagnosis of Ehlers-Danlos Syndromes The diagnosis of Ehlers-Danlos syndromes can be complex due to the wide variety of symptoms and overlapping features with other conditions. Since Ehlers-Danlos syndromes are genetic and vary in severity. Diagnosis is often delayed or misinterpreted—especially for milder types such as hypermobile EDS. A proper diagnosis usually involves a combination of clinical examination, family history, and, in some cases, genetic testing. Doctors begin by assessing the patient’s physical signs. For hypermobile EDS, the Beighton Score is used to measure joint hypermobility. This system gives points based on how far joints like the knees, elbows, and fingers can bend beyond their normal range. A high score may support the diagnosis, but it is not enough on its own. A detailed medical history is essential. Doctors look for recurring joint dislocations, chronic pain, frequent bruising, and slow wound healing. Family history is also considered—many forms of EDS run in families, so a parent or sibling with similar symptoms may point toward a hereditary connective tissue disorder. Clinical Diagnostic Criteria Clinical diagnostic criteria differ depending on the EDS type. For instance: Classical EDS is diagnosed through skin and joint findings, sometimes supported by genetic testing for COL5A1 or COL5A2 mutations. Vascular EDS requires DNA testing for mutations in the COL3A1 gene, especially in patients with thin skin, fragile arteries, or unexplained organ rupture. Kyphoscoliotic and arthrochalasia types are extremely rare and confirmed through genetic analysis and specialist evaluation. In hypermobile EDS, no known genetic marker has yet been identified, so diagnosis relies heavily on clinical signs, exclusion of other disorders, and expert judgement. In South Africa, access to genetic testing is limited in many public health settings. This means diagnosis often depends on clinical recognition and symptom history alone. General practitioners may not be familiar with the full range of EDS symptoms, which can lead to underdiagnosis or misdiagnosis, particularly in rural communities. Diagnosis of Ehlers-Danlos Syndromes Specialist referral is often necessary. Rheumatologists, geneticists, or clinical genetic counsellors are best equipped to assess rare connective tissue disorders. In some cases, patients may need to travel to academic hospitals or private facilities for full assessment. Although there is no cure, a confirmed diagnosis of Ehlers-Danlos syndromes opens the door to targeted treatment, lifestyle guidance, and access to specialist care. It also provides clarity and emotional validation for those who have struggled for years without answers. [Next: Treatment of Ehlers-Danlos Syndromes →]

Diagnosis of Ehlers-Danlos Syndromes Read More »

Physiotherapist assisting patient with joint support during treatment for Ehlers-Danlos Syndromes.

Treatment of Ehlers-Danlos Syndromes

Treatment of Ehlers-Danlos Syndromes The treatment of Ehlers-Danlos syndromes focuses on managing symptoms, preventing injuries, and supporting long-term quality of life. As Ehlers-Danlos syndromes are genetic, there is currently no cure—but with early intervention and the right support, many people live active, fulfilling lives. Doctors tailor treatment plans to each individual’s specific needs. They depend on the type of EDS and the severity of symptoms. Most patients benefit from a multi-disciplinary approach, involving physiotherapists, pain specialists, occupational therapists, and psychologists. Physiotherapy plays a central role. A structured exercise programme helps stabilise joints, strengthen muscles, and reduce the risk of dislocations. Doctors avoid stretching because excessive flexibility can worsen joint instability. Doctors often recommend core strengthening, low-impact activities, and proprioception exercises to improve balance and coordination. Pain management is crucial. Many people with EDS experience chronic pain due to joint instability, muscle fatigue, or previous injuries. Treatment may include: Paracetamol and NSAIDs Low-dose antidepressants or anti-epileptic medications for nerve pain Physical therapy and massage Cognitive behavioural therapy (CBT) to help manage the emotional impact of long-term pain Braces or supports may be used to stabilise vulnerable joints, especially during flare-ups. Custom orthotics or mobility aids may be helpful in cases with severe joint laxity or fatigue. Occupational therapy can assist with adapting daily tasks and preventing joint strain. Techniques include joint protection strategies, activity pacing, and ergonomic support for work or study. Mental health support is vital. Living with EDS can lead to anxiety, depression, or frustration—especially when diagnosis is delayed or misunderstood. Support groups, therapy, and community awareness programmes can make a big difference. Treatment of Ehlers-Danlos Syndromes For rarer types like vascular EDS, more urgent medical oversight is needed. Patients must avoid high-risk activities and may require routine imaging to monitor blood vessels. Any sudden chest, abdominal, or limb pain must be treated as a medical emergency due to the risk of arterial rupture. In South Africa, access to comprehensive treatment depends on location and medical coverage. While larger urban hospitals may offer rheumatology and physiotherapy services, rural patients often face long travel distances and limited care options. Non-profits and advocacy groups are working to increase awareness and support for those living with EDS across all provinces. The treatment of Ehlers-Danlos syndromes requires long-term planning and ongoing support. Although it cannot reverse the condition, it empowers individuals to manage symptoms, protect their bodies, and improve daily functioning. [Next: Complications of Ehlers-Danlos Syndromes →]

Treatment of Ehlers-Danlos Syndromes Read More »

Man sitting on bed with hand on face, experiencing pain from Ehlers-Danlos Syndromes complications.

Complications of Ehlers-Danlos Syndromes

Complications of Ehlers-Danlos Syndromes The complications of Ehlers-Danlos syndromes can be wide-ranging and vary depending on the type and severity of the condition. Because Ehlers-Danlos syndromes affect connective tissue throughout the body, complications may arise in the joints, skin, internal organs, and vascular system. Early diagnosis and proper management reduce the risk of serious long-term damage. The most common complications include: Joint dislocations and subluxations, particularly in hypermobile EDS. These can occur during daily activities and cause pain, instability, and soft tissue injury. Chronic pain, which often worsens over time due to muscle fatigue, nerve strain, and joint instability. Delayed healing, thin scarring, and skin that bruises easily or splits with minor trauma—especially in classical EDS. Fatigue, which may stem from poor sleep, deconditioning, and constant pain. In vascular EDS, complications are far more serious. The most dangerous risks include: Arterial rupture, often affecting the aorta or medium-sized arteries Organ rupture, especially in the intestines or uterus (during childbirth) Internal bleeding, which may be life-threatening and require emergency care Pregnancy in women with vascular EDS requires high-risk monitoring due to the risk of uterine rupture or vascular events. Women with other EDS types may also face challenges such as joint pain, pelvic instability, and premature delivery. Digestive complications can also occur. These include irritable bowel syndrome, gastroparesis, and acid reflux, which are common in hypermobile EDS. Constipation and bladder dysfunction may result from weak pelvic support structures. Other complications include: Dental issues, like fragile teeth or gum disease Frequent injuries, such as sprains, strains, and tendon ruptures Depression and anxiety, often due to long-term pain, disability, or isolation Adverse reactions to surgery, including poor healing or excessive bleeding Complications of Ehlers-Danlos Syndromes In South Africa, the complications of EDS are often compounded by delayed diagnosis, limited access to physical therapy, and a shortage of specialists. As a result, many people live with untreated symptoms or worsening disability. Education for healthcare workers and community awareness can help close the gap in care. While the complications of EDS can be overwhelming, they are not inevitable. With proper care, most people can reduce injuries, manage their pain, and maintain independence. Support from family, health professionals, and the broader community plays a key role in this journey. Understanding the complications of Ehlers-Danlos syndromes helps healthcare teams and families create realistic care plans and empower those affected to live more comfortably and safely. [Next: Back to Overview →]

Complications of Ehlers-Danlos Syndromes Read More »

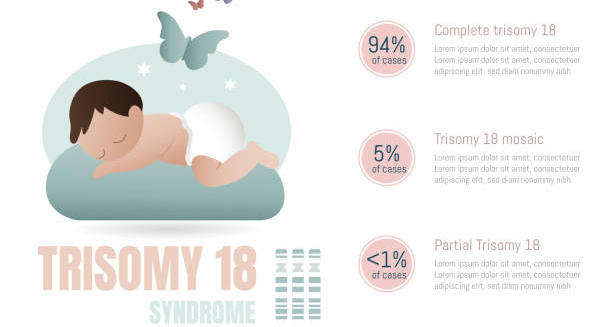
Illustration explaining Edwards’ Syndrome with baby and trisomy 18 chromosome breakdown.

Edwards’ Syndrome

Edwards’ Syndrome Edwards’ syndrome, also known as trisomy 18, is a serious genetic condition caused by the presence of an extra copy of chromosome 18 in a baby’s cells. This additional genetic material disrupts normal development, leading to severe physical and intellectual disabilities. This syndrome affects around 1 in 5,000 live births, but many pregnancies with this condition end in miscarriage or stillbirth. The condition was first described by Dr. John H. Edwards in 1960. It occurs randomly during cell division in the early stages of embryo development. Most cases are not inherited and are instead linked to errors during the formation of egg or sperm cells. The risk of having a baby with Edwards’ syndrome increases with maternal age, particularly in women over 35. Babies born with Edwards’ syndrome often have a low birth weight and a range of physical abnormalities. These may include a small head, clenched fists with overlapping fingers, heart defects, and severe developmental delays. Many also experience breathing difficulties and feeding problems shortly after birth. Sadly, the condition is associated with a high mortality rate. Most babies with this syndrome die before or shortly after birth. Of those who are born alive, only a small percentage survive past their first year, and those who do face complex medical challenges. Edwards’ Syndrome In South Africa, the availability of prenatal screening and diagnostic services varies. In urban areas, pregnant women may be offered blood tests and ultrasound scans that can detect markers for Edwards’ syndrome. However, in rural or under-resourced regions, limited access to these services may delay or prevent early diagnosis. Despite the severe nature of the condition, some families choose to continue with the pregnancy and provide palliative care after birth. Others may opt for medical intervention where appropriate, depending on the child’s condition and prognosis. Understanding Edwards’ syndrome helps expectant parents make informed decisions and prepares families and healthcare providers to offer the best support possible—both emotionally and medically. [Next: Causes of Edwards’ Syndrome →]

Edwards’ Syndrome Read More »

Chromosomal diagram showing Trisomy 18 as the cause of Edwards’ Syndrome.

Causes of Edwards’ Syndrome

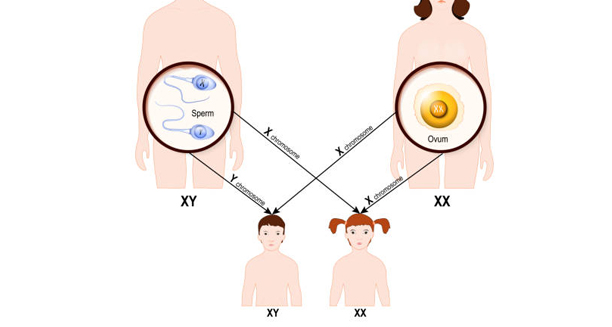
Causes of Edwards’ Syndrome The causes of Edwards’ syndrome lie in a genetic abnormality known as trisomy 18. In this condition, a baby has three copies of chromosome 18 instead of the usual two. This extra chromosome affects nearly every organ and system in the developing body, leading to a wide range of health problems. Edwards’ syndrome is not usually inherited—it occurs as a random event during the formation of reproductive cells. During fertilisation, an egg from the mother and a sperm from the father combine to form a new life with 46 chromosomes—23 from each parent. In trisomy 18, one of the parents’ cells contributes an extra chromosome 18. This typically happens due to a process called nondisjunction, where chromosomes fail to separate properly during cell division. There are three types of Edwards’ syndrome: Full trisomy 18 – where every cell in the body contains an extra chromosome 18. This is the most common and most severe form. Mosaic trisomy 18 – where only some cells have the extra chromosome. The symptoms may be milder depending on the number and type of affected cells. Partial trisomy 18 – where only a part of chromosome 18 is present in triplicate. This is rare and often caused by a piece of the chromosome attaching to another during cell formation. The exact reason for these chromosomal errors is not well understood, but they are more likely to happen as a woman gets older. The risk increases significantly for mothers aged 35 and above. Causes of Edwards’ Syndrome In South Africa, many women may not be aware of these risks, especially in areas with limited access to antenatal education. Routine prenatal screenings may not always be offered, particularly in underfunded clinics. Increasing awareness of maternal age-related risks and improving access to prenatal diagnostics could help identify Edwards’ syndrome earlier. Although the condition usually occurs by chance, parents who have had one child with Edwards’ syndrome may be offered genetic counselling. This can help them understand their risk in future pregnancies and explore available options. Understanding the causes of Edwards’ syndrome allows for better screening and emotional preparation. It also supports more informed conversations between parents and healthcare providers when faced with difficult decisions. [Next: Symptoms of Edwards’ Syndrome →]

Causes of Edwards’ Syndrome Read More »

Scroll to Top