Mental Matters

Health Conditions

Find information on various health conditions affecting people of all ages. This category covers causes, symptoms, diagnosis, and management options for physical illnesses and chronic diseases. Get insights to help you understand different health challenges and make informed decisions about your wellbeing.

Diagnosis of Glaucoma

Diagnosis of Glaucoma

Diagnosis of Glaucoma The diagnosis of glaucoma relies on a thorough clinical evaluation, including eye pressure measurement, optic nerve examination, and visual field testing. Since glaucoma often develops without early symptoms, routine eye checks are the only way to detect the condition before irreversible damage occurs. A timely diagnosis enables early treatment that can preserve vision and slow disease progression. Modern diagnostic methods make it possible to detect glaucoma years before a patient notices any vision changes. The key is combining several tests to build a complete picture of eye health. Comprehensive Eye Examination A standard glaucoma assessment includes: Patient history: Risk factors such as family history, diabetes, steroid use, or ethnicity Visual acuity test: Measures how well a person can see at different distances Slit-lamp examination: Assesses the front of the eye for inflammation, damage, or abnormalities These initial steps guide whether further glaucoma-specific testing is required. Tonometry: Measuring Eye Pressure Tonometry measures intraocular pressure (IOP), which is one of the most important indicators of glaucoma. Elevated pressure suggests a higher risk, though not all glaucoma patients have high readings. There are several types of tonometry: Applanation tonometry: Gold standard, uses a device that gently flattens the cornea Non-contact tonometry (puff test): Uses a brief burst of air Rebound tonometry: Portable and often used for children or home monitoring Normal IOP ranges between 10–21 mmHg, but glaucoma can occur at lower or higher values depending on other factors. Ophthalmoscopy: Examining the Optic Nerve Using a special lens and microscope, the doctor examines the optic disc at the back of the eye. Features suggestive of glaucoma include: Cupping of the optic nerve Thinning of the neuroretinal rim Asymmetry between the two eyes Progressive cupping is a sign of optic nerve damage, often visualised in sequential photos or scans. Visual Field Testing This is a key test to detect functional vision loss: Uses perimetry machines to map out the person’s peripheral vision Patients press a button when they see a light spot in various locations Results show areas of reduced sensitivity or blind spots In glaucoma, visual field loss often starts in the nasal periphery and progresses slowly. Optical Coherence Tomography (OCT) OCT is an advanced imaging technique that provides cross-sectional images of the retina and optic nerve. It helps measure: Thickness of the retinal nerve fibre layer (RNFL) Changes over time, even before functional loss is apparent OCT is especially useful for diagnosing early glaucoma and monitoring disease progression. Gonioscopy: Assessing the Drainage Angle This test evaluates whether the drainage angle between the cornea and iris is open or blocked. It helps distinguish: Open-angle glaucoma Angle-closure glaucoma A special lens is placed on the eye to allow visualisation of the angle. It is particularly important when acute angle-closure glaucoma is suspected. Pachymetry: Measuring Corneal Thickness Central corneal thickness affects IOP readings and is an independent risk factor for glaucoma. Thinner corneas: May lead to underestimation of IOP Are associated with higher risk of optic nerve damage Pachymetry is a quick, painless test using ultrasound or optical methods. Differential Diagnosis Other conditions can mimic glaucoma, such as: Optic neuritis Ischaemic optic neuropathy Compressive lesions (e.g. tumours) Retinal diseases A comprehensive examination helps rule out these alternatives and confirm a glaucoma diagnosis. Screening and Follow-Up Routine screening is recommended for: All adults over 40, every 2 years People with risk factors, annually Children with family history of congenital glaucoma, as advised by specialists Once diagnosed, glaucoma patients require: Lifelong monitoring Regular visual field and OCT testing Adjustments to treatment based on progression Importance of Early Diagnosis Early detection can: Prevent significant vision loss Reduce reliance on more invasive treatments Maintain independence and quality of life Because damage is irreversible, diagnosis must occur before symptoms develop—another reason why eye pressure alone is not enough to rule out glaucoma. Conclusion | Diagnosis of Glaucoma The diagnosis of glaucoma requires a combination of clinical observation, pressure measurement, imaging, and functional testing. With early detection and regular monitoring, patients can preserve their vision and manage the condition effectively for life. [Next: Treatment of Glaucoma→]

Diagnosis of Glaucoma Read More »

Treatment of Glaucoma

Treatment of Glaucoma

Treatment of Glaucoma The treatment of glaucoma focuses on lowering intraocular pressure (IOP) to prevent or slow further damage to the optic nerve. Since glaucoma can cause irreversible vision loss, the goal of treatment is to preserve the remaining sight rather than restore what has already been lost. The good news is that, with timely and consistent management, most people with glaucoma can retain useful vision throughout their lives. There is no cure for glaucoma, but several effective treatment options exist. These include medicated eye drops, laser therapy, surgical procedures, and lifestyle adjustments. The appropriate treatment depends on the type of glaucoma, its severity, and how the individual responds to initial therapies. Eye Drops: First-Line Treatment In most cases, the first step in treating glaucoma involves prescription eye drops that help lower intraocular pressure. These drops either reduce the amount of fluid produced in the eye or improve fluid drainage. The main classes of eye drops include: 1. Prostaglandin Analogues Increase fluid outflow Typically used once daily Examples: latanoprost, bimatoprost Side effects: eye redness, longer eyelashes, iris darkening 2. Beta Blockers Reduce fluid production Used once or twice a day Examples: timolol, betaxolol Side effects: fatigue, low heart rate, possible breathing issues 3. Alpha Agonists Decrease fluid production and increase outflow Examples: brimonidine Side effects: dry mouth, fatigue, allergic reactions 4. Carbonic Anhydrase Inhibitors Reduce fluid production Available in drops or oral form Examples: dorzolamide, acetazolamide Side effects: stinging, taste changes 5. Rho Kinase Inhibitors Enhance drainage through the trabecular meshwork Used alone or in combination with other drops Adherence is critical. Skipping doses or improper application can lead to increased pressure and optic nerve damage. Patients should receive instruction on how to use drops correctly and understand the importance of long-term commitment to therapy. Laser Treatments Laser therapy is often used when drops are ineffective, poorly tolerated, or not suitable for long-term use. It can also serve as an early treatment option, especially in angle-closure glaucoma. 1. Selective Laser Trabeculoplasty (SLT) Used primarily for open-angle glaucoma Targets the drainage tissue to improve fluid outflow Quick and painless outpatient procedure Effects last 1–5 years, and the procedure can be repeated 2. Laser Peripheral Iridotomy Performed for angle-closure glaucoma Creates a small hole in the iris to relieve pressure Prevents future acute attacks in the other eye 3. Cyclodiode Laser Used in advanced or refractory glaucoma Reduces fluid production by targeting the ciliary body Reserved for severe or end-stage cases Laser treatments are typically low-risk and can reduce or eliminate the need for daily eye drops. Surgical Treatments Surgery is considered when medications and laser treatments are not sufficient to control IOP. 1. Trabeculectomy Creates a new drainage channel for fluid to exit the eye Performed in an operating theatre under local anaesthesia Reduces IOP significantly and may reduce or eliminate the need for drops Risks: infection, bleeding, scarring, vision changes 2. Tube Shunt Surgery Involves placing a small tube and plate to redirect fluid Used when trabeculectomy fails or is unsuitable Effective in complex or secondary glaucoma cases 3. Minimally Invasive Glaucoma Surgery (MIGS) A newer class of procedures Less invasive with quicker recovery Examples: iStent, Hydrus Microstent, Kahook Dual Blade Often performed alongside cataract surgery MIGS procedures are particularly suitable for patients with mild to moderate glaucoma. Managing Angle-Closure Glaucoma In acute cases, emergency treatment includes: Eye drops and medications to quickly lower IOP Laser iridotomy to relieve pressure and prevent recurrence Surgical removal of the lens if the attack recurs or vision is compromised Prompt treatment is vital to preserve vision. Lifestyle and Home Management While medical treatments are essential, lifestyle also plays a supporting role: Take medication consistently and attend follow-up appointments Protect eyes from injury and limit exposure to pressure-increasing activities Exercise regularly, but avoid straining or head-down positions in advanced cases Manage systemic conditions like diabetes and high blood pressure Avoid excessive caffeine, which may transiently raise IOP Quitting smoking and eating a nutrient-rich diet also support eye and overall health. Monitoring Progress Once treatment begins, regular monitoring includes: IOP measurements Visual field testing OCT scans of the optic nerve Eye structure assessments Treatment may need to be adjusted over time depending on response and disease progression. Conclusion | Treatment of Glaucoma The treatment of glaucoma is multifaceted and lifelong. With a combination of medication, laser procedures, and surgery where needed, many patients maintain stable vision for decades. Early intervention, consistent follow-up, and patient education remain the pillars of effective glaucoma management. [Next: Complications of Glaucoma →]

Treatment of Glaucoma Read More »

Complications of Glaucoma

Complications of Glaucoma

Complications of Glaucoma The complications of glaucoma can range from mild side effects of treatment to severe vision loss and blindness. Because glaucoma damages the optic nerve gradually and without warning, failure to diagnose or manage it effectively can lead to irreversible harm. While many people with glaucoma live full and independent lives, complications arise when the disease progresses unchecked or when treatment is poorly tolerated. Understanding the potential complications helps patients recognise warning signs early and empowers them to take an active role in their eye health. 1. Vision Loss The most serious and feared complication of glaucoma is permanent vision loss. This occurs when: The optic nerve sustains prolonged pressure damage The retinal ganglion cells die off Visual signals no longer reach the brain effectively In open-angle glaucoma, vision loss: Begins in the peripheral field Progresses slowly over years Becomes noticeable only after significant damage has occurred In angle-closure glaucoma: Vision can deteriorate rapidly Central vision may be affected early if untreated Permanent blindness may result from a single acute episode 2. Blindness Glaucoma is one of the leading causes of irreversible blindness worldwide. This occurs when: The entire optic nerve is compromised Both central and peripheral vision are lost Treatment fails or is delayed Blindness from glaucoma: Is permanent—vision cannot be restored May be complete or partial (legal blindness) Often leads to profound lifestyle and psychological impacts Regular monitoring and timely treatment can almost always prevent this outcome. 3. Side Effects of Medications Eye drops and oral medications used to control intraocular pressure may cause: Local side effects: Red, itchy, or dry eyes Blurred vision after drop instillation Eyelash growth or iris colour changes (with prostaglandins) Systemic side effects: Low blood pressure or heart rate (beta-blockers) Fatigue or dizziness Taste changes or dry mouth Frequent urination or tingling (carbonic anhydrase inhibitors) Adherence may be compromised if side effects are not managed. Switching medications or adjusting dosages can help. 4. Surgical Complications While surgery is often effective, it carries risks, including: Infection (endophthalmitis) Bleeding inside the eye (hyphema) Scarring that blocks fluid drainage Over-filtration, leading to very low eye pressure (hypotony) Vision fluctuations or double vision With skilled surgeons and careful post-operative care, the risk of serious complications remains low. 5. Psychological Impact Vision loss, even when mild, can result in: Anxiety about blindness Depression or social withdrawal Reduced independence or confidence Support groups, counselling, and practical vision aids can help mitigate this burden. Addressing emotional wellbeing is just as important as preserving physical sight. 6. Impact on Daily Living As glaucoma progresses, individuals may experience: Difficulty driving, especially at night or in low contrast Trouble navigating stairs or unfamiliar spaces Increased risk of falls or accidents Need for vision aids, magnifiers, or mobility support Even with moderate visual impairment, many adapt successfully using tools like large-print devices, voice-activated technology, and improved lighting. 7. Financial and Healthcare Burden Long-term glaucoma management may result in: Costs for medications, follow-ups, and surgeries Time off work or lifestyle modifications Dependency on caregivers if vision becomes limited Public health systems often provide screening and treatment support, but in underserved regions, the financial and logistical burden remains significant. Summary of Complications Complication Impact Vision loss Irreversible, often unnoticed early Blindness Complete loss of functional sight Medication side effects Eye discomfort, systemic symptoms Surgical complications Rare but potentially serious Psychological effects Anxiety, depression, loss of confidence Functional limitations Reduced independence, falls, driving risk Economic burden Ongoing costs and lifestyle adjustment Conclusion | Complications of Glaucoma The complications of glaucoma highlight the importance of early detection, consistent treatment, and long-term monitoring. While the disease cannot be cured, modern therapies allow most patients to lead full, independent lives. By recognising complications early and responding appropriately, individuals can protect their vision and quality of life. [Next: Back to Overview →]

Complications of Glaucoma Read More »

Man touching his throat with discomfort due to swollen glands

Glandular Fever

Glandular Fever Glandular fever, also known as infectious mononucleosis or simply mono, is a viral illness most commonly caused by the Epstein-Barr virus (EBV). Glandular fever typically affects teenagers and young adults, although it can occur at any age. It spreads primarily through saliva, earning it the informal name “the kissing disease,” though transmission can also happen through coughing, sneezing, or sharing utensils. The condition is usually mild but can be prolonged and exhausting, with symptoms lasting for several weeks. In rare cases, complications can occur, especially if rest and proper care are not observed. Understanding glandular fever helps individuals manage the illness appropriately and avoid spreading the virus to others. What Is Glandular Fever? Glandular fever is a viral infection that triggers a strong immune response, resulting in: Fever Sore throat Swollen lymph nodes Severe fatigue The illness is caused by the Epstein-Barr virus, a member of the herpesvirus family. Once a person contracts EBV, the virus remains in their body for life in a dormant state. In most cases, it does not reactivate or cause further illness. How It Spreads The virus spreads through bodily fluids, particularly saliva. Common ways people catch glandular fever include: Kissing someone infected Sharing drinks, food, straws, or cutlery Being exposed to droplets from coughs or sneezes Contact with contaminated objects (e.g. toothbrushes, lip balm) EBV is highly contagious during the active phase of infection, especially when symptoms are present. However, the virus can be transmitted even before symptoms begin and for months afterward. Who Is at Risk? Glandular fever most commonly affects: Teenagers and young adults aged 15–25 University students or young professionals in close living or social environments People with weakened immune systems, who may experience more severe illness In children under five, infection with EBV usually causes mild or no symptoms, which is why many adults test positive for past exposure without remembering being ill. Common Symptoms The hallmark symptoms of glandular fever usually appear four to six weeks after exposure and include: Fever, often mild to moderate but occasionally high Severe sore throat, sometimes mistaken for bacterial tonsillitis Swollen lymph nodes, especially in the neck and armpits Profound fatigue that can last for weeks Headache Muscle aches Loss of appetite Swollen tonsils, sometimes with white or grey coating Mild rash, especially if the person has taken antibiotics such as ampicillin or amoxicillin Some individuals also experience: Enlarged spleen or liver Abdominal discomfort Nausea or jaundice Fatigue can be debilitating, lingering for several weeks or months even after the main symptoms have resolved. Incubation and Duration After infection, there is an incubation period of approximately 4 to 6 weeks. The acute illness phase typically lasts 2 to 3 weeks, but fatigue and reduced stamina can persist for: Up to two months in most people Three months or more in a small percentage Proper rest and recovery are key to minimising prolonged symptoms. Diagnosis Doctors often suspect glandular fever based on: A combination of clinical symptoms The patient’s age and lifestyle Physical examination findings such as swollen glands and enlarged tonsils Confirmation may include: Monospot test, which detects heterophile antibodies (most useful after the first week of illness) Full blood count, showing atypical lymphocytes Liver function tests, often mildly abnormal in active infection EBV serology, which can determine whether the infection is recent or past Diagnosis is typically clinical, and additional testing is only necessary if symptoms are unclear or prolonged. How It Differs from Other Illnesses Glandular fever is frequently mistaken for: Streptococcal tonsillitis Flu or COVID-19 Cytomegalovirus (CMV) infection Toxoplasmosis HIV (in early seroconversion) The distinguishing feature of glandular fever is its combination of sore throat, swollen glands, and extreme fatigue that lasts well beyond the usual viral illness duration. Is Glandular Fever Serious? In most cases, glandular fever resolves on its own with proper rest and hydration. However, it can become serious if complications develop, such as: Ruptured spleen (rare but life-threatening) Airway obstruction due to severe tonsil swelling Hepatitis or elevated liver enzymes Prolonged fatigue resembling chronic fatigue syndrome Anaemia or thrombocytopaenia For this reason, individuals are advised to avoid contact sports or heavy lifting for at least four weeks after diagnosis to reduce the risk of spleen rupture. Long-Term Outlook Most people recover fully from glandular fever and do not experience further problems. The body develops lifelong immunity to EBV, so reinfection is extremely rare. However, EBV remains in the body for life in a dormant form. In very rare cases, reactivation can occur, especially in people with compromised immune systems. Understanding glandular fever helps individuals manage the condition safely and prevent unnecessary complications. With rest, fluids, and time, most people return to full health. [Next: Causes of Glandular Fever →]

Glandular Fever Read More »

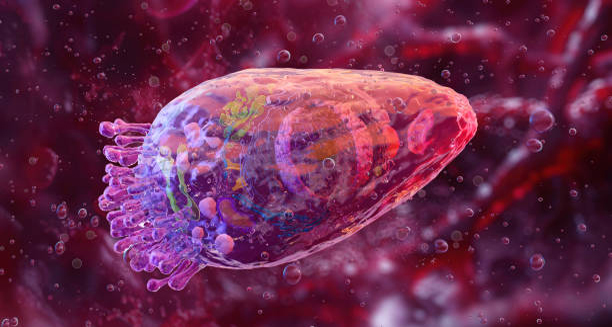
Epstein-Barr virus (EBV) under microscope as cause of glandular fever

Causes of Glandular Fever

Causes of Glandular Fever The causes of glandular fever are viral in nature, with the Epstein-Barr virus (EBV) responsible for around 90% of cases. Glandular fever is not caused by poor hygiene, bacteria, or food poisoning—rather, it results from close personal contact that allows saliva containing EBV to pass from one person to another. EBV is a member of the herpesvirus family and is one of the most common human viruses. It is estimated that more than 90% of adults worldwide have been infected with EBV by the age of 40, often without ever realising it. The virus usually lies dormant after initial infection and does not cause repeated illness in healthy individuals. Epstein-Barr Virus (EBV) The Epstein-Barr virus was first identified in 1964 and is now recognised as the primary cause of infectious mononucleosis (glandular fever). EBV infects B lymphocytes, a type of white blood cell involved in the immune response. The virus causes an immune reaction that results in: Swelling of lymph nodes Inflammation of the throat and tonsils Increase in abnormal lymphocytes (atypical mononucleated cells) A surge of fatigue due to the immune system’s heightened activity Once the virus enters the body, it replicates in the throat and salivary glands before spreading through the bloodstream. The immune response to EBV, rather than the virus itself, causes most of the symptoms associated with glandular fever. How EBV Is Transmitted The virus is spread primarily through saliva, but can also be found in: Mucus from the nose and throat Tears Blood and, in rare cases, semen The most common modes of transmission include: Kissing Sharing drinks, utensils, lip balm, or cigarettes Exposure to droplets from coughing or sneezing Using contaminated objects, such as toothbrushes Because EBV is so widespread, exposure is common. However, not everyone who contracts the virus develops glandular fever. In early childhood, EBV infections often pass unnoticed or with only mild flu-like symptoms. Why Some People Get Glandular Fever Not everyone exposed to EBV develops glandular fever. The likelihood of developing symptoms depends on: Age at the time of infection Children under 5 rarely develop classic symptoms Teenagers and young adults are most likely to experience full-blown glandular fever Immune system response A robust immune reaction is what causes the fatigue and lymph node swelling typical of the illness Genetic predisposition Some evidence suggests genetic factors may influence the body’s response to EBV Those infected with EBV during adolescence or early adulthood are most likely to develop symptoms, while those infected in early childhood often remain asymptomatic. Other Causes of Glandular Fever-Like Illness Although EBV is the leading cause of glandular fever, other viruses can cause a similar illness, including: Cytomegalovirus (CMV) Toxoplasma gondii (a parasite, not a virus) HIV (acute seroconversion illness) Hepatitis viruses Adenoviruses In these cases, the illness is usually less severe, and blood tests help differentiate the underlying cause. Risk Factors Several factors may increase the risk of contracting EBV and developing glandular fever: Living in close quarters, such as dormitories or military barracks Sharing drinks or personal items Kissing multiple partners, particularly among teenagers Weakened immune system, due to illness or medication While these behaviours increase exposure, many people who carry EBV never fall ill, as the immune system usually keeps the virus in check. Can EBV Reactivate? Once a person contracts EBV, the virus remains dormant in their body for life. In rare cases, it may reactivate, particularly in individuals with: Immunodeficiency, such as in advanced HIV or post-organ transplantation Chronic stress or severe illness Certain autoimmune diseases Reactivation is uncommon in healthy people and usually does not cause symptoms. However, EBV reactivation has been loosely associated with conditions like: Chronic fatigue syndrome Multiple sclerosis (MS) Certain lymphomas It is important to note that research is ongoing, and direct causation has not been firmly established. Summary of Main Causes Cause Role in Glandular Fever Epstein-Barr virus (EBV) Primary cause (90% of cases) Cytomegalovirus (CMV) EBV-negative glandular fever-like illness Toxoplasma, hepatitis, HIV Less common, mimic symptoms Saliva exchange Main mode of EBV transmission Age (15–25) Highest risk of symptomatic infection Conclusion | Causes of Glandular Fever The causes of glandular fever are well understood, with the Epstein-Barr virus playing the central role. Transmission occurs primarily through saliva, making the condition particularly common among teenagers and young adults. Understanding how the virus works, who is at risk, and how it spreads helps to prevent infection and allows for early recognition of symptoms. [Next: Symptoms of Glandular Fever→]

Causes of Glandular Fever Read More »

Woman holding sore throat due to glandular fever symptoms

Symptoms of Glandular Fever

Symptoms of Glandular Fever The symptoms of glandular fever vary widely between individuals, depending on their age, immune response, and overall health. Glandular fever, also known as infectious mononucleosis, most commonly affects teenagers and young adults, though people of any age can contract the virus. While some individuals may experience only mild symptoms or none at all, others endure a more severe and prolonged illness that interferes with daily life. The disease is caused primarily by the Epstein-Barr virus (EBV) and triggers an intense immune reaction. This reaction is responsible for many of the hallmark signs, which include fatigue, swollen glands, and a sore throat. Recognising the full spectrum of symptoms allows for early diagnosis, appropriate care, and the prevention of complications. Typical Onset The incubation period for EBV is approximately four to six weeks. During this time, the virus replicates and spreads within the body, often without producing any symptoms. Once the immune system begins to respond, symptoms emerge rapidly and may persist for several weeks. In many cases, the illness begins with general malaise, including: Mild fever Muscle aches Loss of appetite Headache Low energy or sleepiness These early signs can mimic other common viral infections, making initial diagnosis difficult. Core Symptoms Once fully developed, glandular fever typically presents with a characteristic trio of symptoms: 1. Sore Throat The sore throat associated with glandular fever is usually severe and can: Last for more than a week Resemble bacterial tonsillitis Include red, inflamed tonsils with white or grey patches Make swallowing difficult and painful In some cases, the tonsils become so enlarged that they obstruct the airway or cause voice changes. 2. Swollen Lymph Nodes Enlargement of lymph nodes is a key sign and occurs particularly in: The neck The armpits Occasionally the groin These glands may feel tender and firm, and they can persist for several weeks even after other symptoms subside. 3. Fatigue Profound fatigue is perhaps the most debilitating symptom. It can: Begin suddenly and worsen quickly Persist for weeks or even months Be accompanied by sleep disturbances, mental fog, or difficulty concentrating Even after other symptoms improve, fatigue may linger and affect academic performance, work productivity, and overall quality of life. Additional Symptoms In addition to the classic triad, individuals may also experience: Fever: Typically low to moderate, but occasionally higher than 38.5°C Chills and night sweats Muscle and joint pain Headaches Loss of appetite Nausea or mild abdominal pain In some cases, the liver and spleen become inflamed, leading to: Tenderness in the upper abdomen Mild jaundice (yellowing of the skin or eyes) Enlarged spleen (splenomegaly), increasing the risk of rupture The presence of liver and spleen involvement makes it crucial to avoid contact sports or heavy lifting for at least four weeks. Skin Rash and Antibiotic Reactions Some individuals develop a maculopapular rash, which is: Flat or slightly raised Pink or red in appearance Usually non-itchy This is more likely to occur if the person has taken certain antibiotics, particularly amoxicillin or ampicillin, which can trigger an allergic-looking rash in people with EBV. The rash is not harmful and usually disappears within a few days, but its appearance can be alarming if unexpected. In Children Children infected with EBV often display: Very mild symptoms Brief fever or irritability Mild throat inflammation In many cases, the infection goes unnoticed, and the child develops lifelong immunity without ever being diagnosed. In Older Adults Glandular fever is less common in older adults, but when it occurs, symptoms may be: Atypical or less pronounced Mistaken for flu, hepatitis, or other infections Associated with jaundice and liver enzyme abnormalities Fatigue and weakness may persist longer in older individuals, especially if underlying conditions are present. Timeline of Symptoms Timeframe Common Symptoms Week 1 Fatigue, sore throat, mild fever Week 2 Enlarged lymph nodes, severe sore throat Weeks 3–4 Fatigue, lingering fever, swollen glands Weeks 5+ Residual fatigue, occasional mild symptoms When to Seek Medical Advice Medical attention is advised if: Breathing or swallowing becomes difficult Abdominal pain or fullness is felt under the ribs (may suggest spleen enlargement) Symptoms last longer than four weeks without improvement There is concern about jaundice or rash after antibiotics Severe fatigue interferes with daily life Symptoms of Glandular Fever Most cases of glandular fever resolve on their own with time and rest. However, severe or persistent symptoms may indicate complications or require further investigation. Understanding the symptoms of glandular fever helps with early identification, proper care, and safe recovery. While most people recover fully, patience is often required to cope with the extended fatigue phase. [Next: Diagnosis of Glandular Fever →]

Symptoms of Glandular Fever Read More »

Doctor examining woman’s neck for glandular fever diagnosis

Diagnosis of Glandular Fever

Diagnosis of Glandular Fever The diagnosis of glandular fever is based on a combination of clinical symptoms, physical examination, and specific laboratory tests. Because glandular fever shares symptoms with many other illnesses, accurate diagnosis requires careful evaluation, especially when the patient presents with a sore throat, swollen lymph nodes, and persistent fatigue. Early diagnosis is important to manage the condition appropriately, advise on recovery time, and prevent complications such as spleen rupture. Fortunately, a number of simple blood tests can help confirm the presence of Epstein-Barr virus (EBV) or the immune system’s response to it. Initial Clinical Assessment Doctors typically begin by reviewing the patient’s: Age (most cases occur between 15–25) Recent exposure to someone with similar symptoms Lifestyle habits (e.g., close contact, shared utensils, kissing) Current symptoms, including: Duration of sore throat and fatigue Swollen glands Appetite and sleep quality Any rashes or antibiotic use Physical examination usually reveals: Red or swollen tonsils, often with white exudate Swollen lymph nodes in the neck and possibly elsewhere Fever Occasionally, an enlarged spleen or liver tenderness If these findings are consistent with glandular fever, further testing is ordered to confirm the diagnosis. Blood Tests Several blood tests help confirm glandular fever and exclude other causes of similar symptoms. 1. Monospot Test (Heterophile Antibody Test) Detects antibodies that appear in response to EBV Usually becomes positive within one week of symptom onset Quick, inexpensive, and widely available However, it may be: Negative early in infection Less reliable in children under 12 Occasionally false positive due to other conditions 2. Full Blood Count (FBC) Glandular fever often causes: Elevated white blood cells, especially atypical lymphocytes Mild anaemia or low platelet count in some cases The presence of >10% atypical lymphocytes supports the diagnosis strongly. 3. Liver Function Tests (LFTs) Many individuals with glandular fever show: Mildly elevated liver enzymes (ALT, AST) In rare cases, jaundice or hepatitis-like symptoms These abnormalities are usually temporary and resolve without treatment. 4. EBV-Specific Serology If the monospot test is negative or inconclusive, EBV serology is more specific. It measures: IgM antibodies to viral capsid antigen (VCA) – indicates recent infection IgG antibodies to VCA – indicates past infection or long-term immunity EBNA antibodies – appear several weeks post-infection and confirm previous exposure The combination of these markers can determine whether the infection is: Acute (recent) Past or resolved Unlikely to be EBV-related Differential Diagnosis Many other illnesses can mimic glandular fever, including: Streptococcal tonsillitis Cytomegalovirus (CMV) infection HIV (acute seroconversion) Toxoplasmosis Viral hepatitis Each of these conditions may cause similar symptoms, but blood testing helps differentiate them. In children, mild EBV infections may be mistaken for flu or general viral illness. Imaging and Other Investigations Imaging is rarely needed, but an ultrasound may be performed if: There is concern about splenic enlargement The patient reports persistent abdominal pain There is suspicion of liver or gallbladder involvement In hospital settings, imaging may be used to exclude other causes of lymph node swelling, such as lymphoma. When to Repeat Testing Occasionally, early tests may be inconclusive. Repeat testing is advised if: Symptoms persist beyond two weeks without improvement Initial tests are negative but symptoms strongly suggest EBV The patient is immunocompromised or at risk of complications In most cases, the diagnosis becomes clearer as the illness progresses. Importance of Accurate Diagnosis Confirming glandular fever allows: Avoidance of unnecessary antibiotics Guidance on rest and return to school or work Education about avoiding contact sports due to spleen enlargement Monitoring for complications, such as hepatitis, anaemia, or secondary infections Misdiagnosis can lead to inappropriate treatment or unnecessary concern. For instance, mistaking EBV-related sore throat for bacterial tonsillitis may result in antibiotics, which not only don’t help but may cause a rash. Conclusion | Diagnosis of Glandular Fever The diagnosis of glandular fever involves recognising the clinical signs and confirming them with specific blood tests. Early detection ensures better management, appropriate activity restrictions, and reassurance for the patient. With time, most individuals recover completely, and complications are rare when the illness is correctly diagnosed and managed. [Next: Treatment of Glandular Fever→]

Diagnosis of Glandular Fever Read More »

Man holding throat in pain – Treatment of Glandular Fever

Treatment of Glandular Fever

Treatment of Glandular Fever The treatment of glandular fever focuses on relieving symptoms, managing complications, and allowing the body time to recover. Since glandular fever is caused by the Epstein-Barr virus (EBV), there is no cure or antiviral treatment that eliminates the virus. Instead, the approach is supportive, with rest and hydration forming the foundation of recovery. Most people recover fully within a few weeks, though fatigue can persist for longer. Medical intervention is generally not required unless complications develop. Understanding how to treat the condition effectively at home and knowing when to seek help can greatly ease the recovery process. Rest and Recovery The cornerstone of treatment is adequate rest. Individuals with glandular fever often experience: Profound fatigue Muscle aches Weakness and malaise Rest helps the immune system focus on clearing the virus and repairing tissue inflammation. During the first two to three weeks: Avoid school, work, or strenuous activity Get plenty of sleep and limit social activities Take time off sport, particularly contact or impact sports due to risk of spleen rupture Recovery timelines vary, and people should return to normal activities gradually, based on how they feel rather than a fixed schedule. Hydration and Nutrition Fluids are essential during recovery to prevent dehydration, especially when fever or sore throat reduces appetite and fluid intake. Helpful strategies include: Drinking water, diluted juice, herbal teas, or broths Sucking on ice cubes or lollies to soothe the throat Eating soft, easy-to-swallow foods such as yoghurt, soup, or mashed vegetables Avoiding alcohol, which can strain the liver Even if appetite is poor, small, regular meals support energy levels and recovery. Managing Fever and Pain For fever, headaches, or sore throat: Use paracetamol or ibuprofen as directed Avoid aspirin in children due to the risk of Reye’s syndrome Gargle with warm salt water to reduce throat inflammation Try throat lozenges or sprays for temporary relief It’s important not to exceed recommended doses and to use medication only for symptom control. Avoiding Antibiotics Antibiotics are not effective against viruses and should not be used to treat glandular fever. If bacterial infection is suspected (e.g., secondary tonsillitis), a doctor may prescribe antibiotics. However: Amoxicillin and ampicillin can cause a rash in people with EBV Alternative antibiotics should be used if necessary Rash due to antibiotics is not an allergy in these cases, but rather a reaction linked to the virus. Medical Supervision and Monitoring Most cases of glandular fever can be managed at home. However, medical attention is required if: Fever exceeds 39.5°C or persists longer than a week Swallowing becomes extremely difficult Breathing is impaired due to swollen tonsils Abdominal pain suggests spleen involvement There are signs of dehydration (dry mouth, low urine output) In rare cases, hospital admission may be needed for: Severe tonsillar enlargement Airway obstruction Intravenous fluids for dehydration Monitoring of liver function or complications Managing Fatigue Fatigue is the most persistent symptom and may linger for weeks or even months. Tips for managing it include: Pacing activities and listening to the body Breaking tasks into smaller, manageable parts Allowing naps without oversleeping Returning to school or work gradually, possibly with reduced hours For some, especially students or professionals, fatigue may be frustrating or distressing. Patience and support are key. Emotional Support and Reassurance Glandular fever can feel overwhelming due to its long recovery and impact on daily life. Individuals may need: Reassurance that fatigue will resolve over time Mental health support if mood or motivation drops Clear explanations about the illness to avoid worry Family, employers, or educators should be informed, especially if time off or adjustments are needed. Complementary Therapies There is no strong evidence supporting herbal remedies or supplements for glandular fever. However, people sometimes try: Echinacea, elderberry, or zinc lozenges Vitamin C or D to support general immune health Always consult a healthcare provider before starting supplements, particularly if on medication. Summary of Home Care Strategy Purpose Rest and sleep Boost recovery and immune function Fluids and soft food Prevent dehydration, reduce discomfort Paracetamol/ibuprofen Relieve pain and fever Avoid sport Prevent spleen rupture Medical check-ups Identify and treat complications early Conclusion | Treatment of Glandular Fever The treatment of glandular fever revolves around rest, symptom management, and awareness of complications. With time and self-care, most people recover completely. Early recognition of danger signs and patience during the fatigue phase are the keys to a smooth recovery. [Next: Complications of Glandular Fever →]

Treatment of Glandular Fever Read More »

Woman holding her side in pain – Complications of Glandular Fever

Complications of Glandular Fever

Complications of Glandular Fever While the majority of people recover from glandular fever without lasting effects, there are some rare but serious complications to be aware of. Glandular fever, caused by the Epstein-Barr virus, is usually self-limiting and resolves with supportive care. However, the virus can occasionally affect other organs or systems, especially if the immune response is unusually strong or if rest is not adequately observed during recovery. Knowing the potential complications of glandular fever can help patients and healthcare providers act swiftly when red flags appear. Fortunately, with timely intervention, most complications are treatable and do not result in long-term harm. 1. Enlarged or Ruptured Spleen Splenomegaly—an enlarged spleen—is common in glandular fever and occurs in up to 50% of cases. It usually causes: Fullness or pain in the upper left abdomen Tenderness, especially when lying down A feeling of pressure after eating The most serious risk is spleen rupture, which is rare (around 1 in 1,000 cases) but potentially life-threatening. Signs include: Sudden sharp pain in the left side Dizziness or fainting Rapid heart rate or low blood pressure To prevent rupture, patients should avoid: Contact sports Heavy lifting Strenuous activity for at least 4 weeks post-diagnosis 2. Liver Inflammation (Hepatitis) Mild liver inflammation is common and may cause: Elevated liver enzymes on blood tests Tenderness in the upper right abdomen Nausea or reduced appetite In some cases, jaundice This form of hepatitis is self-limiting and resolves without treatment. However, liver function should be monitored, especially if symptoms are severe or prolonged. 3. Airway Obstruction Swelling of the tonsils and surrounding tissues may lead to: Difficulty breathing or swallowing Snoring or sleep apnoea Muffled voice Severe obstruction may require: Corticosteroids to reduce swelling Hospital monitoring for airway support Intravenous fluids if eating or drinking is impaired This is a rare complication but needs immediate attention if breathing is affected. 4. Anaemia and Low Platelet Count In some people, EBV may cause: Haemolytic anaemia, where red blood cells break down prematurely Thrombocytopaenia, a low platelet count Symptoms include: Fatigue, pale skin Easy bruising or bleeding Prolonged bleeding from cuts or nosebleeds These issues usually resolve on their own but should be monitored with blood tests if suspected. 5. Neurological Complications Very rarely, glandular fever may affect the nervous system. Possible conditions include: Meningitis Encephalitis (brain inflammation) Guillain-Barré syndrome Bell’s palsy (facial paralysis) Warning signs include: Severe headache Neck stiffness Seizures Confusion or hallucinations Urgent hospital evaluation is needed in any of these scenarios. These complications are extremely rare but potentially serious. 6. Chronic Fatigue Syndrome (CFS/ME) A small number of individuals develop post-viral fatigue that lasts for months. In some cases, it meets the criteria for chronic fatigue syndrome (CFS) or myalgic encephalomyelitis (ME). Characteristics include: Persistent exhaustion not improved by rest Cognitive issues (brain fog) Sleep disturbances Muscle or joint pain While no cure exists, supportive treatments like pacing, physiotherapy, and psychological support can improve quality of life. 7. Secondary Infections During or shortly after glandular fever, the immune system may be temporarily weakened, increasing susceptibility to: Bacterial tonsillitis Sinus infections Chest infections These may require antibiotics or further investigation if symptoms worsen or change unexpectedly. Summary of Possible Complications Complication Frequency Seriousness Spleen rupture Rare Medical emergency Liver inflammation Common (mild) Usually self-limited Airway obstruction Rare May need steroids or hospital care Anaemia/thrombocytopaenia Uncommon Monitor with tests Neurological issues Very rare Potentially serious Chronic fatigue Small percentage Long-term support Secondary infections Occasionally seen Easily treatable Conclusion | Complications of Glandular Fever The complications of glandular fever are uncommon but can become serious if not recognised early. Spleen rupture, airway obstruction, and post-viral fatigue are the most important risks to be aware of. By resting properly, monitoring symptoms, and seeking medical help when necessary, most individuals recover completely and return to normal life without lasting effects. [Next: Back to Overview →]

Complications of Glandular Fever Read More »

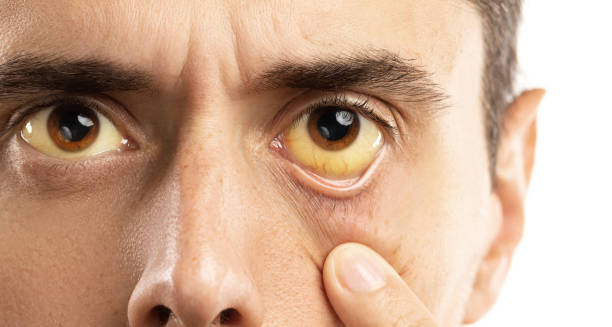
Close-up of a man's yellowish eyes – Gilbert’s Syndrome

Gilbert’s Syndrome

Gilbert’s Syndrome Gilbert’s syndrome is a mild, inherited liver condition that affects how the body processes bilirubin—a yellow pigment formed during the breakdown of red blood cells. People with Gilbert’s syndrome have elevated levels of unconjugated (indirect) bilirubin in their bloodstream, which can occasionally cause a slight yellowing of the skin or eyes, known as jaundice. Despite its effect on bilirubin levels, the condition is harmless and usually requires no treatment. Gilbert’s syndrome is often discovered incidentally during routine blood tests for unrelated health concerns. While it may cause temporary episodes of jaundice, particularly during periods of stress, fasting, illness, or intense exercise, it does not damage the liver or other organs. Understanding the condition helps reduce unnecessary anxiety and prevents misdiagnosis of more serious liver diseases. How Gilbert’s Syndrome Affects the Body Bilirubin is a waste product resulting from the normal breakdown of haemoglobin in ageing red blood cells. Normally, bilirubin travels through the bloodstream to the liver, where it is processed by an enzyme called UGT1A1 (uridine diphosphate-glucuronosyltransferase). This enzyme converts bilirubin into a water-soluble form so it can be excreted in bile. In people with Gilbert’s syndrome, a genetic mutation leads to reduced activity of the UGT1A1 enzyme. As a result: Unconjugated bilirubin builds up in the blood The liver still functions normally but clears bilirubin more slowly During physical or emotional stress, bilirubin levels can temporarily rise further This process is benign, but the intermittent appearance of jaundice can be confusing, especially without a clear diagnosis. Who Gets Gilbert’s Syndrome? Gilbert’s syndrome is one of the most common inherited liver conditions. It affects up to 5–10% of the population worldwide, though many people remain undiagnosed due to the lack of noticeable symptoms. Key demographic features include: Both sexes are affected, though mild jaundice is more noticeable in males due to higher haemoglobin turnover Often identified during late adolescence or early adulthood Runs in families, as it is inherited in an autosomal recessive manner A person must inherit the faulty gene from both parents to develop the condition. Carriers—those with only one copy of the gene—do not usually show symptoms. Common Signs and Symptoms Most individuals with Gilbert’s syndrome experience no symptoms. However, some may notice: Mild yellowing of the whites of the eyes (scleral icterus) Occasional yellowing of the skin, particularly during episodes of raised bilirubin Episodes triggered by: Fasting or skipping meals Physical exertion Illness, such as viral infections Stress or lack of sleep Dehydration Other reported symptoms, though not always linked definitively to Gilbert’s syndrome, include: Fatigue or low energy Mild abdominal discomfort Nausea or digestive irregularities These symptoms are often vague and can result from unrelated issues. However, in some individuals, they may coincide with bilirubin fluctuations. Is It Dangerous? Gilbert’s syndrome is not dangerous. It does not: Damage the liver Lead to liver failure or cirrhosis Increase the risk of hepatitis or other liver diseases Require lifelong medication The key concern with the condition is mistaken diagnosis, particularly when jaundice appears suddenly. This may prompt unnecessary investigations unless a proper diagnosis has already been made. How It’s Diagnosed Gilbert’s syndrome is usually discovered when: Routine blood tests show elevated unconjugated bilirubin levels Liver enzymes (ALT, AST, ALP) and other liver function tests are completely normal There are no signs of liver damage or other abnormalities Doctors may confirm the diagnosis through: Repeat fasting bilirubin tests Genetic testing (to confirm UGT1A1 mutation), although this is not always necessary Ruling out more serious causes of jaundice, such as hepatitis, haemolytic anaemia, or gallbladder disease Once diagnosed, no further testing is usually needed unless new symptoms arise. Emotional and Social Impact While the condition is medically benign, some people experience emotional distress when symptoms first appear—especially the sudden onset of jaundice. Common concerns include: Fear of having liver disease or cancer Embarrassment about visible jaundice Anxiety during exams or work stress that may trigger symptoms Clear explanation, reassurance, and confirmation of the benign nature of the condition are crucial in helping individuals adjust. Living with Gilbert’s Syndrome Most people live completely normal lives. Management focuses on avoiding known triggers, such as: Skipping meals or prolonged fasting Dehydration Overexertion without recovery Poor sleep or high stress Dietary and lifestyle tips may help reduce the likelihood of bilirubin spikes: Eat regular meals with balanced nutrients Stay well hydrated Get sufficient sleep and rest Manage stress with exercise, mindfulness, or relaxation techniques There is no need to follow a special liver diet unless recommended for another condition. Medications and Gilbert’s Syndrome Certain medications may be processed differently in people with Gilbert’s syndrome. These include: Irinotecan, a chemotherapy drug—higher risk of side effects due to reduced metabolism Paracetamol (acetaminophen)—generally safe in normal doses, but caution advised if used excessively Statins and antivirals—usually safe, but liver monitoring may be recommended It’s important to inform healthcare providers about the condition, especially before starting any new medication. Conclusion | Gilbert’s Syndrome Gilbert’s syndrome is a harmless but often misunderstood condition. By recognising the signs, understanding the underlying mechanism, and avoiding unnecessary worry or invasive testing, people with this condition can lead full, healthy lives without limitations. [Next: Causes of Gilbert’s Syndrome →]

Gilbert’s Syndrome Read More »

Scroll to Top