Mental Matters

Health & Wellness

Woman coughing on a sofa, showing signs of illness possibly linked to HIV

Symptoms of HIV

Symptoms of HIV vary widely depending on the infection stage, immune response, and whether treatment has started. Understanding the symptoms of HIV helps with early detection, timely diagnosis, and knowing when to seek medical care. HIV symptoms often mimic common illnesses or remain silent for years, which contributes to underdiagnosis. Phases and Symptoms of HIV HIV progresses through three main stages, each with different symptoms: Not everyone experiences all symptoms, and some people may have no noticeable signs until the virus is advanced. Acute HIV Infection (Primary Stage) Within 2 to 4 weeks after exposure, many people develop acute retroviral syndrome, a flu-like illness that lasts days to weeks. Early symptoms include: This stage is highly infectious due to a high viral load but is often mistaken for a cold or flu. Chronic HIV Infection (Clinical Latency Stage) Following the acute phase, HIV enters a clinical latency period where symptoms may be absent or mild. The virus continues to replicate at low levels, slowly weakening the immune system. Untreated or poorly managed HIV during this phase may cause: Advanced HIV Infection (AIDS) Without treatment, HIV progresses to AIDS, defined by a CD4 count below 200 cells/mm³ or AIDS-defining illnesses. Symptoms are severe and life-threatening, including: Gender-Specific and Paediatric Symptoms Women with HIV may experience: Children may show signs such as: Early testing is especially critical for children born to HIV-positive mothers. Importance of Recognising HIV Symptoms Early recognition leads to prompt testing and treatment, which prevents disease progression and improves quality of life. Due to the variable symptoms and stigma, many people delay diagnosis. Public education and routine screening are vital, especially for high-risk groups. Symptoms After Starting Treatment Some individuals on antiretroviral therapy (ART) may experience immune reconstitution inflammatory syndrome (IRIS), a temporary worsening of symptoms caused by immune recovery. Despite this, most people see improved health, reduced symptoms, and increased energy after starting treatment. Summary Symptoms of HIV range from mild flu-like signs to severe life-threatening conditions depending on the infection stage and care access. Awareness, early testing, and treatment are essential to prevent progression to AIDS. Reducing stigma and educating communities helps individuals seek care sooner, improving personal and public health outcomes. [Next: Diagnosis of HIV →]

Symptoms of HIV Read More »

Positive HIV test result in a labelled blood sample tube

Diagnosis of HIV

The diagnosis of HIV is a crucial step in preventing disease progression, reducing transmission, and improving long-term health outcomes. Early detection enables people to start treatment while their immune system is strong, significantly increasing life expectancy and quality of life. Timely diagnosis also helps stop the spread of HIV to others. Despite major advances in testing technology, stigma, fear, and lack of awareness still delay diagnosis for many individuals. Understanding the available testing methods and their importance is key to ending the HIV epidemic. Why HIV Diagnosis Matters HIV attacks CD4 cells (T-helper cells), weakening the immune system over time. Without testing, HIV may remain undetected for years until severe complications occur. Late diagnosis is a major reason why some people progress to AIDS—the most advanced stage of HIV infection. Routine and accessible testing is the most effective strategy for early detection and prevention. Who Should Get Tested for HIV? Global health guidelines recommend regular HIV testing for: High-risk groups may need testing every 3–6 months. Types of HIV Tests HIV diagnosis relies on detecting antibodies, antigens, or the virus itself. Common tests include: 1. Antibody Tests 2. Antigen/Antibody Tests (4th Generation) 3. Nucleic Acid Tests (NAT) Confirming an HIV Diagnosis A single positive test does not confirm HIV. Follow-up tests are required: The HIV Window Period The window period is the time after infection when tests may not yet detect HIV: Retesting may be necessary if the initial test was taken too soon after exposure. HIV Self-Testing Home test kits allow private testing using oral fluid or a finger-prick of blood. While convenient, self-tests are screening tools only. Positive results must be confirmed at a clinic. Self-testing is especially helpful for people avoiding clinics due to stigma. HIV Testing in Special Populations Emotional Support After Diagnosis An HIV diagnosis can be emotionally overwhelming. Fear, shame, and anxiety are common. Immediate counselling and support services help individuals cope and plan treatment. Healthcare providers should deliver results with compassion and provide clear next steps for care and prevention. Importance of Early HIV Diagnosis Early diagnosis allows people to start antiretroviral therapy (ART), which: People diagnosed early and treated promptly can live long, healthy lives. Bottom line: The diagnosis of HIV is faster, more accurate, and more accessible than ever. But stigma and inequality still delay testing. Expanding awareness, improving access, and offering compassionate care remain key in the global fight against HIV. [Next: Treatment of HIV →]

Diagnosis of HIV Read More »

Antiretroviral HIV medication on HIV/AIDS label background

Treatment of HIV

The treatment of HIV has turned a once-fatal infection into a manageable chronic condition. With proper care and medication, people living with HIV can lead long, healthy lives. The main treatment for HIV is antiretroviral therapy (ART), a combination of drugs that suppress the virus, protect the immune system, and prevent HIV-related complications. Although there is no cure for HIV yet, early and consistent treatment lowers viral load, restores immune function, and stops transmission. People who take ART and achieve an undetectable viral load cannot transmit HIV sexually—a concept known as U=U (Undetectable = Untransmittable). Goals of HIV Treatment The treatment of HIV aims to: Maintaining viral suppression prevents HIV from advancing to AIDS. What Is Antiretroviral Therapy (ART)? ART combines at least three drugs from two or more classes to block HIV at different stages of its lifecycle. This approach stops replication and reduces drug resistance. Main ART drug classes include: Most modern ART comes as a single daily pill, improving adherence. When Should ART Start? Immediately. All people diagnosed with HIV should begin ART as soon as possible. Early treatment: Delaying treatment can cause irreversible immune damage. Monitoring HIV Treatment After starting ART, regular check-ups are essential. Doctors monitor: Managing Side Effects Most people tolerate ART well, but early side effects may include: These usually improve with time or medication changes. Long-term issues like high cholesterol or bone loss require regular monitoring. Importance of Adherence Strict adherence is the key to treatment success. Missing doses can lead to viral rebound and drug resistance. Tools to improve adherence include: Special Treatment Considerations New Advances in HIV Treatment Treatment as Prevention (U=U) People with an undetectable viral load cannot transmit HIV sexually. This powerful fact reduces stigma and prevents new infections. The Future of HIV Care Research into an HIV cure continues, with gene editing and immune therapies showing promise. Until then, widespread ART access, education, and global cooperation remain vital. Bottom line: The treatment of HIV turns the virus into a manageable condition. With early ART, regular monitoring, and strong support systems, people with HIV can expect a long and healthy life. [Next: Complications of HIV →]

Treatment of HIV Read More »

Doctor counselling a patient about complications of HIV infection

Complications of HIV

The complications of HIV vary based on how early the infection is found, how well antiretroviral therapy (ART) works, and the person’s overall health. If HIV is untreated, the immune system weakens over time. This makes the body vulnerable to infections and some cancers. Even with treatment, long-term issues may occur because of inflammation, immune activation, or drug side effects. Understanding the complications of HIV helps patients and doctors manage health more effectively. Complications can be infectious or non-infectious. Infectious complications come from germs taking advantage of weak immunity. Non-infectious complications come from HIV itself or its treatment. ART greatly reduces the risk of both, but ongoing care is essential. Opportunistic Infections Opportunistic infections (OIs) are among the most common complications of HIV when ART is not used. These infections strike when the immune system becomes too weak to fight everyday germs. A CD4 count below 200 cells/mm³ raises the risk. Common OIs include: ART, antibiotics, and CD4 monitoring reduce these risks greatly. HIV-Related Cancers Another major group of complications of HIV includes cancers. Some are AIDS-defining cancers, which signal severe immune weakness. Key cancers include: HIV also raises the risk of anal cancer, liver cancer, and lung cancer because of chronic inflammation and co-infections. Neurological Complications HIV can cross into the brain and affect the nervous system. ART lowers this risk, but problems still occur, especially without treatment. Common neurological complications: Regular check-ups and early ART help prevent these issues. Heart and Blood Vessel Problems HIV increases the risk of heart disease because of inflammation, drug effects, and lifestyle habits like smoking. Common issues include: Healthy lifestyle changes and regular heart checks are vital. Kidney and Liver Complications HIV can damage the kidneys and liver directly or through co-infections. Blood tests monitor these organs regularly in people on ART. Metabolic and Bone Problems HIV and ART can lead to: Healthy eating, exercise, and medication adjustments help manage these problems. Final Thoughts on HIV Complications The complications of HIV can affect almost every body system if left untreated. But with early testing and strict ART use, most complications can be avoided or treated. Regular check-ups and full-body care are the best ways to stay healthy with HIV. [Next: Outlook for HIV →]

Complications of HIV Read More »

Group of hands holding red HIV awareness ribbons in unity

Outlook for HIV

The outlook for HIV has changed dramatically in recent years. Once seen as a deadly disease, HIV is now a manageable condition for millions worldwide. This shift is thanks to antiretroviral therapy (ART), introduced in the mid-1990s. Since then, better medicines, improved tests, and strong public health efforts have boosted life expectancy and quality of life. Today, the outlook for HIV is very positive—if the infection is found early and treatment starts without delay. With proper treatment and care, people with HIV can live almost as long as those without the virus. Many work, start families, and live full lives. Support from counselling, education, and anti-stigma programs has also improved outcomes. Life Expectancy and HIV Life expectancy shows how much the outlook for HIV has improved. In countries with good healthcare, people diagnosed in their 20s can live nearly the same lifespan as HIV-negative people. In lower-income areas, expanding access to treatment is closing the gap. Early diagnosis matters. Starting ART soon protects the immune system, reduces inflammation, and prevents AIDS-related illness. People who begin treatment with higher CD4 counts usually do better over time. U=U: Undetectable Means Untransmittable A key milestone in the outlook for HIV is U=U—Undetectable = Untransmittable. People with an undetectable viral load cannot pass HIV to sexual partners. This changes how we think about intimacy and prevention. The benefits of U=U include: To keep the virus undetectable, people must take ART consistently and attend regular check-ups. Ageing with HIV More people with HIV are living into their 50s and beyond. This creates new challenges: Healthcare systems must adapt and provide complete care for older adults living with HIV. Quality of Life with HIV The outlook for HIV is not just about survival. Quality of life matters too. Many people thrive when they have: Community groups, advocacy programs, and legal support all help improve daily life for people with HIV. The Global HIV Response Globally, the outlook for HIV is hopeful but needs work. UNAIDS aims to end AIDS as a public health threat by 2030. Key actions include: Funding gaps, stigma, and inequality remain big challenges. But progress so far is promising. HIV Cure Research Even though ART works well, the search for a cure continues. Two main types of cures are under study: Scientists are exploring gene editing, vaccines, and stem cell therapy. A few people, such as the “Berlin” and “London” patients, have already been cured. These cases offer hope, but ART is still the main treatment for now. Empowerment and Advocacy The outlook for HIV is also shaped by empowerment. People living with HIV are leaders, advocates, and educators. They fight stigma, push for better care, and inspire others. Living well with HIV is about health, but also dignity, equality, and community. In Summary The outlook for HIV has never been brighter. Early testing, lifelong ART, and strong social support help people live long, healthy lives. Science is moving toward better treatments and, one day, a cure. Together, we can make ending HIV a reality. [Next: Back to Overview →]

Outlook for HIV Read More »

Sick toddler lying on couch clutching abdomen in pain

Hirschsprung’s Disease

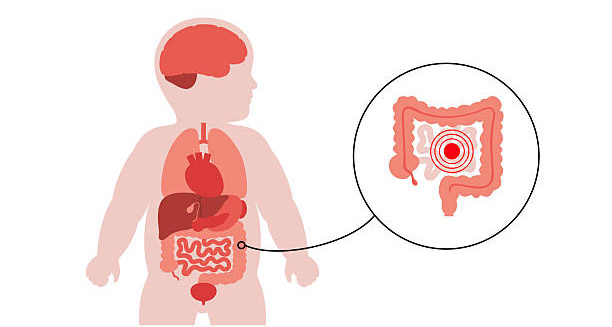
Hirschsprung’s disease is a rare bowel disorder present at birth. It happens when nerve cells that help the bowel move stool are missing from parts of the large intestine. These nerve cells, called ganglion cells, allow the bowel to relax and push waste through. Without them, the affected bowel stays tight and blocks stool. This leads to severe constipation and sometimes infection. Hirschsprung’s disease often shows soon after birth. Some mild cases appear later in infancy or early childhood. What Happens in the Bowel In a healthy bowel, food moves forward because muscles contract in a pattern. This process is controlled by nerve cells in the bowel wall. These cells form early in pregnancy and travel down the colon during growth. In Hirschsprung’s disease, this movement stops too soon. The lower part of the bowel does not get enough nerve cells. The longer the section without nerves, the worse the symptoms. In 80% of cases, only the rectum and sigmoid colon are involved. In severe cases, the whole large bowel or part of the small bowel is affected. How Common Is It? This condition affects about 1 in 5,000 births. It is four times more common in boys than girls. Children with Down syndrome or other genetic conditions have a higher risk. While Hirschsprung’s disease often happens by chance, some cases run in families. When longer bowel segments are involved, family history is more likely. Signs and Early Warning One clear sign in newborns is not passing meconium (the first stool) in the first 48 hours. Babies may also have a swollen belly, vomiting, or feeding problems. In severe cases, the blocked bowel can cause enterocolitis. This is a dangerous infection that can lead to dehydration, sepsis, or a hole in the bowel. Quick diagnosis and treatment are vital. Symptoms in Older Children If the condition is missed at birth, children often suffer from constant constipation. They may have a big belly, poor weight gain, and loss of appetite. Some pass watery stool around hard masses in the bowel. This is called overflow diarrhoea and can confuse doctors. Over time, these children may grow slowly and feel unwell. How Doctors Confirm the Diagnosis When doctors suspect Hirschsprung’s disease, quick referral to a specialist is important. Tests include a contrast enema X-ray to look for a “transition zone” where the bowel changes shape. Another test, anorectal manometry, checks muscle function. The only way to confirm the disease is with a rectal biopsy. This test shows if nerve cells are missing. Treatment and Outlook Surgery is the main treatment for Hirschsprung’s disease. The most common surgery is a pull-through operation. Doctors remove the part of the bowel without nerves and join the healthy part to the anus. Many hospitals use keyhole (minimally invasive) surgery for this. If the child is very sick or has infection, doctors may first create a colostomy to allow recovery. Later, the main surgery is done. Most children do well after surgery, but some may have constipation, soiling, or infections for a while. They may need medicine, diet changes, or physiotherapy to help. Regular follow-up visits are important to check growth and bowel health. Life After Surgery Most children lead normal lives after treatment. But some may have long-term problems like constipation or repeated infections. The condition can also cause stress for older children. Support from doctors, therapists, and parent groups helps families cope. Early diagnosis and surgery give the best results. Parents should watch for signs such as delayed meconium or swollen belly in newborns. While Hirschsprung’s disease can seem scary, advances in surgery and care have improved outcomes. With proper treatment, most children gain full bowel control and grow well. Looking Ahead Research on the genes that cause Hirschsprung’s disease may lead to earlier diagnosis and new treatments in the future. Surgical techniques also keep improving, giving affected children a brighter outlook. [Next: Causes of Hirschsprung’s Disease →]

Hirschsprung’s Disease Read More »

Digital illustration of virus near developing foetus representing genetic causes of Hirschsprung’s Disease

Causes of Hirschsprung’s Disease

Understanding the causes of Hirschsprung’s disease begins with knowing it is present at birth. This disorder starts early in pregnancy when nerve cells do not finish their normal movement through the bowel. These cells, called ganglion cells, control the bowel muscles that push stool forward. When this process fails, part of the bowel cannot relax, causing a blockage. The main causes of Hirschsprung’s disease are genetic changes and problems during early growth in the womb. The severity can vary in each child. How the Problem Starts The bowel nerves form between weeks five and twelve of pregnancy. Special cells from the neural crest move into the gut wall and become ganglion cells. These cells allow peristalsis, the wave-like motion that moves food through the gut. In Hirschsprung’s disease, this movement stops too soon. Parts of the colon or sometimes the small bowel do not get nerve cells. These areas stay tight and block stool. Waste and gas then build up above the blockage. Role of Genes The main reason for this failure is genetic. The RET gene is the most common cause. It makes a protein that helps nerve cells grow. Other important genes include EDNRB, EDN3, GDNF, and SOX10. These work together in a complex system. A change in one or more of them can stop nerve growth in the bowel. The condition can run in families. In some cases, it appears by chance. If there is a family history, the risk for siblings is higher. The inheritance pattern may be dominant or recessive, depending on the gene and the length of bowel affected. Longer bowel segments often run more strongly in families. Boys get short-segment disease more often than girls. Long-segment disease affects both sexes equally. Links with Genetic Syndromes Hirschsprung’s disease can also occur with chromosomal problems. Down syndrome is the most common. Up to 10% of children with Hirschsprung’s also have Down syndrome. Other linked conditions include Waardenburg syndrome, Mowat-Wilson syndrome, and CCHS (congenital central hypoventilation syndrome). These links show how nerve development issues play a key role in this disease. Do Environment or Pregnancy Factors Matter? Environmental factors do not seem to cause Hirschsprung’s disease. However, doctors believe that unknown changes in the womb or gene activity might play a small role. No strong link has been found with a mother’s diet, lifestyle, or infections during pregnancy. This makes the condition very different from other birth defects caused by outside factors. How Much of the Bowel Is Affected? The length of bowel without nerve cells varies. In most children (about 80%), only a short part of the rectum or sigmoid colon is involved. In 15–20%, the disease goes higher in the colon. Rarely, it affects the whole colon or even the small bowel. These severe forms usually appear soon after birth and often link to family history or other syndromes. Why Understanding the Causes Helps Research continues on the causes of Hirschsprung’s disease. Genetic studies now make diagnosis and family risk checks easier. Testing can help families plan early care and future pregnancies. In short, the causes of Hirschsprung’s disease come from early nerve growth problems in the bowel. These mainly result from gene changes in RET and other key genes. They sometimes occur with chromosomal syndromes. So far, no clear environmental risk is known. Learning these causes helps doctors give better advice, plan care, and improve outcomes for families. [Next: Symptoms of Hirschsprung’s Disease →]

Causes of Hirschsprung’s Disease Read More »

Crying baby lying on white sheet, indicating possible symptoms of Hirschsprung’s disease

Symptoms of Hirschsprung’s Disease

The symptoms of Hirschsprung’s disease can vary significantly depending on the age of the child, the length of the affected bowel, and the presence of complications. Early Symptoms in Newborns Some cases show up in the first days of life due to clear signs of bowel blockage. Others appear weeks or months later, especially in mild forms. Knowing the early symptoms of Hirschsprung’s disease is key for quick diagnosis and timely surgery. This prevents life-threatening problems and improves long-term outcomes. In newborns, one major sign is failure to pass meconium in the first 24 to 48 hours after birth. Meconium is the first dark stool most babies pass soon after delivery. In healthy infants, this happens without delay. In Hirschsprung’s disease, missing nerve cells stop normal stool movement. This leads to blockage. The baby often has a swollen belly, green or bilious vomiting, and refuses feeds. Severe cases may show enterocolitis. This is a dangerous bowel infection with fever, watery diarrhoea, and dehydration. Symptoms in Older Infants and Toddlers As babies grow, symptoms of Hirschsprung’s disease change. Older infants and toddlers often suffer from constant constipation that does not improve with diet, fluids, or common laxatives. Parents may notice bloating, fussiness, and feeding troubles. The child may pass only small, hard stools now and then. Sometimes, liquid stool leaks around the hard mass, called overflow incontinence. This can look like diarrhoea and confuse parents or doctors. The belly often stays big due to trapped gas and stool. Some children feel pain or cramps after meals. Poor appetite and slow weight gain follow. Over time, long-term constipation and bowel swelling affect growth and health. If untreated, the bowel can tear or severe enterocolitis can happen. Both are emergencies. Symptoms in Older Children Older kids and even teens with untreated Hirschsprung’s disease may have subtle signs. They may deal with constant constipation, stool accidents, or stress from bathroom issues. Some need enemas or rectal washes to pass stool. This can cause shame, low confidence, and social withdrawal. A full medical history and proper tests prevent misdiagnosis as functional constipation. Hirschsprung-Associated Enterocolitis A serious symptom of Hirschsprung’s disease is enterocolitis. It can happen at any age but is most common in young children. It starts suddenly with fever, belly pain, bad-smelling diarrhoea, and dehydration. Bacteria and trapped stool in the bowel cause this. If untreated, it can lead to shock or bowel rupture. Quick treatment with antibiotics, bowel rest, and fluids is vital. Even after surgery, it can return, so close watch is needed. Why Symptoms Vary The symptoms of Hirschsprung’s disease often cause confusion and delay diagnosis. Constipation is common in kids, so doctors may blame diet, stress, or habits. Hirschsprung’s should be suspected when constipation is severe, does not improve, or comes with belly swelling, late meconium, or blockage signs. The length of the bowel without nerves also changes symptoms. Short-segment disease affects only the lower bowel, so signs may appear later and seem mild. Long-segment or total colonic disease appears in newborns, with severe symptoms and high risk of complications. Children with large affected areas often have other problems or genetic syndromes. Why Quick Action Matters Recognising the symptoms of Hirschsprung’s disease early is essential for proper care. Parents should watch for bowel issues from birth, especially if family history or related conditions like Down syndrome exist. Doctors must stay alert in cases of stubborn constipation or unexplained blockage. Fast referral, correct tests, and early surgery greatly improve a child’s quality of life. The sooner the condition is found and treated, the better the outcome. [Next: Diagnosis of Hirschsprung’s Disease →]

Symptoms of Hirschsprung’s Disease Read More »

Paediatric doctor explaining diagnostic tools for Hirschsprung’s disease to mother with infant

Diagnosis of Hirschsprung’s Disease

The diagnosis of Hirschsprung’s disease is a critical step in ensuring prompt and effective treatment. Why Early Diagnosis Matters This condition affects the large intestine from birth. Early detection lowers the risk of complications and long-term digestive problems. The diagnosis of Hirschsprung’s disease can happen soon after birth or later in childhood. This depends on the severity and length of the affected bowel segment. Timely recognition needs careful symptom checks, specific tests, and confirmation through biopsy. Key Warning Signs in Newborns Newborns with signs of bowel blockage—like a swollen belly, green vomiting, or no meconium within 48 hours—need urgent care. In such cases, Hirschsprung’s disease should be considered. Mild cases show signs later, such as chronic constipation and poor growth. These often delay diagnosis. A detailed medical history and physical exam guide the first suspicion and choice of tests. Common Diagnostic Tests The first test is usually a contrast enema X-ray. This shows the shape of the large bowel. In this test, a special dye is placed in the rectum and colon to outline the intestine. Children with Hirschsprung’s disease often show a “transition zone.” This means a narrow lower bowel without nerve cells, followed by a swollen section above it. This finding suggests the disease but does not confirm it. In very young babies or unusual cases, the transition zone may not appear clearly. More tests may then be needed. Another useful test is anorectal manometry, often for older infants and children. This checks the function of the anal muscles. Normally, when the rectum fills, the internal anal muscle relaxes. This is called the rectoanal inhibitory reflex (RAIR). In Hirschsprung’s disease, this reflex does not happen because the bowel lacks nerve cells. This test is non-invasive and good for short-segment disease. But it can be hard to do in newborns. Biopsy: The Confirming Test The definite diagnosis of Hirschsprung’s disease needs a rectal biopsy. Doctors take a small tissue sample from the rectum to look under a microscope. They check for nerve cells and thick nerve fibres. In babies, a suction biopsy is often used. It does not need full anaesthesia and samples the layers that hold the nerve cells. If the sample shows no nerve cells and thick nerve fibres, the diagnosis is confirmed. Older children or unclear cases may need a full-thickness biopsy. This uses general anaesthesia and removes a deeper piece of bowel wall. Special stains like AChE or immunohistochemistry help show nerve structures. Though more invasive, this test gives accurate results for complex cases. Extra Imaging and Genetic Testing Sometimes, extra imaging like ultrasound or MRI is used. These tests show bowel swelling or related problems. They do not confirm Hirschsprung’s disease but help rule out other causes. In some families, doctors also do genetic tests. Genes like RET, EDNRB, and SOX10 can cause the condition. Finding these helps in planning, but it is not needed for the first diagnosis. Ruling Out Similar Conditions It is important to separate Hirschsprung’s disease from other problems like hypothyroidism, meconium plug syndrome, or bowel movement disorders. Wrong diagnosis delays treatment and raises risks. That is why a team approach with paediatricians, surgeons, gastro doctors, and pathologists works best. Why Timely Diagnosis Saves Lives Early and correct diagnosis prevents long suffering and allows fast surgery to restore bowel function. It lowers the risk of infection, bowel perforation, and growth failure. Once doctors confirm the condition, families can get support and prepare for surgery and aftercare. Doctors must stay alert for Hirschsprung’s disease in children with lasting constipation, especially when usual treatments fail. Signs like no stool in the first two days, repeated vomiting, a swollen belly, and poor weight gain need quick attention. A careful and active approach to diagnosis is the first step in helping children live healthy lives. [Next: Treatment of Hirschsprung’s Disease →]

Diagnosis of Hirschsprung’s Disease Read More »

Treatment of Hirschsprung’s Disease

Treatment of Hirschsprung’s Disease

The treatment of Hirschsprung’s disease is centred around surgical intervention aimed at removing the affected section of bowel that lacks nerve cells, thereby restoring normal intestinal function. Why Surgery is Important The aganglionic segment cannot move stool. This causes blockage, infection, and poor nutrition. Early and proper treatment of Hirschsprung’s disease prevents serious problems and improves long-term results for children. Most cases need surgery within the first year, often soon after diagnosis. The main surgery is called a pull-through procedure. It removes the diseased bowel and connects the healthy part to the anus. The goal is to keep continence and normal bowel function while clearing the blockage. Different techniques exist, such as Swenson, Soave, and Duhamel. Each uses a slightly different method to remove and reconnect the bowel. Modern Surgical Options Today, surgeons often use minimally invasive or laparoscopic pull-through surgery. This reduces recovery time, scarring, and infection risk. In some centres, the operation is done entirely through the anus, called a transanal pull-through. No matter the method, the aim is to remove the diseased part and make sure the rest of the bowel works well. When a child is very sick—due to enterocolitis, large bowel swelling, or poor nutrition—the surgery may happen in two steps. First, doctors create a diverting ostomy. They bring part of the healthy bowel to the surface of the abdomen to form a stoma (opening). This allows waste to exit into a colostomy bag. This gives the bowel time to heal while the child gains strength and better nutrition. Later, the pull-through surgery is done, and the ostomy is closed. Care After Surgery Post-surgical care is key in the treatment of Hirschsprung’s disease. Many children get back normal bowel habits. Some face problems like constipation, soiling, or enterocolitis. Constipation is common after surgery, especially if a short part of bowel still does not work well. Doctors usually manage this with diet changes, stool softeners, or bowel training under supervision. Another issue is Hirschsprung-associated enterocolitis. It can happen even after surgery. Parents learn to watch for warning signs such as fever, diarrhoea, and a swollen belly. They must seek care fast if these appear. Treatment includes antibiotics and rectal washes. In children with repeated episodes, preventive care may be needed. Managing Ongoing Problems Some children may soil or struggle with incontinence, which can be stressful. This often happens because of delayed toilet training or bowel movement issues, not due to surgery errors. Time, specialist care, and bowel programs usually help. Paediatric gastroenterologists and occupational therapists often guide families through this stage. Rarely, when the first surgery fails or problems remain, doctors may need to do another surgery. This could mean removing more bowel or fixing the connection. Children with long-segment or total colonic disease often have harder recoveries. They might need extra feeding support or even intravenous nutrition in severe cases. Long-Term Support and Monitoring All children need regular check-ups after treatment of Hirschsprung’s disease. These visits track growth, bowel habits, and early signs of new issues. Some children benefit from emotional support, especially older kids who feel embarrassed about toileting. Parents also need education. They must know how to care for the bowel, keep hygiene, and notice danger signs. Support groups and counselling can help families cope. Families with a history of Hirschsprung’s disease may also need genetic counselling. This helps them understand the risk of having another child with the same problem and plan for early checks. Future of Treatment New research is looking at stem cell therapy and other methods that may work with or replace surgery. These treatments are not available yet, but they show promise for the future. Conclusion The treatment of Hirschsprung’s disease involves surgery, aftercare, regular follow-up, and family support. Most children recover well and live healthy lives. Still, ongoing care is important for problems like constipation or infections. Early and strong treatment makes a big difference in the quality of life for both child and family. [Next: Complications of Hirschsprung’s Disease →]

Treatment of Hirschsprung’s Disease Read More »

Scroll to Top