Mental Matters

Health & Wellness

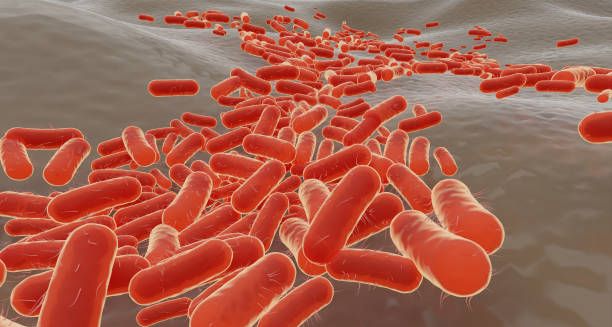
3D illustration of Haemophilus influenzae type b bacteria under magnification.

Causes of Haemophilus influenzae type b

Causes of Haemophilus influenzae type b The causes of Haemophilus influenzae type b disease centre around the bacterium’s ability to enter the body, evade the immune system, and infect vital tissues. Although the causes of Haemophilus influenzae type b illness are well understood in terms of transmission and pathophysiology, certain risk factors can increase the likelihood of severe infection, especially in young children or those with underdeveloped immune defences. Haemophilus influenzae type b (Hib) does not cause disease in everyone it infects. In fact, many people—especially adults—can carry the bacteria in their nose or throat without ever becoming ill. The danger arises when the bacteria penetrate beyond the respiratory tract into areas of the body that are normally sterile, such as the bloodstream, brain, or lungs. 1. Transmission and Entry into the Body Hib spreads from person to person through respiratory droplets. When an infected person sneezes, coughs, or speaks, they release bacteria into the air. These bacteria can then: Colonise the nasopharynx, the upper part of the throat behind the nose Remain harmless in many carriers Cross mucosal barriers under certain conditions, especially when the immune system is compromised Once past the mucosal defences, Hib can: Enter the bloodstream, leading to sepsis Travel to the meninges, causing meningitis Infect the lungs, joints, or bones 2. Capsule-Driven Virulence What sets Hib apart from other types of Haemophilus influenzae is its polysaccharide capsule, known as type b capsule. This capsule: Protects the bacterium from being destroyed by immune cells (phagocytes) Inhibits complement-mediated killing (a key immune system response) Allows the bacteria to survive in the bloodstream and spread throughout the body Strains without this capsule (non-typeable H. influenzae) are less invasive and usually only cause mild respiratory illness or ear infections. 3. Host Factors That Increase Risk Certain individuals are more susceptible to invasive Hib disease due to underlying conditions, such as: a. Young Age Children under five have immature immune systems, making it harder for them to fight off encapsulated bacteria Maternal antibodies may wear off before vaccines take full effect b. Lack of Vaccination Unvaccinated children are at high risk, especially in regions with poor immunisation coverage Delayed or missed vaccine doses reduce protection c. Immunodeficiency Children and adults with conditions like HIV, cancer, or those undergoing immunosuppressive therapy These individuals are less able to clear infections from the bloodstream d. Asplenia (No Spleen) The spleen plays a crucial role in removing encapsulated bacteria People without a functioning spleen (due to trauma, surgery, or disease) are highly vulnerable to Hib e. Malnutrition Poor nutritional status weakens the immune response Increases the severity and duration of infections f. Crowded Living Conditions Hib spreads more easily in settings where close contact is common, such as schools, nurseries, and refugee camps 4. Environmental and Geographic Factors Haemophilus influenzae type b disease is more prevalent in: Low-income countries, where vaccination access is limited Areas with poor public health infrastructure Regions with high rates of respiratory infections, which can facilitate bacterial entry In countries with high vaccine uptake, most Hib cases occur in: Unvaccinated individuals Children who are too young to have received the full vaccine course Immigrant populations from countries without routine Hib immunisation 5. Co-Infections and Viral Illness Viral infections like influenza, RSV, or adenovirus can: Damage the respiratory tract lining Create an entry point for bacteria like Hib Suppress immune responses temporarily This sets the stage for secondary bacterial infections, increasing the likelihood that Hib will invade deeper tissues. 6. Genetic Susceptibility (Under Investigation) Some research suggests that genetic differences in immune system regulation may influence: The body’s ability to recognise and destroy Hib Susceptibility to invasive disease in early childhood Response to vaccination Although not yet fully understood, this area remains a focus of ongoing scientific investigation. Summary Table: Key Factors Contributing to Hib Infection Contributing Factor Role in Disease Respiratory droplet exposure Main route of transmission Type b capsule Protects bacteria from immune attack Young age Weaker immune defence in infants Unvaccinated status Lack of protection increases risk Immunodeficiency Reduces ability to fight infection Crowded conditions Facilitates spread of bacteria Viral co-infections Compromise respiratory defences Conclusion | Causes of Haemophilus influenzae type b The causes of Haemophilus influenzae type b infection are multifactorial, involving bacterial virulence, host immune status, and environmental exposure. Understanding these causes of Haemophilus influenzae type b is essential to guide prevention, particularly through timely vaccination and targeted public health strategies in vulnerable populations. [Next: Symptoms of Haemophilus influenzae type b→]


Causes of Haemophilus influenzae type b Read More »

Mother checking the temperature of a sick child wrapped in a blanket.

Symptoms of Haemophilus influenzae type b

Symptoms of Haemophilus influenzae type b Identifying the symptoms of Haemophilus influenzae type b (Hib) promptly is crucial, as this bacterial infection can progress rapidly, leading to severe complications or even death if untreated. Recognising the symptoms of Haemophilus influenzae type b early can significantly improve patient outcomes and reduce the risk of serious long-term effects. Hib typically affects young children under five years old, though it can occasionally occur in adults, particularly those with compromised immune systems. Initial symptoms often appear mild and similar to common infections, making early recognition challenging. In the early stages, patients might experience fever, lethargy, and irritability. These nonspecific symptoms can easily be mistaken for common viral infections or the flu, particularly in children who might not clearly express their discomfort or pain. As the infection progresses, however, the symptoms become more distinctive and severe, often indicating invasive disease. Symptoms of Haemophilus influenzae type b Meningitis caused by Hib is one of the most serious manifestations. Symptoms indicative of meningitis include a stiff neck, severe headache, photophobia (sensitivity to light), vomiting, altered consciousness, and seizures. In young infants, the classic stiff neck might be absent, and they may instead present with poor feeding, inconsolable crying, high fever, and a bulging fontanelle (soft spot on the head). Parents and caregivers should seek immediate medical attention if any of these symptoms are observed. Another common invasive condition caused by Hib is epiglottitis, a severe swelling of the epiglottis that can rapidly obstruct the airway. Patients with epiglottitis typically show sudden onset of symptoms such as difficulty breathing, drooling due to an inability to swallow saliva, a hoarse voice, and a characteristic posture of leaning forward with an extended neck (known as the tripod position) to ease breathing. Epiglottitis is a medical emergency and requires immediate intervention to secure the airway. Symptoms of Haemophilus influenzae type b Pneumonia is also associated with Hib infections, presenting with symptoms including coughing, difficulty breathing, rapid breathing, chest pain, and fever. Unlike mild respiratory illnesses, Hib-related pneumonia can quickly worsen, necessitating prompt medical intervention to prevent severe complications or fatalities. Less commonly, Hib can cause cellulitis, a deep skin infection characterised by redness, warmth, swelling, and tenderness of the skin, usually on the face, particularly around the cheeks and eyes. The infected skin area can expand rapidly, and patients often experience fever and general malaise alongside localised symptoms. Septic arthritis, another possible manifestation, presents as joint swelling, severe pain and redness. Additionally, warmth of the affected joint, typically accompanied by a high fever. Infants may refuse to move the affected limb or become unusually irritable when the joint is touched or moved. Bacteraemia, or bloodstream infection, caused by Hib, can present initially with nonspecific symptoms such as high fever. As well as chills, rapid breathing, and extreme fatigue. If untreated, bacteraemia can lead to sepsis, a life-threatening condition characterised by organ dysfunction and shock. Symptoms of Haemophilus influenzae type b Early recognition of the symptoms of Haemophilus influenzae type b is essential for rapid initiation of treatment. Caregivers, parents, and healthcare professionals must maintain vigilance. Especially in unvaccinated populations or immunocompromised individuals, as Hib infections can rapidly escalate into severe and life-threatening conditions. [Next: Diagnosis of Haemophilus influenzae type b→]

Symptoms of Haemophilus influenzae type b Read More »

Mother caring for sick child lying on sofa with tissues and thermometer.

Diagnosis of Haemophilus influenzae type b

Diagnosis of Haemophilus influenzae type b Accurate and timely diagnosis of Haemophilus influenzae type b infections is critical to ensuring effective treatment and preventing severe outcomes. The diagnosis of Haemophilus influenzae type b primarily relies on laboratory tests, clinical assessment, and patient history. Healthcare professionals must remain alert to potential cases, particularly in unvaccinated or immunocompromised patients, as Hib infections can rapidly progress to severe illness or death if not promptly identified and managed. Initially, clinicians perform a thorough clinical assessment, evaluating symptoms and patient history. Recognising symptoms such as high fever, irritability, stiff neck, respiratory distress, and other specific signs indicative of invasive Hib diseases, such as meningitis or epiglottitis, provides a strong basis for suspicion of Hib infection. Once a clinician suspects Hib, laboratory confirmation is necessary. Blood cultures are among the most commonly utilised diagnostic tests for invasive Hib diseases. These cultures involve drawing blood from the patient and incubating it under conditions favourable for bacterial growth. If Haemophilus influenzae type b is present, it will multiply, allowing identification through microbiological techniques. Blood cultures are particularly useful in diagnosing bacteraemia and other invasive conditions caused by Hib. For suspected meningitis, clinicians often perform a lumbar puncture (spinal tap). Cerebrospinal fluid (CSF) obtained from this procedure undergoes analysis for cell count, glucose levels, protein concentration, and bacterial culture. Typically, Hib meningitis is associated with increased white blood cell counts (predominantly neutrophils), elevated protein levels, and reduced glucose levels in CSF. Bacterial culture of the CSF is essential for definitive diagnosis and antibiotic susceptibility testing. Diagnosis of Haemophilus influenzae type b In cases of suspected pneumonia caused by Hib, clinicians might request chest X-rays alongside blood cultures. Radiographic images can reveal characteristic signs of pneumonia, such as infiltrates, consolidation, or pleural effusion. While chest imaging is supportive, microbiological confirmation through blood or sputum cultures remains essential for definitive diagnosis. Epiglottitis, a life-threatening manifestation of Hib infection, is typically diagnosed clinically due to its rapid progression and severity. Nonetheless, confirmation is frequently obtained through direct visualisation during endoscopy, where a swollen, cherry-red epiglottis is observed. Throat cultures or blood cultures provide microbiological confirmation, though clinical suspicion alone often dictates immediate treatment to secure the airway and stabilise the patient. Rapid antigen detection tests (RADTs) and polymerase chain reaction (PCR) tests for Hib are increasingly utilised due to their speed and accuracy. PCR assays can detect Hib DNA directly from clinical specimens such as blood, CSF, or respiratory secretions, offering quicker results compared to traditional cultures, particularly important for critically ill patients. In less severe presentations, such as cellulitis or septic arthritis, diagnosis usually involves aspirating fluid from affected areas, such as joint fluid in arthritis or pus from cellulitis lesions, for Gram staining, culture, and PCR testing. Identifying Hib directly from these sites can confirm the diagnosis promptly. Diagnosis of Haemophilus influenzae type b Laboratory identification of Haemophilus influenzae type b typically involves examining bacterial colonies cultured on specialised media. Hib bacteria grow optimally on chocolate agar, a nutrient-rich medium containing factors required by the organism. Colonies typically appear smooth, round, and slightly convex, often producing a distinct odour. Further biochemical tests or serotyping confirm the identification. Prompt and accurate diagnosis of Haemophilus influenzae type b ensures timely initiation of appropriate antibiotic therapy, significantly improving patient outcomes. Early diagnosis not only facilitates rapid treatment but also helps implement public health measures, such as contact tracing and vaccination strategies, to prevent further spread of the infection. [Next: Treatment of Haemophilus influenzae type b→]
Diagnosis of Haemophilus influenzae type b Read More »

Medical professional administering vaccine to a patient’s arm

Treatment of Haemophilus influenzae type b

Treatment of Haemophilus influenzae type b Prompt and effective treatment of Haemophilus influenzae type b (Hib) infections is essential to prevent severe complications or death. The cornerstone of treatment of Haemophilus influenzae type b involves antibiotic therapy, supportive care, and occasionally surgical interventions depending on the clinical presentation and severity of the disease. Immediate medical attention and aggressive management can dramatically improve patient outcomes. Antibiotic therapy is crucial in managing Hib infections. Initial empirical antibiotic therapy often involves broad-spectrum antibiotics such as ceftriaxone or cefotaxime, effective against Hib strains. Doctors give these antibiotics through a vein so they can work quickly. This fast action helps the medicine reach the blood and tissues in time. As a result, it becomes easier to treat serious Hib infections like meningitis, epiglottitis, or blood infections.. Once laboratory results identify Hib and antibiotic sensitivity testing is available, clinicians might tailor antibiotic therapy accordingly, often continuing intravenous treatment for at least 7–14 days to ensure eradication of the bacteria. Treatment of Haemophilus influenzae type b For Hib meningitis, prompt initiation of antibiotic therapy significantly reduces mortality and neurological complications. Alongside antibiotics, corticosteroids like dexamethasone are sometimes administered shortly before or concurrently with antibiotics to reduce inflammation and minimise potential hearing loss and neurological damage. Close monitoring in a hospital setting is necessary to manage potential complications like seizures, cerebral oedema, or increased intracranial pressure. Epiglottitis requires immediate airway management alongside antibiotics. Patients typically require urgent hospitalisation and are often admitted to intensive care units for close observation. Due to potential airway obstruction, clinicians might perform immediate endotracheal intubation or tracheostomy to secure the airway before administering antibiotics. Supportive therapies, such as intravenous fluids and oxygen therapy, are essential to stabilise and manage patients effectively. Patients with Hib pneumonia or cellulitis typically receive antibiotics intravenously initially, with supportive therapies tailored according to symptoms such as respiratory support, hydration, and analgesics to manage pain. Early intervention prevents the progression to severe complications like sepsis or extensive tissue damage. Septic arthritis caused by Hib requires prompt drainage of infected joint fluid combined with antibiotic treatment. Orthopaedic interventions might involve repeated joint aspirations or surgical drainage procedures. To remove infected material effectively and alleviate pressure and pain in the joint. Treatment of Haemophilus influenzae type b Effective management of Hib infections also involves public health interventions. Such as prophylactic antibiotics administered to close contacts, particularly in household settings, to prevent secondary infections. Rifampicin is commonly recommended for chemoprophylaxis to eradicate nasopharyngeal carriage of Hib and prevent further transmission. [Next: Complications of Haemophilus influenzae type b→]
Treatment of Haemophilus influenzae type b Read More »

Three young children lying on a bed with tissues, showing cold or flu symptoms

Complications of Haemophilus influenzae type b

Complications of Haemophilus influenzae type b Identifying and managing potential complications of Haemophilus influenzae type b infections early can significantly impact long-term outcomes and survival rates. The complications of Haemophilus influenzae type b are often severe, affecting multiple organ systems, and require diligent clinical monitoring and intervention to minimise lasting damage or fatality. One of the most serious complications associated with Hib infections is meningitis. Even with appropriate treatment, meningitis can lead to severe neurological sequelae, including permanent hearing loss, intellectual disability, seizures, and cerebral palsy. Prompt antibiotic therapy and corticosteroids significantly reduce the incidence and severity of these neurological complications, but residual impairments may still persist in some patients, necessitating ongoing rehabilitation and supportive care. Epiglottitis, another severe complication of Hib, carries the immediate risk of airway obstruction, potentially leading to respiratory failure and death if untreated. Even after successful acute management, patients may suffer from prolonged hoarseness, difficulty swallowing, or chronic respiratory issues due to structural damage to the airway. Complications of Haemophilus influenzae type b Pneumonia resulting from Hib infection may escalate rapidly, leading to complications such as pleural effusion, empyema (accumulation of pus in the pleural space), lung abscesses, or respiratory failure. These complications require extensive medical and sometimes surgical interventions, prolonged hospital stays, and intensive rehabilitation efforts to restore pulmonary function fully. Bacteraemia, if not swiftly managed, can progress to sepsis, characterised by systemic inflammation, organ dysfunction, shock, and potential multi-organ failure. Sepsis necessitates aggressive intravenous fluid management, antibiotics, supportive therapies such as vasopressors, and close monitoring in intensive care units. Despite optimal treatment, severe sepsis can result in significant morbidity and mortality. Septic arthritis and cellulitis caused by Hib can also have serious long-term implications. Septic arthritis, if inadequately managed, might result in irreversible joint damage, chronic pain, and impaired mobility. Early surgical intervention and antibiotic therapy can minimise joint destruction and improve functional outcomes. Similarly, untreated or inadequately treated cellulitis can lead to widespread skin and soft tissue damage, scarring, and recurrent infections. Complications of Haemophilus influenzae type b Other potential long-term consequences of Hib infections include growth and developmental delays in children who experience severe systemic illness. Nutritional support, physiotherapy, occupational therapy, and psychological interventions may be necessary components of comprehensive care and recovery strategies. Preventing these complications primarily relies on vaccination against Hib, which has significantly reduced the incidence of invasive Hib diseases globally. Nonetheless, awareness and rapid intervention remain critical, especially in unvaccinated or immunocompromised populations. [Next: Back to Overview→]

Complications of Haemophilus influenzae type b Read More »

Man holding chest with liver illustration, indicating possible iron overload

Haemochromatosis

Haemochromatosis Haemochromatosis is a genetic condition in which the body absorbs and stores too much iron from the diet. Over time, this excess iron builds up in vital organs such as the liver, heart, and pancreas, leading to potential long-term damage. Without treatment, Haemochromatosis can cause serious complications including liver disease, heart problems, and diabetes. Often referred to as “iron overload disorder,” Haemochromatosis is one of the most common inherited conditions in people of Northern European descent. Despite this, many individuals remain undiagnosed for years, as early symptoms are vague and easily mistaken for other health issues. Fatigue, joint pain, and abdominal discomfort are among the first signs, but many cases are identified only after organ damage has occurred. What Is Haemochromatosis? Haemochromatosis is a disorder of iron metabolism. Under normal conditions, the body regulates iron absorption based on its needs. However, in people with Haemochromatosis, the regulatory mechanism malfunctions, leading to continuous iron absorption from the small intestine—even when the body already has enough. Excess iron cannot be excreted easily and instead gets stored in tissues and organs. Over time, this leads to oxidative stress, inflammation, and organ damage. If left untreated, iron builds up to toxic levels. Types of Haemochromatosis There are several types of the condition, with hereditary haemochromatosis being the most common: 1. Type 1 – Classic Hereditary Haemochromatosis Caused by mutations in the HFE gene, particularly C282Y and H63D Most common in individuals of Northern European ancestry Symptoms usually appear between ages 30 and 50 2. Type 2 – Juvenile Haemochromatosis Rare and more severe Symptoms appear in adolescence or early adulthood Linked to mutations in HJV or HAMP genes 3. Type 3 and 4 – Non-HFE Haemochromatosis Type 3: Linked to mutations in TFR2 gene Type 4: Also called ferroportin disease, inherited in a dominant pattern Non-genetic forms of iron overload can also occur due to repeated blood transfusions, chronic liver disease, or excessive iron supplementation, but these are not classified as true Haemochromatosis. Who Is at Risk? Risk factors for developing hereditary Haemochromatosis include: Having two copies of the defective HFE gene (homozygous) A family history of the condition Male gender – men are more likely to develop symptoms at a younger age Being of Northern European descent – particularly of Celtic ancestry Women may experience delayed symptom onset due to iron loss during menstruation and pregnancy. Early Signs and Symptoms The condition often goes undetected in its early stages. Symptoms may be subtle and non-specific, including: Chronic fatigue Joint pain, particularly in the hands Abdominal discomfort Loss of libido or erectile dysfunction Memory fog or difficulty concentrating As the condition progresses, iron begins to damage organs, leading to more specific signs such as: Liver enlargement (hepatomegaly) Diabetes mellitus Irregular heart rhythms Skin bronzing or greying (giving rise to the term “bronze diabetes”) Not everyone with Haemochromatosis develops symptoms. Some people remain asymptomatic despite having high iron levels. How Common Is It? Approximately 1 in 200 people of European ancestry have the genetic form of the condition Around 1 in 10 people carry one defective HFE gene and are considered carriers It is more prevalent than many doctors realise, but often underdiagnosed Raising awareness among general practitioners and the public is essential for early detection. Impact on Health and Lifestyle If untreated, iron accumulation can lead to: Cirrhosis of the liver Liver cancer (hepatocellular carcinoma) Heart failure Diabetes due to pancreatic damage Arthritis from joint tissue damage Pituitary dysfunction, affecting hormone levels With early diagnosis and proper management, however, individuals with Haemochromatosis can lead normal, healthy lives. Conclusion | Haemochromatosis Haemochromatosis is a common but under-recognised genetic disorder that causes iron to accumulate in the body’s organs. If left untreated, it can lead to severe and potentially life-threatening complications. However, with early identification and ongoing treatment, most people with Haemochromatosis can maintain good health and prevent long-term damage. Understanding the condition and its risk factors is the first step towards effective management. [Next: Causes of Haemochromatosis →]

Haemochromatosis Read More »

Person clutching back near liver area with digital liver overlay

Causes of Haemochromatosis

Causes of Haemochromatosis The causes of Haemochromatosis are primarily genetic, with the condition most often resulting from mutations in the HFE gene. These mutations disrupt the body’s normal regulation of iron absorption, leading to excessive iron being absorbed from the diet. The exact causes of Haemochromatosis can vary depending on the type, but the underlying problem remains the same: the body stores too much iron, and this iron builds up over time to toxic levels. In normal physiology, iron absorption is tightly controlled. The body only takes in as much iron as it needs, and unused iron is stored safely in ferritin proteins. However, in Haemochromatosis, this control mechanism fails. Instead of moderating absorption, the intestines continue to draw in iron even when the body already has an excess. 1. Genetic Mutations – The Root Cause The majority of hereditary Haemochromatosis cases are linked to mutations in the HFE gene, which regulates how much iron is absorbed in the gut. a. C282Y Mutation The most common and clinically significant Individuals with two copies (homozygous) are most likely to develop symptoms Alters a protein involved in sensing body iron levels b. H63D Mutation Milder than C282Y Often present in compound heterozygotes (one copy of each mutation) May cause iron overload when combined with other risk factors c. S65C Mutation Less common Usually does not cause disease unless combined with another HFE mutation The faulty gene prevents the liver from producing hepcidin, a hormone that controls iron absorption. Without enough hepcidin, the gut continues to absorb iron unchecked. 2. Inherited Types of Haemochromatosis Different types are classified based on the gene affected: Type Gene Involved Typical Onset Severity Type 1 HFE Adulthood Mild to moderate Type 2 HJV, HAMP Childhood/adolescence Severe Type 3 TFR2 Young adulthood Moderate Type 4 SLC40A1 (ferroportin) Variable Mild, dominant inheritance These types are inherited in an autosomal recessive or dominant pattern. Family history plays a key role in determining risk. 3. Secondary (Non-Hereditary) Iron Overload Although genetic forms account for most cases, iron overload can also result from non-genetic causes: Repeated blood transfusions, especially in conditions like thalassaemia or sickle cell anaemia Excessive iron supplementation, particularly over long periods Chronic liver disease, which affects iron metabolism Alcohol abuse, which enhances iron absorption Certain rare anemias, such as sideroblastic anaemia These causes require different management approaches and are not classified as true Haemochromatosis. 4. Role of Hepcidin Hepcidin is a hormone produced by the liver that regulates iron absorption by signalling the gut to reduce intake when iron levels are high. In people with Haemochromatosis: Hepcidin levels are abnormally low Iron transport proteins in the intestine remain active This leads to continuous absorption, even when the body is overloaded Understanding this hormonal mechanism has paved the way for future treatments targeting hepcidin regulation. 5. Environmental and Lifestyle Factors While genetic mutations are the primary cause, certain lifestyle choices can influence the severity or onset of symptoms: High dietary iron intake, especially from red meat or iron-fortified foods Excessive alcohol consumption, which damages the liver and increases iron absorption Vitamin C supplementation, which enhances iron uptake Viral infections, such as hepatitis, may worsen liver damage These factors don’t cause Haemochromatosis, but they can aggravate iron overload in genetically predisposed individuals. 6. Gender Differences in Presentation Men are more likely to show symptoms earlier due to: Lack of natural iron loss through menstruation Higher baseline iron levels Less frequent medical evaluations related to hormonal health Women may remain asymptomatic until after menopause, when menstrual blood loss ceases. Conclusion | Causes of Haemochromatosis The causes of Haemochromatosis are predominantly genetic, with mutations in the HFE gene leading to the body’s inability to regulate iron absorption. Without intervention, iron accumulates over time and can damage multiple organs. While inherited forms are most common, secondary causes such as chronic liver disease and transfusion overload also contribute to iron excess in some patients. Understanding the causes of Haemochromatosis is vital for early detection, appropriate testing, and prevention of long-term complications. [Next: Symptoms of Haemochromatosis→]

Causes of Haemochromatosis Read More »

Man clutching chest with highlighted liver to show haemochromatosis symptoms

Symptoms of Haemochromatosis

Symptoms of Haemochromatosis The symptoms of haemochromatosis are often subtle in the early stages, which can make diagnosis challenging. Many individuals live with excess iron in their body for years before experiencing any noticeable health issues. However, as iron builds up over time, the symptoms of haemochromatosis can become wide-ranging and affect multiple organs, potentially leading to serious complications if left untreated. Haemochromatosis is a genetic condition in which the body absorbs and stores too much iron from food. This excess iron is deposited in various tissues and organs, including the liver, heart, joints, pancreas, and skin. If not recognised early, it can result in irreversible damage. Early detection and treatment can prevent most long-term consequences. Common Early Symptoms The initial signs of haemochromatosis are often vague and nonspecific, which can lead to confusion with other conditions. These early symptoms include: Chronic fatigue or low energy levels Joint pain, especially in the hands and knuckles Abdominal discomfort or unexplained bloating Decreased libido or sexual dysfunction Unexplained weight loss Mood changes, including depression or irritability Because these symptoms are common in other disorders or even in healthy ageing, they are frequently overlooked or misattributed to lifestyle stress or menopause. Skin Changes One of the hallmark symptoms, though it appears in later stages, is a bronze or greyish skin tone. This occurs when iron deposits affect the skin’s pigmentation, giving it a tanned or metallic appearance—sometimes referred to as “bronze diabetes” when combined with elevated blood sugar. While this pigmentation is striking, it may go unnoticed or be mistaken for a natural tan. It usually only occurs after prolonged iron overload. Joint and Muscle Problems Haemochromatosis commonly affects the joints, particularly: The knuckles of the index and middle fingers The hips, knees, and ankles This may result in: Arthritis-like symptoms, such as stiffness, swelling, and pain Reduced mobility Early-onset osteoarthritis Joint symptoms often persist even after treatment, making them one of the more frustrating long-term effects. Liver Symptoms Since the liver is a primary site for iron storage, it is especially vulnerable. Liver-related symptoms may include: Enlarged liver (hepatomegaly) Elevated liver enzymes in blood tests Right upper abdominal pain Cirrhosis, particularly in advanced cases Increased risk of liver cancer (hepatocellular carcinoma) By the time liver symptoms appear, significant damage may have already occurred. Regular monitoring and imaging can help detect changes early. Endocrine and Metabolic Effects Iron overload disrupts the endocrine system, leading to: Diabetes mellitus, due to damage to the pancreas Hypothyroidism, resulting from pituitary or thyroid gland involvement Hypogonadism, or reduced hormone production in men and women Infertility in some individuals Men may experience testicular atrophy, loss of libido, and erectile dysfunction. Women may report irregular periods or early menopause. Cardiovascular Symptoms When excess iron affects the heart, it can result in: Irregular heart rhythms (arrhythmias) Heart failure, with symptoms such as breathlessness and fluid retention Palpitations or chest discomfort These complications are more common in untreated cases or older adults with prolonged iron accumulation. Symptoms by Gender Men are more likely to be diagnosed earlier and present with more severe symptoms. Women often experience delayed symptom onset due to iron loss during menstruation and pregnancy. However, after menopause, iron levels may rise sharply, and symptoms can appear more rapidly. Psychological and Neurological Symptoms Chronic iron overload may contribute to: Depression or mood swings Memory problems or difficulty concentrating Peripheral neuropathy, including numbness or tingling in the limbs These symptoms can worsen quality of life and may be confused with other neurological conditions or age-related decline. Symptom Timeline Timeframe Possible Symptoms Early stage Fatigue, joint pain, low libido, abdominal discomfort Middle stage Skin changes, hormonal disturbances, elevated liver enzymes Late stage Cirrhosis, diabetes, heart failure, arthritis, infertility Importance of Early Recognition The earlier haemochromatosis is identified, the better the outcome. Once damage has occurred to organs like the liver or heart, it may not be fully reversible—even if iron levels are brought under control. Recognising the symptoms of haemochromatosis early offers the best chance of avoiding complications. Conclusion | Symptoms of Haemochromatosis The symptoms of haemochromatosis are diverse and often mimic other common conditions, making early recognition difficult but essential. From fatigue and joint pain to liver disease and hormonal imbalances, the symptoms can affect nearly every part of the body. Identifying these signs and acting early can prevent severe, irreversible damage and lead to a full and healthy life with appropriate treatment. [Next: Diagnosis of Haemochromatosis →]

Symptoms of Haemochromatosis Read More »

Ultrasound scan being performed on patient's side for haemochromatosis diagnosis

Diagnosis of Haemochromatosis

Diagnosis of Haemochromatosis The diagnosis of haemochromatosis begins with a suspicion based on symptoms, family history, or abnormal blood tests. Given that early symptoms are non-specific, the diagnosis of haemochromatosis often occurs incidentally during routine checks. Confirming the condition involves a combination of blood tests, genetic testing, and sometimes imaging or a liver biopsy. Haemochromatosis is the most common inherited condition among people of Northern European background. It usually follows an autosomal recessive pattern, which means a person must inherit a faulty gene from both parents to develop the disease. Because symptoms can be mild or appear slowly over time, many people don’t know they have it. However, if the condition is not found early, extra iron can build up in the body and damage organs like the liver, heart, and pancreas. That’s why early diagnosis is so important. With regular blood tests and treatment, most people can avoid serious health problems and live full, healthy lives. Initial Blood Tests The first step in diagnosis involves measuring iron levels in the blood through two key markers: 1. Serum Ferritin Measures iron storage in the body Elevated in most people with haemochromatosis Can also be raised due to inflammation, liver disease, or cancer, so not entirely specific 2. Transferrin Saturation Indicates how much iron is bound to the transport protein transferrin A level above 45% is suggestive of iron overload Usually the most sensitive early indicator These two tests are often ordered together, and persistent abnormalities prompt further investigation. Genetic Testing If blood tests suggest iron overload, genetic testing is used to confirm the diagnosis. The test checks for mutations in the HFE gene, particularly: C282Y mutation (most common and significant) H63D mutation (less severe impact) Diagnosis is generally confirmed in individuals who are homozygous for C282Y (i.e. carry two copies of the gene mutation). Those with compound heterozygosity (one C282Y and one H63D mutation) may also show signs of iron overload, though usually less severe. Family Screening Once a diagnosis is confirmed, close family members are often advised to undergo: Genetic testing Iron studies This helps detect undiagnosed cases early and prevents long-term complications in other relatives. Additional Blood Work Other tests are used to assess the extent of organ involvement: Liver function tests (ALT, AST, GGT) Fasting glucose or HbA1c to check for diabetes Hormonal panels (testosterone, oestradiol, TSH, cortisol) Full blood count to exclude anaemia or other disorders These tests help tailor treatment and assess whether further imaging or referral is needed. Imaging Studies To assess liver damage, doctors may recommend imaging: Ultrasound: Detects liver enlargement, nodules, or fatty changes MRI with T2-weighted imaging: Measures iron concentration in the liver and heart without the need for biopsy Elastography (FibroScan): Non-invasive test to assess liver stiffness, indicating fibrosis or cirrhosis MRI is particularly valuable for monitoring patients and may also detect iron in other organs like the pancreas or heart. Liver Biopsy (In Select Cases) In some instances, a liver biopsy may be recommended: The biopsy allows for direct measurement of hepatic iron concentration and assessment of fibrosis or cirrhosis. However, this is now less commonly performed thanks to advanced imaging and genetic testing. Diagnostic Criteria Test Diagnostic Relevance Transferrin Saturation > 45% Suggests iron overload Elevated Ferritin Supports diagnosis but not specific Homozygous C282Y Mutation Confirms genetic haemochromatosis MRI or Biopsy Evaluates extent of iron deposition and organ damage Differential Diagnosis Other conditions that may mimic or influence iron levels include: Alcohol-related liver disease Chronic viral hepatitis Inflammatory conditions Metabolic syndrome Iron-loading anaemias like thalassaemia Therefore, accurate diagnosis depends on combining lab values, genetic results, and clinical history. Importance of Early Diagnosis When caught early, haemochromatosis is entirely manageable through regular blood removal (phlebotomy). Early diagnosis prevents complications such as: Liver cirrhosis Diabetes Heart failure Arthritis Delays in diagnosis may result in irreversible organ damage and a higher risk of liver cancer, particularly in men over 50. Conclusion | Diagnosis of Haemochromatosis The diagnosis of haemochromatosis usually begins with blood tests that measure iron levels in the body. If these tests show high levels of iron or ferritin, doctors may follow up with genetic testing to confirm the condition. In some cases, imaging scans or a liver biopsy may be used to check for organ damage. Thanks to greater awareness and easier access to genetic testing, more people are now being diagnosed early—often before serious problems develop. This makes a big difference because early treatment is simple but very effective. When haemochromatosis is caught in time, regular treatment can remove the extra iron and prevent long-term damage. As a result, people with the condition can stay healthy and avoid serious complications. [Next: Treatment of Haemochromatosis→]

Diagnosis of Haemochromatosis Read More »

Cartoon doctor reviewing treatment plan for haemochromatosis with DNA symbol

Treatment of Haemochromatosis

Treatment of Haemochromatosis The treatment of haemochromatosis focuses on reducing iron levels in the body to prevent organ damage and alleviate symptoms. Since iron overload is at the core of this condition, the treatment of haemochromatosis aims to remove excess iron before it can accumulate in vital organs such as the liver, heart, and pancreas. When diagnosed early and managed properly, individuals with haemochromatosis can lead full and healthy lives. Haemochromatosis is most often caused by a genetic mutation that leads to increased iron absorption from food. Without treatment, iron builds up gradually and causes a range of complications, including liver cirrhosis, diabetes, heart problems, and joint pain. Early intervention plays a vital role in preventing irreversible damage. First-Line Treatment: Phlebotomy (Venesection) Phlebotomy, also known as venesection, is the cornerstone of haemochromatosis management. This simple procedure involves regularly removing blood from the body, much like donating blood. Since each unit of blood contains about 250 mg of iron, the body compensates by using excess iron stores to make new red blood cells. Key points: Initial phase: Blood is removed once or twice weekly until iron levels are reduced to normal Maintenance phase: Blood is removed every 2–4 months to maintain target iron levels The frequency is guided by serum ferritin and transferrin saturation levels Procedure takes about 15–30 minutes and is done on an outpatient basis Phlebotomy is safe, cost-effective, and well-tolerated by most patients. Side effects are usually minor and include fatigue or dizziness immediately after the procedure. Monitoring Iron Levels Effective treatment requires regular monitoring of iron markers: Serum ferritin: Indicates total iron stores Transferrin saturation: Reflects how much iron is bound in the blood Haemoglobin: Checked to ensure the patient is not anaemic before each session The goal is to maintain serum ferritin below 50–100 µg/L without causing anaemia. Diet and Lifestyle Adjustments Although diet alone cannot treat haemochromatosis, certain changes support phlebotomy and help prevent further iron accumulation. Recommended actions: Avoid iron supplements and multivitamins with iron Limit consumption of red meat and liver, which are high in haem iron Reduce vitamin C supplements, as vitamin C enhances iron absorption Limit alcohol, especially in those with liver involvement Drink tea or coffee with meals, as these contain tannins that reduce iron absorption Balanced nutrition is essential, and extreme dietary restriction is not usually necessary. A dietitian can help tailor a plan suited to the individual’s needs. Chelation Therapy (For Rare Cases) When phlebotomy is not possible — for example, in people with anaemia or poor venous access — iron chelation therapy may be used. This involves medications that bind to excess iron and allow it to be excreted in urine or stool. Common agents: Deferasirox (oral) Deferoxamine (injected or infused) Chelation therapy is generally reserved for: Individuals with secondary iron overload (e.g. from frequent blood transfusions) Those who cannot tolerate or undergo phlebotomy Side effects can include nausea, diarrhoea, and kidney or liver function changes, so regular monitoring is required. Treating Organ-Specific Complications Long-term iron overload can damage several organs, requiring targeted management: 1. Liver: If fibrosis or cirrhosis is present, patients need hepatology support Regular ultrasound and alpha-fetoprotein tests to monitor for liver cancer Avoid alcohol to reduce further liver stress 2. Diabetes: Iron-induced damage to the pancreas may lead to type 2 diabetes Requires standard diabetic management, including diet, medication, or insulin 3. Heart: Cardiomyopathy may necessitate cardiac medication and close monitoring Severe arrhythmias may require pacemaker or defibrillator placement 4. Joints: Arthropathy due to iron deposition causes joint pain Treated with analgesics, anti-inflammatory drugs, or physical therapy Genetic Counselling and Family Screening Since hereditary haemochromatosis is genetic, family members of diagnosed individuals are often advised to undergo genetic testing and iron studies. Early detection in relatives enables preventative treatment before complications develop. Counselling helps individuals understand their carrier status, potential risks to children, and lifestyle adjustments if needed. Pregnancy and Haemochromatosis Phlebotomy is generally avoided during pregnancy unless iron levels are dangerously high. Most women with haemochromatosis have normal pregnancies, especially when the condition is well-managed before conception. Iron supplementation should be avoided unless there is proven deficiency. Long-Term Outlook With early diagnosis and consistent treatment, the outlook for haemochromatosis is excellent: Normal life expectancy when treatment begins before organ damage Improvement in symptoms such as fatigue and joint pain Reversal or stabilisation of liver and heart damage if treated early However, late diagnosis or non-compliance with therapy increases the risk of permanent complications. Conclusion | Treatment of Haemochromatosis The treatment of haemochromatosis revolves around phlebotomy, lifestyle changes, and managing iron levels to prevent organ damage. With adherence to therapy and routine monitoring, the treatment of haemochromatosis is highly effective, and most patients can expect a normal and healthy life. Early detection and continued management are key to minimising long-term complications. [Next: Complications of Haemochromatosis →]

Treatment of Haemochromatosis Read More »

Scroll to Top