Mental Matters

Health & Wellness

Woman with hand on side, showing liver illustration representing haemochromatosis complications

Complications of Haemochromatosis

Complications of Haemochromatosis The complications of haemochromatosis occur when excess iron builds up in organs and tissues, leading to damage over time. If left untreated, the complications of haemochromatosis can be severe and include liver cirrhosis, diabetes, heart disease, arthritis, and hormonal imbalances. Fortunately, early diagnosis and treatment can prevent or limit most of these outcomes. Haemochromatosis causes the body to absorb more iron than it needs. Over years, this iron accumulates silently, as the body has no natural mechanism to excrete excess iron efficiently. Once stores exceed safe levels, iron begins to deposit in vital organs, disrupting their normal function and potentially leading to life-threatening illness. 1. Liver Complications The liver is one of the first organs affected by iron overload. Common liver-related complications: Hepatomegaly (enlarged liver) Fibrosis (scarring) Cirrhosis – a significant risk factor for liver failure and liver cancer Hepatocellular carcinoma (HCC) – a rare but serious consequence of long-term iron overload Patients with cirrhosis require: Regular imaging (ultrasound) Blood tests (alpha-fetoprotein) to screen for liver cancer Avoidance of alcohol and hepatitis co-infection Liver damage may be partially reversible if treatment begins before cirrhosis develops. 2. Diabetes and Pancreatic Dysfunction Iron deposits in the pancreas disrupt insulin production, leading to type 2 diabetes mellitus. Symptoms include: Increased thirst and urination Fatigue and blurred vision Weight changes Known as “bronze diabetes” when combined with skin pigmentation changes, this complication may require insulin therapy or oral hypoglycaemic agents. Even after iron levels are controlled, pancreatic damage may persist. 3. Heart Complications Excess iron can infiltrate the heart muscle, leading to: Cardiomyopathy – weakening of the heart muscle Arrhythmias – irregular heart rhythms Heart failure – reduced pumping efficiency These complications may cause: Breathlessness Swelling in the legs Fatigue and reduced exercise tolerance Treatment includes iron removal, cardiac medications, and in some cases, implantable devices like pacemakers. 4. Joint and Musculoskeletal Problems Iron can accumulate in the joints, particularly the hands, hips, and knees. Common issues: Arthropathy (joint disease) Osteoarthritis-like symptoms Stiffness and chronic pain Reduced grip strength Unfortunately, joint symptoms often do not improve even after iron reduction, making pain management and physiotherapy important. 5. Skin Discolouration Iron deposits in the skin can cause: Grey-brown or bronze pigmentation Often noticeable on the face, neck, and forearms This gives rise to the term “bronze diabetes” when combined with glucose intolerance. Skin tone often improves with ongoing treatment. 6. Hormonal and Sexual Dysfunction Iron affects hormone-producing glands, particularly the pituitary gland, resulting in: Hypogonadism – reduced sex hormone production Erectile dysfunction or reduced libido Amenorrhoea or infertility in women Thyroid and adrenal gland dysfunction (less common) Hormone replacement therapy may be needed in these cases. 7. Fatigue and Cognitive Issues Fatigue is one of the most commonly reported symptoms, even in early stages: May persist even after iron levels normalise Possibly due to long-term inflammation or organ damage Affects quality of life, work, and mental health Some patients report: Brain fog Concentration difficulties Mood changes These issues may improve with treatment but often require holistic care. 8. Increased Risk of Certain Infections Iron is essential for bacterial growth. Excess iron may predispose individuals to infections, including: Listeria monocytogenes Yersinia enterocolitica Vibrio vulnificus These pathogens thrive in iron-rich environments, particularly in those undergoing iron chelation therapy. Awareness and appropriate hygiene precautions are important. 9. Long-Term Disability If complications are not managed in time, they may lead to: Permanent organ dysfunction Reduced mobility Dependence on medication or assistive devices Shortened life expectancy Late-stage diagnosis often involves multiple overlapping complications. Preventing Complications The best way to avoid these outcomes is through: Early detection Regular phlebotomy Routine monitoring of iron and organ function Family screening to identify at-risk relatives Even those with early organ damage may stabilise or improve with consistent management. Conclusion | Complications of Haemochromatosis The complications of haemochromatosis can affect many parts of the body. If the condition is not treated early, extra iron can build up and damage important organs like the liver, heart, pancreas, and joints. Over time, this may lead to serious problems such as liver disease, heart issues, diabetes, arthritis, and hormone imbalances. However, with early diagnosis and regular treatment—such as blood removal (phlebotomy) to lower iron levels—most of these complications can be prevented or even reversed. That’s why routine check-ups and blood tests are so important, especially for people with a family history of the condition. By learning about the possible complications, patients and healthcare providers can work together to catch problems early, plan better care, and support long-term health. [Next: Back to Overview →]
Complications of Haemochromatosis Read More »

Damaged blood vessel leaking blood, symbolising haemophilia

Haemophilia

Haemophilia Haemophilia is a rare genetic bleeding disorder in which the blood does not clot properly due to a deficiency or absence of certain clotting factors. The two main types, Haemophilia A and Haemophilia B, result from deficiencies in clotting factor VIII and IX respectively. People with this condition bleed for longer periods following injury, surgery, or even spontaneously into joints and muscles, often leading to serious complications without appropriate treatment. This lifelong condition mostly affects males, although females can be carriers and occasionally show mild symptoms. With early diagnosis, access to clotting factor replacement therapy, and ongoing medical management, individuals with Haemophilia can lead active, fulfilling lives. However, untreated or poorly managed cases may result in chronic joint damage, internal bleeding, and life-threatening haemorrhages. What Happens in Haemophilia? The blood clotting process involves a cascade of proteins known as clotting factors. When one of these is missing or malfunctioning, the chain reaction necessary for clot formation is disrupted. As a result, people with this condition experience: Prolonged bleeding after cuts or injuries Internal bleeding, especially into joints (haemarthrosis) Easy bruising Risk of spontaneous haemorrhages, even without trauma Although Haemophilia is often associated with excessive external bleeding, internal bleeding is more dangerous and frequently goes unnoticed until symptoms arise. Types of Haemophilia The condition is categorised based on which clotting factor is deficient: 1. Haemophilia A (Classic Haemophilia) Caused by a deficiency in factor VIII Most common form, accounting for around 80% of cases Severity depends on the level of factor VIII activity in the blood 2. Haemophilia B (Christmas Disease) Caused by a deficiency in factor IX Accounts for around 15–20% of cases Similar symptoms and severity grading as Haemophilia A Both types are inherited in an X-linked recessive manner, meaning the gene responsible is located on the X chromosome. Males, having one X chromosome, are more commonly affected, while females are typically carriers. Severity Classification The severity of this condition is determined by the percentage of clotting factor present: Severe: <1% activity – spontaneous bleeding common Moderate: 1–5% activity – bleeding with minor trauma Mild: 6–40% activity – bleeding usually only with surgery or major injury Severe Haemophilia often presents early in life, while mild cases may go undiagnosed until adulthood. Who Is Affected? Globally, this condition affects about: 1 in 5,000 male births for Haemophilia A 1 in 25,000 male births for Haemophilia B Although it is present at birth, the disorder may not be recognised immediately unless there’s unusual bleeding after circumcision, immunisation, or falls during toddlerhood. Signs in Children Parents may notice: Large bruises after minor bumps Swollen, warm, and painful joints (indicating internal bleeding) Prolonged bleeding after dental visits or cuts Excessive crying and refusal to move a limb after minor trauma Prompt diagnosis is critical to prevent long-term damage. Acquired Haemophilia In rare cases, people may develop acquired Haemophilia, a condition where the immune system mistakenly produces antibodies that attack clotting factors, usually factor VIII. This can occur in: Postpartum women Older adults Individuals with autoimmune diseases or cancer Acquired this condition can affect both sexes and requires urgent immunosuppressive and haemostatic therapy. Diagnosis Haemophilia is diagnosed through: Clotting tests, such as activated partial thromboplastin time (aPTT) Factor assays, which measure the specific clotting factor levels Genetic testing, especially in families with known Haemophilia Early diagnosis allows for education, lifestyle planning, and preventive care. Living with Haemophilia Though incurable, modern treatment means most patients can enjoy a normal life. Key considerations include: Avoiding contact sports or activities with high risk of injury Regular prophylactic infusions for those with severe forms Access to emergency care and clotting factor products Dental hygiene and careful planning of surgeries The creation of comprehensive care centres has improved life expectancy and quality of life dramatically in recent decades. Conclusion | Haemophilia Haemophilia is a complex but manageable bleeding disorder with potentially serious implications if untreated. With appropriate therapy, education, and support, individuals with this condition can lead healthy and active lives. Ongoing research into gene therapy and novel treatments holds promise for a future where the burden of this condition may be significantly reduced. [Next: Causes of Haemophilia →]

Haemophilia Read More »

Blood test tube marked positive for haemophilia

Causes of Haemophilia

Causes of Haemophilia The causes of Haemophilia are rooted in a genetic mutation that impairs the body’s ability to produce specific clotting factors essential for normal blood coagulation. In most cases, the causes of Haemophilia can be traced to inherited mutations passed from mother to son, but spontaneous mutations or acquired forms may also occur. Haemophilia is a classic example of a genetic bleeding disorder, where a single faulty gene disrupts a vital physiological process. This condition highlights the importance of the clotting cascade, a highly coordinated system that, when impaired, leads to dangerous and prolonged bleeding episodes. 1. Genetic Inheritance Haemophilia A and B are inherited in an X-linked recessive pattern: Males have one X and one Y chromosome. If the X chromosome carries the defective gene, they will express the disease. Females have two X chromosomes. If one X has the defective gene, they are typically carriers and usually asymptomatic, though some may show mild symptoms if the working gene is underexpressed. A carrier mother has a: 50% chance of passing the defective gene to her sons (who will have the disease) 50% chance of passing it to her daughters (who will become carriers) In families with no known history, up to one-third of cases are due to spontaneous mutations. 2. Mutations in Specific Genes Haemophilia results from mutations in: The F8 gene (on the X chromosome) for Haemophilia A The F9 gene (also on the X chromosome) for Haemophilia B These genes provide instructions for making clotting factors VIII and IX respectively. Mutations can vary: Point mutations Insertions or deletions Inversions, such as the intron 22 inversion in Haemophilia A, which is common in severe cases The nature of the mutation often influences the severity of the condition. Some mutations lead to no functional protein being produced, while others result in a less active version. 3. Carrier Status and Mild Haemophilia in Females While traditionally considered male-only, some female carriers may experience: Heavy menstrual bleeding Bleeding after dental work or surgery Easy bruising This is due to lyonisation (random X-chromosome inactivation), where the working gene may be inactive in a significant number of cells. Female carriers should be assessed for factor levels and receive appropriate counselling and management, especially during childbirth or surgical procedures. 4. Acquired Haemophilia In contrast to inherited forms, acquired Haemophilia is caused by: Autoantibodies that neutralise factor VIII (rarely factor IX) Often appears later in life, typically after age 60 Can also occur postpartum or in association with autoimmune diseases, cancer, or drug reactions Unlike inherited Haemophilia, acquired Haemophilia affects both men and women and can lead to severe bleeding despite no family history. 5. Gene Therapy and Genetic Testing Understanding the genetic basis of Haemophilia has enabled the development of: Gene therapy, where a healthy version of the clotting factor gene is inserted using viral vectors Preimplantation genetic diagnosis (PGD), which allows carrier parents to screen embryos for Haemophilia mutations Prenatal testing, including amniocentesis and chorionic villus sampling (CVS) Families with a history of Haemophilia benefit from early genetic counselling to understand inheritance risks and testing options. 6. Spontaneous Mutations Around 30% of Haemophilia cases occur with no known family history, due to new mutations in the F8 or F9 gene. These may arise: During sperm or egg formation In the embryo after conception Such mutations are unpredictable but carry the same risk of inheritance in future generations. Summary Table: Causes of Haemophilia Cause Description Inherited X-linked mutation Defective F8 or F9 gene passed from carrier mothers Spontaneous mutation New mutation with no family history Acquired antibodies Autoimmune reaction neutralising clotting factors Lyonisation in carriers Inactivation of healthy X gene in female carriers 7. Misconceptions About Causes Common myths include: Haemophilia is caused by an injury – it is not; it is genetic or autoimmune All cases are inherited – not true; many arise spontaneously Women can’t have Haemophilia – false; some women experience mild symptoms or acquired forms Public education and medical awareness are essential in dispelling these myths. Conclusion | Causes of Haemophilia The causes of haemophilia are mostly genetic. In most cases, it happens because of a mutation in the gene that controls the production of clotting factor VIII (in Haemophilia A) or factor IX (in Haemophilia B). These mutations are usually passed down through families in an X-linked recessive pattern. This means the condition mostly affects males, while females can be carriers. However, in some cases, haemophilia can also result from a new or spontaneous gene mutation, with no family history. Either way, the result is the same—blood doesn’t clot properly, which increases the risk of prolonged or internal bleeding. By understanding what causes haemophilia, doctors can diagnose the condition early, create effective treatment plans, and offer genetic counselling to help families understand the risks and options for the future. [Next: Symptoms of Haemophilia→]

Causes of Haemophilia Read More »

Man pinching nose with tissue showing a nosebleed

Symptoms of Haemophilia

Symptoms of Haemophilia The symptoms of haemophilia primarily involve excessive or prolonged bleeding, often triggered by injury or surgery, but sometimes occurring spontaneously. For many, the symptoms of haemophilia begin in early childhood, especially in more severe forms. Because the condition interferes with the body’s ability to form stable blood clots, even minor wounds can result in persistent bleeding, and internal bleeding may occur without any visible cause. Haemophilia is an inherited bleeding disorder caused by a deficiency in clotting factors—usually Factor VIII (haemophilia A) or Factor IX (haemophilia B). These proteins are essential in the cascade that enables blood to clot. When they’re missing or defective, bleeding episodes can become frequent, painful, and dangerous without proper treatment. Key Signs of Haemophilia The severity of haemophilia symptoms depends on how much clotting factor is present. Individuals are classified as having: Severe haemophilia: <1% clotting factor Moderate haemophilia: 1–5% Mild haemophilia: 5–40% Those with severe haemophilia may show symptoms early in life, often before their first birthday. Children with moderate or mild forms might not be diagnosed until a significant injury or surgery reveals abnormal bleeding. External Bleeding Symptoms Common external symptoms include: Prolonged bleeding from cuts or wounds Frequent nosebleeds that are hard to stop Excessive bleeding after tooth loss, vaccinations, or minor surgical procedures Bleeding that restarts hours after it seemed to stop Even small cuts may bleed longer than expected. In mild cases, this may be the only symptom, sometimes only noticed after surgery or dental work. Internal Bleeding Symptoms Spontaneous or trauma-induced internal bleeding is a hallmark of moderate to severe haemophilia. This includes: Joint Bleeding (Haemarthrosis) Swelling, warmth, stiffness, or pain in joints (especially knees, ankles, and elbows) Limitation of movement Often the first noticeable sign in toddlers learning to walk Repeated bleeds can cause permanent joint damage or deformities Muscle Bleeding Swelling and tightness in muscles Numbness or tingling due to pressure on nerves Pain, especially in the forearms, thighs, or calves Deep Internal Bleeding Occurs in the abdomen, pelvis, or chest Symptoms include pain, bloating, nausea, or difficulty breathing Can be life-threatening if not treated promptly Brain Bleeding (Intracranial Haemorrhage) One of the most serious complications: May occur without trauma in severe cases Signs include: Persistent headache Vomiting Confusion or lethargy Seizures or loss of consciousness Vision or speech changes This is a medical emergency that requires immediate intervention. Other Symptoms Blood in the urine (haematuria) Blood in the stool Excessive bruising, especially from minor bumps Delayed healing after surgery or injury These signs may be overlooked or misattributed in early life if bleeding episodes are not severe. Symptoms in Newborns Haemophilia is often diagnosed shortly after birth if: There is prolonged bleeding after circumcision Bleeding occurs after heel pricks or injections Large bruises appear after minor handling In families with known history, newborns may be screened at birth. Symptoms in Carriers (Females) Most people with haemophilia are male, but female carriers may experience: Heavy menstrual bleeding Easy bruising Prolonged bleeding after surgery or dental work Some carriers have factor levels low enough to be symptomatic, particularly for haemophilia A. Symptom Triggers While spontaneous bleeding occurs mostly in severe haemophilia, symptoms may also be triggered by: Trauma (even minor) Physical exertion Surgery Dental procedures Injections or blood draws Regular activity, such as walking or brushing teeth, usually doesn’t cause bleeding unless joints or gums are already vulnerable. Conclusion | Symptoms of Haemophilia The symptoms of haemophilia vary widely depending on severity, but the most consistent features include prolonged bleeding, joint pain, and bruising. In severe cases, spontaneous bleeding into joints and internal organs can lead to disability or life-threatening events. Recognising the symptoms of haemophilia early is vital to ensure proper management and prevent long-term complications through timely treatment and care. [Next: Diagnosis of Haemophilia →]

Symptoms of Haemophilia Read More »

Microscope slide being prepared for blood analysis

Diagnosis of Haemophilia

Diagnosis of Haemophilia The diagnosis of haemophilia relies on specialised blood tests that measure clotting factor activity, supported by a detailed personal and family history. Because the diagnosis of haemophilia can be life-changing, especially for children and families, it is essential that testing is accurate, timely, and followed by appropriate counselling. Haemophilia is often suspected when a person experiences unusual or prolonged bleeding after minor injuries or procedures. In families with a known history, infants may be screened shortly after birth. Diagnosing the condition early allows treatment to start before major complications arise. Initial Clinical Suspicion Doctors may suspect haemophilia if a patient presents with: Recurrent joint or muscle bleeds Frequent bruising with no clear cause Prolonged bleeding after dental work, circumcision, or vaccinations Family history of bleeding disorders In severe cases, these symptoms often begin in infancy or early childhood. In milder forms, the condition may not become apparent until surgery or trauma exposes abnormal bleeding. Laboratory Tests for Diagnosis The primary test used in diagnosing haemophilia is a clotting factor assay, which measures how much of a specific clotting factor is present in the blood. Key Tests: Activated Partial Thromboplastin Time (aPTT) Measures the time it takes for blood to clot Prolonged in haemophilia A or B May be normal in mild cases Prothrombin Time (PT) Usually normal in haemophilia Helps rule out other bleeding disorders Factor VIII Assay Used to diagnose haemophilia A Low or absent levels confirm diagnosis Factor IX Assay Used to diagnose haemophilia B (Christmas disease) Genetic Testing Identifies specific gene mutations Helps confirm diagnosis in ambiguous cases Useful for prenatal testing or determining carrier status in females These tests are conducted in specialised laboratories, as accuracy is critical. Diagnosing Severity Based on clotting factor levels, haemophilia is classified as: Severe: <1% activity Moderate: 1–5% activity Mild: 5–40% activity Knowing the severity guides treatment decisions and monitoring frequency. Diagnosis in Newborns In families with a history of haemophilia, diagnosis may occur: Immediately after birth, via umbilical cord blood sampling If there’s bleeding after circumcision or heel-prick tests If bruises develop without trauma In boys born to known carrier mothers, early testing is standard. In cases with no known family history, diagnosis is often delayed until symptoms appear. Prenatal and Carrier Testing Prenatal Diagnosis: Performed via chorionic villus sampling or amniocentesis Allows early identification of affected foetuses in at-risk pregnancies Carries a small risk of bleeding or miscarriage Carrier Testing: Identifies females who carry the defective gene Helps in family planning, genetic counselling, and risk assessment In some cases, carriers have low factor levels and may need treatment Differential Diagnosis Several other conditions must be ruled out before confirming haemophilia: Von Willebrand disease Platelet function disorders Liver disease, which affects clotting factor production Vitamin K deficiency These conditions require different management approaches, so precise diagnosis is essential. Role of Haemophilia Treatment Centres Specialised haemophilia treatment centres (HTCs) offer: Comprehensive diagnostic services Genetic counselling Long-term care and education Access to new treatments or clinical trials In many countries, HTCs are the standard of care for ongoing monitoring and support. Importance of Early Diagnosis Early diagnosis is critical for: Preventing joint damage through prophylactic treatment Avoiding complications from surgery or trauma Empowering families with knowledge and support Ensuring safe vaccinations and medical interventions With modern diagnostic tools, haemophilia can often be identified within weeks of birth. Conclusion | Diagnosis of Haemophilia The diagnosis of haemophilia is made through clinical evaluation and laboratory testing of clotting factor levels. Early and accurate diagnosis of haemophilia is essential to begin timely treatment, prevent complications, and provide the individual and their family with appropriate support. With proper diagnosis and monitoring, people with haemophilia can lead active and fulfilling lives. [Next: Treatment of Haemophilia→]

Diagnosis of Haemophilia Read More »

Illustration of haemophilia treatment with syringe and blood samples.

Treatment of Haemophilia

Treatment of Haemophilia The treatment of haemophilia focuses on replacing the missing clotting factor to stop or prevent bleeding. In the past, treatment was mainly given after a bleeding episode started. However, thanks to modern advances, care has become much more proactive. Today, many people receive regular infusions to keep clotting levels stable and avoid bleeding altogether. Newer treatments last longer, are easier to use, and carry fewer risks. In some cases, gene therapy may even help the body make its own clotting factor. With these improvements, people with haemophilia can live full, active lives. Although it remains a lifelong condition, the right treatment plan can greatly reduce complications and make daily life much easier to manage. Haemophilia is a genetic condition that affects the blood’s ability to clot properly. It happens when the body doesn’t make enough clotting factor VIII (in Haemophilia A) or factor IX (in Haemophilia B). These clotting factors are proteins that help stop bleeding. As a result, even small cuts or injuries can cause bleeding that lasts much longer than normal. In more serious cases, bleeding can happen inside the body—especially in the joints, muscles, or internal organs—even without an obvious injury. This makes early diagnosis and proper treatment very important for staying healthy and active. 1. Factor Replacement Therapy The cornerstone of treatment is clotting factor replacement, which can be administered as: On-demand therapy: Given during or immediately after a bleeding episode Prophylactic therapy: Given regularly to prevent bleeding, often 2–3 times per week a. Plasma-Derived Factors These are extracted from donated human plasma and processed to remove pathogens. Though effective, they are being replaced in many countries by recombinant products due to concerns about blood-borne diseases. b. Recombinant Clotting Factors These are manufactured using genetic engineering, making them safer and more consistent. They come in: Standard half-life products, which require frequent dosing Extended half-life (EHL) products, which last longer in the bloodstream, reducing infusion frequency Most children and young adults with severe haemophilia are placed on prophylactic recombinant therapy early in life to prevent joint damage. 2. Non-Factor Replacement Therapies In recent years, newer treatments have been developed that don’t involve traditional factor replacement. These include: a. Emicizumab (for Haemophilia A) A bispecific monoclonal antibody Mimics the function of factor VIII Given subcutaneously (under the skin) weekly or monthly Effective even in patients with inhibitors Emicizumab is transforming care by providing a less invasive, more convenient option, especially in children and those with needle phobia. b. Other Novel Agents Fitusiran and concizumab are being studied to rebalance clotting mechanisms by targeting anticoagulant pathways These therapies represent the future of haemophilia treatment, especially in patients who develop resistance to clotting factor products 3. Treatment of Bleeds If bleeding occurs, immediate treatment with clotting factor is essential. Common bleeding scenarios include: Joint bleeds (most common) Muscle haematomas Mouth and gum bleeds Post-surgical or dental procedures Early intervention reduces pain and long-term joint damage. In serious cases, hospitalisation and imaging may be required to assess internal bleeding. 4. Managing Inhibitors Some people develop inhibitors—antibodies that neutralise the effectiveness of infused clotting factor. Treatment options include: Bypassing agents such as activated prothrombin complex concentrate (aPCC) or recombinant factor VIIa Immune tolerance induction (ITI): Regular high-dose factor therapy to “train” the immune system to stop producing inhibitors Inhibitors are a major complication and require specialist haematology care. 5. Gene Therapy One of the most exciting advancements in the treatment of Haemophilia is gene therapy. Involves delivering a working copy of the defective gene using a viral vector Aims to achieve long-term or even permanent production of clotting factor Clinical trials have shown promising results, especially for Haemophilia B Gene therapy is not yet widely available, but it holds great potential for transforming how haemophilia is managed in the future. 6. Comprehensive Haemophilia Care Effective treatment extends beyond medication. Comprehensive care includes: Physiotherapy, especially for joint health Dental care, as bleeding can occur easily in the gums Psychological support, for coping with the emotional impact of chronic illness Social work, to support access to treatment, especially in lower-income regions Many countries have haemophilia treatment centres (HTCs) that offer multidisciplinary care under one roof. 7. Home Therapy and Self-Management Most patients in high-resource settings are trained to administer their own treatment at home, especially for prophylaxis. Reduces emergency visits Encourages independence Improves quality of life Mobile apps and telehealth tools now support treatment logging, reminders, and remote monitoring by specialists. 8. Special Considerations a. Surgery and Dental Procedures Require careful planning and clotting factor coverage Local anaesthesia may be preferred Tranexamic acid or antifibrinolytics are often used adjunctively b. Sports and Physical Activity Generally encouraged, especially low-impact sports like swimming and cycling Protective gear and awareness are essential Exercise improves joint strength and reduces bleeding risk Conclusion | Treatment of Haemophilia The treatment of haemophilia has come a long way in recent years. In the past, most care focused on replacing the missing clotting factor through regular injections. Today, however, there are many more options. For example, newer therapies last longer, require fewer doses, and carry fewer risks. In addition, gene therapy now offers a possible long-term solution by helping the body produce its own clotting factor. Because of these advances, people with haemophilia now have more choices than ever before. With the right care, they can prevent most bleeding episodes, stay active, and avoid serious complications. Most importantly, access to a skilled medical team and regular follow-ups helps them stay healthy. As treatment continues to improve, living with haemophilia becomes easier. Many people are now able to lead full, independent lives with little interruption to work, school, or daily activities. [Next: Complications of Haemophilia →]

Treatment of Haemophilia Read More »

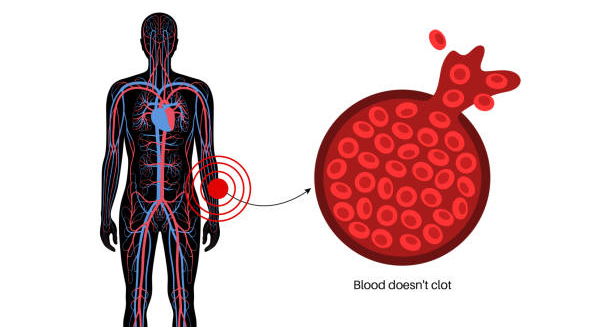
Diagram showing blood that doesn’t clot and potential haemophilia complications.

Complications of Haemophilia

Complications of Haemophilia The complications of Haemophilia range from spontaneous bleeding and joint damage to more serious problems like inhibitor development and life-threatening internal haemorrhages. Although modern treatments have significantly reduced the burden, the complications of Haemophilia remain a concern, especially in individuals who do not have access to regular therapy. Haemophilia is a chronic disorder that requires lifelong management. Without consistent treatment and monitoring, bleeding can occur unpredictably, leading to physical disability, emotional distress, and reduced quality of life. 1. Joint Damage (Haemophilic Arthropathy) One of the most common long-term complications is chronic joint damage, resulting from repeated bleeding into joints (haemarthrosis). Key joints affected: Knees Ankles Elbows Each bleed causes inflammation and cartilage damage, leading to: Pain and swelling Reduced mobility Joint deformity Chronic arthritis Without prophylactic treatment, joint disease may begin in early childhood and worsen with age. 2. Muscle Bleeds and Haematomas Bleeding into muscles can cause: Swelling and bruising Pressure on nerves, leading to numbness or tingling Compartment syndrome, a rare but serious condition where pressure builds up inside a muscle group, cutting off blood supply These bleeds may mimic trauma injuries and require urgent assessment and treatment. 3. Internal Bleeding Spontaneous bleeding can occur inside the: Abdomen or pelvis Brain (intracranial haemorrhage) Throat or neck Signs of serious internal bleeding include: Sudden, severe headache Vomiting, confusion, or loss of consciousness Difficulty breathing or swallowing Sudden abdominal pain or distension These are medical emergencies requiring hospital care and high-dose factor replacement. 4. Inhibitor Development Some individuals develop inhibitors—antibodies that render standard clotting factor therapy ineffective. This complication leads to: Uncontrolled bleeding, even with treatment More frequent joint and muscle bleeds Need for complex and expensive therapies like bypassing agents Inhibitor development is more common in Haemophilia A and often appears during early childhood. 5. Blood-Borne Infections (Historic Risk) Before the 1990s, many people with haemophilia contracted: Hepatitis B or C HIV/AIDS This was due to contaminated plasma-derived clotting factors. Today, all blood products are rigorously screened, and recombinant factor products carry no infection risk. However, some older individuals still live with the consequences of past infections, such as: Chronic liver disease Cirrhosis Liver cancer 6. Chronic Pain and Reduced Mobility Joint and muscle damage from repeated bleeds may result in: Daily chronic pain Limited range of motion Reliance on mobility aids (e.g., canes, wheelchairs) Social isolation or depression Pain management often includes physiotherapy, exercise, and medication. Mental health support is equally important for overall wellbeing. 7. Psychological and Social Impact Living with a chronic condition like haemophilia can take a toll on mental health. Common challenges include: Anxiety around bleeding episodes Depression due to physical limitations Stigma or isolation, especially in school or work environments Employment and insurance barriers Support groups, counselling, and educational outreach can help individuals and families cope more effectively. 8. Surgical Risks People with haemophilia face added risks during any surgical or dental procedure due to bleeding. Without proper clotting factor cover, surgery can lead to: Excessive bleeding Delayed healing Post-operative complications Elective procedures require coordinated care between haematology and surgical teams, often with multiple days of factor replacement and monitoring. 9. Reduced Quality of Life in Resource-Limited Settings In many parts of the world, access to clotting factor therapy is limited or non-existent. As a result: Children die young from uncontrolled bleeding Survivors experience severe disability Educational and employment opportunities are lost Global efforts through organisations like the World Federation of Hemophilia (WFH) aim to improve access and reduce these disparities. 10. Financial Burden Haemophilia treatment is expensive. In high-income countries, annual costs for prophylactic factor therapy can exceed $200,000 per person. For families and healthcare systems, this financial burden can be overwhelming, especially in the absence of: Insurance cover Government funding Access to affordable generic products Conclusion | Complications of Haemophilia The complications of Haemophilia can be serious, particularly in those who do not receive early diagnosis or consistent treatment. From joint damage and chronic pain to life-threatening bleeds and psychosocial challenges, the complications of Haemophilia affect nearly every aspect of life. With improved therapies, supportive care, and global advocacy, many of these complications can be prevented or effectively managed, offering hope for a healthier future. [Next: Back to Overview →]

Complications of Haemophilia Read More »

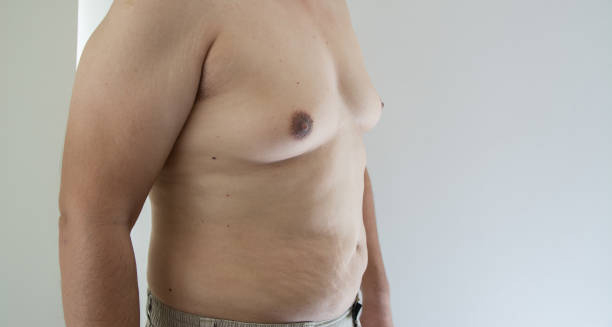
Male torso showing signs of gynaecomastia

Gynaecomastia

Gynaecomastia Gynaecomastia is the benign enlargement of breast tissue in males, often resulting in physical changes that can be emotionally distressing. While gynaecomastia is not usually harmful to physical health, it can lead to psychological discomfort, body image concerns, and social embarrassment. It commonly affects boys during puberty and older men, though it may occur at any age due to hormonal changes, medications, or underlying medical conditions. This condition is characterised by an increase in glandular breast tissue, rather than fat, and it typically presents as a firm or rubbery mass beneath the nipple. Gynaecomastia differs from pseudogynaecomastia, which is caused by fat accumulation rather than glandular growth. Understanding the underlying causes, clinical features, and treatment options can help affected individuals manage their symptoms and seek appropriate care. How Common Is Gynaecomastia? Gynaecomastia is relatively common: Affects up to 70% of adolescent boys at some stage during puberty Occurs in 35–65% of men over 50 Seen in newborns, often due to maternal oestrogen exposure May be unilateral (one side) or bilateral (both sides) In many cases, especially in teenagers, the condition resolves spontaneously within months or a few years without intervention. Signs and Symptoms The primary symptom of gynaecomastia is breast enlargement, which may be accompanied by: Tenderness or sensitivity in the affected area A rubbery or firm mass under the nipple Swelling that feels symmetrical and centred around the areola Occasionally, itchiness or slight pain, though severe pain is uncommon The condition is usually not dangerous, but significant growth or persistent discomfort should prompt medical evaluation to rule out other causes, including male breast cancer (which is rare but possible). Hormonal Imbalance and Gynaecomastia The condition is primarily linked to an imbalance between oestrogen and testosterone: Oestrogen, though typically considered a female hormone, is present in males in small amounts If oestrogen levels increase or testosterone levels fall, breast tissue may enlarge This imbalance can occur naturally (e.g. during puberty or ageing), or be triggered by medications, disease, or lifestyle factors The oestrogen-testosterone ratio is a crucial factor in maintaining typical male breast tissue size. Disruption of this ratio is central to the development of gynaecomastia. Risk Groups While any male can develop gynaecomastia, certain groups are more prone: Teenage boys going through puberty Men over 50, particularly those with age-related hormone decline Bodybuilders using anabolic steroids or hormone supplements Men with chronic conditions, such as liver disease or kidney failure Patients on specific medications, including anti-androgens, some antidepressants, anti-anxiety medications, and chemotherapy agents Men with a family history of hormonal disorders or testicular abnormalities may also face an increased risk. Emotional and Psychological Impact Although gynaecomastia is not life-threatening, it can profoundly affect mental and emotional wellbeing: Embarrassment in changing rooms or when shirtless Social withdrawal, particularly among teenagers Reduced self-esteem or body image confidence Anxiety or depression, especially if the condition is persistent For many individuals, the emotional burden of gynaecomastia outweighs the physical symptoms. Psychological support or counselling can be a helpful part of treatment, particularly in long-standing or severe cases. Differentiating Gynaecomastia from Other Conditions A key step in clinical evaluation is distinguishing gynaecomastia from: Pseudogynaecomastia – breast enlargement due to fat deposits, common in obese individuals Breast cancer – a hard, irregular, and often painless lump, more likely to be unilateral and not centred behind the nipple Mastitis or abscess – marked by inflammation, redness, and warmth, which may indicate infection A thorough history, physical examination, and occasionally imaging or blood tests are used to confirm the diagnosis and exclude serious conditions. When to See a Doctor Medical evaluation is recommended when: The breast enlargement is painful or progressive There is nipple discharge, particularly if bloody The enlargement is unilateral or firm There are signs of hormonal disorders (e.g. decreased libido, erectile dysfunction) The person is on medication known to cause gynaecomastia Early assessment helps guide management and rule out underlying disease. Conclusion | Gynaecomastia Gynaecomastia is a common, often benign condition marked by male breast enlargement due to hormonal imbalance. While not usually a health threat, gynaecomastia can cause considerable emotional and social distress. Recognising the signs, understanding the hormonal mechanisms involved, and knowing when to seek medical help are all important steps in addressing this condition. With the right support and treatment, most individuals can manage or resolve the symptoms effectively. [Next: Causes of Gynaecomastia →]

Gynaecomastia Read More »

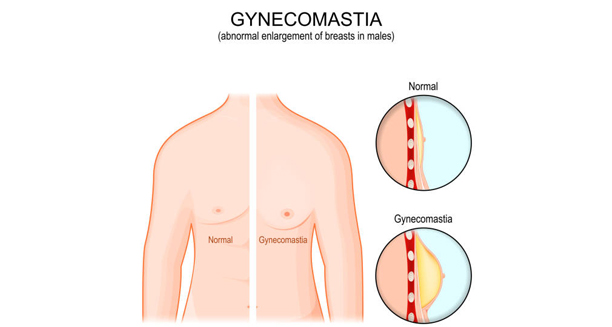
Medical illustration comparing normal male chest with gynaecomastia

Causes of Gynaecomastia

Causes of Gynaecomastia The causes of gynaecomastia are rooted in a hormonal imbalance, typically involving an increase in oestrogen or a decrease in testosterone. Although it may seem alarming, the causes of gynaecomastia are often benign and treatable, especially when identified early. Gynaecomastia, the enlargement of breast tissue in males, can affect newborns, adolescents, and adults, and can arise from a range of natural, medical, or environmental factors. Understanding what causes gynaecomastia is key to diagnosing and treating it properly. The condition happens when hormone levels—especially the balance between estrogen and testosterone—change. These changes may be due to natural aging, certain medications, or underlying health problems. In some cases, lifestyle factors or substance use can also play a role. Importantly, gynaecomastia is not the same as extra fat in the chest, which is called pseudogynaecomastia. However, both conditions can look similar, and sometimes the causes overlap. That’s why it’s important for doctors to look at the whole picture—including hormone levels, medical history, and overall health—when making a diagnosis. By identifying the root cause, healthcare providers can offer the most effective and personalised care. 1. Hormonal Imbalance The human body requires a delicate balance between oestrogen and testosterone. Men naturally produce oestrogen in small amounts, but when the balance tips in favour of oestrogen, breast tissue can develop. Common reasons for hormonal imbalance include: Puberty: Hormonal fluctuations during adolescence are the most frequent cause. Up to 70% of boys experience temporary gynaecomastia, which usually resolves within 6–24 months. Ageing: As men age, testosterone levels decline and fat tissue increases. Fat can convert testosterone into oestrogen via an enzyme called aromatase, leading to breast tissue growth. Obesity: Being overweight raises oestrogen levels and contributes to both true gynaecomastia and pseudogynaecomastia. In most cases, the hormonal imbalance is transient and not linked to serious health issues. However, persistent or painful enlargement should always be evaluated. 2. Medications Several medications are known to alter hormone levels or mimic oestrogen, which can lead to breast tissue growth in men. These include: a. Anti-androgens Used to treat prostate cancer, enlarged prostate, and some skin conditions, drugs like: Flutamide Spironolactone Finasteridecan block testosterone and increase the relative impact of oestrogen. b. Antipsychotics and Antidepressants Drugs such as risperidone, haloperidol, and tricyclic antidepressants may raise prolactin levels, which can stimulate breast tissue growth. c. Cardiovascular drugs Calcium channel blockers, digoxin, and ACE inhibitors have been implicated in some cases, though the mechanism is not always clear. d. Chemotherapy Cancer treatments can disrupt hormone regulation, especially when used in combination with hormone-blocking drugs. e. Ulcer and acid-reflux medications Cimetidine and ranitidine (now less commonly used) have weak oestrogenic effects and can contribute to gynaecomastia with long-term use. Always inform your healthcare provider about all medications and supplements, as switching drugs may help reverse the symptoms. 3. Substance Use Certain substances, legal and illicit, are associated with hormone disruption and breast enlargement: Alcohol: Chronic use affects liver function, reducing the liver’s ability to clear oestrogen from the body. Cannabis: Studies have linked long-term use to reduced testosterone levels and possible oestrogenic effects. Anabolic steroids: Bodybuilders and athletes who use synthetic testosterone may develop gynaecomastia during the “off-cycle” period, when natural testosterone drops but oestrogen levels remain elevated. Heroin and amphetamines: These may suppress testosterone production through central nervous system effects. Avoiding or discontinuing these substances often leads to improvement, although long-standing gynaecomastia may persist without surgical intervention. 4. Health Conditions Several medical conditions can disturb hormonal balance, leading to breast tissue development in males: a. Liver disease Chronic liver disorders, including cirrhosis, impair oestrogen breakdown and increase its levels in the bloodstream. Conditions such as non-alcoholic fatty liver disease also contribute indirectly via obesity. b. Kidney failure Long-term dialysis can cause hormonal shifts, particularly with reduced testosterone production and elevated prolactin. c. Hyperthyroidism An overactive thyroid gland increases sex hormone-binding globulin (SHBG), which binds testosterone and leaves more unbound oestrogen active in the body. d. Pituitary tumours Some tumours produce excess prolactin, a hormone that stimulates breast tissue development in both sexes. e. Hypogonadism Primary testicular failure, whether genetic (e.g., Klinefelter syndrome) or acquired, results in reduced testosterone and higher oestrogen effects. Damage from mumps, injury, or radiation can also lead to low testosterone and subsequent gynaecomastia. In all cases, treating the underlying health issue is crucial for resolving the breast enlargement and preventing recurrence. 5. Tumours and Hormone-Secreting Growths Although rare, tumours that secrete hormones may directly increase oestrogen or decrease testosterone: Testicular tumours (e.g., Sertoli or Leydig cell tumours) Adrenal gland tumours HCG-producing tumours (commonly seen in lung, liver, or stomach cancers) These require urgent assessment and imaging studies. A testicular ultrasound or abdominal scan may be ordered if a mass is suspected. 6. Herbal Products and Supplements Some plant-based products contain phytoestrogens, compounds that mimic oestrogen in the body. Common examples include: Tea tree oil and lavender oil (topical use has been linked to breast growth in boys) Soy-based products (usually in high, concentrated amounts) Herbal supplements, such as those used for body enhancement or testosterone boosting, may contain undeclared hormone-active ingredients The risk is higher when products are used frequently or over long periods. 7. Idiopathic Gynaecomastia In some cases, no clear cause is found — this is termed idiopathic gynaecomastia. While frustrating, this form is often harmless and may stabilise or regress over time. Nonetheless, ongoing monitoring and exclusion of serious causes are essential, especially in adult males or post-pubertal boys with persistent symptoms. Conclusion | Causes of Gynaecomastia The causes of gynaecomastia come from many different sources. Often, it begins with natural changes in hormone levels—especially during puberty or older age. However, other factors can also play a role. For example, certain medications, such as those for high blood pressure or ulcers, may lead to breast tissue growth. In addition, long-term health problems like liver or kidney disease can affect hormone balance. Substance use, including alcohol, anabolic steroids, or marijuana, can also increase the risk. Fortunately, in most cases, gynaecomastia goes away once

Causes of Gynaecomastia Read More »

Man covering chest due to breast swelling or tenderness

Symptoms of Gynaecomastia

Symptoms of Gynaecomastia The symptoms of gynaecomastia can vary from mild breast enlargement to significant swelling and tenderness, affecting one or both breasts. While the physical appearance is the most noticeable feature, the symptoms of gynaecomastia can also include pain, emotional discomfort, and psychological distress—especially in adolescents and adult men. Gynaecomastia is defined as the benign enlargement of male breast tissue caused by hormonal imbalances, typically involving increased oestrogen activity or decreased androgens. It can affect newborns, adolescents, and older men, and its symptoms may range from barely perceptible to significantly distressing, both physically and emotionally. Common Physical Symptoms The physical signs of gynaecomastia are usually the most obvious, and often include: Firm or rubbery tissue underneath the nipple area Symmetrical or asymmetrical breast enlargement (one-sided or both) Tenderness or mild pain in the affected breast A disc-like mound of tissue beneath the areola (the dark area around the nipple) In some cases, visible swelling that resembles female breast development Unlike fat tissue associated with obesity, the glandular tissue in gynaecomastia is firmer and more nodular to the touch. The tissue is usually located centrally under the nipple and does not extend broadly like adipose tissue in pseudogynaecomastia. Unilateral vs Bilateral Symptoms Unilateral gynaecomastia (one breast only) occurs in about one-third of cases Bilateral gynaecomastia (both breasts) is more common and may occur evenly or unevenly Asymmetry often causes additional anxiety, as men may fear cancer or another underlying disease While breast cancer in men is rare, any lump that is hard, fixed, or associated with nipple discharge warrants immediate medical evaluation. Pain and Tenderness Pain is not always present, but when it occurs, it may include: A dull ache or sensitivity Discomfort when pressure is applied, such as when lying on the chest or wearing tight clothing Tender nipples, which may be irritated by contact with fabrics Pain is typically more noticeable during the growth phase of gynaecomastia, when hormonal fluctuations are most active. Emotional and Psychological Effects The symptoms of gynaecomastia go beyond the physical. Many men and boys experience: Body image concerns Shame or embarrassment, particularly during social or intimate situations Avoidance of activities like swimming or changing in public locker rooms Low self-esteem, especially during adolescence Depression or anxiety, in severe or long-standing cases In teenagers, these psychological symptoms may significantly impact quality of life, school participation, and peer relationships. Nipple Changes Although rare, some men notice: Nipple protrusion or change in shape Increased pigmentation or sensitivity In isolated cases, clear or milky discharge, which should be evaluated further Any bloody or spontaneous nipple discharge must be promptly assessed to rule out malignancy. Distinguishing Features of True Gynaecomastia To confirm that symptoms are consistent with true gynaecomastia and not fat-related enlargement (pseudogynaecomastia), key signs include: A firm mass under the nipple Tissue that does not change significantly with weight loss No signs of infection or inflammation In contrast, pseudogynaecomastia (caused by excess body fat) tends to be soft, evenly distributed, and responsive to changes in diet and exercise. Progression and Duration of Symptoms Gynaecomastia can be: Transient, especially in newborns and teenagers Persistent, in cases related to medications, liver disease, or ageing Progressive, if underlying causes are not addressed Symptoms often resolve spontaneously within 6 to 24 months in adolescents but may persist into adulthood if not evaluated. When to Seek Medical Advice It is important to consult a healthcare provider if: The swelling is rapid or painful There is nipple discharge or skin dimpling Only one side is affected Symptoms cause emotional distress There is a family history of breast cancer or testicular disease These features help differentiate benign gynaecomastia from more serious conditions such as tumours or hormonal disorders. Conclusion | Symptoms of Gynaecomastia The symptoms of gynaecomastia include not only visible breast enlargement but also tenderness, nipple sensitivity, and psychological discomfort. Understanding the full range of symptoms of gynaecomastia is essential for early recognition, appropriate diagnosis, and compassionate management. For many men, timely reassurance and evaluation can ease physical discomfort and restore confidence. [Next: Diagnosis of Gynaecomastia →]

Symptoms of Gynaecomastia Read More »

Scroll to Top