Mental Matters

Author name: admin

Pregnant woman undergoing prenatal check-up for Group B Strep screening

Diagnosis of Group B Strep

Diagnosis of Group B Strep Doctors diagnose Group B Streptococcus (GBS) using several clinical and laboratory methods, depending on whether they’re checking for harmless colonisation or an active infection. In pregnant women, routine screening identifies colonisation. In newborns and adults, rapid testing of blood, urine, or spinal fluid helps doctors confirm infection quickly and begin treatment. Even though GBS is a common bacterium, doctors must clearly tell the difference between normal colonisation and serious infection. In high-risk groups—like newborns, pregnant women, and adults with weakened immune systems—early and accurate diagnosis can help prevent complications and save lives. 1. Diagnosis in Pregnant Women (Screening for Colonisation) Doctors usually screen pregnant women for GBS between 35 and 37 weeks of pregnancy. The steps include: A positive result shows colonisation, not infection. In this case, doctors give antibiotics during labour to protect the baby from infection during birth. In some countries, doctors use a risk-based approach instead of routine screening. They give antibiotics during labour if any of these apply: 2. Diagnosis in Newborns When a newborn shows signs of GBS infection, time is critical. Doctors perform several tests to confirm the diagnosis: a. Blood Cultures b. Cerebrospinal Fluid (CSF) Testing c. Chest X-Ray d. Complete Blood Count (CBC) and CRP Since infections in newborns can progress quickly, doctors usually start treatment before results are ready, especially if symptoms are severe. 3. Diagnosis in Adults When adults show signs of GBS infection, doctors choose tests based on symptoms and the part of the body affected: a. Urine Culture b. Blood Cultures c. Wound or Tissue Cultures d. Joint Fluid or Bone Testing e. Chest Imaging Doctors combine these tests with a physical exam and patient history to make a clear diagnosis. [Next: Treatment of Group B Strep→]

Diagnosis of Group B Strep Read More »

Pregnant woman holding medication for Group B Strep treatment

Treatment of Group B Strep

Treatment of Group B Strep The treatment of Group B Strep focuses on eradicating the infection with antibiotics and preventing transmission in high-risk populations. In pregnant women, the treatment of Group B Strep is primarily aimed at reducing the risk of neonatal infection. In newborns and vulnerable adults, immediate antibiotic therapy is vital to avoid life-threatening complications such as sepsis and meningitis. Group B Streptococcus (GBS) is a bacterium commonly carried without symptoms, but when it causes infection, prompt medical intervention becomes essential. Treatment protocols vary depending on whether the individual is colonised, symptomatic, or suffering from an invasive disease. Treatment During Pregnancy and Labour 1. Intrapartum Antibiotic Prophylaxis (IAP) Pregnant women who test positive for GBS colonisation are not treated during pregnancy, but they are given intravenous antibiotics during labour to prevent transmission to the baby. Penicillin G is the drug of choice Ampicillin is an acceptable alternative Cefazolin, clindamycin, or vancomycin may be used for those allergic to penicillin The antibiotic should be administered at least four hours before delivery to ensure it has sufficient time to reduce bacterial levels in the birth canal. Intrapartum antibiotics are recommended if: The woman tested positive for GBS at 35–37 weeks She previously had a baby with GBS disease GBS was found in her urine during the current pregnancy She presents in labour before screening results are available and has risk factors (fever, prolonged rupture of membranes) Prophylaxis is not needed in cases of planned caesarean delivery before labour begins and before membranes rupture. 2. Treating GBS-Related Infections in Pregnancy Doctors give oral or intravenous antibiotics during pregnancy if Group B Streptococcus (GBS) causes urinary tract infections or chorioamnionitis. These infections may increase the risk of preterm birth and require close monitoring. Treatment in Newborns Babies suspected of having GBS disease—whether early- or late-onset—require immediate hospital admission and intravenous antibiotics. Doctors typically begin treatment before confirming test results because the infection can progress rapidly First-Line Treatment: Benzylpenicillin (or ampicillin) Gentamicin (an aminoglycoside for broad coverage) Treatment duration depends on the severity and type of infection: Sepsis: 7–10 days Pneumonia: 7–10 days Meningitis: 14–21 days Monitoring and Supportive Care In addition to antibiotics, supportive care may include: Oxygen or ventilation for breathing difficulties Intravenous fluids for hydration and stabilising blood pressure Monitoring of heart rate, breathing, and temperature Nutritional support if feeding is poor In neonatal intensive care units (NICUs), continuous observation ensures early detection of treatment response or deterioration. Treatment in Non-Pregnant Adults While most adults carry GBS without symptoms, immunocompromised individuals, the elderly, and those with underlying health issues may develop serious infections. Treatment of GBS Infections in Adults: Penicillin G or amoxicillin is usually first-line Doctors typically require hospitalisation to administer intravenous antibiotics and monitor the patient. For penicillin-allergic patients, vancomycin is an effective alternative Treatment length varies depending on the infection site: Urinary tract infections: 5–7 days Skin and soft tissue infections: 10–14 days Sepsis: 10–14 days Osteomyelitis or joint infections: 4–6 weeks Meningitis: 14–21 days Doctors typically require hospitalisation to administer intravenous antibiotics and monitor the patient. Antibiotic Resistance and Challenges Group B Strep remains largely susceptible to beta-lactam antibiotics, including penicillin. However: Doctors recommend resistance testing if the patient cannot use penicillin. Doctors recommend resistance testing if the patient cannot use penicillin Misuse or overuse of antibiotics may contribute to resistance over time Maintaining prudent antibiotic practices is essential to preserve treatment effectiveness. Emerging Therapies and Vaccine Development Currently, no licensed vaccine exists for GBS. However, research is underway to develop maternal vaccines that: Stimulate antibody production during pregnancy Pass protection to the baby through the placenta Reduce reliance on intrapartum antibiotics Such vaccines may prove especially valuable in low-resource settings without access to routine screening. Conclusion | Treatment of Group B Strep The treatment of Group B Strep varies based on the patient’s risk and presentation. In pregnant women, intrapartum antibiotics significantly reduce neonatal infection risk. Doctors rely on intravenous antibiotics and supportive care to treat newborns and adults with invasive disease. [Next: Complications of Group B Strep →]

Treatment of Group B Strep Read More »

Medical illustration showing brain infection as a complication of Group B Strep

Complications of Group B Strep

Complications of Group B Strep The complications of Group B Strep can be severe, particularly in newly borns and individuals with weak immune systems. While many adults carry the bacterium without issue, when infection occurs, the complications of Group B Strep may include long-term neurological damage, lung failure, organ dysfunction, or even death. Early recognition and treatment are essential to prevent or minimise these outcomes. Group B Streptococcus (GBS) infections range from mild to critical. The risk of complications is highest in the first days of life for newly borns, particularly when the correct steps during labour are not taken. Similarly, older adults and patients with chronic illnesses face heightened danger from GBS once it becomes invasive. Complications in Newborns 1. Sepsis Sepsis is a life-threatening condition where the body’s response to infection causes widespread inflammation, organ failure, or shock. In GBS-related neonatal sepsis: The infection spreads rapidly through the bloodstream Babies may develop low blood pressure, breathing problems, or poor circulation Immediate intensive care and antibiotics are required Risk of death is significant without treatment 2. Pneumonia Pneumonia due to GBS causes: Fluid buildup in the lungs Laboured or rapid breathing Low oxygen levels While treatable, severe cases may require mechanical breathing and extensive hospitalisation. 3. Meningitis Meningitis is more common in late-onset GBS and occurs when the bacteria reach the membranes around the brain and spinal cord. Complications include: Seizures Increased intracranial pressure Brain swelling Neurological damage Death in severe or untreated cases 4. Long-Term Neurological Issues Even with successful treatment, some babies develop: Hearing loss Cerebral palsy Developmental delays Learning difficulties The severity depends on how quickly the infection was diagnosed and treated. 5. Death Mortality from GBS in newborns ranges from 4–6% in high-resource settings and can be significantly higher in low-income regions without access to screening and care. Complications in Pregnant Women GBS infections during pregnancy may lead to: Urinary tract infections that spread to the kidneys (pyelonephritis) Chorioamnionitis, which can trigger preterm birth Endometritis or wound infections after delivery Sepsis, particularly after prolonged or complicated labour In rare cases, infection may spread to the placenta, threatening both mother and baby. Complications in Adults Non-pregnant adults, especially those over 65 or with chronic illnesses, may experience: 1. Skin and Soft Tissue Infections Can progress to necrotising fasciitis (flesh-eating disease) May require surgery or even amputation Risk of recurrence is higher in diabetics 2. Urinary Tract Infections Often benign but may ascend to cause kidney infections or enter the bloodstream Repeated UTIs may cause long-term bladder problems 3. Osteomyelitis and Joint Infections Bone infections can take weeks to resolve and may impair mobility Septic arthritis requires surgical drainage and extended antibiotic therapy 4. Sepsis and Septic Shock Leads to organ failure Requires intensive care, fluids, and vasopressors Mortality risk increases with age and underlying illness 5. Pneumonia Particularly dangerous in older adults and those with lung disease May be confused with viral or aspiration pneumonia, delaying treatment Emotional and Psychological Impact Parents of babies affected by GBS may experience: Anxiety or depression after a NICU admission Guilt or confusion, especially if they were unaware of GBS risks Postnatal PTSD in cases involving emergency delivery or neonatal complications Counselling and peer support can play a vital role in recovery. Financial and Systemic Burdens Complications from GBS: Increase hospital stays and NICU admissions Add pressure on overstretched healthcare systems Lead to long-term medical needs for children with neurological sequelae Prevention is cost-effective and reduces not only personal but societal burden. Preventing Complications Most complications are preventable with: Screening and intrapartum antibiotics in pregnancy Prompt treatment of suspected neonatal infections Proper wound care and hygiene in high-risk adults Vaccination development, which remains a top priority globally Conclusion | Complications of Group B Strep The complications of Group B Strep can be life-altering and, in some cases, fatal. From meningitis in newborns to sepsis in elderly adults, the burden of GBS disease underscores the need for vigilance, education, and prevention. By recognising the warning signs, implementing robust maternity care protocols, and developing future vaccines, healthcare providers can reduce the global impact of Group B Strep complications and safeguard the health of vulnerable populations. [Next: Back to Overview →]

Complications of Group B Strep Read More »

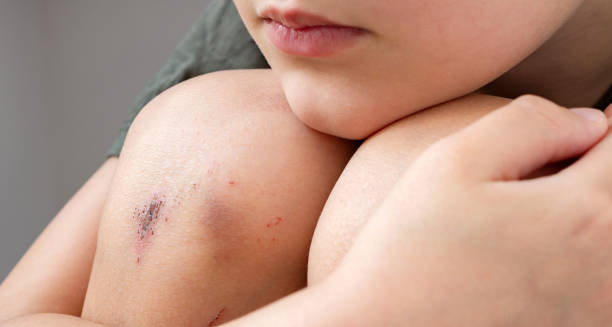
Close-up of a child's grazed knee with minor cuts and bruises

Grazes

Grazes – Overview Grazes are superficial skin injuries caused by friction or scraping against a rough surface. Also known as abrasions, this occurs when the outer layers of the skin are worn away, exposing sensitive nerve endings and capillaries. Although generally minor, they can be painful, bleed slightly, and require proper cleaning to prevent infection. These injuries are common among children, athletes, and people who engage in outdoor activities. Falling on concrete, gravel, or carpet are typical causes of grazes. Unlike cuts, these injuries do not usually involve deep tissue damage, but the affected area may sting and appear raw or red. Grazes usually heal without scarring, provided the wound is kept clean and moist during the healing process. The skin regenerates over time, forming a scab that eventually falls off. Most of these injuries do not require medical treatment, although larger or contaminated abrasions may need attention from a healthcare provider. Grazes – Overview The risk of infection increases if the injury is caused by dirty surfaces or if foreign material remains embedded in the skin. Tetanus vaccination should be up to date, especially for more extensive grazes involving soil or rusty metal. In summary, grazes are common, usually harmless skin abrasions that heal well with proper care. Keeping the wound clean and protected is key to a smooth and fast recovery. [Next: Causes of Grazes →]

Grazes Read More »

Teen boy sitting on pavement after falling and grazing his knee

Causes of Grazes

Causes of Grazes Causes of grazes are almost always mechanical, involving the skin scraping against a rough or hard surface. Unlike penetrating wounds, grazes result from friction, which removes the top layers of skin but usually spares deeper tissues. They are often accidental and tend to occur in active individuals or during unexpected falls. Accidental Falls The most common cause of grazes is a fall: Children running and tripping on pavements or school playgrounds Cyclists or skateboarders falling onto gravel, concrete, or tarmac Runners stumbling on uneven surfaces The palms, knees, elbows, and shins are frequent sites of injury due to instinctive reactions to break a fall. Sports and Physical Activities Contact and high-intensity sports often lead to grazes, including: Football, rugby, or hockey where collisions and tackles are common Martial arts or wrestling, where friction with mats causes abrasions Track and field events, particularly during falls or slides on synthetic surfaces Everyday Incidents Falling indoors onto rough carpet or textured flooring Brushing against brick walls or fences Removing adhesive bandages or tape too quickly Occupational Hazards Certain jobs may involve exposure to abrasive surfaces: Construction workers Landscapers and gardeners Delivery personnel navigating uneven terrain Lack of proper protective gear increases the risk. Environmental Factors | Causes of Grazes Wet or slippery conditions can cause sudden slips leading to grazing injuries, particularly when walking or running downhill or on slick surfaces. In conclusion, causes of grazes include falls, sports, occupational exposure, and environmental hazards. Taking safety precautions and using appropriate protective clothing can help minimise the risk. [Next: Symptoms of Grazes →]

Causes of Grazes Read More »

Close-up of a fresh red graze on human skin

Symptoms of Grazes

Symptoms of Grazes Symptoms of grazes are usually immediate and easily recognisable. The pain, appearance, and discomfort associated with grazes reflect the level of surface damage to the skin. While typically not serious, grazes can be very painful due to exposed nerve endings in the outer skin layers. Immediate Symptoms Stinging or burning pain at the site of injury, especially when touched or exposed to air Visible abrasion: The skin looks raw, red, or pink, and in some cases, small specks of dirt or debris may be embedded Bleeding or weeping: Grazes may ooze blood or clear fluid due to capillary disruption Swelling and mild inflammation around the affected area Scab Formation After the initial weeping phase, a scab forms over the graze: Protects the wound as new skin develops underneath Appears brown or reddish Should be left undisturbed to avoid re-injury or infection Itching and Tightness As healing progresses: The area may feel tight, particularly on joints or over muscles Itching is common during scab formation and indicates healing Scratching can lead to reopening the wound or introducing bacteria Signs of Infection While most grazes heal without issue, infection can occur if the wound is not properly cleaned: Increased redness or swelling Pus formation or foul odour Warmth around the site Persistent pain Fever or swollen lymph nodes (in severe cases) Delayed Healing Certain individuals may notice slower recovery due to: Underlying conditions like diabetes Poor blood circulation Repeated trauma to the area Symptoms of Grazes In summary, symptoms of grazes include immediate pain, visible skin loss, and scab formation, with potential signs of infection during recovery. Prompt wound care supports fast healing and minimises complications. [Next: Diagnosis of Grazes →]

Symptoms of Grazes Read More »

Doctor examining a patient's arm for grazes or skin injuries

Diagnosis of Grazes

Diagnosis of Grazes Diagnosis of grazes is usually clinical, meaning it is based on visual inspection and a brief patient history. In most cases, grazes are easily identifiable by their characteristic appearance and do not require specialised testing. However, a thorough examination ensures that no deeper injuries or complications are missed. Clinical Assessment During diagnosis, a healthcare provider will assess: Size and depth of the graze Location (over joints, hands, face, etc.) Signs of contamination (presence of gravel, dirt, or debris) Signs of infection (redness, pus, odour) Associated injuries, such as bruises, swelling, or sprains The goal is to determine whether the graze is superficial or if further treatment, such as wound cleaning, dressing, or antibiotics, is necessary. Wound Classification Healthcare professionals often classify wounds to guide treatment: Superficial grazes: Affect only the epidermis and are the most common Partial-thickness abrasions: Extend into the dermis but do not involve deeper tissues Full-thickness abrasions: Rare, may involve fat or muscle and can require medical attention Tetanus Risk Evaluation For more extensive grazes, especially those contaminated with soil or rust, the doctor will ask about tetanus vaccination history. A booster may be offered if more than 10 years have passed since the last dose, or sooner if the wound is high-risk. Functional Testing (If Over Joints) If the graze is located near or over a joint, the provider may check for: Range of motion: Ensuring movement is not restricted due to pain or swelling Deeper damage: Looking for indications of underlying ligament or tendon injury When Imaging Is Needed Though rare for grazes, an X-ray may be considered if: A foreign body is suspected within the wound There is significant swelling or pain, raising concern about fractures or joint involvement Diagnosis of Grazes In summary, diagnosis of grazes is straightforward and based on appearance, depth, and contamination risk. Early and accurate evaluation helps prevent complications and supports effective healing. [Next: Treatment of Grazes →]

Diagnosis of Grazes Read More »

Treatment of Grazes

Treatment of Grazes

Treatment of Grazes Treatment of grazes focuses on cleaning the wound, protecting it during healing, and preventing infection. Most grazes can be treated at home with basic first aid supplies, but some may need professional care, especially if they are large, contaminated, or slow to heal. Immediate First Aid Wash hands before touching the wound Stop any bleeding with gentle pressure using sterile gauze or a clean cloth Clean the wound under cool, running water; use mild soap around (not in) the wound Remove debris carefully with tweezers sterilised with alcohol Apply antiseptic such as iodine or chlorhexidine to reduce infection risk Avoid using hydrogen peroxide or alcohol directly in the wound, as these may delay healing. Dress the Wound Cover with a non-stick, sterile dressing or hydrocolloid plaster Change the dressing daily or when wet or dirty Apply antibiotic ointment (if advised) to prevent infection and keep the wound moist Keeping the wound moist—not dry—encourages faster healing with reduced scarring. Pain and Inflammation Over-the-counter pain relievers like paracetamol or ibuprofen may help Elevate the area if there is swelling, especially on limbs When to See a Doctor Seek medical attention if: The graze is large, deep, or heavily contaminated Signs of infection develop (pus, redness, warmth) The wound doesn’t improve within a few days There’s concern about tetanus (dirty wound, rusty surface, no recent booster) Avoiding Re-injury Keep the area protected during sports or work Use knee or elbow pads for children involved in high-impact play Treatment of Grazes In summary, treatment of grazes involves careful cleaning, protection, and infection prevention. Most heal quickly with home care, but attention to cleanliness and dressing changes is vital to avoid complications. [Next: Complications of Grazes →]

Treatment of Grazes Read More »

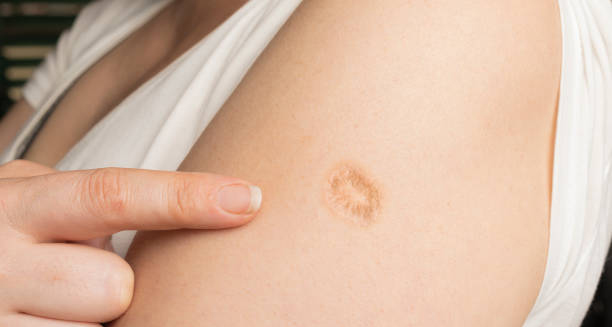
Healed scar from a graze on upper arm

Complications and Recovery from Grazes

Complications and Recovery from Grazes Complications and recovery from grazes are generally minimal, as these injuries involve only the skin’s surface. However, if grazes are not properly cleaned or cared for, they may become infected or result in delayed healing and scarring. Recovery time depends on the size, depth, and location of the graze, as well as the individual’s overall health. Possible Complications Infection: If the wound becomes red, swollen, hot, or filled with pus, this indicates infection and may require antibiotics. Scarring: While superficial grazes usually heal without marks, deeper abrasions may leave scars, especially if picked or scratched. Delayed healing: Caused by re-injury, underlying health conditions (e.g. diabetes), or poor wound hygiene Embedded debris: If not fully removed, particles like gravel or sand can cause inflammation or chronic irritation Signs of Proper Healing Formation of a scab, which protects new skin underneath Reduction in redness and swelling within a few days Itching, which signals tissue repair Return of normal skin colour and texture over time Recovery Timeline Small grazes: Heal in 3–7 days Moderate abrasions: May take 1–2 weeks Deeper abrasions: Require longer, especially if scarring occurs Healing is quicker in young, healthy individuals and when the wound is kept clean, moist, and protected. Scar Prevention Once healed, apply moisturiser or silicone gel to soften scar tissue Protect the area from sun exposure, as new skin is prone to pigmentation changes Aftercare Tips Avoid scratching or disturbing the scab Continue dressing changes until the wound is dry and sealed Monitor for changes that may suggest complications Complications and Recovery from Grazes In conclusion, complications and recovery from grazes are uncommon with good wound care. Most people experience complete healing without long-term effects. Understanding proper aftercare helps ensure fast recovery and minimal scarring. [Next: Back to Overview →]

Complications and Recovery from Grazes Read More »

Medical illustration of granulomatosis with polyangiitis symptoms

Granulomatosis with Polyangiitis

Granulomatosis with Polyangiitis Granulomatosis with polyangiitis is a rare but serious autoimmune disease characterised by inflammation of blood vessels, particularly small- and medium-sized vessels throughout the body. Formerly known as Wegener’s granulomatosis, granulomatosis with polyangiitis often affects the respiratory tract and kidneys, although it can involve many organs. The inflammation can lead to tissue damage, organ dysfunction, and, if left untreated, life-threatening complications. This condition belongs to a group of disorders known as ANCA-associated vasculitides (AAV), named for the presence of anti-neutrophil cytoplasmic antibodies (ANCAs) found in many affected individuals. Granulomatosis with polyangiitis tends to strike adults aged 40–60 but can occur at any age. Early diagnosis and aggressive treatment with immunosuppressive drugs can help achieve remission and prevent permanent damage. Key Characteristics Granulomatosis with polyangiitis is marked by three main pathological features: Granulomatous inflammation – a type of immune response involving clusters of inflammatory cells Vasculitis – inflammation of the blood vessel walls Necrosis – tissue damage resulting from loss of blood supply or immune destruction These features affect organs such as: Sinuses, nose, and upper airways Lungs Kidneys Skin, eyes, joints, and nervous system Symptoms often begin subtly, with fatigue, joint pain, or sinus issues, before progressing to more serious organ involvement. Epidemiology and Risk Granulomatosis with polyangiitis is rare, with an estimated annual incidence of 10–20 cases per million people worldwide. Risk factors include: Middle age (more common in individuals aged 40–65) Slight male predominance Caucasian ethnicity (more prevalent in European populations) Family history of autoimmune disorders (though not directly inherited) It affects people globally and across all demographics, but detection rates vary due to limited awareness and diagnostic capacity in some regions. Early Symptoms Initial symptoms may be vague and resemble common illnesses: Fatigue and general malaise Unexplained weight loss Fever and night sweats Persistent sinus infections or nasal congestion Ear pain or hearing loss Dry cough or shortness of breath Joint and muscle aches Because these symptoms mimic those of respiratory infections, sinusitis, or allergies, the condition is often misdiagnosed in its early stages. Respiratory Involvement The upper and lower respiratory tracts are commonly affected: Sinusitis, nasal crusting, or frequent nosebleeds Saddle-nose deformity due to cartilage destruction Chronic cough, wheezing, or haemoptysis (coughing up blood) Lung nodules or infiltrates, visible on chest imaging These issues can escalate to lung haemorrhage or respiratory failure if not promptly addressed. Kidney Involvement One of the most serious aspects of granulomatosis with polyangiitis is glomerulonephritis, or inflammation of the kidneys’ filtering units: Early signs include blood or protein in the urine May progress silently to kidney failure Renal biopsy is often necessary for definitive diagnosis If untreated, kidney involvement can lead to irreversible damage and the need for dialysis. Other Organ Systems The disease may also affect: Skin – purple spots (purpura), ulcers, or nodules Eyes – inflammation, dryness, pain, or vision loss Nerves – tingling, numbness, or muscle weakness Joints – arthritis-like pain, especially in large joints Multisystem involvement complicates diagnosis and requires a coordinated approach to treatment. Diagnosis Challenges Because of its rarity and non-specific early symptoms, diagnosis is often delayed. The condition must be distinguished from infections, cancers, and other autoimmune diseases. Blood tests, imaging, and biopsy are typically needed for confirmation. Importance of Early Treatment Prompt recognition is critical. Without treatment, granulomatosis with polyangiitis can progress rapidly, causing permanent damage or death. With appropriate therapy, however, long-term remission is possible for many patients. Conclusion | Granulomatosis with Polyangiitis Granulomatosis with polyangiitis is a complex autoimmune vasculitis that causes systemic inflammation and serious organ damage if left untreated. Its early symptoms often mimic common conditions, making awareness and timely diagnosis vital. Despite its severity, with modern immunosuppressive therapy, granulomatosis with polyangiitis is a manageable condition, and many individuals can achieve lasting remission. [Next: Causes of Granulomatosis with Polyangiitis →]


Granulomatosis with Polyangiitis Read More »

Scroll to Top