Mental Matters

Author name: admin

Causes of Granulomatosis with Polyangiitis

Causes of Granulomatosis with Polyangiitis

Causes of Granulomatosis with Polyangiitis Doctors still do not fully understand what causes granulomatosis with polyangiitis (GPA). However, they believe it begins with an abnormal immune response that causes inflammation in blood vessels and nearby tissues. Even though the exact cause remains unknown, research points to a mix of genetics, environmental exposure, infections, and autoimmune activity as major contributors. GPA belongs to a group of illnesses called ANCA-associated vasculitides, which involve harmful antibodies called anti-neutrophil cytoplasmic antibodies (ANCAs). These antibodies seem to play a key role in the damage seen in affected organs. 1. Autoimmune Mechanisms First and foremost, GPA behaves like an autoimmune disease. In this condition, the immune system attacks the body’s own tissues by mistake. While the reason for this faulty immune attack isn’t clear, several things happen: This process creates granulomas, blood vessel inflammation (vasculitis), and in some cases, tissue death (necrosis). 1. Autoimmune Mechanisms First and foremost, GPA behaves like an autoimmune disease. In this condition, the immune system attacks the body’s own tissues by mistake. While the reason for this faulty immune attack isn’t clear, several things happen: This process creates granulomas, blood vessel inflammation (vasculitis), and in some cases, tissue death (necrosis). 2. Genetic Factors Although GPA doesn’t pass directly from parent to child, certain genes may make some people more likely to develop it. For example: These genetic factors suggest that some individuals carry an inherited vulnerability. When exposed to the right trigger, their immune system may overreact. 3. Environmental and Occupational Exposures Next, environmental and workplace exposures may also trigger GPA in people who already carry genetic risk. Research has linked the disease to: These substances may damage tissues or overstimulate the immune system, leading to inflammation. 4. Infections Infections may also play an important role. They can either trigger GPA for the first time or make it worse later. Specifically: These infections may set off or maintain harmful immune reactions that damage the blood vessels. 5. Drug-Induced Triggers Although uncommon, certain medications can cause a condition that looks like GPA. These include: Usually, the symptoms go away after stopping the drug. Doctors can often tell drug-induced cases apart from true GPA through blood tests and history. 6. Immune System Triggers Sometimes, GPA may start after the immune system reacts to injury or repeated exposure to certain antigens. For example: This overreaction turns into chronic inflammation unless doctors stop it early. 7. Hormonal and Biological Factors Finally, some differences in age, sex, and hormones may affect who gets GPA. For instance: Although doctors don’t yet understand these patterns fully, they point to a mix of biological influences. Summary of Contributing Factors Category Examples Autoimmune response ANCA antibodies, neutrophil activation Genetic susceptibility HLA genes, PTPN22, SERPINA1 Environmental exposure Silica, solvents, farm chemicals Infections Staphylococcus aureus, viral infections Drug-induced triggers Hydralazine, PTU, levamisole Biological factors Age, sex, immune system behavior Multifactorial Nature of GPA So far, no single cause explains all cases of GPA. Instead, the disease likely results from a mix of factors, such as: This complex picture explains why GPA looks different from one person to another. It also guides doctors to treat the root immune problem—not just the symptoms. Conclusion | Causes of Granulomatosis with Polyangiitis To sum up, GPA results from a combination of genetic, environmental, infectious, and immune-related factors. Even though researchers haven’t found one clear cause, growing evidence points to autoimmune activity driven by ANCAs. By better understanding what causes GPA, doctors can improve how they diagnose it, treat it, and support patients living with this rare but serious condition. [Next: Symptoms of Granulomatosis with Polyangiitis→]
Causes of Granulomatosis with Polyangiitis Read More »

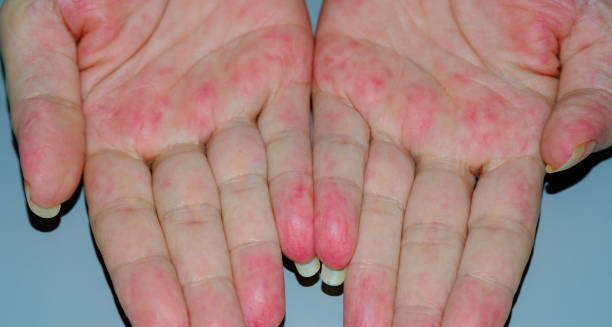
Red rash and inflammation on palms due to granulomatosis with polyangiitis

Symptoms of Granulomatosis with Polyangiitis

Symptoms of Granulomatosis with Polyangiitis The symptoms of granulomatosis with polyangiitis vary widely depending on which organs are affected, but typically include a mix of respiratory, renal, and generalised inflammatory signs. The symptoms of granulomatosis with polyangiitis often start gradually and may initially resemble common illnesses such as sinusitis or the flu, making early diagnosis challenging. However, as the disease progresses, organ damage may become more pronounced, sometimes resulting in life-threatening complications if left untreated. Granulomatosis with polyangiitis (GPA) is a rare autoimmune vasculitis that causes inflammation of small- and medium-sized blood vessels, particularly in the lungs, kidneys, and upper airways. Granulomas—clusters of inflammatory cells—also form in tissues, further contributing to damage. Because GPA can affect virtually any organ system, the symptoms are diverse and may develop over days, weeks, or even months. General Symptoms In the early stages, people often experience non-specific systemic symptoms such as: Fatigue and low energy Weight loss without trying Fever and night sweats Loss of appetite Joint and muscle aches resembling arthritis Mild anaemia or generalised weakness These symptoms often precede more localised organ involvement and are sometimes mistaken for viral infections or chronic fatigue syndrome. Upper Respiratory Tract Involvement The upper respiratory tract is involved in over 90% of cases. Common symptoms include: Chronic sinusitis or persistent nasal congestion Bloody or crusted nasal discharge Nosebleeds (epistaxis) Nasal septal perforation, which may lead to a saddle-nose deformity Hearing loss due to eustachian tube dysfunction Ear pain, fullness, or infections These symptoms are often recurrent and may resist standard treatment with antibiotics or decongestants, raising suspicion of an underlying inflammatory process. Lower Respiratory Tract Symptoms Lung involvement is another hallmark of GPA and may present with: Chronic dry cough Shortness of breath Chest pain, especially on deep breathing Coughing up blood (haemoptysis) Wheezing or crackles on examination Chest X-rays or CT scans may reveal nodules, infiltrates, or cavities—sometimes misinterpreted as infections, tuberculosis, or cancer. In severe cases, lung haemorrhage can occur, requiring urgent treatment. Kidney Involvement Kidney inflammation, or glomerulonephritis, may be silent in early stages but is one of the most serious manifestations: Blood in the urine (haematuria) Protein in the urine (proteinuria) Foamy urine High blood pressure Swelling in the ankles or around the eyes Without treatment, kidney function may deteriorate rapidly, leading to chronic kidney disease or kidney failure. Eye and Vision Problems Inflammation may extend to the eyes, resulting in: Red, painful eyes Blurred vision or double vision Dry eyes Episcleritis or scleritis (inflammation of the white part of the eye) Vision loss in severe cases Prompt ophthalmologic assessment is essential to preserve vision in affected individuals. Skin Lesions Skin symptoms occur in approximately 30–50% of cases. These may include: Reddish or purple spots (purpura), particularly on the legs Ulcers, especially on the extremities Tender nodules or lumps Rashes resembling allergic reactions Skin biopsy may help confirm vasculitis as the cause of these lesions. Nervous System Symptoms The nervous system may also be affected, causing: Peripheral neuropathy (numbness, tingling, or burning in the hands or feet) Muscle weakness Cranial nerve palsies Rarely, stroke-like episodes or central nervous system involvement Neurological symptoms can be subtle or debilitating, depending on the nerves involved. Gastrointestinal Involvement Although less common, the gastrointestinal system can also be affected, leading to: Abdominal pain Nausea or vomiting Gastrointestinal bleeding or ulcers These symptoms may mimic other GI conditions and complicate diagnosis. Symptoms in Children Granulomatosis with polyangiitis is rare in children but presents similarly: Fever, weight loss, and fatigue Ear, nose, and throat infections that do not resolve Joint pain or swelling Haematuria or proteinuria Paediatric diagnosis can be particularly challenging due to overlap with common childhood illnesses. Patterns and Progression There is no fixed sequence for symptom development: Some individuals have isolated respiratory symptoms for months before kidney involvement appears Others may present suddenly with multisystem disease Flare-ups can alternate with periods of remission This unpredictable pattern underscores the need for ongoing monitoring and early specialist referral. Conclusion | Symptoms of Granulomatosis with Polyangiitis The symptoms of granulomatosis with polyangiitis are diverse, ranging from sinus congestion and joint pain to life-threatening kidney failure or lung haemorrhage. Because the symptoms of granulomatosis with polyangiitis often mimic more common conditions, early recognition requires a high index of suspicion, especially in persistent or multisystem disease. Accurate diagnosis and early treatment are essential to reduce the risk of long-term complications and achieve remission. [Next: Diagnosis of Granulomatosis with Polyangiitis →]

Symptoms of Granulomatosis with Polyangiitis Read More »

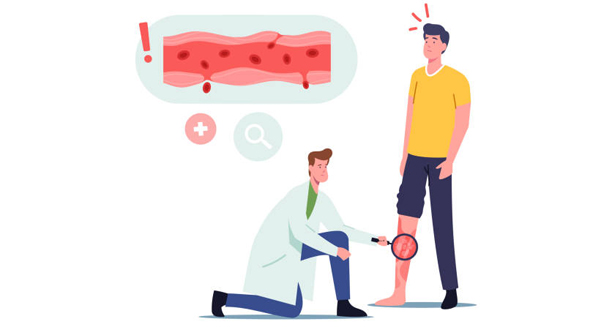
Doctor examining leg rash to diagnose granulomatosis with polyangiitis

Diagnosis of Granulomatosis with Polyangiitis

Diagnosis of Granulomatosis with Polyangiitis The diagnosis of granulomatosis with polyangiitis involves a combination of clinical evaluation, blood tests, imaging, and tissue biopsy. Since the diagnosis of granulomatosis with polyangiitis can be challenging due to its rarity and symptom overlap with other illnesses, it requires a coordinated approach between general practitioners, rheumatologists, nephrologists, and other specialists. Granulomatosis with polyangiitis (GPA) is an ANCA-associated vasculitis that causes inflammation of blood vessels and tissues. Diagnosis is critical to prevent organ damage that cannot be undone, and early treatment improves outcomes significantly. Clinical Evaluation Diagnosis begins with a detailed medical history and physical examination. Key clues include: Chronic sinus, nasal, or ear infections Persistent cough or haemoptysis Blood in the urine or kidney function decline Joint pains, skin lesions, and systemic inflammation Symptoms involving multiple systems (e.g. lungs and kidneys) Because no single symptom is definitive, the pattern of involvement often points toward GPA. Blood Tests Several blood tests support the diagnosis and rule out other conditions: 1. ANCA (Anti-Neutrophil Cytoplasmic Antibody) Test Positive in approximately 80–90% of GPA cases Most patients test positive for c-ANCA (cytoplasmic ANCA), targeting proteinase 3 (PR3) A smaller number have p-ANCA, often targeting myeloperoxidase (MPO) Though not 100% specific, ANCA testing is a valuable tool for diagnosis when interpreted alongside clinical findings. 2. Inflammatory Markers Elevated ESR (erythrocyte sedimentation rate) Raised CRP (C-reactive protein) These non-specific markers indicate active inflammation and help monitor disease activity. 3. Renal Function Tests Serum creatinine and eGFR to assess kidney function Urinalysis to detect blood, protein, or red blood cell casts in the urine Abnormal kidney results often prompt further testing, including biopsy. Imaging Studies Imaging helps identify organ involvement and guide biopsy: Chest X-ray or CT Scan May reveal lung nodules, cavities, infiltrates, or effusions Useful for checking disease severity and monitoring response to treatment Sinus or Ear CT Scans Show mucosal thickening, bone destruction, or fluid build-up Can guide surgical sampling in ENT-related cases Biopsy Tissue biopsy remains the gold standard for diagnosis. Biopsies may be taken from: Kidneys – to identify crescentic glomerulonephritis and confirm vasculitis Lungs – when accessible and safe Skin – in patients with rashes or ulcers Nasal or sinus tissue – often inflamed and easier to access Typical findings include granulomatous inflammation, vasculitis, and necrosis. Diagnostic Criteria and Scoring The American College of Rheumatology (ACR) and European Alliance of Associations for Rheumatology (EULAR) provide classification criteria based on symptoms, ANCA status, imaging, and biopsy results. These criteria help standardise diagnosis in both clinical and research settings. A formal diagnosis often requires several of the following: ANCA positive Upper or lower airway involvement Renal issues or any evidence of glomerulonephritis Histopathological confirmation of granulomas or vasculitis Differential Diagnosis GPA must be distinguished from: Infections (e.g. tuberculosis, fungal lung infections) Other vasculitides, such as microscopic polyangiitis or eosinophilic granulomatosis with polyangiitis Lung cancer or lymphoma Systemic lupus erythematosus Goodpasture’s syndrome Biopsy and ANCA testing are crucial in making these distinctions. Challenges in Diagnosis Diagnosis may be delayed due to: Non-specific early symptoms Misdiagnosis as sinusitis, pneumonia, or asthma Intermittent flares and remissions Negative ANCA test in a small proportion of cases In these scenarios, repeat testing and tissue sampling may be necessary. Importance of Early Diagnosis Early diagnosis allows for prompt initiation of treatment: Reduces risk of permanent organ damage Improves survival rates and quality of life Increases likelihood of achieving remission With current treatments, many patients can lead full and active lives despite the initial severity of disease. Conclusion | Diagnosis of Granulomatosis with Polyangiitis The diagnosis of granulomatosis with polyangiitis requires careful clinical judgment supported by laboratory and histological evidence. Because the diagnosis of granulomatosis with polyangiitis can be difficult in early stages, clinicians must maintain a high index of suspicion in patients with multi-system symptoms. Timely recognition, expert consultation, and comprehensive testing are the foundation for effective management of this complex autoimmune vasculitis. [Next: Treatment of Granulomatosis with Polyangiitis→]

Diagnosis of Granulomatosis with Polyangiitis Read More »

Immunosuppressive medication for granulomatosis with polyangiitis treatment

Treatment of Granulomatosis with Polyangiitis

Treatment of Granulomatosis with Polyangiitis Treating granulomatosis with polyangiitis (GPA) involves two key phases: first, inducing remission and then maintaining it over the long term to prevent relapses. Since GPA treatment lowers the immune system’s defenses, doctors must balance stopping inflammation with minimizing side effects and complications. GPA is a serious autoimmune disease that causes inflammation in blood vessels. Thankfully, treatment has come a long way. Thanks to powerful immune-suppressing medications and newer biologic drugs, many patients now enter remission and live well—especially when treatment starts early and fits the severity of the disease. Phase 1: Induction of Remission The first goal in treatment is to quickly stop active inflammation. This step helps protect vital organs like the kidneys and lungs from lasting damage. 1. Glucocorticoids (Steroids) Doctors usually begin with strong steroids such as prednisolone or methylprednisolone: Although steroids work well, using them for a long time can cause problems such as: To lower these risks, doctors often add other medications that reduce the need for high steroid doses. 2. Immunosuppressive Agents Doctors usually combine steroids with one of these two powerful immune-suppressing drugs: a. Cyclophosphamide b. Rituximab Both treatments need regular blood tests and infection prevention, such as antibiotics to guard against lung infections. Additional Support During Induction During this early treatment phase, patients often need extra care: This support helps reduce side effects and improves the patient’s ability to stay on treatment. Phase 2: Maintenance of Remission Once inflammation is under control, treatment shifts to keeping the disease quiet. This helps prevent flare-ups and limits long-term damage. 1. Azathioprine 2. Methotrexate 3. Mycophenolate Mofetil 4. Rituximab (Maintenance Doses) Most patients stay on maintenance therapy for 18 to 24 months, or longer if they’re at high risk of relapsing. Monitoring and Follow-Up Doctors must check patients often during and after treatment. These checks usually include: Patients also need regular checks for the side effects of their medications, including infections and possible cancers. Lifestyle and Preventive Measures To stay well during treatment, patients should also: Open, honest communication with a team of doctors—including rheumatologists, lung specialists, and mental health experts—helps patients stay on track and feel supported. Pregnancy and Fertility Considerations Treatment may affect the ability to have children, so doctors discuss fertility early on: Women should aim to become pregnant during remission, and specialists should guide treatment before and during pregnancy. Prognosis with Treatment Without treatment, GPA can be deadly. However, today’s treatment offers real hope: Conclusion | Treatment of Granulomatosis with Polyangiitis Treating GPA is complex, but it works well when started early and managed closely. From steroids to biologics to supportive care, every part of treatment must match the patient’s needs and goals. With routine checkups, healthy habits, and strong medical support, most patients can enjoy active, fulfilling lives—even with this rare autoimmune disease. [Next: Complications of Granulomatosis with Polyangiitis →]

Treatment of Granulomatosis with Polyangiitis Read More »

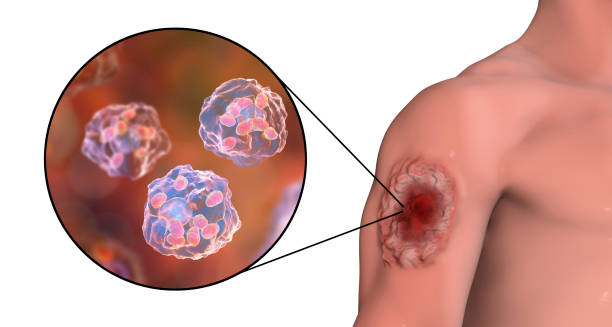
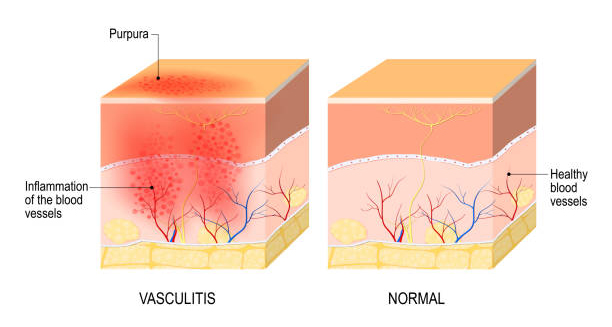
Granulomatosis with polyangiitis skin lesion and neutrophil inflammation

Complications of Granulomatosis with Polyangiitis

Complications of Granulomatosis with Polyangiitis Granulomatosis with polyangiitis (GPA) can lead to many serious complications. These problems come from both the disease itself and the side effects of long-term treatment with immune-suppressing medicine. As a result, the illness can affect almost every organ system. The most severe complications include kidney failure, lung bleeding, long-term infections, and a lower quality of life due to organ damage or the effects of treatment. GPA is a disease that causes inflammation of blood vessels throughout the body. Without proper treatment, the condition can worsen quickly. Even when patients receive treatment, doctors still need to check them often. This helps catch problems early and avoid lasting damage. 1. Kidney Failure One of the most dangerous complications of GPA involves the kidneys. The disease often leads to glomerulonephritis, a type of kidney inflammation. This condition causes: Even when the disease seems under control, kidney problems can still appear if inflammation continues. 2. Lung Damage GPA can also harm the lungs in many ways. Some common lung-related problems include: In the long run, this damage can cause breathing problems and the need for oxygen support. 3. Hearing and Sinus Problems The disease often affects the nose and ears. Over time, this may lead to: These problems often need help from an ENT doctor and may affect a person’s daily life and confidence. 4. Vision Problems When GPA reaches the eyes, it can cause: Eye problems from GPA are emergencies. Eye specialists must treat them right away to protect vision. 5. Nerve Damage (Peripheral Neuropathy) Inflammation of the blood vessels that feed the nerves can cause: Even after treatment, nerve healing can take a long time and may not be complete. 6. Skin Ulcers and Tissue Death GPA can also affect the skin. When this happens, people may get: These skin issues can reduce movement and often lead to hospital visits. 7. Disease Relapse and Long-Term Illness Many people with GPA experience relapses. In fact: Over time, these repeated flare-ups can lead to more organ damage and stronger medication side effects. 8. Higher Risk of Infections Since treatment weakens the immune system, people with GPA are more likely to get infections, such as: To help prevent this, patients should follow infection prevention plans and stay up to date with vaccines. 9. Increased Risk of Cancer Some medications, especially cyclophosphamide, can raise the risk of certain cancers. These include: Doctors recommend regular cancer screenings for people who take these drugs long-term. 10. Mental and Emotional Effects Living with GPA can take a toll on mental health. Many people experience: Talking to mental health professionals or joining support groups can help patients cope better and stay positive. 11. Fertility and Pregnancy Concerns Cyclophosphamide may affect the ability to have children, especially in younger patients. Also: Planning ahead and getting the right advice helps patients make informed choices. Summary of Key Complications System Affected Possible Problems Kidneys Kidney inflammation, long-term damage, kidney failure Lungs Bleeding, lung lumps, coughing, infections ENT Hearing loss, nasal shape changes, smell loss Eyes Vision loss, nerve damage Nerves Numbness, weakness, movement issues Skin Ulcers, dead tissue, slow healing General Relapse, infections, cancer risk, emotional stress Conclusion The complications of granulomatosis with polyangiitis can be very serious, especially if doctors don’t catch the disease early or if patients don’t receive ongoing care. However, with early treatment and a complete care plan, many of these problems can be avoided or managed well. Teaching patients about the disease, checking on them regularly, and involving a team of health professionals are the best ways to reduce long-term harm and improve quality of life. [Next: Back to Overview →]

Complications of Granulomatosis with Polyangiitis Read More »

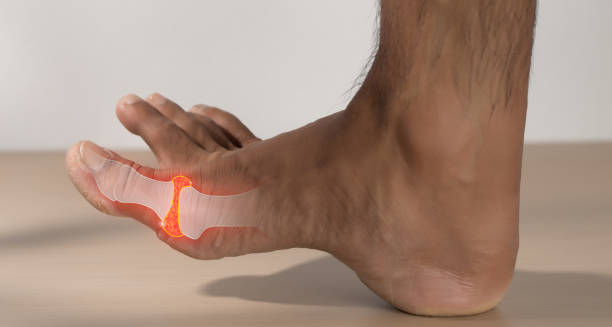
Inflamed toe joint with highlighted gout pain

Gout

Gout Gout is a form of inflammatory arthritis characterised by sudden, severe attacks of pain, swelling, and redness in one or more joints. Most commonly affecting the big toe, gout occurs when high levels of uric acid in the blood form sharp crystals in the joints. These crystals trigger inflammation and intense discomfort, often waking people in the middle of the night with a burning sensation in the affected joint. Although historically associated with overindulgence in rich foods and alcohol—often referred to as “the disease of kings”—gout affects millions of people worldwide, regardless of lifestyle. It is a chronic condition that, if left untreated, can lead to joint damage, kidney stones, and a significant reduction in quality of life. Fortunately, with proper treatment and lifestyle adjustments, gout can be effectively managed or even prevented. What Is Uric Acid? Uric acid is a natural waste product formed when the body breaks down purines—substances found in human cells and in many foods, such as red meat, seafood, and alcohol. Normally, uric acid dissolves in the blood, passes through the kidneys, and exits the body via urine. However, when the body produces too much uric acid or fails to excrete enough of it, the substance builds up in the bloodstream (hyperuricaemia). When uric acid concentrations become too high, it can crystallise, depositing sharp, needle-like crystals in the joints and surrounding tissue. This leads to the intense pain and inflammation that characterise a gout attack. Symptoms and Presentation The hallmark of gout is a sudden and excruciating flare-up of joint pain, often at night. Classic symptoms include: Intense joint pain, often in the big toe (podagra), but also in ankles, knees, elbows, wrists, or fingers Swelling and redness in the affected joint Warmth and tenderness over the joint, with extreme sensitivity to touch Limited range of motion as inflammation worsens Lingering discomfort after the acute attack subsides An initial attack typically lasts 3 to 10 days and may not recur for months or even years. Without treatment, however, attacks become more frequent and severe, eventually affecting multiple joints and causing chronic damage. Who Gets Gout? Gout can affect anyone, but certain groups are more susceptible: Men over 40 are at higher risk than women, though postmenopausal women also see increased incidence Individuals with a family history of gout People with kidney disease, high blood pressure, or diabetes Those who are overweight or obese Individuals on certain medications, such as diuretics or immunosuppressants People who consume excessive alcohol, especially beer or spirits Although diet and lifestyle contribute to risk, genetic and medical factors often play a more significant role. Stages of Gout Gout develops in distinct stages: Asymptomatic hyperuricaemia: Elevated uric acid levels without symptoms Acute gout attack: Sudden joint pain and inflammation Intercritical gout: The symptom-free period between attacks Chronic tophaceous gout: Frequent attacks and joint damage, often with visible deposits (tophi) under the skin Progression to chronic gout can take years, but it is preventable with early diagnosis and management. Gout and Kidney Health Because uric acid is primarily filtered by the kidneys, any impairment in kidney function can exacerbate gout. Conversely, excess uric acid can form crystals in the kidneys, leading to kidney stones or even chronic kidney disease over time. This bidirectional relationship highlights the importance of monitoring kidney health in people with gout. Misconceptions About Gout Despite its prevalence, gout is often misunderstood. Common myths include: “Only old men get gout” – It can affect younger people and women, particularly after menopause “Gout is self-inflicted” – While diet plays a role, genetics and underlying health conditions are major factors “Once symptoms are gone, it’s cured” – Without long-term uric acid control, attacks will likely return Dispelling these myths can encourage earlier treatment and reduce stigma. Conclusion | Gout Gout is a painful and potentially disabling form of arthritis that arises from elevated uric acid levels in the body. While it often begins with a sudden attack in a single joint, gout is a chronic condition that requires long-term management to prevent joint damage and kidney complications. Through a combination of medication, lifestyle changes, and medical monitoring, most individuals can achieve excellent control and avoid future flare-ups. [Next: Causes of Gout →]

Gout Read More »

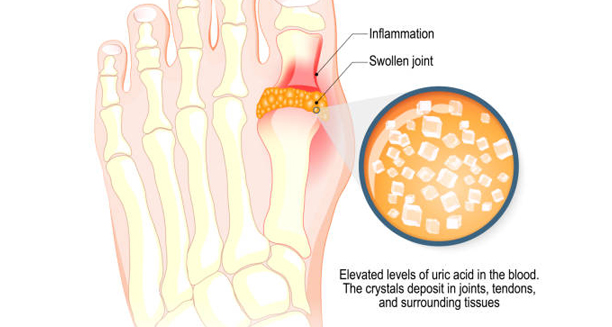
Illustration showing uric acid crystal buildup in the toe joint causing gout

Causes of Gout

Causes of Gout The causes of gout are primarily linked to elevated levels of uric acid in the blood, a condition known as hyperuricaemia. When uric acid builds up, it can form sharp crystals that deposit in the joints, triggering inflammation and pain. While the biological mechanism behind gout is well understood, the causes of gout are complex and multifactorial, involving genetics, diet, kidney function, and other health conditions. Understanding the diverse causes can help individuals reduce their risk and support healthcare professionals in designing tailored treatment strategies. 1. Overproduction of Uric Acid In some individuals, the body naturally produces more uric acid than it can efficiently eliminate. This may be due to: Genetic predisposition: Some people inherit a tendency to produce more purines or less effective enzymes for uric acid breakdown High cell turnover conditions, such as psoriasis or certain cancers Crash diets or starvation, which can increase uric acid generation Excessive alcohol use, which raises purine metabolism and uric acid production People who overproduce uric acid may develop gout even with normal kidney function. 2. Reduced Excretion of Uric Acid More commonly, gout results from the kidneys failing to eliminate uric acid efficiently. This can be caused by: Chronic kidney disease, which reduces filtration efficiency Dehydration, limiting uric acid clearance Certain medications, including: Diuretics (e.g. thiazides, loop diuretics) Low-dose aspirin Cyclosporine and other immunosuppressants In such cases, even moderate uric acid production can result in crystal accumulation. 3. Dietary Triggers While diet alone rarely causes gout, it can significantly influence uric acid levels, particularly in susceptible individuals. Foods high in purines include: Red meat and organ meats (e.g. liver, kidneys) Seafood, especially shellfish and oily fish like sardines Alcohol, especially beer and spirits Sugary drinks and foods high in fructose, which increase uric acid synthesis Frequent consumption of these foods can precipitate acute attacks in those with underlying hyperuricaemia. 4. Obesity and Metabolic Syndrome Obesity is a significant risk factor for gout. It contributes by: Increasing uric acid production Decreasing renal excretion efficiency Promoting insulin resistance, which is linked to elevated uric acid levels People with metabolic syndrome—characterised by central obesity, hypertension, high triglycerides, and insulin resistance—are at particularly high risk of developing gout. 5. Medical Conditions Several health conditions are known to increase gout risk: Hypertension Diabetes mellitus Hypothyroidism Sleep apnoea Organ transplants, especially those requiring immunosuppressive drugs These conditions often overlap, amplifying the risk and complexity of gout management. 6. Family History Gout tends to run in families. Individuals with a close relative (parent or sibling) who has gout are more likely to develop the condition themselves. This is due to: Shared genetic traits Common lifestyle habits Similar metabolic profiles Family history should be considered a strong risk indicator and used to guide early screening and prevention strategies. 7. Trauma or Surgery Physical stress, such as joint injury or recent surgery, can trigger an acute gout attack. The reason is not fully understood, but stress on a joint may mobilise uric acid or create conditions favourable to crystal deposition. Postoperative patients with known hyperuricaemia are often monitored closely to prevent flare-ups during recovery. 8. Age and Hormonal Changes Men over 40 are more likely to develop gout due to naturally higher uric acid levels Women are largely protected until menopause, after which oestrogen levels drop and uric acid levels may rise Hormonal shifts, including from medications like testosterone therapy, can also impact uric acid metabolism Summary of Major Causes Category Examples Overproduction Genetics, high purine turnover, alcohol Underexcretion Kidney disease, diuretics, dehydration Dietary factors Red meat, seafood, alcohol, sugary drinks Medical conditions Obesity, diabetes, hypertension, hypothyroidism Genetics Family history of gout Physical triggers Trauma, surgery Hormonal influence Menopause, testosterone therapy Conclusion | Causes of Gout The causes of gout are diverse and often interrelated, combining genetic, metabolic, dietary, and lifestyle factors. While some risk factors like age or genetics are unchangeable, others—such as diet, hydration, and medication use—can be addressed to reduce uric acid levels. By understanding the causes of gout, patients and healthcare providers can work together to prevent flare-ups and manage long-term health effectively. [Next: Symptoms of Gout→]

Causes of Gout Read More »

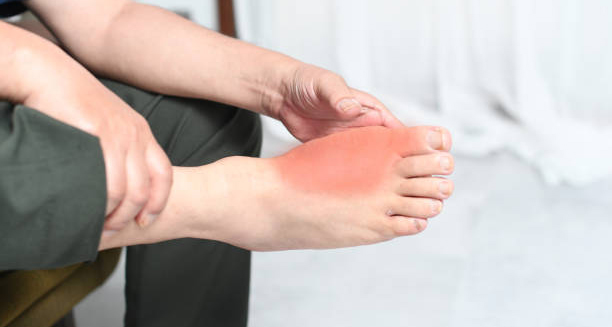
Person holding red, inflamed foot due to gout symptoms

Symptoms of Gout

Symptoms of Gout The symptoms of gout are often dramatic, involving sudden, intense pain, redness, and swelling in a joint—usually at night. These flares can appear without warning and are frequently so severe that even the light touch of a bedsheet feels unbearable. The symptoms of gout vary in intensity and frequency, but they tend to follow a predictable pattern that can help in early diagnosis and effective management. Gout is caused by the accumulation of uric acid crystals in joints and surrounding tissues. These sharp, needle-like crystals provoke a powerful inflammatory response, leading to the characteristic pain and swelling associated with a gout attack. Understanding the full range of symptoms is essential for distinguishing gout from other forms of arthritis and for initiating timely treatment. Classic Presentation of Gout The most recognisable symptom of gout is the sudden onset of intense joint pain, which often: Begins at night or in the early morning Affects one joint at a time (monoarticular), most often the big toe (a condition known as podagra) Is accompanied by redness, swelling, warmth, and extreme tenderness This pain typically peaks within 6–24 hours, with some attacks lasting up to 10 days. The joint may return to normal between episodes, especially in early stages of the disease. Commonly Affected Joints Although gout most often affects the big toe, other joints are frequently involved, particularly during repeated attacks. These include: Ankles Knees Elbows Wrists Fingers Midfoot joints Over time, if gout is not properly managed, it may affect multiple joints simultaneously, a condition known as polyarticular gout. Redness, Swelling, and Heat During an acute attack, the joint often becomes visibly inflamed: The skin may appear shiny, red, or purplish The joint is hot to the touch Swelling is usually pronounced and may extend beyond the joint itself Some people report peeling or scaling of the skin over the affected area once the flare resolves. Lingering Discomfort After the most intense phase of a gout flare subsides, many individuals experience lingering symptoms: Joint stiffness Low-grade discomfort or tenderness Reduced range of motion These residual effects can last for several days or even weeks, depending on the severity of the attack and whether treatment was initiated. Chronic Gout and Tophaceous Deposits In chronic or poorly managed cases, gout may evolve into a more advanced stage: Tophi: Firm, chalky nodules composed of uric acid crystals that form beneath the skin Common locations include fingers, elbows, knees, toes, and the ears These deposits can become infected, ulcerate, or interfere with joint function Tophaceous gout indicates long-standing disease and often results in joint deformity and permanent damage. Kidney and Urinary Symptoms While not always apparent, symptoms related to kidney involvement may also be present: Back or flank pain, due to kidney stones Frequent urination or urgency Blood in urine (haematuria) Cloudy or foul-smelling urine Gout increases the risk of uric acid kidney stones, which may pass unnoticed or cause severe pain if obstructing urine flow. General Systemic Symptoms Although rare, severe gout flares can trigger systemic symptoms, especially in people with widespread joint involvement or underlying health conditions. These may include: Fever Chills Fatigue or malaise Loss of appetite These symptoms can mimic infection or other inflammatory conditions, which is why proper diagnosis is crucial. Gout in Women While men are more commonly affected, women—especially after menopause—may also develop gout. In women, symptoms may be: More likely to involve joints in the hands or knees Initially less intense but become more severe with time Less likely to present with classic podagra Because women often present atypically, gout may be underdiagnosed or misdiagnosed in female patients. Triggers of Gout Symptoms Several factors may provoke or worsen gout symptoms: Alcohol consumption, especially beer and spirits High-purine foods, such as red meat or seafood Dehydration, leading to higher uric acid concentration Sudden weight loss or fasting Injury or recent surgery, particularly joint trauma Illness or fever, which alters metabolism Avoiding known triggers is a key part of long-term gout management. Early Signs to Watch For Before an acute flare, some people experience warning signs, including: Mild discomfort or tingling in the joint Stiffness that resolves with movement Feeling of fullness or pressure Recognising these early signs allows for prompt treatment, which can reduce the duration and intensity of a flare. Conclusion | Symptoms of Gout The symptoms of gout can range from a sudden, excruciating joint flare to chronic pain and deformity. Recognising these symptoms—especially in the early stages—allows for timely diagnosis and intervention, helping to prevent long-term joint damage. Understanding the full spectrum of symptoms of gout also empowers individuals to manage the condition proactively and avoid known triggers. [Next: Diagnosis of Gout →]

Symptoms of Gout Read More »

Doctor examining inflamed foot for gout diagnosis

Diagnosis of Gout

Diagnosis of Gout The diagnosis of gout is primarily clinical but can be confirmed with laboratory tests and imaging when necessary. Early and accurate diagnosis of gout is critical for initiating appropriate treatment, managing flare-ups, and preventing joint and kidney complications. Because the symptoms can mimic other types of arthritis, such as rheumatoid arthritis or septic arthritis, a thorough evaluation is essential. Gout occurs due to the deposition of uric acid crystals in joints and tissues, triggered by high levels of uric acid in the bloodstream. Identifying these crystals or the conditions that lead to their formation helps differentiate gout from similar conditions and informs long-term management strategies. Clinical Evaluation The first step in diagnosing gout involves a comprehensive history and physical examination. Key questions include: When did the symptoms begin? Is the pain intermittent or persistent? Are specific triggers (food, alcohol, injury) involved? Is there a family history of gout or kidney disease? During the physical exam, clinicians assess: Joint redness, swelling, and tenderness Presence of tophi (chalky nodules under the skin) Range of motion in affected joints The combination of sudden joint pain, swelling, warmth, and rapid onset—especially in the big toe—is highly suggestive of gout. Joint Fluid Analysis The gold standard for confirming gout is joint aspiration: A small needle is used to extract synovial fluid from the inflamed joint The fluid is examined under a polarised light microscope Needle-shaped, negatively birefringent uric acid crystals confirm the diagnosis This test is especially important when the diagnosis is uncertain, or if septic arthritis is a possible alternative. Blood Tests Several blood tests support the diagnosis: Serum uric acid levels: Elevated levels (>6.8 mg/dL or >400 µmol/L) suggest gout but may be normal during an acute attack C-reactive protein (CRP) and erythrocyte sedimentation rate (ESR): Markers of inflammation White blood cell count: May be elevated during flares Kidney function tests, including creatinine and eGFR, to assess uric acid clearance Repeated testing is often needed, as levels can fluctuate based on hydration, diet, and medication use. Imaging When joint aspiration is not feasible or gout has progressed to chronic stages, imaging can be helpful. X-rays May show joint erosion, particularly in chronic or tophaceous gout Limited in early-stage disease Ultrasound Can detect urate crystal deposits Shows the “double contour sign,” indicating crystal coating on cartilage Useful for visualising tophi and guiding joint aspiration Dual-energy CT (DECT) Highly sensitive in detecting urate crystals Useful in atypical or difficult-to-diagnose cases Not widely available in all healthcare settings Differential Diagnosis Gout can resemble several other conditions: Septic arthritis (joint infection): Requires urgent antibiotic treatment Pseudogout: Caused by calcium pyrophosphate crystals Rheumatoid arthritis: Usually involves multiple joints symmetrically Reactive arthritis: Associated with prior infection Joint fluid analysis and imaging help distinguish gout from these mimics. Gout in Women and Elderly In postmenopausal women and older adults: Symptoms may be less typical Flare-ups may involve knees or hands rather than toes Other forms of arthritis may coexist, complicating diagnosis This group often requires more detailed testing to confirm gout. When to Refer Referral to a rheumatologist is advised when: The diagnosis is uncertain Gout is resistant to standard therapies There are multiple or complex comorbidities Advanced joint damage or tophaceous deposits are present Specialist input may also be necessary for long-term urate-lowering therapy management. Conclusion | Diagnosis of Gout The diagnosis of gout is based on clinical presentation, supported by synovial fluid analysis, blood tests, and imaging when needed. An accurate diagnosis of gout allows for appropriate treatment, helps rule out more serious conditions like infection, and sets the stage for long-term management to prevent flares and joint damage. Early diagnosis not only improves outcomes but also reduces the likelihood of chronic disability. [Next: Treatment of Gout→]

Diagnosis of Gout Read More »

NSAID capsule used in the treatment of gout symptoms and inflammation

Treatment of Gout

Treatment of Gout The treatment of gout aims to relieve the pain of acute attacks, prevent future flare-ups, and reduce long-term uric acid levels to prevent joint and kidney damage. Because gout is a chronic condition driven by elevated uric acid, the treatment of gout must address both immediate symptoms and the underlying metabolic cause. A combination of medication, dietary changes, and long-term monitoring is typically required for successful management. Gout is one of the few forms of arthritis that is both preventable and curable with appropriate treatment. The challenge lies in timely diagnosis, patient adherence, and adjustment of therapy based on evolving needs. Immediate Relief During an Acute Attack When a gout flare occurs, the focus is on rapid relief of inflammation and pain. First-line therapies include: 1. Non-Steroidal Anti-Inflammatory Drugs (NSAIDs) Drugs such as naproxen, ibuprofen, or indometacin are commonly prescribed Most effective when taken at the onset of symptoms Should be continued for a few days after symptoms resolve to prevent recurrence Patients with kidney disease or gastrointestinal issues may require alternative options. 2. Colchicine Especially effective in the early hours of an attack Slows down inflammation by affecting white blood cell activity Can cause side effects like diarrhoea or nausea if taken in high doses Modern dosing strategies use lower doses to reduce these side effects 3. Corticosteroids Used when NSAIDs or colchicine are contraindicated Can be administered orally (e.g. prednisolone) or injected directly into the affected joint Rapidly reduces inflammation but may affect blood sugar levels or immune function For severe attacks, a combination of two anti-inflammatory treatments may be needed. Lifestyle Changes to Prevent Flares In addition to medication, lifestyle modifications play a crucial role in preventing further gout attacks. Recommendations include: Limiting purine-rich foods, such as red meat, shellfish, and organ meats Reducing alcohol intake, especially beer and spirits Avoiding sugary drinks and foods high in fructose Increasing fluid intake to support kidney function Maintaining a healthy body weight to lower uric acid levels Exercising regularly, though avoiding strenuous activity during a flare A registered dietitian can provide individualised advice tailored to comorbidities like diabetes or heart disease. Long-Term Uric Acid Control Once the acute phase is resolved, long-term management aims to lower serum uric acid levels below target thresholds—typically <360 μmol/L (6 mg/dL) or <300 μmol/L (5 mg/dL) in severe or tophaceous gout. 1. Urate-Lowering Therapy (ULT) This is recommended for: Individuals with recurrent gout flares (≥2 per year) Presence of tophi Joint damage on imaging Coexisting chronic kidney disease or kidney stones The two main classes of ULT include: a. Xanthine Oxidase Inhibitors Allopurinol: First-line treatment; reduces uric acid production Febuxostat: An alternative for those intolerant to allopurinol Dosing starts low and increases gradually to minimise the risk of flares. b. Uricosurics Increase uric acid excretion by the kidneys Less commonly used due to risk of kidney stones Examples: probenecid, benzbromarone (not available in all countries) ULT is a lifelong commitment in most cases, as stopping it can lead to flare recurrence. Bridging and Monitoring Initiating ULT may temporarily trigger gout flares. To prevent this, doctors often prescribe colchicine or NSAIDs as bridging therapy for the first 3–6 months. Ongoing monitoring includes: Regular serum uric acid checks Evaluation of kidney and liver function Monitoring for drug side effects, including skin rashes, gastrointestinal upset, or liver abnormalities Close follow-up is essential during the first year of treatment. Role of Patient Education Patients who understand their condition are more likely to manage it effectively. Education should cover: The chronic nature of gout Importance of adherence to daily urate-lowering therapy Identifying early signs of a flare Managing dietary and lifestyle triggers The difference between flare treatment and preventive medications Support from pharmacists, dietitians, and nurses reinforces key messages. Alternative and Adjunctive Therapies While evidence is limited, some adjunctive options may support traditional therapy: Vitamin C: May lower uric acid slightly in some individuals Cherries or cherry juice: Anecdotal reports suggest benefit, but more studies are needed Coffee: Some observational studies link moderate consumption to reduced gout risk However, these should not replace medication or formal care. Conclusion | Treatment of Gout The treatment of gout involves more than just managing painful attacks—it requires long-term commitment to reducing uric acid and modifying lifestyle factors. With a tailored approach combining medication, education, and dietary changes, most patients can experience complete resolution of symptoms. Early and sustained treatment of gout prevents complications, enhances quality of life, and ensures long-term joint health. [Next: Complications of Gout →]

Treatment of Gout Read More »

Scroll to Top