Mental Matters

Author name: admin

Person holding lower back in pain, indicating kidney-related complications of glomerulonephritis

Complications of Glomerulonephritis

Complications of Glomerulonephritis The complications of glomerulonephritis can be serious, particularly when diagnosis is delayed or treatment is inadequate. While many cases resolve with minimal long-term damage, others lead to chronic kidney disease, systemic complications, or even kidney failure. Identifying the complications of glomerulonephritis early can prevent life-altering consequences and improve long-term outcomes. These complications arise as a result of ongoing inflammation, immune dysfunction, or scarring in the kidneys. The severity and likelihood of complications depend on the type of glomerulonephritis, the underlying cause, and how promptly it is managed. 1. Chronic Kidney Disease (CKD) One of the most common long-term outcomes of glomerulonephritis is chronic kidney disease. Repeated inflammation or ongoing damage to the glomeruli can lead to: Gradual decline in kidney function Increased serum creatinine and reduced GFR Accumulation of waste products in the blood CKD develops in stages and may remain stable for years if well managed. However, without appropriate treatment, it may eventually progress to kidney failure. 2. End-Stage Renal Disease (ESRD) If glomerular damage continues unchecked, end-stage renal disease can occur. This is the most severe complication and requires: Dialysis, either haemodialysis or peritoneal dialysis, to perform the kidney’s filtering role Kidney transplantation, when suitable ESRD significantly affects quality of life and life expectancy. It is more common in chronic or severe cases of glomerulonephritis, particularly those resistant to treatment. 3. Nephrotic Syndrome Several forms of glomerulonephritis can lead to nephrotic syndrome, a condition marked by: Severe proteinuria Low blood albumin levels Generalised oedema High cholesterol and blood lipid levels Nephrotic syndrome increases the risk of: Blood clots (venous thromboembolism) Infections, due to loss of immunoglobulins Malnutrition, if protein loss is significant Early and aggressive treatment can reverse nephrotic syndrome in many cases. 4. Hypertension (High Blood Pressure) Inflamed or scarred kidneys struggle to regulate fluid and salt, leading to high blood pressure, which in turn accelerates glomerular damage. Complications of uncontrolled hypertension include: Heart disease Stroke Vision loss Further kidney damage Managing blood pressure is essential to prevent worsening of glomerulonephritis. 5. Electrolyte and Metabolic Imbalances Advanced glomerular disease can disrupt electrolyte levels and cause: Hyperkalaemia (high potassium), increasing the risk of cardiac arrhythmias Metabolic acidosis, leading to fatigue and bone loss Calcium and phosphate imbalances, which contribute to bone disease These imbalances require close monitoring and may need specific medications or dietary adjustments. 6. Anaemia Reduced kidney function impairs the production of erythropoietin, a hormone required for red blood cell production. This can lead to: Chronic anaemia Fatigue, weakness, and reduced concentration Anaemia of chronic disease is common in later stages and often requires iron supplementation or erythropoiesis-stimulating agents. 7. Cardiovascular Disease Glomerulonephritis increases the risk of heart disease through several mechanisms: Hypertension High cholesterol (especially in nephrotic syndrome) Inflammation and oxidative stress Anaemia, which increases cardiac strain Cardiovascular events are a leading cause of death in people with chronic kidney disease, making prevention vital. 8. Psychological and Quality-of-Life Impacts Living with chronic illness can result in: Depression or anxiety Loss of independence Work or school disruptions Financial strain due to medical costs Early referral to counselling services, social workers, and patient support groups can help mitigate these challenges. Summary of Common Complications Complication Impact Chronic kidney disease Gradual loss of kidney function Kidney failure (ESRD) Requires dialysis or transplant Nephrotic syndrome Severe protein loss and immune risk Hypertension Heart disease, stroke, kidney damage Electrolyte imbalances Bone, heart, and muscle complications Anaemia Fatigue, reduced productivity Cardiovascular disease Increased mortality risk Mental health challenges Depression, anxiety, social impact Conclusion | Complications of Glomerulonephritis The complications of glomerulonephritis can range from manageable metabolic issues to life-threatening kidney failure. However, with early detection, appropriate treatment, and regular follow-up, many of these complications can be avoided or delayed. Addressing the complications of glomerulonephritis proactively not only protects kidney health but also improves overall quality of life and long-term outcomes. [Next: Back to Overview →]

Complications of Glomerulonephritis Read More »

Glaucoma

Glaucoma

Glaucoma Glaucoma is a group of eye conditions that damage the optic nerve, often due to abnormally high pressure inside the eye. Left untreated, glaucoma can lead to irreversible vision loss or even total blindness. It is one of the leading causes of preventable blindness worldwide, particularly among people over the age of 60. However, early diagnosis and proper treatment can preserve sight and significantly slow progression. The disease is typically painless in its early stages, which makes it particularly dangerous. Many people do not realise they have glaucoma until permanent damage has already occurred. Because of this, regular eye tests—especially after the age of 40—are vital to detect the condition before symptoms become apparent. What Is Glaucoma? Glaucoma refers to a family of eye diseases that share a common characteristic: progressive damage to the optic nerve, which connects the eye to the brain and is responsible for transmitting visual signals. Damage to the nerve impairs peripheral vision initially and can eventually affect central vision. In many cases, the damage is associated with elevated intraocular pressure (IOP), which results from a build-up of aqueous humour—the fluid inside the front part of the eye. When this fluid does not drain properly, pressure increases and damages the nerve fibres in the optic nerve. However, not all glaucoma patients have high eye pressure. In normal-tension glaucoma, optic nerve damage occurs despite IOP being within the normal range, likely due to poor blood flow or other risk factors. Types of Glaucoma There are several different forms of this condition, each with its own causes and characteristics: 1. Primary Open-Angle Glaucoma The most common type worldwide Caused by slow clogging of the eye’s drainage canals Develops gradually and often without symptoms Peripheral vision is affected first 2. Angle-Closure Glaucoma (Acute Glaucoma) Less common but more dangerous Occurs when the iris bulges forward and blocks the drainage angle Sudden increase in IOP leads to eye pain, redness, headache, and blurred vision A medical emergency that requires immediate treatment 3. Normal-Tension Glaucoma Optic nerve damage occurs despite normal IOP levels Risk factors include poor circulation, migraines, and vascular conditions 4. Congenital Glaucoma Present at birth due to developmental defects in the eye Symptoms include clouded cornea, enlarged eyes, and excessive tearing Requires surgery and lifelong monitoring 5. Secondary Glaucoma Caused by an underlying condition such as eye injury, inflammation, steroids, or diabetes Can mimic open-angle or angle-closure types Risk Factors Certain factors increase the risk of developing this condition: Age over 60 Family history of this condition African, Asian, or Hispanic ancestry High eye pressure (IOP) Thin corneas Diabetes or hypertension Prolonged use of corticosteroids Eye injuries or surgery history Because many of these risk factors are silent, routine eye screening is the most effective way to catch glaucoma early. Symptoms In its early stages, this conditionoften has no noticeable symptoms. This is why it is often called the “silent thief of sight.” In Primary Open-Angle Glaucoma: Vision loss begins at the edges of visual field May go unnoticed until significant peripheral vision is lost Gradually progresses to central vision if untreated In Acute Angle-Closure Glaucoma: Sudden onset of severe eye pain Redness, haloes around lights, and blurred vision Nausea and vomiting Requires immediate medical intervention to prevent permanent blindness How Glaucoma Is Diagnosed Routine eye exams include several tests to detect this condition, such as: Tonometry: Measures eye pressure Ophthalmoscopy: Examines the optic nerve Visual field testing: Detects peripheral vision loss Pachymetry: Measures corneal thickness Gonioscopy: Checks the drainage angle Most people are diagnosed during routine check-ups, underscoring the importance of regular eye care, especially in those with risk factors. Prevention and Screening While glaucoma cannot always be prevented, its progression can be significantly delayed. Prevention strategies include: Regular eye exams: Every 2 years for those over 40; annually if at risk Managing diabetes and blood pressure Protecting eyes from injury Avoiding prolonged steroid use unless medically necessary Early detection remains the most powerful tool in preserving vision. The Impact of Untreated Glaucoma If glaucoma is not diagnosed or managed, it can lead to: Permanent vision loss Blindness Reduced independence and quality of life Vision lost to glaucoma cannot be restored, which is why timely diagnosis and ongoing treatment are essential. Living with Glaucoma With proper care, most people with this condition retain good vision throughout life. Key to this is: Adherence to medication Routine follow-up with an ophthalmologist Reporting any new vision changes promptly Understanding glaucoma empowers individuals to seek appropriate care, protect their sight, and lead full, independent lives. [Next: Causes of Glaucoma →]

Glaucoma Read More »

Causes of Glaucoma

Causes of Glaucoma

Causes of Glaucoma The causes of glaucoma vary depending on the specific type of the condition. At its core, glaucoma is linked to damage of the optic nerve, often—but not always—caused by elevated intraocular pressure. Understanding what leads to increased pressure, as well as what can damage the optic nerve in normal-tension cases, is key to recognising risks and preventing sight loss. Although many factors contribute to the development of glaucoma, most involve the build-up of fluid in the eye, poor drainage, or damage from compromised blood supply. Genetics and systemic health conditions also play significant roles. Eye Fluid Dynamics The eye continuously produces a fluid called aqueous humour, which: Nourishes the eye tissues Maintains proper pressure inside the eye Drains through the trabecular meshwork at the drainage angle between the iris and cornea When this drainage system becomes blocked or inefficient, fluid builds up, leading to: Increased intraocular pressure (IOP) Compression of the optic nerve fibres Gradual death of nerve cells responsible for vision This process is central to primary open-angle glaucoma, the most common form of the disease. Causes of Different Types of Glaucoma 1. Primary Open-Angle Glaucoma This is usually caused by: Age-related changes in the eye’s drainage system Resistance to fluid outflow, even though the angle is open Genetic mutations affecting pressure regulation While eye pressure increases slowly, it eventually reaches a level that damages the optic nerve. Some people with high eye pressure never develop nerve damage, while others with normal pressure can develop glaucoma. 2. Angle-Closure Glaucoma This occurs when: The iris bulges forward, narrowing or blocking the drainage angle Fluid builds up rapidly, causing a sudden spike in IOP The eye cannot drain fluid quickly enough, creating acute symptoms Common triggers include: Pupil dilation in low light Certain medications Hyperopia (farsightedness), which can alter eye anatomy This type is more common in women, older adults, and people of Asian descent. 3. Normal-Tension Glaucoma In these cases, optic nerve damage occurs despite normal eye pressure. Possible causes include: Poor blood flow to the optic nerve Vascular conditions like low blood pressure or Raynaud’s disease Genetic factors Structural vulnerability of the optic nerve This form is more common in people of Japanese ancestry and those with a family history of glaucoma. 4. Congenital Glaucoma This rare form occurs in infants and young children. Causes include: Malformation of the drainage system during development Genetic defects affecting eye growth Inherited mutations passed from parents Early surgical treatment is often required to preserve vision. 5. Secondary Glaucoma Secondary glaucoma results from another condition that interferes with fluid drainage or increases pressure. Causes include: Eye trauma or surgery Inflammatory eye diseases (e.g. uveitis) Steroid medications Diabetes, which can cause neovascular glaucoma Tumours or lens dislocation Managing the underlying condition is essential for treating this form of glaucoma. Genetic and Family Factors Genetics play a significant role in all types of glaucoma. Those with a family history—especially first-degree relatives—are at four to nine times greater risk of developing the disease. Specific genes linked to glaucoma include: MYOC – associated with juvenile open-angle glaucoma OPTN and TBK1 – linked to normal-tension glaucoma CYP1B1 – associated with congenital glaucoma Because of the genetic link, screening and early testing are advised for relatives of diagnosed patients. Systemic Conditions That Increase Risk Certain systemic illnesses and lifestyle factors can contribute to glaucoma: Diabetes mellitus Hypertension or hypotension Obstructive sleep apnoea Migraine Use of steroids (oral, inhaled, or topical) Smoking and poor cardiovascular health These conditions may either raise eye pressure or reduce blood supply to the optic nerve. Environmental and Behavioural Factors While less clearly established, other potential contributors include: Chronic eye strain Low oxygen levels at high altitudes Excessive caffeine intake, which may raise IOP temporarily Prolonged stress, affecting vascular tone Though not direct causes, these factors may compound risk in already susceptible individuals. Summary of Main Causes Glaucoma Type Primary Cause Open-Angle Slow fluid drainage, age, genetics Angle-Closure Iris position, anatomy, sudden blockage Normal-Tension Poor blood flow, nerve vulnerability Congenital Developmental defects, genetic mutation Secondary Trauma, inflammation, medications Conclusion | Causes of Glaucoma The causes of glaucoma are diverse and often interrelated. Elevated eye pressure, poor fluid drainage, genetic predisposition, and vascular problems all contribute to the development of this sight-threatening condition. Identifying risk factors early and understanding the underlying mechanisms allows for better prevention, early diagnosis, and timely treatment. [Next: Symptoms of Glaucoma→]

Causes of Glaucoma Read More »

Symptoms of Glaucoma

Symptoms of Glaucoma

Symptoms of Glaucoma The symptoms of glaucoma depend on the type and stage of the disease. In its early stages, glaucoma is often silent and symptomless, which is why it is commonly referred to as the “silent thief of sight.” Many people do not realise they have the condition until irreversible damage to their vision has already occurred. Recognising the different symptom patterns between the various types of glaucoma is crucial for timely diagnosis and prevention of vision loss. In most cases, symptoms progress gradually, affecting peripheral vision first. However, certain types—such as acute angle-closure glaucoma—can cause rapid, painful symptoms that require emergency intervention. Understanding what to look out for, even in the absence of discomfort, empowers individuals to protect their eyesight through regular screenings and prompt action. Symptoms of Primary Open-Angle Glaucoma This is the most common form of glaucoma globally, accounting for approximately 70–90% of cases. It progresses slowly and often goes unnoticed for years. Typical symptoms include: Gradual loss of peripheral (side) vision Tunnel vision in advanced stages Difficulty adjusting to low light or glare Blurred vision in the late stages Because central vision remains intact until the disease is advanced, many people do not realise their peripheral vision is deteriorating. By the time vision loss is noticed, substantial and irreversible optic nerve damage may have already occurred. Symptoms of Acute Angle-Closure Glaucoma This type presents suddenly and requires urgent treatment to prevent permanent vision loss. It is less common but far more dramatic in presentation. Common signs and symptoms include: Severe eye pain, often in one eye Redness of the eye Blurry vision or haloes around lights Sudden visual loss Headache, especially on the affected side Nausea and vomiting This occurs when the drainage angle in the eye becomes abruptly blocked, causing a rapid rise in intraocular pressure. If not treated within hours, it can lead to permanent blindness. Anyone experiencing these symptoms should seek emergency medical attention. Symptoms of Normal-Tension Glaucoma Despite normal intraocular pressure, optic nerve damage still occurs in this form of the disease. The symptoms mirror those of open-angle glaucoma but may appear in people without the traditional risk of high eye pressure. These symptoms include: Gradual peripheral vision loss Difficulty seeing in dim light Occasional blurred or distorted vision Because pressure readings may be normal, diagnosis can be delayed unless the optic nerve is thoroughly assessed during routine eye exams. Symptoms of Secondary Glaucoma Secondary glaucoma arises from other medical conditions, eye injuries, or medications. Symptoms vary depending on the underlying cause but may include: Blurred vision Eye pain or redness Increased sensitivity to light Visual disturbances related to inflammation, trauma, or cataract complications Sometimes the symptoms of the primary condition—such as uveitis or steroid-induced IOP elevation—overshadow the signs of glaucoma, making early detection more challenging. Symptoms in Congenital Glaucoma This rare form affects newborns and infants. The signs may include: Cloudy cornea Excessive tearing (epiphora) Enlarged eyes (buphthalmos) Light sensitivity (photophobia) Failure to thrive due to discomfort Parents often notice that their infant has unusually large, shiny eyes. Prompt referral to a paediatric ophthalmologist is essential to prevent lifelong visual impairment. Vision Loss Pattern in Glaucoma Glaucoma typically affects peripheral vision first. As the disease progresses: Vision loss extends towards the centre Blind spots develop in the visual field Tunnel vision becomes more pronounced In the final stages, central vision is lost, potentially leading to complete blindness Because this pattern of vision loss is painless and slow, people may adapt unconsciously—turning their heads more often or relying on the unaffected eye—without realising the extent of the damage. Psychological and Functional Symptoms As vision deteriorates, people with glaucoma may experience: Difficulty reading or driving Reduced mobility, especially in unfamiliar environments Increased risk of falls or collisions Anxiety, frustration, or depression due to declining independence While vision cannot be restored, timely treatment can preserve what remains and slow the progression of symptoms. Summary of Symptoms by Type Type of Glaucoma Key Symptoms Open-angle Slow peripheral vision loss, tunnel vision Angle-closure Sudden pain, haloes, blurred vision, nausea Normal-tension Vision loss with normal IOP, often unnoticed Secondary Depends on underlying condition (pain, redness) Congenital Cloudy eyes, tearing, light sensitivity in infants Conclusion | Symptoms of Glaucoma The symptoms of glaucoma range from subtle and progressive to sudden and severe, depending on the type. Because early stages are often asymptomatic, regular eye examinations are essential—especially for those at increased risk. Early detection offers the best chance of preserving vision and maintaining quality of life. [Next: Diagnosis of Glaucoma →]

Symptoms of Glaucoma Read More »

Diagnosis of Glaucoma

Diagnosis of Glaucoma

Diagnosis of Glaucoma The diagnosis of glaucoma relies on a thorough clinical evaluation, including eye pressure measurement, optic nerve examination, and visual field testing. Since glaucoma often develops without early symptoms, routine eye checks are the only way to detect the condition before irreversible damage occurs. A timely diagnosis enables early treatment that can preserve vision and slow disease progression. Modern diagnostic methods make it possible to detect glaucoma years before a patient notices any vision changes. The key is combining several tests to build a complete picture of eye health. Comprehensive Eye Examination A standard glaucoma assessment includes: Patient history: Risk factors such as family history, diabetes, steroid use, or ethnicity Visual acuity test: Measures how well a person can see at different distances Slit-lamp examination: Assesses the front of the eye for inflammation, damage, or abnormalities These initial steps guide whether further glaucoma-specific testing is required. Tonometry: Measuring Eye Pressure Tonometry measures intraocular pressure (IOP), which is one of the most important indicators of glaucoma. Elevated pressure suggests a higher risk, though not all glaucoma patients have high readings. There are several types of tonometry: Applanation tonometry: Gold standard, uses a device that gently flattens the cornea Non-contact tonometry (puff test): Uses a brief burst of air Rebound tonometry: Portable and often used for children or home monitoring Normal IOP ranges between 10–21 mmHg, but glaucoma can occur at lower or higher values depending on other factors. Ophthalmoscopy: Examining the Optic Nerve Using a special lens and microscope, the doctor examines the optic disc at the back of the eye. Features suggestive of glaucoma include: Cupping of the optic nerve Thinning of the neuroretinal rim Asymmetry between the two eyes Progressive cupping is a sign of optic nerve damage, often visualised in sequential photos or scans. Visual Field Testing This is a key test to detect functional vision loss: Uses perimetry machines to map out the person’s peripheral vision Patients press a button when they see a light spot in various locations Results show areas of reduced sensitivity or blind spots In glaucoma, visual field loss often starts in the nasal periphery and progresses slowly. Optical Coherence Tomography (OCT) OCT is an advanced imaging technique that provides cross-sectional images of the retina and optic nerve. It helps measure: Thickness of the retinal nerve fibre layer (RNFL) Changes over time, even before functional loss is apparent OCT is especially useful for diagnosing early glaucoma and monitoring disease progression. Gonioscopy: Assessing the Drainage Angle This test evaluates whether the drainage angle between the cornea and iris is open or blocked. It helps distinguish: Open-angle glaucoma Angle-closure glaucoma A special lens is placed on the eye to allow visualisation of the angle. It is particularly important when acute angle-closure glaucoma is suspected. Pachymetry: Measuring Corneal Thickness Central corneal thickness affects IOP readings and is an independent risk factor for glaucoma. Thinner corneas: May lead to underestimation of IOP Are associated with higher risk of optic nerve damage Pachymetry is a quick, painless test using ultrasound or optical methods. Differential Diagnosis Other conditions can mimic glaucoma, such as: Optic neuritis Ischaemic optic neuropathy Compressive lesions (e.g. tumours) Retinal diseases A comprehensive examination helps rule out these alternatives and confirm a glaucoma diagnosis. Screening and Follow-Up Routine screening is recommended for: All adults over 40, every 2 years People with risk factors, annually Children with family history of congenital glaucoma, as advised by specialists Once diagnosed, glaucoma patients require: Lifelong monitoring Regular visual field and OCT testing Adjustments to treatment based on progression Importance of Early Diagnosis Early detection can: Prevent significant vision loss Reduce reliance on more invasive treatments Maintain independence and quality of life Because damage is irreversible, diagnosis must occur before symptoms develop—another reason why eye pressure alone is not enough to rule out glaucoma. Conclusion | Diagnosis of Glaucoma The diagnosis of glaucoma requires a combination of clinical observation, pressure measurement, imaging, and functional testing. With early detection and regular monitoring, patients can preserve their vision and manage the condition effectively for life. [Next: Treatment of Glaucoma→]

Diagnosis of Glaucoma Read More »

Treatment of Glaucoma

Treatment of Glaucoma

Treatment of Glaucoma The treatment of glaucoma focuses on lowering intraocular pressure (IOP) to prevent or slow further damage to the optic nerve. Since glaucoma can cause irreversible vision loss, the goal of treatment is to preserve the remaining sight rather than restore what has already been lost. The good news is that, with timely and consistent management, most people with glaucoma can retain useful vision throughout their lives. There is no cure for glaucoma, but several effective treatment options exist. These include medicated eye drops, laser therapy, surgical procedures, and lifestyle adjustments. The appropriate treatment depends on the type of glaucoma, its severity, and how the individual responds to initial therapies. Eye Drops: First-Line Treatment In most cases, the first step in treating glaucoma involves prescription eye drops that help lower intraocular pressure. These drops either reduce the amount of fluid produced in the eye or improve fluid drainage. The main classes of eye drops include: 1. Prostaglandin Analogues Increase fluid outflow Typically used once daily Examples: latanoprost, bimatoprost Side effects: eye redness, longer eyelashes, iris darkening 2. Beta Blockers Reduce fluid production Used once or twice a day Examples: timolol, betaxolol Side effects: fatigue, low heart rate, possible breathing issues 3. Alpha Agonists Decrease fluid production and increase outflow Examples: brimonidine Side effects: dry mouth, fatigue, allergic reactions 4. Carbonic Anhydrase Inhibitors Reduce fluid production Available in drops or oral form Examples: dorzolamide, acetazolamide Side effects: stinging, taste changes 5. Rho Kinase Inhibitors Enhance drainage through the trabecular meshwork Used alone or in combination with other drops Adherence is critical. Skipping doses or improper application can lead to increased pressure and optic nerve damage. Patients should receive instruction on how to use drops correctly and understand the importance of long-term commitment to therapy. Laser Treatments Laser therapy is often used when drops are ineffective, poorly tolerated, or not suitable for long-term use. It can also serve as an early treatment option, especially in angle-closure glaucoma. 1. Selective Laser Trabeculoplasty (SLT) Used primarily for open-angle glaucoma Targets the drainage tissue to improve fluid outflow Quick and painless outpatient procedure Effects last 1–5 years, and the procedure can be repeated 2. Laser Peripheral Iridotomy Performed for angle-closure glaucoma Creates a small hole in the iris to relieve pressure Prevents future acute attacks in the other eye 3. Cyclodiode Laser Used in advanced or refractory glaucoma Reduces fluid production by targeting the ciliary body Reserved for severe or end-stage cases Laser treatments are typically low-risk and can reduce or eliminate the need for daily eye drops. Surgical Treatments Surgery is considered when medications and laser treatments are not sufficient to control IOP. 1. Trabeculectomy Creates a new drainage channel for fluid to exit the eye Performed in an operating theatre under local anaesthesia Reduces IOP significantly and may reduce or eliminate the need for drops Risks: infection, bleeding, scarring, vision changes 2. Tube Shunt Surgery Involves placing a small tube and plate to redirect fluid Used when trabeculectomy fails or is unsuitable Effective in complex or secondary glaucoma cases 3. Minimally Invasive Glaucoma Surgery (MIGS) A newer class of procedures Less invasive with quicker recovery Examples: iStent, Hydrus Microstent, Kahook Dual Blade Often performed alongside cataract surgery MIGS procedures are particularly suitable for patients with mild to moderate glaucoma. Managing Angle-Closure Glaucoma In acute cases, emergency treatment includes: Eye drops and medications to quickly lower IOP Laser iridotomy to relieve pressure and prevent recurrence Surgical removal of the lens if the attack recurs or vision is compromised Prompt treatment is vital to preserve vision. Lifestyle and Home Management While medical treatments are essential, lifestyle also plays a supporting role: Take medication consistently and attend follow-up appointments Protect eyes from injury and limit exposure to pressure-increasing activities Exercise regularly, but avoid straining or head-down positions in advanced cases Manage systemic conditions like diabetes and high blood pressure Avoid excessive caffeine, which may transiently raise IOP Quitting smoking and eating a nutrient-rich diet also support eye and overall health. Monitoring Progress Once treatment begins, regular monitoring includes: IOP measurements Visual field testing OCT scans of the optic nerve Eye structure assessments Treatment may need to be adjusted over time depending on response and disease progression. Conclusion | Treatment of Glaucoma The treatment of glaucoma is multifaceted and lifelong. With a combination of medication, laser procedures, and surgery where needed, many patients maintain stable vision for decades. Early intervention, consistent follow-up, and patient education remain the pillars of effective glaucoma management. [Next: Complications of Glaucoma →]

Treatment of Glaucoma Read More »

Complications of Glaucoma

Complications of Glaucoma

Complications of Glaucoma The complications of glaucoma can range from mild side effects of treatment to severe vision loss and blindness. Because glaucoma damages the optic nerve gradually and without warning, failure to diagnose or manage it effectively can lead to irreversible harm. While many people with glaucoma live full and independent lives, complications arise when the disease progresses unchecked or when treatment is poorly tolerated. Understanding the potential complications helps patients recognise warning signs early and empowers them to take an active role in their eye health. 1. Vision Loss The most serious and feared complication of glaucoma is permanent vision loss. This occurs when: The optic nerve sustains prolonged pressure damage The retinal ganglion cells die off Visual signals no longer reach the brain effectively In open-angle glaucoma, vision loss: Begins in the peripheral field Progresses slowly over years Becomes noticeable only after significant damage has occurred In angle-closure glaucoma: Vision can deteriorate rapidly Central vision may be affected early if untreated Permanent blindness may result from a single acute episode 2. Blindness Glaucoma is one of the leading causes of irreversible blindness worldwide. This occurs when: The entire optic nerve is compromised Both central and peripheral vision are lost Treatment fails or is delayed Blindness from glaucoma: Is permanent—vision cannot be restored May be complete or partial (legal blindness) Often leads to profound lifestyle and psychological impacts Regular monitoring and timely treatment can almost always prevent this outcome. 3. Side Effects of Medications Eye drops and oral medications used to control intraocular pressure may cause: Local side effects: Red, itchy, or dry eyes Blurred vision after drop instillation Eyelash growth or iris colour changes (with prostaglandins) Systemic side effects: Low blood pressure or heart rate (beta-blockers) Fatigue or dizziness Taste changes or dry mouth Frequent urination or tingling (carbonic anhydrase inhibitors) Adherence may be compromised if side effects are not managed. Switching medications or adjusting dosages can help. 4. Surgical Complications While surgery is often effective, it carries risks, including: Infection (endophthalmitis) Bleeding inside the eye (hyphema) Scarring that blocks fluid drainage Over-filtration, leading to very low eye pressure (hypotony) Vision fluctuations or double vision With skilled surgeons and careful post-operative care, the risk of serious complications remains low. 5. Psychological Impact Vision loss, even when mild, can result in: Anxiety about blindness Depression or social withdrawal Reduced independence or confidence Support groups, counselling, and practical vision aids can help mitigate this burden. Addressing emotional wellbeing is just as important as preserving physical sight. 6. Impact on Daily Living As glaucoma progresses, individuals may experience: Difficulty driving, especially at night or in low contrast Trouble navigating stairs or unfamiliar spaces Increased risk of falls or accidents Need for vision aids, magnifiers, or mobility support Even with moderate visual impairment, many adapt successfully using tools like large-print devices, voice-activated technology, and improved lighting. 7. Financial and Healthcare Burden Long-term glaucoma management may result in: Costs for medications, follow-ups, and surgeries Time off work or lifestyle modifications Dependency on caregivers if vision becomes limited Public health systems often provide screening and treatment support, but in underserved regions, the financial and logistical burden remains significant. Summary of Complications Complication Impact Vision loss Irreversible, often unnoticed early Blindness Complete loss of functional sight Medication side effects Eye discomfort, systemic symptoms Surgical complications Rare but potentially serious Psychological effects Anxiety, depression, loss of confidence Functional limitations Reduced independence, falls, driving risk Economic burden Ongoing costs and lifestyle adjustment Conclusion | Complications of Glaucoma The complications of glaucoma highlight the importance of early detection, consistent treatment, and long-term monitoring. While the disease cannot be cured, modern therapies allow most patients to lead full, independent lives. By recognising complications early and responding appropriately, individuals can protect their vision and quality of life. [Next: Back to Overview →]

Complications of Glaucoma Read More »

Man touching his throat with discomfort due to swollen glands

Glandular Fever

Glandular Fever Glandular fever, also known as infectious mononucleosis or simply mono, is a viral illness most commonly caused by the Epstein-Barr virus (EBV). Glandular fever typically affects teenagers and young adults, although it can occur at any age. It spreads primarily through saliva, earning it the informal name “the kissing disease,” though transmission can also happen through coughing, sneezing, or sharing utensils. The condition is usually mild but can be prolonged and exhausting, with symptoms lasting for several weeks. In rare cases, complications can occur, especially if rest and proper care are not observed. Understanding glandular fever helps individuals manage the illness appropriately and avoid spreading the virus to others. What Is Glandular Fever? Glandular fever is a viral infection that triggers a strong immune response, resulting in: Fever Sore throat Swollen lymph nodes Severe fatigue The illness is caused by the Epstein-Barr virus, a member of the herpesvirus family. Once a person contracts EBV, the virus remains in their body for life in a dormant state. In most cases, it does not reactivate or cause further illness. How It Spreads The virus spreads through bodily fluids, particularly saliva. Common ways people catch glandular fever include: Kissing someone infected Sharing drinks, food, straws, or cutlery Being exposed to droplets from coughs or sneezes Contact with contaminated objects (e.g. toothbrushes, lip balm) EBV is highly contagious during the active phase of infection, especially when symptoms are present. However, the virus can be transmitted even before symptoms begin and for months afterward. Who Is at Risk? Glandular fever most commonly affects: Teenagers and young adults aged 15–25 University students or young professionals in close living or social environments People with weakened immune systems, who may experience more severe illness In children under five, infection with EBV usually causes mild or no symptoms, which is why many adults test positive for past exposure without remembering being ill. Common Symptoms The hallmark symptoms of glandular fever usually appear four to six weeks after exposure and include: Fever, often mild to moderate but occasionally high Severe sore throat, sometimes mistaken for bacterial tonsillitis Swollen lymph nodes, especially in the neck and armpits Profound fatigue that can last for weeks Headache Muscle aches Loss of appetite Swollen tonsils, sometimes with white or grey coating Mild rash, especially if the person has taken antibiotics such as ampicillin or amoxicillin Some individuals also experience: Enlarged spleen or liver Abdominal discomfort Nausea or jaundice Fatigue can be debilitating, lingering for several weeks or months even after the main symptoms have resolved. Incubation and Duration After infection, there is an incubation period of approximately 4 to 6 weeks. The acute illness phase typically lasts 2 to 3 weeks, but fatigue and reduced stamina can persist for: Up to two months in most people Three months or more in a small percentage Proper rest and recovery are key to minimising prolonged symptoms. Diagnosis Doctors often suspect glandular fever based on: A combination of clinical symptoms The patient’s age and lifestyle Physical examination findings such as swollen glands and enlarged tonsils Confirmation may include: Monospot test, which detects heterophile antibodies (most useful after the first week of illness) Full blood count, showing atypical lymphocytes Liver function tests, often mildly abnormal in active infection EBV serology, which can determine whether the infection is recent or past Diagnosis is typically clinical, and additional testing is only necessary if symptoms are unclear or prolonged. How It Differs from Other Illnesses Glandular fever is frequently mistaken for: Streptococcal tonsillitis Flu or COVID-19 Cytomegalovirus (CMV) infection Toxoplasmosis HIV (in early seroconversion) The distinguishing feature of glandular fever is its combination of sore throat, swollen glands, and extreme fatigue that lasts well beyond the usual viral illness duration. Is Glandular Fever Serious? In most cases, glandular fever resolves on its own with proper rest and hydration. However, it can become serious if complications develop, such as: Ruptured spleen (rare but life-threatening) Airway obstruction due to severe tonsil swelling Hepatitis or elevated liver enzymes Prolonged fatigue resembling chronic fatigue syndrome Anaemia or thrombocytopaenia For this reason, individuals are advised to avoid contact sports or heavy lifting for at least four weeks after diagnosis to reduce the risk of spleen rupture. Long-Term Outlook Most people recover fully from glandular fever and do not experience further problems. The body develops lifelong immunity to EBV, so reinfection is extremely rare. However, EBV remains in the body for life in a dormant form. In very rare cases, reactivation can occur, especially in people with compromised immune systems. Understanding glandular fever helps individuals manage the condition safely and prevent unnecessary complications. With rest, fluids, and time, most people return to full health. [Next: Causes of Glandular Fever →]

Glandular Fever Read More »

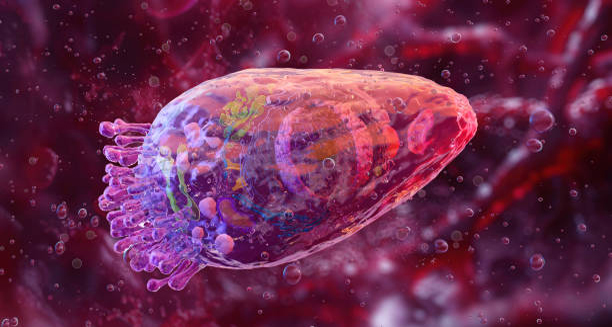
Epstein-Barr virus (EBV) under microscope as cause of glandular fever

Causes of Glandular Fever

Causes of Glandular Fever The causes of glandular fever are viral in nature, with the Epstein-Barr virus (EBV) responsible for around 90% of cases. Glandular fever is not caused by poor hygiene, bacteria, or food poisoning—rather, it results from close personal contact that allows saliva containing EBV to pass from one person to another. EBV is a member of the herpesvirus family and is one of the most common human viruses. It is estimated that more than 90% of adults worldwide have been infected with EBV by the age of 40, often without ever realising it. The virus usually lies dormant after initial infection and does not cause repeated illness in healthy individuals. Epstein-Barr Virus (EBV) The Epstein-Barr virus was first identified in 1964 and is now recognised as the primary cause of infectious mononucleosis (glandular fever). EBV infects B lymphocytes, a type of white blood cell involved in the immune response. The virus causes an immune reaction that results in: Swelling of lymph nodes Inflammation of the throat and tonsils Increase in abnormal lymphocytes (atypical mononucleated cells) A surge of fatigue due to the immune system’s heightened activity Once the virus enters the body, it replicates in the throat and salivary glands before spreading through the bloodstream. The immune response to EBV, rather than the virus itself, causes most of the symptoms associated with glandular fever. How EBV Is Transmitted The virus is spread primarily through saliva, but can also be found in: Mucus from the nose and throat Tears Blood and, in rare cases, semen The most common modes of transmission include: Kissing Sharing drinks, utensils, lip balm, or cigarettes Exposure to droplets from coughing or sneezing Using contaminated objects, such as toothbrushes Because EBV is so widespread, exposure is common. However, not everyone who contracts the virus develops glandular fever. In early childhood, EBV infections often pass unnoticed or with only mild flu-like symptoms. Why Some People Get Glandular Fever Not everyone exposed to EBV develops glandular fever. The likelihood of developing symptoms depends on: Age at the time of infection Children under 5 rarely develop classic symptoms Teenagers and young adults are most likely to experience full-blown glandular fever Immune system response A robust immune reaction is what causes the fatigue and lymph node swelling typical of the illness Genetic predisposition Some evidence suggests genetic factors may influence the body’s response to EBV Those infected with EBV during adolescence or early adulthood are most likely to develop symptoms, while those infected in early childhood often remain asymptomatic. Other Causes of Glandular Fever-Like Illness Although EBV is the leading cause of glandular fever, other viruses can cause a similar illness, including: Cytomegalovirus (CMV) Toxoplasma gondii (a parasite, not a virus) HIV (acute seroconversion illness) Hepatitis viruses Adenoviruses In these cases, the illness is usually less severe, and blood tests help differentiate the underlying cause. Risk Factors Several factors may increase the risk of contracting EBV and developing glandular fever: Living in close quarters, such as dormitories or military barracks Sharing drinks or personal items Kissing multiple partners, particularly among teenagers Weakened immune system, due to illness or medication While these behaviours increase exposure, many people who carry EBV never fall ill, as the immune system usually keeps the virus in check. Can EBV Reactivate? Once a person contracts EBV, the virus remains dormant in their body for life. In rare cases, it may reactivate, particularly in individuals with: Immunodeficiency, such as in advanced HIV or post-organ transplantation Chronic stress or severe illness Certain autoimmune diseases Reactivation is uncommon in healthy people and usually does not cause symptoms. However, EBV reactivation has been loosely associated with conditions like: Chronic fatigue syndrome Multiple sclerosis (MS) Certain lymphomas It is important to note that research is ongoing, and direct causation has not been firmly established. Summary of Main Causes Cause Role in Glandular Fever Epstein-Barr virus (EBV) Primary cause (90% of cases) Cytomegalovirus (CMV) EBV-negative glandular fever-like illness Toxoplasma, hepatitis, HIV Less common, mimic symptoms Saliva exchange Main mode of EBV transmission Age (15–25) Highest risk of symptomatic infection Conclusion | Causes of Glandular Fever The causes of glandular fever are well understood, with the Epstein-Barr virus playing the central role. Transmission occurs primarily through saliva, making the condition particularly common among teenagers and young adults. Understanding how the virus works, who is at risk, and how it spreads helps to prevent infection and allows for early recognition of symptoms. [Next: Symptoms of Glandular Fever→]

Causes of Glandular Fever Read More »

Woman holding sore throat due to glandular fever symptoms

Symptoms of Glandular Fever

Symptoms of Glandular Fever The symptoms of glandular fever vary widely between individuals, depending on their age, immune response, and overall health. Glandular fever, also known as infectious mononucleosis, most commonly affects teenagers and young adults, though people of any age can contract the virus. While some individuals may experience only mild symptoms or none at all, others endure a more severe and prolonged illness that interferes with daily life. The disease is caused primarily by the Epstein-Barr virus (EBV) and triggers an intense immune reaction. This reaction is responsible for many of the hallmark signs, which include fatigue, swollen glands, and a sore throat. Recognising the full spectrum of symptoms allows for early diagnosis, appropriate care, and the prevention of complications. Typical Onset The incubation period for EBV is approximately four to six weeks. During this time, the virus replicates and spreads within the body, often without producing any symptoms. Once the immune system begins to respond, symptoms emerge rapidly and may persist for several weeks. In many cases, the illness begins with general malaise, including: Mild fever Muscle aches Loss of appetite Headache Low energy or sleepiness These early signs can mimic other common viral infections, making initial diagnosis difficult. Core Symptoms Once fully developed, glandular fever typically presents with a characteristic trio of symptoms: 1. Sore Throat The sore throat associated with glandular fever is usually severe and can: Last for more than a week Resemble bacterial tonsillitis Include red, inflamed tonsils with white or grey patches Make swallowing difficult and painful In some cases, the tonsils become so enlarged that they obstruct the airway or cause voice changes. 2. Swollen Lymph Nodes Enlargement of lymph nodes is a key sign and occurs particularly in: The neck The armpits Occasionally the groin These glands may feel tender and firm, and they can persist for several weeks even after other symptoms subside. 3. Fatigue Profound fatigue is perhaps the most debilitating symptom. It can: Begin suddenly and worsen quickly Persist for weeks or even months Be accompanied by sleep disturbances, mental fog, or difficulty concentrating Even after other symptoms improve, fatigue may linger and affect academic performance, work productivity, and overall quality of life. Additional Symptoms In addition to the classic triad, individuals may also experience: Fever: Typically low to moderate, but occasionally higher than 38.5°C Chills and night sweats Muscle and joint pain Headaches Loss of appetite Nausea or mild abdominal pain In some cases, the liver and spleen become inflamed, leading to: Tenderness in the upper abdomen Mild jaundice (yellowing of the skin or eyes) Enlarged spleen (splenomegaly), increasing the risk of rupture The presence of liver and spleen involvement makes it crucial to avoid contact sports or heavy lifting for at least four weeks. Skin Rash and Antibiotic Reactions Some individuals develop a maculopapular rash, which is: Flat or slightly raised Pink or red in appearance Usually non-itchy This is more likely to occur if the person has taken certain antibiotics, particularly amoxicillin or ampicillin, which can trigger an allergic-looking rash in people with EBV. The rash is not harmful and usually disappears within a few days, but its appearance can be alarming if unexpected. In Children Children infected with EBV often display: Very mild symptoms Brief fever or irritability Mild throat inflammation In many cases, the infection goes unnoticed, and the child develops lifelong immunity without ever being diagnosed. In Older Adults Glandular fever is less common in older adults, but when it occurs, symptoms may be: Atypical or less pronounced Mistaken for flu, hepatitis, or other infections Associated with jaundice and liver enzyme abnormalities Fatigue and weakness may persist longer in older individuals, especially if underlying conditions are present. Timeline of Symptoms Timeframe Common Symptoms Week 1 Fatigue, sore throat, mild fever Week 2 Enlarged lymph nodes, severe sore throat Weeks 3–4 Fatigue, lingering fever, swollen glands Weeks 5+ Residual fatigue, occasional mild symptoms When to Seek Medical Advice Medical attention is advised if: Breathing or swallowing becomes difficult Abdominal pain or fullness is felt under the ribs (may suggest spleen enlargement) Symptoms last longer than four weeks without improvement There is concern about jaundice or rash after antibiotics Severe fatigue interferes with daily life Symptoms of Glandular Fever Most cases of glandular fever resolve on their own with time and rest. However, severe or persistent symptoms may indicate complications or require further investigation. Understanding the symptoms of glandular fever helps with early identification, proper care, and safe recovery. While most people recover fully, patience is often required to cope with the extended fatigue phase. [Next: Diagnosis of Glandular Fever →]

Symptoms of Glandular Fever Read More »

Scroll to Top