Mental Matters

Author name: admin

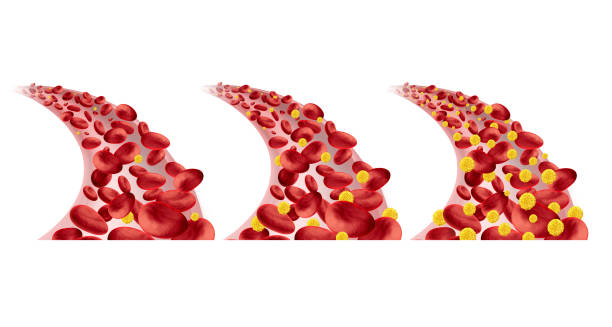
Visual representation of increasing ketone levels in blood vessels

Symptoms of Diabetic Ketoacidosis

Symptoms of Diabetic Ketoacidosis Symptoms of diabetic ketoacidosis typically develop quickly and can become severe within hours. Because diabetic ketoacidosis affects multiple body systems, its symptoms span from gastrointestinal discomfort to altered mental status. Early recognition of these symptoms is essential to prevent serious complications and ensure timely treatment. Early Symptoms Excessive thirst and frequent urination are often the first signs As ketone levels rise, the body attempts to flush out excess sugar through urine, leading to dehydration Individuals may also experience dry mouth, weakness, and fatigue Gastrointestinal Symptoms Nausea and vomiting are common and can contribute to further fluid loss Abdominal pain or cramping may be present, especially in children Loss of appetite often accompanies these symptoms Respiratory Changes As acidosis worsens, the body attempts to correct pH levels by altering breathing Individuals may begin breathing more rapidly and deeply (known as Kussmaul respirations) This distinctive breathing pattern is a critical clinical clue Fruity Breath Odour One hallmark symptom is a sweet or fruity-smelling breath, caused by the presence of acetone (a type of ketone) in exhaled air Neurological Symptoms of Diabetic Ketoacidosis As the condition progresses, mental status changes may occur: Confusion Agitation or irritability Drowsiness or loss of consciousness If untreated, this can advance to coma and become life-threatening Signs of Shock Severe DKA may result in low blood pressure and fast heart rate Cold, clammy skin and weak pulse are signs of impending shock When to Seek Emergency Care Any combination of vomiting, abdominal pain, altered breathing, and confusion should be treated as a medical emergency Blood or urine ketone test kits can help confirm elevated ketone levels at home In summary, symptoms of diabetic ketoacidosis progress quickly and should never be ignored. Recognising these red flags allows for immediate medical intervention, which is vital to prevent permanent damage or death. [Next: Diagnosis of Diabetic Ketoacidosis→]

Symptoms of Diabetic Ketoacidosis Read More »

Book with diabetic ketoacidosis title beside medical diagnosis clipboard

Diagnosis of Diabetic Ketoacidosis

Diagnosis of Diabetic Ketoacidosis Diagnosis of diabetic ketoacidosis requires a combination of clinical evaluation and laboratory tests. Because diabetic ketoacidosis (DKA) can develop rapidly and pose serious health risks, timely diagnosis is essential. Most cases present in hospital emergency departments, where healthcare professionals assess symptoms, vital signs, and biochemical markers to confirm the condition and rule out other possible causes. Initial Clinical Assessment Patients usually present with: Nausea and vomiting Abdominal pain Rapid, deep breathing (Kussmaul respirations) Fruity-smelling breath (due to acetone) Lethargy, confusion, or in severe cases, unconsciousness The clinician will take a medical history, focusing on diabetes management, recent infections, missed insulin doses, and stress events such as trauma or surgery. Physical examination helps assess dehydration, mental status, and respiratory function. Key Laboratory Tests Blood Glucose: Elevated levels above 11 mmol/L (200 mg/dL) Confirms hyperglycaemia, a core feature of DKA Ketones: Detected in blood or urine Blood ketone level >3.0 mmol/L indicates significant ketosis Arterial Blood Gas (ABG): Measures acidity of the blood pH less than 7.3 confirms metabolic acidosis Bicarbonate level <15 mmol/L is also a diagnostic marker Electrolytes: Potassium may be normal or high at first but drops with treatment Sodium, chloride, and anion gap are also monitored to assess severity Renal Function: Urea and creatinine levels are checked to evaluate dehydration and kidney involvement Urinalysis: Reveals ketones, glucose, and sometimes evidence of infection Other Tests: ECG (to detect electrolyte disturbances) Chest X-ray or blood cultures if infection is suspected Differential Diagnosis of Diabetic Ketoacidosis Other conditions that mimic DKA include: Starvation ketosis Alcoholic ketoacidosis Sepsis Lactic acidosis Therefore, clinicians must use a combination of biochemical evidence and clinical signs to confirm the diagnosis. In conclusion, diagnosis of diabetic ketoacidosis hinges on identifying the triad of hyperglycaemia, ketosis, and metabolic acidosis. Prompt recognition ensures effective treatment and reduces the risk of serious complications or death. [Next: Treatment of Diabetic Ketoacidosis →]

Diagnosis of Diabetic Ketoacidosis Read More »

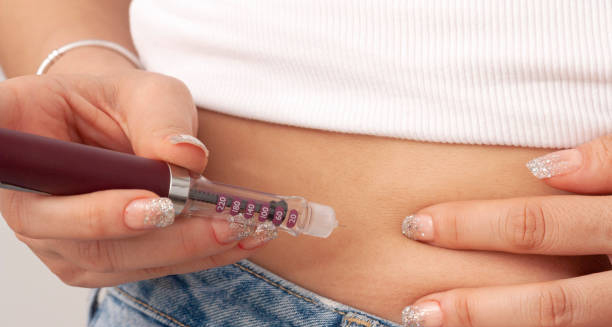
Person administering insulin injection into abdomen

Treatment of Diabetic Ketoacidosis

Treatment of Diabetic Ketoacidosis Treatment of diabetic ketoacidosis focuses on correcting high blood sugar, replacing lost fluids and electrolytes, and stopping ketone production. Since diabetic ketoacidosis can lead to life-threatening complications, treatment must be initiated without delay, usually in an emergency department or intensive care unit. Fluid Replacement The first priority in treating DKA is addressing severe dehydration: Isotonic saline (0.9% sodium chloride) is administered intravenously Fluid replacement helps reduce blood glucose levels, improve circulation, and support kidney function Doctors give an initial bolus followed by ongoing rehydration over 24–48 hours Insulin Therapy Doctors start intravenous insulin after administering fluids to reduce blood glucose and stop ketone production Doctors prefer a continuous low-dose insulin infusion to avoid sudden glucose drops. Insulin also helps shift potassium back into cells, which necessitates close potassium monitoring Electrolyte Monitoring Healthcare providers closely observe potassium levels and replace potassium as needed Hypokalaemia (low potassium) can occur quickly during treatment and is potentially fatal Sodium and phosphate may also need correction Monitoring and Adjustments Healthcare providers check blood glucose, ketones, and acid-base status hourly at first Doctors adjust insulin and fluids based on these results Healthcare providers continuously monitor vital signs and urine output to assess progress Treating the Underlying Cause Doctors identify infection through cultures and treat it with appropriate antibiotics, as infection is a common trigger Other causes, such as missed insulin, trauma, or medication errors, should be addressed Transition to Subcutaneous Insulin They stop IV insulin once ketosis resolves and the patient can eat Doctors introduce a subcutaneous insulin regimen with overlap to prevent rebound hyperglycaemia Patient Education on Treatment of Diabetic Ketoacidosis Education on proper insulin use, blood glucose monitoring, sick day management, and diet is vital to prevent recurrence In summary, treatment of diabetic ketoacidosis involves intensive fluid resuscitation, insulin therapy, and electrolyte correction. With timely medical care and careful monitoring, most patients recover fully. [Next: Complications and Recovery from Diabetic Ketoacidosis →]

Treatment of Diabetic Ketoacidosis Read More »

Illustration showing diabetes management tools, medication, and glucose monitoring for diabetic ketoacidosis recovery

Complications and Recovery from Diabetic Ketoacidosis

Complications and Recovery from Diabetic Ketoacidosis Complications and recovery from diabetic ketoacidosis depend on how early treatment is started and how well the condition is managed. While diabetic ketoacidosis is reversible with proper care, it can cause significant health issues if diagnosis or treatment is delayed. Ongoing support and education are essential to full recovery and long-term diabetes control. Acute Complications Cerebral Oedema Most common in children and adolescents Caused by rapid shifts in fluid and glucose levels during treatment Can result in seizures, coma, or death Electrolyte Imbalance Potassium, sodium, and phosphate levels can fluctuate dangerously Hypokalaemia may lead to arrhythmias or cardiac arrest Hypoglycaemia Overcorrection with insulin can cause blood sugar to drop too low Symptoms include sweating, confusion, and in severe cases, unconsciousness Acute Kidney Injury Severe dehydration and high ketone levels may impair kidney function Usually reversible with rehydration and electrolyte balance Cardiovascular Strain Tachycardia, low blood pressure, and stress on the heart are common in severe cases Underlying heart conditions may worsen Recovery Timeline | Complications and Recovery from Diabetic Ketoacidosis Most patients improve within 24 to 48 hours of treatment Ketone levels usually normalise within 12–24 hours Hospital stays typically range from 2 to 4 days, depending on severity Post-Recovery Monitoring Regular follow-up appointments are essential Patients may need insulin adjustments and diabetes education Monitoring for complications like kidney dysfunction or cardiovascular strain is ongoing Psychosocial Considerations Recurrent DKA may be linked to insulin omission due to emotional distress, fear of weight gain, or mental health conditions Psychological counselling and support groups can help address these issues Preventing Recurrence Adherence to insulin regimens Clear action plans for sick days or infections Regular blood glucose and ketone monitoring Educating family and caregivers to recognise early warning signs In conclusion, complications and recovery from diabetic ketoacidosis are manageable with prompt care and structured follow-up. With proper education, support, and medical guidance, most patients return to full function and significantly reduce their risk of recurrence. [Next: Back to Overview →]

Complications and Recovery from Diabetic Ketoacidosis Read More »

Notebook with Diabetes Insipidus title near medical report

Diabetes Insipidus

Diabetes Insipidus – Overview Diabetes insipidus is a rare medical condition characterised by excessive thirst and the excretion of large amounts of dilute urine. Unlike diabetes mellitus, which is related to blood sugar regulation. This is caused by a problem with the regulation of water balance in the body. This leads to significant fluid loss and a constant need to urinate, which can be dangerous if not properly managed. The condition arises due to issues with the hormone vasopressin. Also known as antidiuretic hormone (ADH), which plays a crucial role in controlling the body’s water balance. When functioning normally, ADH signals the kidneys to retain water and concentrate urine. In this condition, this process is impaired. Either due to insufficient production of the hormone or a failure of the kidneys to respond to it. There are four main types of this: central, nephrogenic, dipsogenic, and gestational. Central results from damage to the pituitary gland or hypothalamus. While nephrogenic diabetes insipidus stems from a resistance of the kidneys to ADH. Dipsogenic diabetes insipidus involves a malfunction in the thirst mechanism, and gestational D-insipidusoccurs during pregnancy due to placental enzyme interference. Diabetes Insipidus Though this is not life-threatening with proper treatment. It can severely disrupt daily life and, if unmanaged, lead to dehydration, electrolyte imbalances, and complications in the kidneys and other organs. Recognising symptoms early and receiving appropriate care is essential to ensure a good quality of life. In summary, diabetes insipidus is a rare but manageable disorder that disrupts fluid regulation in the body. With early diagnosis and ongoing treatment, individuals can maintain stable hydration levels and avoid serious complications. [Next: Causes of Diabetes Insipidus →]

Diabetes Insipidus Read More »

Hormone molecule model linked to diabetes insipidus

Causes of Diabetes Insipidus

Causes of Diabetes Insipidus Causes of diabetes insipidus depend on the type of condition present, as each form originates from a different disruption in the body’s ability to regulate water. Although diabetes insipidus is rare, understanding its underlying causes is crucial for both diagnosis and management. Central Diabetes Insipidus Damage to the hypothalamus or pituitary gland, which produce and release antidiuretic hormone (ADH), causes this most common form: Head injuries or brain surgery may damage ADH-producing areas Tumours, such as craniopharyngiomas or pituitary adenomas, can interfere with hormone production Infections like meningitis or encephalitis can inflame or destroy ADH-secreting tissue Genetic mutations may also lead to inherited central diabetes insipidus In central diabetes insipidus, the body produces insufficient ADH, so the kidneys do not receive signals to retain water. Nephrogenic Diabetes Insipidus Here, the kidneys fail to respond to normal levels of ADH: Can be inherited, often due to mutations in the AVPR2 or AQP2 genes Chronic kidney disease or damage from certain medications, especially lithium or tetracycline antibiotics, may induce resistance to ADH High calcium levels (hypercalcaemia) and low potassium levels (hypokalaemia) can disrupt kidney function This type does not respond well to hormone replacement, making management more complex. Dipsogenic Diabetes Insipidus | Causes of Diabetes Insipidus This form results from a problem in the hypothalamus that affects thirst regulation: Individuals may drink excessive amounts of water without feeling the need to Psychiatric disorders or brain trauma can lead to this dysfunctional thirst mechanism Over time, this constant intake suppresses ADH secretion, mimicking diabetes insipidus Gestational Diabetes Insipidus Occurs during pregnancy when the placenta produces an enzyme (vasopressinase) that breaks down ADH: Usually appears in the third trimester and resolves after childbirth Women carrying multiple foetuses are at higher risk In conclusion, causes of diabetes insipidus are diverse, ranging from genetic and neurological to hormonal and renal. Identifying the specific type helps guide targeted treatment and effective long-term management. [Next: Symptoms of Diabetes Insipidus →]

Causes of Diabetes Insipidus Read More »

Woman with dry, cracked lips from dehydration

Symptoms of Diabetes Insipidus

Symptoms of Diabetes Insipidus Symptoms of diabetes insipidus primarily relate to the body’s inability to retain water, leading to excessive urination and persistent thirst. People with diabetes insipidus may pass up to 20 litres of urine in a day, which significantly impacts daily routines and overall health. Key Symptoms of Diabetes Insipidus Polyuria: The production of unusually large volumes of dilute urine, often requiring frequent trips to the toilet, including during the night (nocturia) Polydipsia: Constant, intense thirst that leads to increased water intake, often exceeding normal daily needs Dry mouth and dehydration, despite high fluid intake Fatigue and lethargy due to electrolyte imbalances and sleep disturbances Headaches or irritability, especially in children, caused by fluid and salt imbalances Signs in Infants and Children Irritability that improves with drinking water Poor feeding and slow growth Vomiting or constipation Unexplained fever Bedwetting or enuresis in older children Differences Between Types In central D- insipidus, symptoms often appear suddenly, especially following trauma or surgery In nephrogenic D-insipidus, symptoms may be present from birth or develop gradually due to chronic kidney problems Dipsogenic diabetes insipidus includes a psychological component, as individuals drink water excessively without physical thirst Gestational diabetes insipidus typically resolves after delivery but presents with similar symptoms in late pregnancy Complications If Untreated Severe dehydration: Dry skin, low blood pressure, dizziness, or even shock Electrolyte imbalances: Affecting muscle function, heart rhythm, and nerve transmission Kidney strain from constant fluid excretion In summary, symptoms of diabetes insipidus can range from bothersome to life-threatening if not properly addressed. Recognising the signs early ensures individuals receive prompt treatment and avoid serious complications. [Next: Diagnosis of Diabetes Insipidus →]

Symptoms of Diabetes Insipidus Read More »

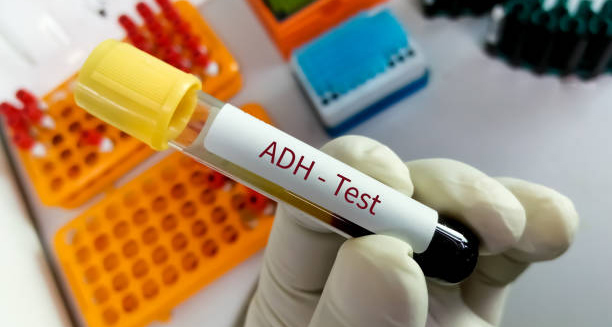
ADH test tube held in gloved hand

Diagnosis of Diabetes Insipidus

Diagnosis of Diabetes Insipidus Accurate diagnosis of diabetes insipidus is essential to prevent serious complications like dehydration, electrolyte imbalance, and kidney dysfunction. Since its symptoms—such as excessive urination and extreme thirst—can mimic other conditions, careful clinical evaluation and specific tests are required to confirm the diagnosis and determine the type. Common Diagnostic Methods Diagnosis typically begins with a detailed medical history and physical examination, followed by targeted laboratory tests to assess the body’s ability to concentrate urine and regulate fluid balance. Water Deprivation Test This is the most definitive test for diagnosing diabetes insipidus: The individual is closely monitored while fluids are restricted Healthcare providers regularly measure body weight, urine output, and urine concentration (osmolality) Normally, urine becomes more concentrated with dehydration; in diabetes insipidus, it remains dilute Doctors may administer ADH (vasopressin) to distinguish between central and nephrogenic diabetes insipidus Urine and Blood Tests Healthcare providers use these tests to evaluate hydration status and kidney function: Urine osmolality: Low in diabetes insipidus, despite dehydration Blood osmolality: Often elevated due to water loss Sodium levels: May be high in untreated cases MRI of the Brain If healthcare providers suspect central diabetes insipidus, they may order brain imaging to: Detect abnormalities in the pituitary gland or hypothalamus Identify potential causes such as tumors, trauma, or inflammation Differentiating Between Types Identifying the type of diabetes insipidus helps determine the most effective treatment: Central DI: Low ADH levels; improves with desmopressin (synthetic ADH) Nephrogenic DI: Normal or high ADH levels; no response to desmopressin Dipsogenic DI: Linked to excessive fluid intake and suppressed ADH secretion Gestational DI: Typically confirmed through history and blood tests during pregnancy; resolves postpartum Who Should Be Evaluated? Healthcare providers recommend testing for individuals who: Experience frequent urination and unquenchable thirst Have a history of head injury, brain surgery, or neurological conditions Show signs of unexplained dehydration or electrolyte imbalance Have a family history of diabetes insipidus or related kidney disorders The Importance of Early Diagnosis of Diabetes Insipidus Prompt diagnosis of diabetes insipidus enables: Early intervention to prevent dehydration and complications Identification of underlying causes such as tumors or genetic conditions Tailored treatment plans that improve long-term quality of life In summary, diagnosing diabetes insipidus involves a combination of clinical observation, lab testing, and imaging studies. Recognising and differentiating its forms early ensures effective management and helps avoid serious health risks. [Next: Treatment of Diabetes Insipidus →]

Diagnosis of Diabetes Insipidus Read More »

Woman eating healthy food after workout

Treatment of Diabetes Insipidus

Treatment of Diabetes Insipidus Treatment of diabetes insipidus aims to reduce excessive urination and maintain proper hydration and electrolyte balance. Because the condition varies by type and underlying cause, healthcare providers tailor management to each individual. Healthcare providers adjust the dosage based on symptoms, urine output, and sodium levelsWith appropriate care, most people with diabetes insipidus can lead healthy, active lives. Central Diabetes Insipidus This form typically responds well to hormone replacement therapy: Desmopressin (DDAVP): A synthetic version of vasopressin (ADH), available as a nasal spray, oral tablet, or injection Helps the kidneys retain water and concentrate urine Healthcare providers adjust the dosage based on symptoms, urine output, and sodium levels Careful monitoring prevents complications such as water retention and low sodium (hyponatraemia) Nephrogenic Diabetes Insipidus Treatment focuses on improving the kidney’s response to ADH and reducing urine output: Low-salt diet: Reduces the amount of urine produced Thiazide diuretics: Paradoxically decrease urine volume by altering sodium handling in the kidneys NSAIDs (like indomethacin): Sometimes used to enhance the effect of thiazides Hydration: Regular fluid intake remains essential to avoid dehydration Inherited forms may require lifelong management with specialised care Dipsogenic Diabetes Insipidus | Treatment of Diabetes Insipidus Because this form is linked to excessive fluid intake, management is more behavioural: Treat underlying psychiatric or neurological conditions, if present Monitor fluid intake to avoid water intoxication In some cases, low-dose desmopressin may be used cautiously under strict supervision Gestational Diabetes Insipidus This form usually resolves after childbirth, but may require temporary treatment: Desmopressin is safe and effective for use during pregnancy Regular monitoring of electrolytes and fluid balance is essential, particularly in the third trimester High-risk pregnancies (e.g., multiple foetuses) may need closer observation Ongoing Monitoring and Support Effective treatment includes regular follow-ups to assess symptoms, adjust medication, and monitor hydration: Blood tests: To monitor sodium and osmolality Urine output logs: Help track treatment effectiveness Education: Patients and caregivers should learn to recognise signs of dehydration or overhydration When to Seek Specialist Care Referral to an endocrinologist or nephrologist may be needed for: Difficult-to-manage cases Suspected genetic forms Associated pituitary or kidney disorders In conclusion, treatment of diabetes insipidus varies by type but generally focuses on controlling urine output and maintaining fluid balance. With the right care plan, individuals can manage their condition effectively and avoid serious complications. [Next: Complications and Prognosis of Diabetes Insipidus →]

Treatment of Diabetes Insipidus Read More »

Woman experiencing shortness of breath while seated on a couch

Complications and Recovery from Diabetes Insipidus

Complications and Recovery from Diabetes Insipidus Complications and recovery from diabetes insipidus depend on the type, severity, and how early the condition is diagnosed and managed. While diabetes insipidus is rarely life-threatening when treated properly, inadequate control can lead to significant health issues. Understanding potential complications and the path to recovery is essential for long-term well-being. Common Complications If left untreated or poorly managed, diabetes insipidus can lead to serious consequences related to fluid and electrolyte imbalance: Dehydration Excessive urination without sufficient fluid intake leads to rapid fluid loss Symptoms include dry mouth, sunken eyes, low blood pressure, and dizziness Severe dehydration can result in confusion, fainting, or shock Electrolyte Imbalances Loss of sodium and other essential minerals disrupts cellular function Can cause muscle cramps, fatigue, irregular heart rhythms, and seizures Sodium levels may become dangerously high (hypernatraemia) or, with overtreatment, too low (hyponatraemia) Kidney and Bladder Strain Persistent high urine output puts pressure on the kidneys and urinary system May increase the risk of urinary tract infections and bladder issues over time Impact on Daily Life Frequent urination, including at night (nocturia), can disrupt sleep and reduce quality of life In children, symptoms may affect growth, behaviour, and school performance Recovery and Long-Term Management Recovery from diabetes insipidus involves restoring fluid balance and preventing recurrence of symptoms: Medical Stabilisation Healthcare providers rapidly rehydrate patients in acute cases of dehydration Medical professionals correct electrolyte levels under supervision, often in a hospital setting Ongoing Treatment Doctors adjust desmopressin or other medications to keep urine output and thirst under control Regular follow-ups ensure continued effectiveness and safety of treatment Monitoring and Prevention | Complications and Recovery from Diabetes Insipidus Healthcare providers teach patients to monitor their fluid intake and watch for signs of imbalance Blood and urine tests help track sodium levels and kidney function Healthcare providers recommend wearing medical alert identification in case of emergencies Special Considerations by Type Central DI: Usually well-controlled with medication; recovery focuses on dosage adjustment and managing any underlying brain condition Nephrogenic DI: Requires more complex, often long-term management; ongoing kidney monitoring is key Patients with dipsogenic DI may require behavioural therapy and psychological support for recovery Gestational DI: Typically resolves after childbirth, though temporary treatment may be necessary; follow-up ensures no persistent issues Quality of Life and Support With proper management, most individuals lead normal, active lives Support groups, education, and caregiver involvement can improve daily coping Children with DI can thrive with structured care and coordination between families, schools, and healthcare providers In conclusion, complications and recovery from diabetes insipidus are manageable with early diagnosis, appropriate treatment, and regular follow-up. With personalised care and education, individuals can minimise risks and enjoy a high quality of life. [Next: Back to Overview →]

Complications and Recovery from Diabetes Insipidus Read More »

Scroll to Top