Mental Matters

Author name: admin

Causes of Laryngeal (larynx) cancer

Causes of Laryngeal (larynx) cancer

Laryngeal (larynx) cancer develops when the cells lining the inside of the larynx change abnormally and start growing uncontrollably. Over time, these cells form malignant tumours. These tumours can invade nearby tissues and spread to other parts of the body. The exact cause of laryngeal (larynx) cancer often involves a mix of environmental, lifestyle, and genetic factors. These disrupt normal cell control within the larynx. Tobacco use: The main cause The most important and well-known cause of laryngeal (larynx) cancer is tobacco use. This includes smoking cigarettes, cigars, or pipes, as well as chewing tobacco. Tobacco has many cancer-causing chemicals that damage the lining of the throat and larynx. These chemicals change the DNA in the cells lining the larynx. This increases the chance of mutations and cancer. The risk rises with how much and how long someone uses tobacco. Long-term smokers, especially those who start young, have the highest risk. Alcohol use and combined risk Heavy drinking is another major risk factor closely linked to smoking. Alcohol can irritate and inflame the larynx lining. When combined with tobacco, the risk of cancer increases greatly. The effects of alcohol and tobacco together are much stronger than either alone. People who both smoke and drink heavily can be up to 100 times more likely to get laryngeal cancer than those who do not. Occupational exposures Exposure to harmful substances at work can also cause laryngeal (larynx) cancer. People who breathe in asbestos, wood dust, coal dust, diesel fumes, or certain chemicals may have higher risk. These substances can cause long-term irritation and damage to the larynx cells. Workers in industries such as construction, metalworking, textiles, and chemicals are especially affected. Human papillomavirus (HPV) infection HPV, especially type 16, is another cause. HPV is more often linked to throat cancers but can infect the larynx too. HPV-related laryngeal cancers tend to happen in younger people who do not smoke. These cancers may react differently to treatment. HPV spreads through intimate contact, including oral sex. Rising HPV-related cancers have led to public health efforts promoting HPV vaccination. Acid reflux (GORD) Gastro-oesophageal reflux disease (GORD), or acid reflux, may also raise risk. In GORD, stomach acid flows back into the throat and larynx. This acid irritates the lining over time. While acid reflux alone rarely causes cancer, it can increase risk when combined with smoking or drinking. Poor diet and nutrition A diet low in fruits and vegetables may increase the chance of laryngeal cancer. Lack of vitamins, antioxidants, and fibre can weaken the body’s ability to repair damaged cells. Diets high in processed meats and low in plant foods link to several cancers, including those in the head and neck. Genetic factors Genetic predisposition plays a smaller role. People with a family history of head and neck cancers might inherit weaker defenses against carcinogens. This makes them more vulnerable to tobacco and alcohol effects. Still, most laryngeal (larynx) cancer cases happen without a clear inherited pattern. Age and gender risks Age and gender also affect risk. Laryngeal cancer is much more common in men. This is partly because men have historically smoked and drank more. Risk increases with age, and most cases occur in people over 60. Immune system suppression Weakened immunity from medical treatments, HIV, or organ transplants may also raise risk. A weaker immune system can fail to remove cells with early cancer changes. This allows cancer to develop. In many cases, laryngeal (larynx) cancer results from several causes combined. For example, a smoker who drinks heavily and works with toxic chemicals faces a much higher risk than someone exposed to only one factor. Knowing these multiple causes helps with prevention and guides early detection efforts in high-risk groups. In conclusion, laryngeal (larynx) cancer is mainly caused by tobacco and alcohol use. However, other factors like workplace exposures, HPV infection, acid reflux, poor diet, and immune suppression also contribute. Awareness of these causes is key to public health and personal prevention. Avoiding smoking, heavy drinking, and unprotected HPV exposure can greatly reduce the risk of this serious disease. [Next: Symptoms of Laryngeal (larynx) cancer →]

Causes of Laryngeal (larynx) cancer Read More »

Symptoms of Laryngeal (larynx) cancer

Symptoms of Laryngeal (larynx) cancer

Laryngeal (larynx) cancer presents with a range of symptoms that often relate to the tumour’s location and size within the larynx. Since the larynx helps with speaking, breathing, and swallowing, even small growths can cause noticeable changes. Spotting the early signs of laryngeal (larynx) cancer makes a big difference. Finding it early gives a better chance of successful treatment. It can also help save the voice and breathing functions. Hoarseness and voice changes One of the most common early signs of laryngeal (larynx) cancer is a hoarse or changed voice that does not go away. If the cancer grows on or near the vocal cords—called glottic cancer—it changes how the cords vibrate. This makes the voice sound different. People may say their voice is rough, weak, deeper, or strained. Unlike hoarseness from a cold or shouting, which gets better in a few days, voice changes from cancer stay and get worse slowly. If your voice changes and it lasts longer than three weeks, see a doctor right away. Throat pain and the feeling of something stuck Another sign is a sore throat that stays or a feeling like there’s a lump in the throat. Swallowing or drinking doesn’t make this feeling go away. It can be more noticeable when talking or using your voice for a long time. This can lead to pain when speaking and a lower ability to talk for long periods. Trouble swallowing and ear pain Laryngeal (larynx) cancer can also make it hard to swallow, especially when the tumour is above the vocal cords (supraglottic area). As it grows, it may block the throat partly. This makes swallowing food or pills difficult. Some people also feel pain when swallowing. This pain can spread to the ears because nerves in the throat and ears are connected. If someone has ear pain but no ear infection, doctors should check further. This is especially true for people who smoke or drink a lot. Persistent cough and blood in spit Some people with laryngeal (larynx) cancer have a cough that won’t go away. Sometimes the spit may have streaks of blood. This could mean that the tumour is causing small wounds or has affected nearby blood vessels. These signs should never be ignored. The cough may be dry or bring up mucus, but it usually doesn’t get better with normal treatments like syrups or antibiotics. Breathing problems and noisy breathing As the tumour gets bigger, it can block the airway. This makes it harder to breathe. People may notice noisy breathing (stridor), feel short of breath, or have trouble getting enough air while walking or exercising. In serious cases, breathing can become hard even when resting. If this happens, it’s a medical emergency. Neck lumps and swollen glands A lump or swelling in the neck could mean the cancer has spread to the lymph nodes. Sometimes, this is the first sign a person notices—especially if the main tumour is above or below the vocal cords and hasn’t affected the voice. These lumps are usually firm, do not hurt, and don’t go away. Laryngeal (larynx) cancer symptoms in late stages When laryngeal (larynx) cancer gets worse, people may lose weight without trying. They can also feel very tired. This may happen because they are eating less or because their body is reacting to the cancer. People may say they don’t feel hungry, get tired faster, or feel weak all the time. Some may also have bad breath or always feel the need to clear their throat. These symptoms can also happen with other issues like infections or acid reflux. But if they stay even after treatment, doctors should check for cancer. Advanced symptoms of Laryngeal (larynx) cancer If the cancer goes untreated or gets to a late stage, people may lose their voice completely. This can happen if the vocal cords get damaged or removed during treatment. Many also feel emotional stress. Losing the ability to speak or feeling self-conscious can hurt a person’s mental health, social life, and job. Many of these signs look like those from other conditions such as laryngitis, allergies, acid reflux, or tense voice muscles. However, cancer symptoms do not go away quickly. They often get worse slowly. Anyone who has these symptoms—especially people who smoke or drink heavily—should see an ENT (ear, nose, and throat) specialist. Tests for Laryngeal (larynx) cancer symptoms Doctors do not usually screen for laryngeal (larynx) cancer in healthy people. So, early diagnosis depends on knowing the symptoms and getting checked quickly. A nasendoscopy is a simple test done in the doctor’s office. A small, flexible camera goes through the nose to look at the larynx. This can help doctors see any strange growths. If they find anything, they’ll usually take a small sample (biopsy) to check for cancer. In short, the main symptoms of laryngeal (larynx) cancer include a hoarse voice, sore throat, trouble swallowing, a lasting cough, ear pain, breathing problems, and lumps in the neck. These signs can show up alone or together. They often get worse as time goes on. Knowing these signs and acting early can lead to better treatment, a higher chance of recovery, and possibly keeping the voice. [Next: Diagnosis of Laryngeal (larynx) cancer →]
Symptoms of Laryngeal (larynx) cancer Read More »

Diagnosis of Laryngeal (larynx) cancer

Diagnosis of Laryngeal (larynx) cancer

Laryngeal (larynx) cancer is diagnosed through a structured clinical process that begins with suspicion based on symptoms and progresses through visual examination, imaging, and biopsy confirmation. Recognising early symptoms and risk factors Getting a timely and correct diagnosis of Laryngeal (larynx) cancer is very important. It helps doctors begin treatment early and improves the chances of a good outcome. However, many early signs look like common problems such as laryngitis or acid reflux. Because of this, doctors must stay alert. This is especially true for people who smoke or drink a lot. The process usually starts with a visit to a general doctor or an ENT (ear, nose, and throat) specialist. The doctor will ask many questions. These include how long the symptoms have lasted and whether they’ve worsened. Common signs include a hoarse voice, a sore throat, trouble swallowing, or a lump in the neck. The doctor will also ask about lifestyle habits. These might include smoking, alcohol use, or certain job exposures. They’ll also check for any personal or family history of cancer. Laryngoscopy and biopsy Next, the doctor will do a physical check-up. They will feel the neck to check for swollen glands or lumps. These may show that the cancer has spread nearby. But since the voice box is deep inside the throat, doctors need special tools to look at it closely. The main test for diagnosis of Laryngeal (larynx) cancer is a laryngoscopy. This lets doctors see the larynx directly. There are two types: If the doctor finds a lump, they will remove a small piece of it. This goes to a lab. A lab expert checks it under a microscope to see if it is cancer. They will also see what type it is—most often, it’s squamous cell cancer. The lab will also check how fast the cancer cells are growing. Imaging and cancer staging After cancer is confirmed, doctors need to see how far it has spread. This step is called staging. It helps them decide the best way to treat it. Several types of scans are used: Doctors then use the TNM system to stage the cancer: These details give the cancer a stage from 0 to IV. Lower stages (0–II) are often small and still inside the voice box. These cases may only need surgery or radiation. Advanced stages (III–IV) may need more than one type of treatment. Assessing voice and emotional health Another part of the diagnosis of Laryngeal (larynx) cancer involves checking how well the voice works. Doctors may record the patient’s voice or test its quality. This helps with planning voice recovery, especially if surgery may affect the vocal cords. In some cases, a speech therapist joins early to help patients prepare. Doctors may also ask for blood tests. These tests don’t confirm cancer, but they show if the body is healthy enough for treatment. Tests might include blood counts, liver and kidney checks, or signs of poor nutrition if the person feels tired or has lost weight. The emotional side matters too. Hearing that you have laryngeal cancer—especially with the risk of losing your voice—can be very upsetting. That’s why mental health care is part of the process. Counsellors, support groups, and psychologists can help people deal with their fears. Summary of the diagnosis of Laryngeal (larynx) cancer To sum up, the diagnosis of Laryngeal (larynx) cancer follows a careful plan. It starts with a doctor’s exam, then moves to a close look with laryngoscopy, and finally a biopsy confirms the result. Doctors use scans to find the cancer’s stage. The whole process helps begin treatment early, which is key to better results. Today, patients benefit from advanced tools, faster diagnosis, and care from many types of health professionals. These steps make sure treatment is right for each person. They also support the patient’s breathing, speaking, and overall well-being. [Next: Treatment of Laryngeal (larynx) cancer →]
Diagnosis of Laryngeal (larynx) cancer Read More »

Treatment of Laryngeal (larynx) cancer

Treatment of Laryngeal (larynx) cancer

Laryngeal (larynx) cancer treatment depends on several key factors, including the tumour’s location, the stage of the disease, the patient’s health, and the importance of voice preservation. Treatment of laryngeal (larynx) cancer today is highly individualised. Doctors use a mix of medical science, surgery, and rehabilitation to give each patient the best possible outcome. The main treatment options include surgery, radiotherapy, and chemotherapy. These may be used alone or in combination. The goal is to remove or destroy the cancer while preserving speech, swallowing, and breathing. In early-stage cases, cure rates are high, and most patients can keep their natural voice. Advanced cancer usually needs stronger treatment. Surgical Options for Treating Laryngeal (larynx) Cancer Surgery plays a major role, especially for localised tumours or when radiotherapy is not suitable. Surgical choices vary depending on where the tumour is and how far it has spread. Laser surgery (transoral laser microsurgery) is a common method for early-stage glottic cancers. This minimally invasive technique removes the tumour through the mouth using a laser. It avoids external cuts, preserves the voice, and allows quick recovery. Partial laryngectomy removes only part of the larynx, aiming to save structure and function. Some patients can still speak and swallow without needing a permanent stoma (a neck opening for breathing). Total laryngectomy becomes necessary for large or invasive tumours. This surgery removes the entire larynx and creates a permanent stoma. Natural speech is no longer possible. However, many patients regain their ability to speak using speech therapy or a voice prosthesis. Neck dissection may also be done to remove lymph nodes in the neck if cancer has spread there. Recovery after surgery needs a team approach. ENT surgeons, speech therapists, nutritionists, and mental health professionals all play a part. Radiotherapy in Treatment of Laryngeal (larynx) Cancer Radiotherapy uses high-energy rays to kill cancer cells. It is often the main treatment in early-stage laryngeal (larynx) cancer, especially when preserving the voice is important. Sometimes, radiotherapy is used on its own, with no need for surgery. Treatment usually takes several weeks and is done on an outpatient basis. Side effects may include sore throat, dry mouth, hoarseness, tiredness, and taste changes. These symptoms often improve after treatment ends, but some people may have lasting voice or swallowing issues. In more advanced cases, doctors may combine radiotherapy with chemotherapy. This approach, called chemoradiotherapy, can help save the larynx without surgery. However, it can be harder on the body and needs a longer recovery. Role of Chemotherapy in Treatment of Laryngeal (larynx) Cancer Chemotherapy uses strong drugs to stop cancer cells from growing. It is not the first choice for early-stage laryngeal (larynx) cancer but becomes important in later or inoperable stages. Chemotherapy may be used: Drugs like cisplatin, fluorouracil, and carboplatin are common. Side effects include nausea, fatigue, weak immunity, and hair loss. Supportive care helps patients manage these effects. Newer Therapies in Treatment of Laryngeal (larynx) Cancer Some patients with advanced or recurring cancer may receive newer treatments like targeted therapy or immunotherapy. Cetuximab is a targeted drug that blocks a protein (EGFR) that helps cancer cells grow. It can be used with radiation. Immunotherapy, such as nivolumab, helps the immune system find and kill cancer cells. It is mainly used when other treatments fail. Rehabilitation After Treatment of Laryngeal (larynx) Cancer Speech and swallowing therapy is vital after treatment, especially for those who had surgery. Patients who had a partial or total laryngectomy may need help learning to speak again. Options include: Swallowing therapy may be needed if eating muscles or nerves were affected. Some people may need soft diets or temporary feeding tubes during recovery. Psychological Care in Treatment of Laryngeal (larynx) Cancer A laryngeal (larynx) cancer diagnosis is difficult, especially when it affects speech or appearance. Emotional support is a key part of care. Counselling, support groups, and mental health services help patients cope with stress and body changes. This support is especially important for those adjusting to life with a stoma. Follow-up and Lifestyle Changes After Treatment of Laryngeal (larynx) Cancer Quitting smoking is vital during and after treatment. Smoking reduces success rates, slows healing, and increases the risk of more cancers. Cutting down on alcohol is also advised. Long-term follow-up is needed to check for cancer return, treat side effects, and offer continued rehab. Follow-up plans often include scopes, imaging tests, and blood work based on individual needs. In summary, treatment of laryngeal (larynx) cancer depends on the tumour’s size, location, and spread. Most patients need a mix of surgery, radiation, chemotherapy, and rehab. The main goal is to cure the cancer while saving speech and swallowing. With early diagnosis and proper care, many people recover well and maintain a good quality of life. [Next: Complications of Laryngeal (larynx) cancer →]
Treatment of Laryngeal (larynx) cancer Read More »

Complications of Laryngeal (larynx) cancer

Complications of Laryngeal (larynx) cancer

Laryngeal (larynx) cancer can give rise to a range of complications, both from the disease itself and from the treatments used to manage it. While many individuals respond well to therapy, especially when diagnosed early, the impact of laryngeal (larynx) cancer on speech, swallowing, breathing, and overall quality of life can be significant. Understanding these complications is essential for patients, caregivers, and healthcare providers to plan comprehensive care that includes both medical treatment and long-term support. Voice loss and speech problems in laryngeal (larynx) cancer One of the most immediate and life-altering complications of laryngeal (larynx) cancer is voice loss or permanent changes in speech. Depending on the extent of surgery or the effects of radiotherapy, patients may experience hoarseness, reduced vocal power, or even complete aphonia (loss of voice). Total laryngectomy, often required in advanced-stage cancers, involves removing the voice box completely. This eliminates the natural ability to speak. Although speech can return with a voice prosthesis or electrolarynx, it takes training and practice. The new voice rarely sounds like normal speech. This change can have a major psychological and social effect. Many patients experience isolation, loss of confidence, and workplace difficulties. Swallowing issues and breathing complications Another common complication is dysphagia—difficulty swallowing. Radiotherapy and surgery can both damage or alter the swallowing muscles. This increases the risk of aspiration, when food or liquid enters the airway. Aspiration can lead to coughing, chest infections, and even malnutrition. Some people may need feeding tubes, either short- or long-term, if they cannot eat enough by mouth. Breathing problems may also occur, especially in people who have had a tracheostomy or laryngectomy. In these cases, breathing shifts to a stoma in the neck, bypassing the nose and mouth. Although many adapt to this change, it needs daily care. The stoma must be cleaned, humidified, and protected from dust and water. Over time, it may become narrowed or infected. Wound problems, fibrosis, and dental damage Infections and slow wound healing are additional risks after surgery. The neck is a delicate area with many blood vessels and tissues. This makes it prone to wound breakdown, bleeding, or fistula formation—an abnormal link between tissues. These issues may delay recovery and sometimes need more surgery. Radiotherapy can also cause long-term effects like tissue fibrosis, jaw stiffness, and chronic pain. Patients often experience dry mouth (xerostomia), loss of taste, and dental decay. Fibrosis may reduce neck mobility and make chewing or speaking harder. Dental care is very important, as radiation weakens teeth and gums. Patients usually have dental checks before treatment and must follow strict hygiene routines. Nutritional complications and cancer recurrence Nutritional deficiencies often result from poor swallowing, nausea, or lack of appetite. Changes in taste can also reduce interest in food. Patients may lose weight, feel tired, or become dehydrated. Dietitians help create tailored meal plans, suggest supplements, or arrange tube feeding if needed. Another serious risk is cancer recurrence or spread. Even after successful treatment, the cancer may return to the same area or reach other parts like the lungs or lymph nodes. Smoking and alcohol use after treatment increase this risk. Regular check-ups, imaging scans, and laryngoscopy are essential for early detection. Psychological, sexual, and financial challenges Emotional and psychological effects often go unnoticed but can deeply affect recovery. Many patients struggle with depression, anxiety, or low self-esteem. Social isolation is common, especially in those who cannot speak or have visible changes like a stoma. Counselling, peer support groups, and mental health care are key parts of treatment. Some people also face sexual problems. Stress, body image concerns, or side effects from treatment may reduce sexual interest or function. Though less talked about in head and neck cancer, this issue matters and deserves attention during recovery. Financial burden and risk of second cancers Laryngeal (larynx) cancer can bring financial and work-related issues. Treatment often lasts many weeks, followed by a long recovery. People in physically demanding or vocal professions may struggle to return to work. Costs of treatment, travel, medical devices, and rehab can be high. Social workers and vocational counsellors help patients manage these challenges and access support services. There is also a risk of second cancers, especially in those who keep smoking or drinking. The concept of “field cancerisation” means that the entire throat and airway system may develop more cancers later. This highlights the need for quitting tobacco and alcohol, as well as regular screening for any new symptoms. Managing complications of laryngeal (larynx) cancer for better outcomes In conclusion, laryngeal (larynx) cancer can lead to numerous complications affecting speech, swallowing, breathing, mental health, and overall wellbeing. While many of these challenges are manageable with proper support and rehabilitation, they require early recognition and a multidisciplinary approach. Ongoing follow-up, psychological care, nutritional guidance, and patient education are essential to improving long-term outcomes and helping individuals regain as much function and independence as possible after treatment. With appropriate care, many patients go on to lead fulfilling lives—even after major surgeries or therapies—proving that survival is only one part of the cancer journey; living well is equally important. [Next: Back to Overview →]

Complications of Laryngeal (larynx) cancer Read More »

Overview of Lambert-Eaton myasthenic syndrome

Overview of Lambert-Eaton myasthenic syndrome

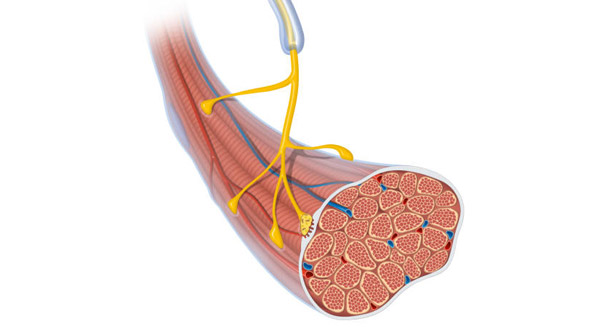
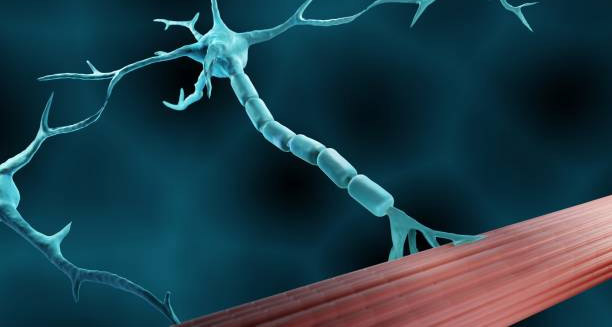
Lambert-Eaton myasthenic syndrome is a rare autoimmune condition that affects the neuromuscular junction—the critical point where nerves communicate with muscles. In individuals with Lambert-Eaton myasthenic syndrome, the immune system mistakenly attacks voltage-gated calcium channels (VGCCs) on the nerve endings. This attack hinders the release of acetylcholine, a neurotransmitter essential for stimulating muscle contraction. As a result, people with the disorder experience progressive muscle weakness and fatigue, particularly in the limbs. Although rare, the condition has major clinical importance. Around half of all cases occur with small-cell lung cancer. This strong link makes it a typical paraneoplastic syndrome. In the rest of the cases, no cancer is present. These cases appear to be caused purely by an immune system problem. Early diagnosis is essential, not just to manage symptoms but also to find hidden cancer that may not yet show signs. This disorder affects the presynaptic part of the nerve-muscle junction. That sets it apart from myasthenia gravis, which targets the postsynaptic side. The difference is important, as it changes how doctors diagnose and treat each condition. While both cause muscle weakness, the patterns of weakness and progression differ. This contrast helps doctors tell them apart. Clinical importance of the overview of Lambert-Eaton myasthenic syndrome Patients often feel weak in their hips and thighs at first. They may struggle to walk, stand up, or climb stairs. Many also report dry mouth, constipation, trouble with erections, or sweating problems. These symptoms show that the autonomic nervous system may also be involved. In some cases, these symptoms appear before any cancer signs and serve as early warnings. Because Lambert-Eaton myasthenic syndrome often links to cancer, diagnosing it can lead to the discovery of a hidden tumour. Most often, this is a small-cell lung carcinoma. Detecting cancer early improves both cancer and neuromuscular outcomes. On the other hand, if there’s no cancer, the focus shifts to controlling the immune system and easing symptoms. Even though it’s serious, Lambert-Eaton myasthenic syndrome is manageable. Better understanding of the disease has led to more accurate tests and improved treatments. With early diagnosis and the right care, many patients feel stronger and live better lives. This overview of Lambert-Eaton myasthenic syndrome sets the stage for a deeper look at what causes it, how it shows up, how it is diagnosed, and how it is treated. Whether you’re a patient, caregiver, or health professional, knowing more about the condition helps improve care and support. [Next: Causes of Lambert-Eaton myasthenic syndrome →]

Overview of Lambert-Eaton myasthenic syndrome Read More »

Causes of Lambert-Eaton myasthenic syndrome

Causes of Lambert-Eaton myasthenic syndrome

Lambert-Eaton myasthenic syndrome is caused by an autoimmune attack on the nervous system, specifically targeting voltage-gated calcium channels (VGCCs) located at the presynaptic terminals of motor neurons. This immune system attack blocks the release of acetylcholine. That’s the chemical needed to make muscles move. Without enough of it, muscles become weak. This weakness usually starts in the arms or legs and gets worse over time. Doctors group Lambert-Eaton myasthenic syndrome into two types based on the root cause: paraneoplastic and non-paraneoplastic. The paraneoplastic type shows up in around 50 to 60% of people. It usually links to small-cell lung cancer (SCLC). In these cases, the immune system reacts to proteins in the cancer but also attacks nerve cells by mistake. So while the body tries to fight the cancer, it also harms the nervous system. The strong link between cancer and LEMS In small-cell lung cancer, the tumour produces proteins that look like VGCCs. This similarity tricks the immune system. It begins to fight both the tumour and the calcium channels. As a result, nerve signals don’t reach muscles. This is how the cancer ends up causing weakness. Smoking makes things worse. Since it’s the top cause of small-cell lung cancer, it indirectly raises the risk of getting Lambert-Eaton myasthenic syndrome. On the other hand, non-paraneoplastic Lambert-Eaton myasthenic syndrome happens with no cancer. Doctors don’t always know what starts it. But even in this form, the body still makes harmful antibodies that target VGCCs. Many of these patients also have other autoimmune diseases, like type 1 diabetes, hypothyroidism, or rheumatoid arthritis. This pattern shows that the immune system is off balance in more than one way. Genetic and environmental causes of Lambert-Eaton myasthenic syndrome Family history may play a role too. Certain genes, especially human leukocyte antigen (HLA) types, may raise the risk. These same genes appear in other autoimmune diseases. Though we don’t have strong proof yet, the idea of inherited risk is gaining ground. Besides genes, the environment might also trigger Lambert-Eaton myasthenic syndrome. Some infections confuse the immune system. For example, a virus or bacteria may look like a body cell. The immune system then makes a mistake and attacks the body instead. While we’re not sure infections cause LEMS directly, they might help start the problem in people who already have the wrong genes. Other possible causes of Lambert-Eaton myasthenic syndrome Another theory points to chemicals or toxins. People exposed to certain harmful agents—like heavy metals, solvents, or cancer-causing chemicals at work—might face higher risk. These toxins may damage the immune system or increase cancer risk, both of which link back to Lambert-Eaton myasthenic syndrome. A key feature of the condition is that it targets the presynaptic side of the nerve-muscle connection. That’s different from conditions like myasthenia gravis, which affects the postsynaptic side. Knowing this helps doctors run the right tests and choose better treatments. In the end, the causes of Lambert-Eaton myasthenic syndrome fall into two main groups. One relates to cancer, mostly small-cell lung cancer. The other involves the immune system going wrong without any cancer. Finding the exact cause helps shape the right treatment. For cancer-linked cases, spotting the tumour early improves both survival and nerve recovery. For the idiopathic type, calming the immune system becomes the main goal. Understanding the causes of Lambert-Eaton myasthenic syndrome guides care By knowing more about the causes of Lambert-Eaton myasthenic syndrome, doctors can respond faster and choose treatments that work best. Whether it starts from cancer, genes, infections, or unknown reasons, early diagnosis and action make a big difference. [Next: Symptoms of Lambert-Eaton myasthenic syndrome →]

Causes of Lambert-Eaton myasthenic syndrome Read More »

Symptoms of Lambert-Eaton myasthenic syndrome

Symptoms of Lambert-Eaton myasthenic syndrome

Lambert-Eaton myasthenic syndrome presents with a distinctive pattern of symptoms, primarily affecting muscle strength and autonomic function. The hallmark of Lambert-Eaton myasthenic syndrome is slowly worsening muscle weakness. It usually starts in the large muscles near the body’s centre, like the hips, thighs, and shoulders. Over time, this weakness makes everyday activities harder. Walking, climbing stairs, or lifting things can become difficult. Although the symptoms might look like other nerve and muscle conditions, LEMS has some unique signs. These differences help doctors tell it apart from conditions like myasthenia gravis or muscular dystrophy. One of the first and most common signs is trouble standing up from a chair or getting out of bed. This happens because the thigh and hip muscles lose strength. People also find it hard to lift their arms overhead. That makes grooming, dressing, or carrying even light items a struggle. The weakness often shows up on both sides of the body at the same time. As the condition gets worse, it may spread to the upper arms, neck, and chest. However, in most people, the face and eye muscles stay strong. Muscle weakness and improvement with use in Lambert-Eaton myasthenic syndrome Unlike myasthenia gravis, where muscles get weaker the more they’re used, Lambert-Eaton myasthenic syndrome shows something different called facilitation. This means that using the muscle briefly can actually make it stronger for a short time. For example, someone may have trouble starting to walk but can take stronger steps after a few tries. This odd improvement often surprises both patients and doctors. It also helps in making the right diagnosis. Another important part of Lambert-Eaton myasthenic syndrome is the way it affects the autonomic nervous system. These symptoms may come before or along with muscle weakness. They are also very helpful in telling LEMS apart from other muscle conditions. The most common of these symptoms is a dry mouth, which affects more than 80% of people with LEMS. Other signs include constipation, blurry vision, less sweating, and problems with erections in men. These symptoms happen because of poor nerve signals to automatic body systems. They can lower someone’s quality of life a lot. Autonomic symptoms and other early warning signs Some people feel very tired, even when they haven’t done much. This can be mistaken for depression or chronic fatigue in the beginning. In a few cases, people may also have a hoarse voice or slight trouble swallowing. But these symptoms are not as common or as strong as they are in other muscle diseases. Eye and breathing muscles usually stay unaffected. Still, if LEMS goes untreated or becomes severe, it may affect more areas. The start of Lambert-Eaton myasthenic syndrome can be slow or sudden. In cases linked to cancer—especially small-cell lung cancer—symptoms often get worse fast. This leads to quicker loss of strength and nerve function. On the other hand, when cancer is not involved, the symptoms may develop over many months. This slow start often causes delays in getting the right diagnosis because the signs are easy to miss at first. Many people say their symptoms are worse in the morning and get a bit better later in the day. A short amount of activity can help ease the weakness. This daily pattern of ups and downs can be confused with conditions like fibromyalgia or arthritis. That’s why it’s so important for doctors to carefully look at how symptoms change and grow over time when they see someone with ongoing weakness. Diagnostic confusion and long-term effects of Lambert-Eaton myasthenic syndrome Sometimes, people also notice a mild tremor or muscle cramps. These signs are not as common but can make diagnosis harder. Over time, some muscles—especially in the thighs and upper arms—may shrink. This happens from both lack of use and long-term nerve problems. Because the symptoms of Lambert-Eaton myasthenic syndrome can be so mixed, doctors may not spot it right away. Many patients are first told they have depression, chronic tiredness, or weakness from aging. That’s why doctors need to look closely at symptoms, watch how they change, and do the right tests. Living with the condition can also affect a person’s emotions. Ongoing weakness and tiredness can lead to worry, frustration, and staying away from others. This is even more likely if the condition gets diagnosed late or is not treated well. It’s important to care for both the body and mind in people with LEMS. To sum up, Lambert-Eaton myasthenic syndrome usually shows up with muscle weakness in the hips, shoulders, and thighs. It often includes strange muscle improvement after short use and problems like dry mouth and constipation. These signs—especially in older people or smokers—should alert doctors to check for LEMS and any hidden cancer. Finding the problem early leads to faster treatment, better symptom control, and, when cancer is involved, quicker action to treat it.  [Next: Diagnosis of Lambert-Eaton myasthenic syndrome →]

Symptoms of Lambert-Eaton myasthenic syndrome Read More »

Diagnosis of Lambert-Eaton myasthenic syndrome

Diagnosis of Lambert-Eaton myasthenic syndrome

Lambert-Eaton myasthenic syndrome is a rare autoimmune condition, and diagnosing it can be challenging due to its subtle onset and overlap with other neuromuscular disorders. Early diagnosis of Lambert-Eaton myasthenic syndrome is crucial. It helps begin effective treatment and detect related cancers—especially small-cell lung carcinoma. Diagnosis involves a mix of clinical evaluation, lab tests, nerve studies, and cancer screening. Clinical signs help start the diagnosis of Lambert-Eaton myasthenic syndrome The process starts with a full clinical assessment. A neurologist will take a detailed medical history. They focus on muscle weakness patterns and autonomic symptoms like dry mouth, constipation, erectile issues, or blurry vision. A key sign is muscle weakness that gets better briefly with exercise. This is called post-exercise facilitation. It helps set Lambert-Eaton apart from myasthenia gravis, where strength declines with activity. During a physical exam, weakness shows up in the upper arms and thighs. Reflexes may seem absent at first but often return after brief movement. This recovery of tendon reflexes is another clue. In contrast, myasthenia gravis usually features steady reflexes and no strength rebound. Nerve studies confirm the diagnosis of Lambert-Eaton myasthenic syndrome If signs point to Lambert-Eaton, doctors order nerve studies. Repetitive nerve stimulation (RNS) and electromyography (EMG) are the main tools. In RNS, doctors stimulate a nerve at low frequency and measure the muscle’s response. In Lambert-Eaton, this response starts weak but then increases sharply—often by over 100%—after brief high-frequency stimulation or exercise. This sharp rise, called an incremental response, is a hallmark of the condition. EMG tests can also help. Single-fibre EMG, used more in myasthenia gravis, may still detect transmission problems in Lambert-Eaton. It may show “jitter” or missed signals, though less often. Still, RNS remains the best nerve test for this disease. Antibody testing supports the diagnosis of Lambert-Eaton myasthenic syndrome Blood tests help confirm the autoimmune cause. Most patients—about 85–90%—have antibodies against P/Q-type voltage-gated calcium channels (VGCCs). These antibodies are very specific to Lambert-Eaton and rarely show up in other diseases. Doctors might also check for other antibodies, like anti-Hu or anti-CRMP5. These appear more in small-cell lung cancer. If found, they increase the need for urgent cancer checks. Cancer screening is vital in diagnosis of Lambert-Eaton myasthenic syndrome Because Lambert-Eaton often links to small-cell lung cancer, doctors always screen for cancer. This starts with a high-resolution chest CT scan. If results are unclear but suspicion remains high, doctors may order a PET scan or MRI. In high-risk people—especially older adults with a history of smoking—repeat scans every 3–6 months for two years may be needed to catch any hidden cancer early. Doctors must rule out conditions that mimic Lambert-Eaton myasthenic syndrome It is important to tell Lambert-Eaton apart from other nerve and muscle problems. Myasthenia gravis and peripheral neuropathies often look similar. Mistaking one for the other can delay care and miss a cancer diagnosis. Clues like reflex changes and muscle facilitation help. Blood and nerve test results provide the strongest evidence to confirm the diagnosis. Sometimes, a muscle biopsy is done. However, this is rare in Lambert-Eaton. The problem lies in nerve-to-muscle signals—not in the muscle itself. If doctors suspect a second muscle disorder, a biopsy might add useful information. Routine blood markers like ESR and CRP are usually normal. Even so, doctors may test for thyroid function or other autoimmune issues. Non-cancer forms of Lambert-Eaton may appear alongside type 1 diabetes, lupus, or thyroid disease. A team approach helps manage the diagnosis of Lambert-Eaton myasthenic syndrome Once the diagnosis is clear, the patient usually sees a team of experts. This team includes neurologists, oncologists, immunologists, and physiotherapists. Working together ensures both the nerve symptoms and possible cancer get the right attention. Early diagnosis of Lambert-Eaton myasthenic syndrome improves outcomes. Treatment can ease symptoms and slow the disease. In cancer-linked cases, treating the tumour may even reverse the nerve problems. In other cases, a clear diagnosis opens the door to immunotherapy and supportive care. Diagnosing Lambert-Eaton myasthenic syndrome relies on clinical signs, nerve studies, antibody tests, and cancer screening. Catching it early leads to better symptom control and may uncover cancer at a stage when it can still be treated. [Next: Treatment of Lambert-Eaton myasthenic syndrome →]

Diagnosis of Lambert-Eaton myasthenic syndrome Read More »

Treatment of Lambert-Eaton myasthenic syndrome

Treatment of Lambert-Eaton myasthenic syndrome

Lambert-Eaton myasthenic syndrome is a treatable condition, and with early intervention, many patients experience significant improvement in muscle strength and daily functioning. The treatment of Lambert-Eaton myasthenic syndrome involves a dual approach: addressing the underlying cause—especially if cancer is present—and managing the neuromuscular symptoms through medication and supportive therapies. The specific treatment plan depends on whether the patient has paraneoplastic or non-paraneoplastic LEMS, as well as the severity of their symptoms. Cancer-focused treatment of Lambert-Eaton myasthenic syndrome For individuals with paraneoplastic Lambert-Eaton myasthenic syndrome, managing the associated cancer is the top priority. This is usually small-cell lung cancer (SCLC). Chemotherapy and radiotherapy aimed at shrinking or eliminating the tumour can often improve LEMS symptoms. In many cases, muscle strength returns after the cancer responds to treatment. This highlights the importance of early cancer screening and fast oncological care for every LEMS diagnosis. Once cancer is treated or if no cancer is found, the focus shifts to strengthening muscles and calming the immune response. The most common treatment for symptoms is amifampridine, also known as 3,4-diaminopyridine or 3,4-DAP. This drug boosts acetylcholine release at nerve endings, helping muscles work better despite damaged calcium channels. Many patients notice stronger muscles and better stamina with this medication. Amifampridine usually works well, but side effects can occur. These include tingling, stomach pain, and, in rare cases, seizures. Doctors must carefully adjust the dose and monitor patients. In some places, this drug may be hard to access. In such cases, doctors may use compounded versions or alternatives like guanidine hydrochloride, though these have more risks and don’t work as well. Immunotherapy and supportive treatment of Lambert-Eaton myasthenic syndrome If symptoms persist or the patient has non-paraneoplastic LEMS, immune suppression may be needed. Corticosteroids like prednisone are often used first. Doctors may also prescribe other drugs such as azathioprine, cyclophosphamide, or mycophenolate mofetil. These medications lower the immune system’s activity, reducing the production of harmful antibodies. However, they come with risks. Patients need regular check-ups to watch for infections, liver problems, or low blood cell counts. Another option is intravenous immunoglobulin (IVIG) therapy. This involves giving antibodies from healthy donors to calm the immune system. IVIG helps when symptoms worsen quickly or before surgery. Although costly and not a long-term fix, it often improves symptoms for a short time and can be repeated during relapses. Plasmapheresis, also called plasma exchange, removes damaging antibodies from the blood. It acts fast and is useful in severe cases or when IVIG doesn’t work. However, its effects are temporary, so doctors usually follow it with long-term immune treatments. Rehabilitation and holistic care in Lambert-Eaton myasthenic syndrome Patients with milder symptoms or those who respond to amifampridine can benefit from regular physiotherapy. Muscle weakness can cause inactivity, which leads to further loss of strength. A custom exercise plan from a physiotherapist helps maintain mobility, balance, and confidence. Occupational therapy also plays a key role. Therapists teach energy-saving techniques and recommend tools or home changes to make daily life easier. These adjustments can preserve independence, especially in people with long-term or changing symptoms. Lifestyle choices matter too. A healthy diet, quitting smoking, and staying hydrated all support treatment. Avoiding tobacco is critical because it increases the risk of small-cell lung cancer. For symptoms like dry mouth, patients can try sugar-free lozenges, frequent sips of water, or saliva substitutes. Other issues, such as constipation or erectile dysfunction, may need extra treatment or lifestyle changes. Patients should feel comfortable discussing these concerns with their doctor. Long-term treatment and research in Lambert-Eaton myasthenic syndrome Mental health support is essential. Coping with a rare disease can be stressful and isolating. Counselling, support groups, and mental health services can help patients deal with anxiety, depression, or loneliness. These emotional challenges often feel heavier when cancer is also present. Because Lambert-Eaton myasthenic syndrome is a long-term condition, regular check-ups with a neurologist are vital. Ongoing monitoring helps ensure that treatments still work, side effects are under control, and new symptoms are managed early. For patients with cancer, follow-up is especially important since cancer relapse can worsen LEMS symptoms. Researchers are exploring new treatments that target the immune system with fewer side effects. One option under study is rituximab, a biologic used in other autoimmune diseases. Although not yet standard care, this drug may become part of future personalised therapies for LEMS. In summary, the treatment of Lambert-Eaton myasthenic syndrome needs a broad and tailored strategy. Cancer treatment is key in paraneoplastic cases and often improves symptoms. For all patients, drugs like amifampridine, immune therapies, IVIG, or plasmapheresis form the foundation of symptom management. Physical therapy, occupational help, mental health care, and lifestyle support all contribute to a plan that improves both health and quality of life. [Next: Complications of Lambert-Eaton myasthenic syndrome →]

Treatment of Lambert-Eaton myasthenic syndrome Read More »

Scroll to Top