Mental Matters

Health Conditions

Find information on various health conditions affecting people of all ages. This category covers causes, symptoms, diagnosis, and management options for physical illnesses and chronic diseases. Get insights to help you understand different health challenges and make informed decisions about your wellbeing.

Woman clutching stomach and head in pain, showing symptoms of chronic pancreatitis.

Symptoms of Chronic Pancreatitis

Symptoms of Chronic Pancreatitis Symptoms of chronic pancreatitis often develop gradually but can become severe and debilitating over time. As chronic pancreatitis progresses, the pancreas loses its ability to produce digestive enzymes and hormones, leading to both digestive and metabolic problems. 1. Abdominal Pain Chronic, upper abdominal pain is the hallmark symptom. It may radiate to the back, worsen after eating, or become constant in advanced stages. Pain can be dull, burning, or sharp, and often significantly impacts quality of life. 2. Nausea and Vomiting These symptoms often accompany flare-ups or episodes of increased inflammation. In some cases, vomiting may be linked to complications like gastric outlet obstruction or severe malabsorption. 3. Weight Loss | Symptoms of Chronic Pancreatitis Weight loss is common, often due to reduced appetite, chronic pain, or malabsorption of fats and nutrients. Despite eating normally, patients may struggle to maintain body weight. 4. Fatty, Greasy Stools (Steatorrhoea) When the pancreas fails to produce enough digestive enzymes, fats are not properly broken down. This leads to pale, foul-smelling, greasy stools that may float and are difficult to flush. This symptom becomes more common in later stages. 5. Bloating and Indigestion Pancreatic insufficiency leads to poor digestion of proteins, fats, and carbohydrates. This causes bloating, excessive gas, and a sensation of fullness after small meals. 6. Diabetes As insulin-producing cells are damaged, patients may develop diabetes mellitus. Known as type 3c diabetes, this form arises due to loss of pancreatic endocrine function and can be difficult to control. 7. Fatigue | Symptoms of Chronic Pancreatitis Fatigue stems from poor nutritional absorption, pain, and sleep disturbance. Ongoing discomfort can disrupt rest and reduce physical stamina. 8. Jaundice (in rare cases) If a blocked bile duct accompanies the pancreatic inflammation, yellowing of the skin and eyes may occur. This requires prompt evaluation to rule out complications like cancer. Recognising symptoms of chronic pancreatitis early allows for quicker diagnosis, treatment, and nutritional support. Persistent abdominal pain, weight loss, and greasy stools should prompt investigation, especially in individuals with known risk factors like alcohol use or prior pancreatitis. [Next: Diagnosis of Chronic Pancreatitis →]

Symptoms of Chronic Pancreatitis Read More »

Doctor examining pancreas through magnifying glass representing chronic pancreatitis diagnosis.

Diagnosis of Chronic Pancreatitis

Diagnosis of Chronic Pancreatitis Diagnosis of chronic pancreatitis involves a combination of clinical evaluation, imaging, and laboratory tests. Since this pancreatitis progresses gradually and can mimic other gastrointestinal disorders, accurate diagnosis may be delayed, especially in early stages. 1. Medical History and Physical Examination Doctors begin by reviewing symptoms, alcohol use, smoking, family history, and any prior episodes of acute pancreatitis. Physical examination may reveal upper abdominal tenderness or signs of malnutrition such as weight loss and muscle wasting. 2. Blood Tests | Diagnosis of Chronic Pancreatitis Routine blood tests may show elevated levels of pancreatic enzymes (amylase and lipase), though these are often normal in chronic cases. Other tests assess liver function, blood sugar levels, calcium, and triglycerides. 3. Faecal Elastase Test This stool test measures the amount of pancreatic enzyme elastase. Low levels indicate exocrine insufficiency, suggesting advanced disease. 4. Imaging Tests 5. Pancreatic Function Tests These assess the ability of the pancreas to produce enzymes. Direct tests, such as secretin stimulation, are more accurate but less commonly used due to complexity. 6. Genetic Testing | Diagnosis of Chronic Pancreatitis If hereditary pancreatitis is suspected, genetic testing for PRSS1, CFTR, and SPINK1 mutations may be performed, particularly in younger patients. 7. Biopsy (if needed) A biopsy may be done if cancer is suspected or if imaging reveals suspicious masses. This helps distinguish chronic pancreatitis from pancreatic cancer. Accurate diagnosis of chronic pancreatitis is crucial to guide treatment, prevent complications, and improve quality of life. Early intervention with enzyme replacement, pain control, and lifestyle modification can dramatically affect long-term outcomes. [Next: Treatment of Chronic Pancreatitis →]

Diagnosis of Chronic Pancreatitis Read More »

Woman experiencing abdominal pain due to chronic pancreatitis complications.

Complications and Recovery from Chronic Pancreatitis

Complications and Recovery from Chronic Pancreatitis Complications and recovery from chronic pancreatitis are closely linked to disease severity, duration, and how well treatment is managed. While this pancreatitis is progressive and irreversible, early intervention and consistent care can minimise complications and enhance recovery. 1. Pancreatic Insufficiency As damage accumulates, the pancreas can no longer produce enough enzymes for digestion. This leads to malnutrition, vitamin deficiencies, and significant weight loss unless enzyme supplements are used. 2. Diabetes Mellitus Pancreatic endocrine cells are destroyed over time, leading to type 3c diabetes. This form of diabetes may be brittle and harder to manage due to concurrent malabsorption and fluctuating insulin needs. 3. Pseudocysts | Complications and Recovery from Chronic Pancreatitis Fluid-filled sacs may form within or near the pancreas. Small pseudocysts often resolve on their own, but larger ones may require drainage to prevent infection or rupture. 4. Bile Duct Obstruction Scarring or inflammation can block the bile duct, causing jaundice. In some cases, stenting or surgery is needed to restore normal bile flow. 5. Chronic Pain Persistent pain affects daily functioning and quality of life. Some patients become dependent on opioids, which carry risks of addiction and side effects. Pain clinics and multidisciplinary management are essential. 6. Increased Cancer Risk Chronic inflammation is a known risk factor for pancreatic cancer. Though the risk is relatively small, regular monitoring is advised, especially in hereditary cases or long-standing disease. 7. Osteoporosis | Complications and Recovery from Chronic Pancreatitis Fat malabsorption impairs calcium and vitamin D absorption, increasing the risk of osteoporosis and fractures. Bone density scans and supplements may be recommended. Recovery Outlook Although full reversal is not possible, many patients experience improved quality of life with proper care. Recovery focuses on symptom control, nutritional rehabilitation, and psychosocial support. Education, consistent follow-up, and support groups play a vital role in helping individuals adjust to chronic illness. Many patients with good adherence to therapy are able to work, travel, and maintain meaningful activities. In conclusion, complications and recovery from chronic pancreatitis require ongoing, personalised care. With the right support and treatment strategy, many people can manage the condition effectively and avoid further decline. [Next: Back to Overview→]

Complications and Recovery from Chronic Pancreatitis Read More »

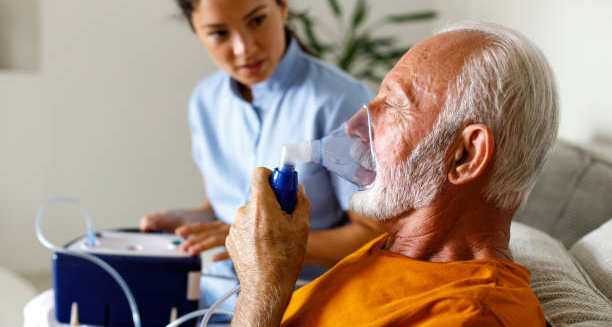
Elderly man with COPD using a nebuliser at home, assisted by a nurse.

Chronic Obstructive Pulmonary Disease

Chronic Obstructive Pulmonary Disease (COPD) – Overview Chronic obstructive pulmonary disease is a long-term respiratory condition that causes airflow blockage and breathing-related problems. It includes both emphysema and chronic bronchitis, making this disease (COPD) one of the leading causes of illness and death worldwide. The disease develops gradually, with symptoms often going unnoticed until significant lung damage has occurred. COPD occurs when the lungs become inflamed and damaged, usually due to long-term exposure to harmful substances like cigarette smoke or air pollutants. The damage leads to narrowing of the airways and destruction of lung tissue, making it increasingly difficult to breathe. People with COPD often struggle to exhale fully, causing air to become trapped in the lungs. The disease is most common in people over the age of 40 and in smokers or former smokers. It can also affect non-smokers exposed to occupational dust, fumes, or indoor pollution from biomass fuels used for cooking or heating. Genetics also play a role; a rare inherited condition known as alpha-1 antitrypsin deficiency can increase susceptibility to COPD. Chronic Obstructive Pulmonary Disease (COPD) Symptoms develop slowly over years and include shortness of breath, persistent cough with phlegm, wheezing, and frequent respiratory infections. Over time, daily activities like walking, climbing stairs, or even talking can become difficult. Although COPD cannot be cured, it can be managed effectively with lifestyle changes, medications, and pulmonary rehabilitation. Early diagnosis and intervention are key to slowing progression and improving quality of life. In summary, this chronic disease is a preventable and treatable lung condition that limits airflow and causes breathing difficulties. With proper care and ongoing management, many people with COPD can continue leading active and fulfilling lives. [Next: Causes of Chronic Obstructive Pulmonary Disease →]

Chronic Obstructive Pulmonary Disease Read More »

Industrial smoke polluting the air, contributing to causes of chronic obstructive pulmonary disease.

Causes of Chronic Obstructive Pulmonary Disease

Causes of Chronic Obstructive Pulmonary Disease Causes of chronic obstructive pulmonary disease are mainly related to long-term exposure to harmful particles or gases that damage the lungs. While smoking remains the most significant risk factor, other causes contribute to the global burden of thisdisease, especially in low- and middle-income countries. 1. Smoking Tobacco Cigarette smoking is the leading cause of COPD. Around 85–90% of cases are linked to current or past tobacco use. The harmful chemicals in cigarette smoke inflame and destroy lung tissue, causing irreversible damage to airways and alveoli. Smoking cigars, pipes, and even marijuana can also contribute to COPD. 2. Exposure to Air Pollutants Long-term exposure to air pollution, especially fine particulate matter from vehicles or industrial sources, increases the risk of developing COPD. Indoor pollution from biomass fuel used for cooking and heating in poorly ventilated homes is a major contributor in many countries. 3. Occupational Hazards Jobs involving exposure to dust, vapours, chemicals, or fumes (e.g. in mining, construction, and agriculture) have been associated with a higher incidence of COPD. Prolonged inhalation of these substances irritates and inflames the lungs. 4. Genetic Factors A rare inherited condition called alpha-1 antitrypsin deficiency affects the production of a protein that protects the lungs from damage. Individuals with this condition may develop COPD at a younger age, even if they have never smoked. Genetic predisposition may also make some smokers more vulnerable to lung damage than others. 5. Respiratory Infections Repeated lung infections during childhood, especially in early years, may contribute to the development of COPD later in life. Infections can impair lung growth and resilience, increasing susceptibility to damage from pollutants or smoking. 6. Ageing and Gender | Causes of Chronic Obstructive Pulmonary Disease While not direct causes, ageing increases vulnerability to COPD due to natural decline in lung function. Men were historically more affected, but rates in women are rising, partly due to increased smoking among females and biological susceptibility to smoke-related damage. Understanding the causes of chronic obstructive pulmonary disease helps guide prevention efforts. Avoiding smoking, limiting exposure to pollutants, and identifying those with genetic risk can all reduce incidence. Public health interventions targeting indoor air quality and occupational safety are also vital. [Next: Symptoms of Chronic Obstructive Pulmonary Disease →]

Causes of Chronic Obstructive Pulmonary Disease Read More »

Woman coughing persistently, showing symptoms of chronic obstructive pulmonary disease.

Symptoms of Chronic Obstructive Pulmonary Disease

Symptoms of Chronic Obstructive Pulmonary Disease Symptoms of chronic obstructive pulmonary disease often develop gradually, and many people don’t realise they have it until significant lung damage has occurred. Because this disease worsens over time, recognising symptoms early can make a big difference in managing the disease and preserving lung function. 1. Shortness of Breath (Dyspnoea) This is the most common and progressive symptom. It typically starts during physical activity and worsens over time, eventually occurring even at rest. Patients often describe it as a feeling of “air hunger” or not getting enough air. 2. Persistent Cough A chronic cough that produces mucus (also called a smoker’s cough) is a hallmark symptom of COPD. This cough may appear years before other symptoms and often worsens in the morning or during cold weather. 3. Sputum Production Increased mucus production is caused by inflammation and excess secretions in the airways. The sputum may be clear, white, yellow, or green, depending on infection or inflammation levels. 4. Wheezing A whistling or squeaky sound when breathing, especially during exhalation, is caused by narrowed or inflamed airways. Wheezing may become more noticeable during infections or exercise. 5. Frequent Respiratory Infections People with COPD are more susceptible to bronchitis, pneumonia, and the common cold. Infections can trigger flare-ups (exacerbations), leading to worsening symptoms and hospitalisation. 6. Chest Tightness | Symptoms of Chronic Obstructive Pulmonary Disease Some individuals experience a sense of pressure or tightness in the chest, often triggered by exertion or cold air. This may be mistaken for heart-related issues and requires proper diagnosis. 7. Fatigue and Loss of Energy Reduced oxygen levels, especially during exertion, can lead to chronic fatigue and reduced stamina. Activities of daily living become exhausting, affecting independence and quality of life. 8. Unintended Weight Loss In advanced stages, the body works harder to breathe, burning more calories. This can result in weight loss and muscle wasting, particularly in the arms and legs. Recognising symptoms of chronic obstructive pulmonary disease early is vital. Anyone with a persistent cough, breathlessness, or history of smoking should seek medical advice. Early intervention, even in mild cases, can greatly improve outcomes and reduce complications. [Next: Diagnosis of Chronic Obstructive Pulmonary Disease →]

Symptoms of Chronic Obstructive Pulmonary Disease Read More »

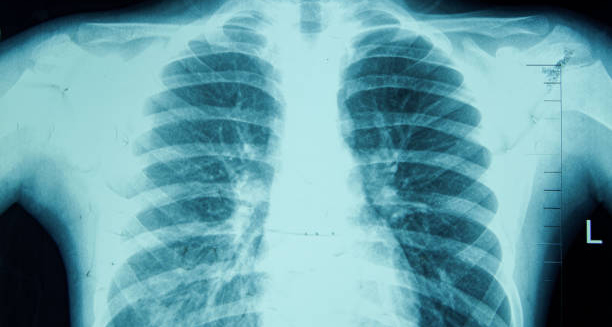
Chest X-ray showing lung damage associated with chronic obstructive pulmonary disease.

Diagnosis of Chronic Obstructive Pulmonary Disease

Diagnosis of Chronic Obstructive Pulmonary Disease Diagnosis of chronic obstructive pulmonary disease involves evaluating medical history, assessing symptoms, and conducting specific lung function tests. Because this disease shares symptoms with other respiratory conditions like asthma or heart failure, a thorough evaluation is essential for an accurate diagnosis. 1. Medical History and Physical Examination The first step involves reviewing the patient’s history of smoking, exposure to occupational dust or fumes, and frequency of respiratory infections. A physical exam may reveal signs such as wheezing, prolonged expiration, or reduced breath sounds. 2. Spirometry (Lung Function Test) Spirometry is the gold standard for diagnosing COPD. The test measures how much air a person can breathe out in one second (FEV1) and the total amount exhaled (FVC). A reduced FEV1/FVC ratio (below 70%) confirms airflow limitation characteristic of COPD. 3. Chest X-Ray or CT Scan | Diagnosis of Chronic Obstructive Pulmonary Disease Imaging tests can rule out other conditions like lung cancer, tuberculosis, or heart disease. They may show lung overinflation, flattened diaphragms, or enlarged air spaces typical of emphysema. 4. Arterial Blood Gas Analysis In advanced COPD or during exacerbations, blood tests may be done to measure oxygen and carbon dioxide levels. Low oxygen and high CO₂ levels suggest severe disease and guide oxygen therapy decisions. 5. Alpha-1 Antitrypsin Deficiency Test If COPD is diagnosed in a person under 45 or without a smoking history, this blood test may be ordered to check for inherited enzyme deficiencies that cause early-onset lung damage. 6. Six-Minute Walk Test | Diagnosis of Chronic Obstructive Pulmonary Disease This assesses the functional impact of COPD by measuring how far a person can walk in six minutes. It also helps determine if supplemental oxygen is needed during exertion. 7. Blood and Sputum Tests These tests may help rule out infection or other underlying diseases. Sputum cultures can detect bacterial causes of chronic bronchitis or infections during flare-ups. An early and accurate diagnosis allows for effective treatment planning. Once diagnosed, the disease is staged according to severity, guiding interventions and monitoring over time. [Next: Treatment of Chronic Obstructive Pulmonary Disease →]

Diagnosis of Chronic Obstructive Pulmonary Disease Read More »

Woman breaking a cigarette in half as part of chronic obstructive pulmonary disease treatment.

Treatment of Chronic Obstructive Pulmonary Disease

Treatment of Chronic Obstructive Pulmonary Disease Treatment of chronic obstructive pulmonary disease focuses on relieving symptoms, slowing disease progression, preventing complications, and improving quality of life. Although chronic obstructive pulmonary disease is irreversible, a combination of medications, therapies, and lifestyle changes can significantly improve daily function and outcomes. 1. Smoking Cessation The most important step in managing COPD is quitting smoking. Stopping smoking slows lung function decline and improves response to medication. Behavioural therapy, nicotine replacement, and prescription medications can help with cessation. 2. Bronchodilators These medications relax the muscles around the airways, making breathing easier. They are usually inhaled and include: 3. Inhaled Corticosteroids Used in combination with bronchodilators, corticosteroids reduce airway inflammation and the frequency of exacerbations. They are not usually prescribed alone due to potential side effects. 4. Combination Inhalers Many patients benefit from inhalers that combine two or more medications, such as long-acting bronchodilators and steroids, for convenience and enhanced effect. 5. Pulmonary Rehabilitation A supervised programme of exercise, education, and breathing techniques improves lung efficiency, muscle strength, and confidence in managing symptoms. It can greatly reduce hospital admissions and fatigue. 6. Oxygen Therapy For patients with chronically low blood oxygen levels, supplemental oxygen improves survival and quality of life. It may be used continuously or only during exertion or sleep. 7. Vaccinations | Treatment of Chronic Obstructive Pulmonary Disease Influenza and pneumococcal vaccines help prevent infections that can cause severe flare-ups or hospitalisation. 8. Surgical Options In selected patients with severe emphysema, surgery may be considered. This includes lung volume reduction surgery or, rarely, lung transplantation in younger individuals with end-stage disease. Treatment of chronic obstructive pulmonary disease is most effective when it includes lifestyle modification, medication adherence, and regular follow-up. Education and support empower patients to manage their symptoms and stay active. [Next: Complications and Recovery from Chronic Obstructive Pulmonary Disease →]

Treatment of Chronic Obstructive Pulmonary Disease Read More »

Woman coughing and wrapped in a blanket, showing complications of chronic obstructive pulmonary disease.

Complications and Recovery from Chronic Obstructive Pulmonary Disease

Complications and Recovery from Chronic Obstructive Pulmonary Disease Complications and recovery from chronic obstructive pulmonary disease vary depending on disease severity, treatment adherence, and lifestyle factors. Although this is progressive, many patients can reduce complications and enjoy meaningful recovery through proactive management. 1. Exacerbations Flare-ups or exacerbations are episodes of worsening symptoms often triggered by infections or environmental irritants. They can lead to hospitalisation and accelerate lung function decline. Preventing exacerbations is a primary goal of COPD treatment. 2. Respiratory Failure In advanced COPD, gas exchange becomes impaired. This may result in chronic low oxygen (hypoxaemia) and high carbon dioxide (hypercapnia) levels, requiring long-term oxygen therapy or non-invasive ventilation. 3. Heart Problems COPD increases the risk of heart disease, especially right-sided heart failure (cor pulmonale) due to strain on the heart from lung dysfunction. This complication may require diuretics or additional heart medications. 4. Pneumonia and Other Infections People with COPD are more prone to pneumonia, bronchitis, and influenza, which can be life-threatening. Vaccination and prompt treatment of infections are essential. 5. Depression and Anxiety Living with chronic breathlessness and declining physical ability can lead to mental health issues. Support groups, counselling, and appropriate medication can help address emotional challenges. 6. Weight Loss and Muscle Wasting Advanced COPD increases energy demands while reducing appetite, leading to weight loss. Nutritional counselling and exercise can slow this process and restore strength. Recovery and Management | Complications and Recovery from Chronic Obstructive Pulmonary Disease While full recovery from COPD is not possible, symptom control and improved functional ability are achievable. With the right treatment plan: Rehabilitation, medication optimisation, smoking cessation, and caregiver support all contribute to meaningful improvements. In conclusion, complications require long-term commitment. With a structured plan and proactive care, patients can slow disease progression, prevent hospitalisations, and maintain quality of life. [Next: Back to Overview →]

Complications and Recovery from Chronic Obstructive Pulmonary Disease Read More »

Yellow radiation warning flag symbolising environmental causes of chronic myeloid leukaemia.

Chronic Myeloid Leukaemia

Chronic Myeloid Leukaemia – Overview Chronic myeloid leukaemia is a slow-growing cancer of the bone marrow and blood that primarily affects adults. Although this leukaemia (CML) may initially develop with few or no symptoms. It is a serious condition that, if left untreated, can progress to more aggressive phases resembling acute leukaemia. It represents approximately 15% of all adult leukaemias and most commonly occurs in individuals aged 50 to 70. CML begins in the bone marrow, where blood cells are produced. A genetic mutation occurs in a stem cell, producing an abnormal chromosome known as the Philadelphia chromosome. This mutation creates a fusion gene called BCR-ABL1. Which produces a protein that promotes the uncontrolled growth of white blood cells. These abnormal cells accumulate in the bloodstream and bone marrow, interfering with the production of healthy blood cells. CML typically progresses through three phases: chronic, accelerated, and blast crisis. Most individuals are diagnosed during the chronic phase, which is the most stable and easiest to treat. Without effective management, the disease may evolve into the accelerated phase and eventually a blast crisis. Furthermore, it resembles acute leukaemia with a poorer prognosis. Chronic Myeloid Leukaemia Thanks to advances in molecular biology, particularly the development of tyrosine kinase inhibitors (TKIs), CML is now considered a highly treatable disease. Many people live long and healthy lives with CML, often experiencing long-term remission and normal life expectancy when diagnosed early and treated properly. In summary, this condition is a genetically driven blood cancer that can be effectively managed with modern targeted therapies. Early diagnosis and continuous monitoring are essential for achieving the best possible outcomes. [Next: Causes of Chronic Myeloid Leukaemia →]

Chronic Myeloid Leukaemia Read More »

Scroll to Top