Mental Matters

Health & Wellness

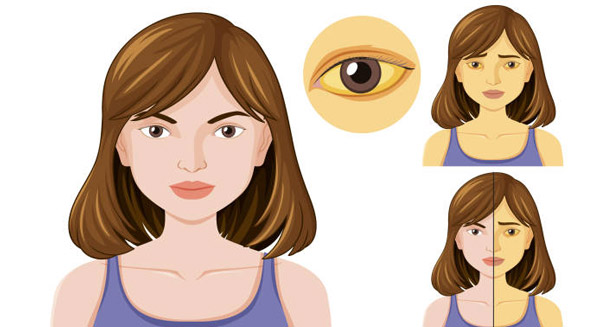
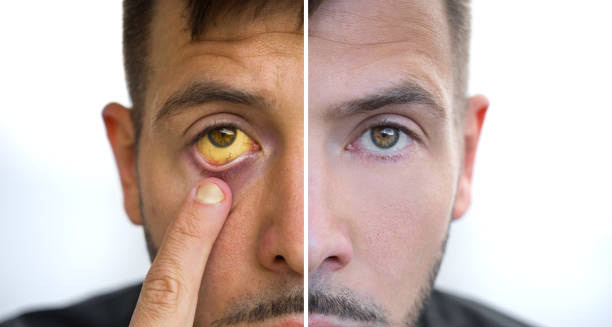
Split image showing one side of a man with yellow eyes and the other side with normal eyes, indicating symptoms of jaundice

Symptoms of Jaundice

Jaundice presents primarily as a yellowish discolouration of the skin, the sclera (whites of the eyes), and mucous membranes due to the accumulation of bilirubin in the bloodstream. Although this yellowing is the most recognisable sign, jaundice often occurs with a range of other symptoms depending on its underlying cause. These other symptoms give important clues and help doctors tell the types of jaundice apart—pre-hepatic, hepatic, or post-hepatic. They also show how serious the condition is and how quickly it needs treatment. Jaundice does not happen by itself. Usually, it shows the liver, bile ducts, or blood cells are not working properly. That is why the symptoms that come with jaundice are very important. Knowing them helps doctors spot jaundice early. It also guides the right treatment and can save lives. Visible Yellowing of the Skin and Eyes The most clear and common symptom of jaundice is yellowing of the skin and the whites of the eyes. This yellow colour shows up best in natural light. It usually starts on the face and upper body and then moves down. The yellow can be very light or dark orange-yellow, depending on how much bilirubin builds up and how long it stays high. In newborns, the yellowing often starts at the head and spreads to the chest, belly, and limbs. Doctors use this pattern along with bilirubin tests to decide if treatment is needed. In adults, the eyes often show yellowing first because the whites have no pigment. This makes the yellow colour easy to see. Dark-Coloured Urine One key symptom of conjugated jaundice—common in liver or bile duct problems—is dark urine. Patients describe it as tea-coloured, cola-coloured, or brownish. This happens because conjugated bilirubin dissolves in water and passes into urine when its blood levels rise. Dark urine often shows before the skin turns yellow. Some people may not notice it if they do not check their urine often. Still, doctors always ask about urine colour during exams. Pale or Clay-Coloured Stools Bile pigments give poop its normal brown colour. In obstructive jaundice, bile cannot reach the intestines because of blockages. As a result, stools turn pale, grey, or clay-coloured. This change is a strong sign of post-hepatic jaundice caused by gallstones, bile duct narrowing, or tumours. Sometimes stools also become greasy or smell bad. This happens if fat absorption drops because bile is missing in the gut. Generalised Itching (Pruritus) Itching, called pruritus, is a common and troubling symptom, especially in jaundice with blocked bile flow. Bile salts build up in the skin and cause intense itching. It often gets worse at night. Itching can affect any part of the body but is usually all over and very strong. This leads to scratching, skin damage, and even infections. People with long-term liver disease or bile duct blockage say itching is one of the worst symptoms. It often does not get better with antihistamines, making it harder to treat. Fatigue and Weakness Fatigue is a common symptom in jaundice, especially when caused by liver problems like hepatitis, cirrhosis, or autoimmune disease. The liver is key for energy and clearing toxins. When it gets hurt, energy drops. Patients often feel very tired, unmotivated, and mentally foggy. This can seriously affect daily life and might be blamed on other causes if jaundice is mild or new. Abdominal Pain or Discomfort Pain or discomfort in the belly often comes with jaundice, depending on the cause. In pre-hepatic jaundice caused by red blood cell breakdown, pain may be slight or missing.In hepatitis, people feel dull pain or discomfort in the right upper belly where the liver sits.In obstructive jaundice, sudden, sharp pain may mean gallstones. Slow, worsening pain could mean a tumour pressing on bile ducts. Belly swelling, fullness, or tenderness when touched can also happen with liver or bile duct problems. Nausea and Vomiting Nausea, poor appetite, and vomiting often occur with jaundice from liver illness. These symptoms show the liver’s role in digestion and detox. People with sudden hepatitis may feel sick and avoid fatty foods. Those with liver cirrhosis might have ongoing nausea that feels like indigestion. Fever and Chills Fever with jaundice usually means infection. One dangerous illness is ascending cholangitis, a bile duct infection often caused by gallstones blocking bile flow. Classic signs are: Other infections causing fever and jaundice include viral hepatitis, malaria, and leptospirosis. Chills and shaking support infection as the cause and need urgent care. Weight Loss and Anorexia Unplanned weight loss with jaundice may point to cancer. Pancreatic cancer, bile duct cancer, and liver cancer are common causes. Older adults or people who smoke, drink heavily, or have liver disease should be checked closely. Loss of appetite often comes before weight loss. It may happen because of belly discomfort, nausea, or liver problems. Confusion or Mental Changes (Hepatic Encephalopathy) In late liver disease, jaundice can come with mental changes like confusion, forgetfulness, mood swings, and less alertness. This is called hepatic encephalopathy. It happens when toxins, like ammonia, build up because the damaged liver can’t remove them. This is a medical emergency. If untreated, it can lead to coma or death. It mostly occurs in chronic liver failure or sudden liver injury. Signs in Newborns Babies with jaundice mainly show yellow skin and eyes. But some signs warn of serious problems: These may mean kernicterus, a rare but serious brain injury caused by very high bilirubin. Conclusion The symptoms of jaundice range from small changes in skin colour to serious, life-threatening problems. Yellow skin and eyes remain the key signs. Other symptoms like dark urine, pale stools, itching, and belly pain guide doctors to the cause. Early spotting of these signs, especially when combined, helps start the right treatment fast. Whether jaundice comes from infection, metabolism, blockage, or cancer, checking symptoms is crucial. People who notice yellow skin or eyes with other signs should get medical help quickly. [Next: Treatment of Jaundice →]

Symptoms of Jaundice Read More »

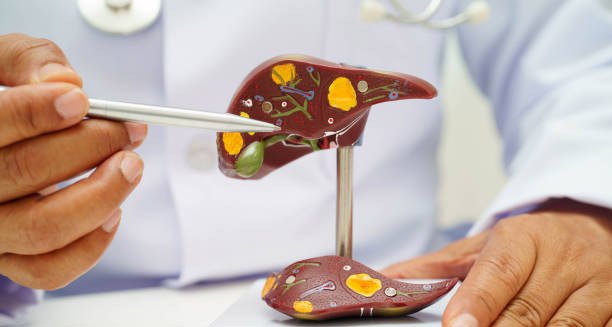
Doctor pointing at a liver model to explain the diagnosis of jaundice and bile flow issues

Diagnosis of Jaundice

Jaundice is a visible symptom that typically signals an underlying medical condition affecting the liver, bile ducts, or red blood cells. While the yellow discolouration of the skin and eyes may be easily observed, determining the cause of jaundice requires a structured diagnostic approach. Early and accurate diagnosis is vital in identifying potentially serious or life-threatening conditions such as bile duct obstruction, hepatitis, or liver cancer. Clinicians rely on a combination of medical history, physical examination, laboratory tests, and imaging studies to evaluate the origin and severity of jaundice. Understanding the mechanisms behind bilirubin metabolism is crucial to interpreting diagnostic results correctly. Bilirubin, the substance responsible for the yellowing seen in jaundice, is produced when red blood cells are broken down. It is processed in the liver and excreted through the bile ducts. A disruption at any point in this pathway may lead to bilirubin accumulation and, subsequently, jaundice. Initial Clinical Evaluation Medical History The first and most important step is a thorough medical history. Doctors ask about when the yellowing started and how long it has lasted. They check for recent travel, especially to places where hepatitis or malaria is common. They review all medicines used, including herbal remedies and over-the-counter drugs. Alcohol use is also important. Family history of liver or blood problems matters too. They ask about diet, lifestyle, and job risks, especially in healthcare, food handling, or chemical work. This information helps doctors guess the likely causes, such as viral hepatitis, alcohol damage, or blood disorders. Physical Examination Doctors perform a detailed physical exam to find clues. Yellowing of the whites of the eyes (scleral icterus) often appears before the skin changes. They feel the liver to check its size and firmness; a big, hard liver can mean cirrhosis or cancer. Tenderness in the right upper belly suggests inflammation or blockage. Signs like spider veins on the skin, red palms, and fluid in the belly point to long-term liver disease. An enlarged spleen may happen in blood disorders or portal hypertension. Laboratory Investigations Bilirubin Tests Blood tests measure total bilirubin, the overall level in the blood. Doctors check unconjugated (indirect) bilirubin, which rises in cases like haemolysis before the liver. They also measure conjugated (direct) bilirubin, which increases when the liver or bile ducts fail to remove bilirubin properly. Comparing these two types helps pinpoint the problem’s location. Liver Function Tests (LFTs) Doctors test enzymes like ALT and AST, which rise when liver cells get hurt, for example in hepatitis. ALP and GGT levels increase if bile flow is blocked. They also check albumin and clotting time (PT). Low albumin or long PT means the liver is not working well. Full Blood Count (FBC) A low haemoglobin with a high number of young red cells (reticulocytes) suggests red blood cells are breaking down. Raised white blood cells can mean infection or inflammation. Viral Hepatitis Panel Doctors test for hepatitis A, B, C, D, and E, especially if jaundice comes with tiredness, fever, or belly pain. Chronic hepatitis B and C raise the risk of cirrhosis and liver cancer. Autoimmune and Metabolic Markers Tests for anti-smooth muscle antibodies or anti-nuclear antibodies can suggest autoimmune hepatitis. Low ceruloplasmin points to Wilson’s disease. Iron tests check for haemochromatosis. Alpha-1 antitrypsin levels also help find rare causes. These tests help find treatable but uncommon liver problems. Urinalysis Urine tests are quick and useful. Dark urine with bilirubin confirms conjugated jaundice. Urobilinogen is often missing if bile flow is blocked but high if red cells break down too fast. This helps decide if the problem is in or after the liver. Stool Colour and Bile Pigments Patients may notice pale or clay-coloured stools when bile does not reach the intestines. Although this is a subjective sign, it points to obstructive jaundice and calls for more imaging tests. Imaging Techniques Ultrasound Scan Doctors usually start with an abdominal ultrasound. It is safe and easy to do. Ultrasound can spot gallstones, bile duct widening, liver lumps or cysts, and signs of cirrhosis. CT Scan (Computed Tomography) A CT scan gives detailed images of the body. It can find pancreatic cancer, bile duct tumours, and swollen lymph nodes. It helps plan surgery if needed. MRI and MRCP (Magnetic Resonance Cholangiopancreatography) MRI, especially MRCP, shows the bile ducts and pancreas clearly. Doctors use it when ultrasound results are unclear. Endoscopic Retrograde Cholangiopancreatography (ERCP) ERCP uses a flexible tube with a camera passed through the mouth to the bile ducts. It helps see blockages, remove stones, place stents, or take tissue samples. ERCP has risks and is used mainly when treatment is planned. Liver Biopsy If blood tests and scans do not show the cause, doctors may take a small piece of liver tissue. They look at it under a microscope to check inflammation, scarring, tumours, or storage diseases like Wilson’s or haemochromatosis. This test helps with unclear liver problems or chronic disease. Specialised Tests in Neonates Newborns with jaundice need specific tests like transcutaneous bilirubin measurements and blood bilirubin levels. A Coombs test checks for red cell breakdown. Blood typing of mother and baby helps find incompatibility. Early detection is key to prevent brain damage called kernicterus. Conclusion Diagnosing jaundice needs a careful mix of exam, lab tests, and imaging. By figuring out if the problem is before, in, or after the liver, doctors can find the cause and start treatment fast. Each step—from noticing yellow skin to biopsies—plays a key role. Quick diagnosis improves results and avoids problems like liver failure, infection, or brain damage in babies. Patients with jaundice must get thorough checks, especially if they have fever, confusion, or rapid weight loss. [Next: Treatment of Jaundice →]
Diagnosis of Jaundice Read More »

Stethoscope on wooden background with colourful letters spelling ‘Jaundice’

Treatment of Jaundice

Jaundice is not a disease in itself but a symptom that arises due to underlying conditions affecting the metabolism or excretion of bilirubin. As such, the treatment of jaundice focuses on identifying and managing the root cause while also addressing any complications that may arise. Because jaundice may be caused by conditions ranging from benign viral infections to life-threatening malignancies, a tailored treatment approach is crucial. In most cases, this involves a combination of medical, surgical, and supportive therapies. Importantly, the specific intervention chosen depends on whether the jaundice is pre-hepatic, hepatic, or post-hepatic, a distinction based on the site of disruption in bilirubin metabolism. Thus, the management of jaundice varies significantly across clinical presentations and is best guided by diagnostic investigations and clinical assessment. General Supportive Measures No matter the cause, certain basic steps can ease symptoms and help patients feel better. First, keeping well hydrated supports liver work and helps flush out toxins. Next, a balanced diet rich in antioxidants and low in saturated fats can ease liver stress. For patients with chronic liver disease, doctors may recommend special diets, such as low-protein meals for those with hepatic encephalopathy. Avoiding alcohol is vital because it can harm liver cells and worsen jaundice. Also, stopping medicines that can hurt the liver, like high doses of paracetamol, some antibiotics, and statins, can prevent further damage. These basic steps build a foundation while doctors treat the underlying cause more specifically. Treatment of Pre-Hepatic Jaundice Pre-hepatic jaundice happens when the body destroys red blood cells too fast, making the liver unable to keep up with processing bilirubin. Management of Haemolysis First, doctors find and remove the cause, which might be certain drugs, infections, or immune reactions. They then treat blood disorders like sickle cell anemia, thalassemia, or hereditary spherocytosis. These may need blood transfusions, iron removal treatments, or even bone marrow transplants. For autoimmune haemolytic anaemia, doctors often use corticosteroids or, sometimes, immunosuppressants or spleen removal surgery. Infections like malaria get treated with anti-malarial drugs and supportive care. If the case is severe, patients may need hospital stays to stabilize their condition and manage anemia. Treatment of Hepatic Jaundice Hepatic jaundice occurs when liver cells get damaged or stop working well. The most common causes include viral hepatitis, alcoholic liver disease, drug damage, and cirrhosis. Viral Hepatitis Hepatitis A and E usually get better on their own. Treatment involves rest, fluids, and avoiding anything that harms the liver. Hepatitis B and C might need antiviral medicines. For chronic cases, long-term treatment reduces the virus and stops the liver from getting worse. Doctors regularly check liver function with blood tests to track recovery or decline. Alcoholic Hepatitis Stopping alcohol use is key for healing and long-term liver health. Patients also need good nutrition and vitamin support, especially thiamine, folate, and B vitamins. Corticosteroids may help reduce inflammation in severe cases, but doctors watch patients closely because this treatment can be risky. Non-Alcoholic Fatty Liver Disease (NAFLD) Weight loss and lifestyle changes are the main treatments. Diet and exercise help most. Managing other health problems like diabetes, high blood pressure, and high cholesterol slows the disease. Autoimmune Hepatitis Doctors treat this with immune-suppressing drugs, usually corticosteroids plus azathioprine. Drug-Induced Liver Injury Doctors stop the harmful drug right away. For paracetamol overdose, they use N-acetylcysteine as an antidote. Supportive care helps, and in severe cases, liver transplantation might be needed. Treatment of Post-Hepatic (Obstructive) Jaundice This type happens when bile ducts get blocked, stopping bilirubin from leaving the body. Gallstones Doctors use a procedure called ERCP to remove stones blocking the common bile duct. Often, they remove the gallbladder surgically to stop stones from coming back. Tumours (e.g., pancreatic cancer, cholangiocarcinoma) Doctors place stents to keep bile ducts open and relieve blockage. If the tumor can be removed, surgery is done. Advanced or inoperable tumors may get chemotherapy or radiotherapy. Biliary Strictures or Infections These conditions might need antibiotics, bile drainage, or surgery depending on severity. Phototherapy in Neonatal Jaundice Newborn jaundice is common and usually harmless, but very high bilirubin levels can cause brain damage called kernicterus. Phototherapy This treatment changes bilirubin into a form the body can easily get rid of. Hospitals use blue lights or fiber-optic blankets. Phototherapy is safe and effective but needs close monitoring to prevent dehydration or overheating. Exchange Transfusion Doctors use this when phototherapy doesn’t work. They replace the baby’s blood with donor blood to quickly lower bilirubin. Liver Transplantation In severe liver failure, cirrhosis, or liver cancer, a liver transplant can save a life. Doctors decide who qualifies based on health scores like MELD and overall condition. After transplant, patients need lifelong medicines to stop rejection and regular check-ups. Surgical techniques and care have improved outcomes greatly. Treatment of Underlying Metabolic or Genetic Disorders Sometimes jaundice comes from rare inherited problems. Examples include: Early diagnosis and treatment of these rare causes are vital to stop permanent damage. Managing Complications of Jaundice Doctors often need to treat problems caused by jaundice too. Hepatic Encephalopathy Doctors use lactulose, rifaximin, and diet changes to manage this brain condition. Ascites Salt restriction, diuretics, and sometimes fluid removal help control fluid buildup in the belly. Coagulopathy Vitamin K or plasma transfusions may help when blood doesn’t clot well. Pruritus Doctors relieve itching with cholestyramine, ursodeoxycholic acid, and antihistamines. Regular check-ups and patient education help prevent worsening and hospital visits. Conclusion The treatment of jaundice needs a clear understanding of its cause. It ranges from simple care and lifestyle changes to surgery and liver transplants. Quick action saves lives in acute cases, while chronic problems need long-term care from many specialists. New tests and treatments have improved patient outcomes. Still, fast diagnosis, correct treatment, and ongoing care remain the keys to success. [Next: Complications of Jaundice →]

Treatment of Jaundice Read More »

Illustration of a woman showing progression from healthy skin to yellowing due to jaundice and potential complications

Complications of Jaundice

Jaundice may initially appear to be a benign symptom—simply the yellowing of the skin and eyes—but it can lead to or signify serious underlying health complications. While mild forms, especially in newborns or during short viral infections, often resolve on their own, severe or prolonged jaundice can cause major problems. The complications depend on the cause, how long jaundice lasts, and how quickly treatment starts. If untreated, jaundice can cause permanent organ damage, chronic illness, or even death. Since jaundice often signals liver, bile duct, or blood disorders, most complications come from these diseases. Understanding these risks helps doctors prevent issues early and monitor high-risk patients well. 1. Hepatic Encephalopathy Hepatic encephalopathy (HE) is a serious brain condition that happens in advanced liver disease. It occurs when toxins like ammonia build up because the liver cannot remove them. This can happen in jaundice caused by liver failure or cirrhosis. Symptoms include confusion, mood changes, drowsiness, tremors, and poor coordination. HE needs urgent treatment, including medications like lactulose and rifaximin, and sometimes intensive care. Repeated episodes may mean a liver transplant is necessary. 2. Kernicterus (in Neonates) Kernicterus is a severe brain injury caused by very high levels of bilirubin crossing into a newborn’s brain. It is a feared complication but can be prevented with proper monitoring. Signs include poor feeding, high-pitched crying, muscle stiffness, seizures, hearing loss, and cerebral palsy. Treatments include phototherapy and, if needed, blood exchange. Delays can cause lifelong disability or death. 3. Coagulopathy and Bleeding Tendencies The liver makes clotting factors. In liver diseases causing jaundice, this function can fail, leading to coagulopathy—where blood does not clot well. This causes easy bruising, bleeding in the gut, brain hemorrhage, or excessive bleeding after injuries or surgery. Doctors monitor clotting tests and may give vitamin K or plasma. Severe cases might need a liver transplant. 4. Chronic Pruritus and Skin Infections In jaundice caused by bile flow blockage, bile salts build up in the skin and cause severe itching (pruritus). Constant scratching can lead to skin damage and infections. This itching affects sleep and mood. Treatments include antihistamines, bile acid binders, and sometimes bile duct drainage to relieve blockage. 5. Renal Dysfunction Advanced liver failure can cause hepatorenal syndrome (HRS), a type of kidney failure without kidney damage. Symptoms include low urine output, low blood pressure, and rising kidney markers. Treatment includes medicines to improve blood flow, albumin infusions, and dialysis while waiting for a liver transplant. 6. Malabsorption and Nutritional Deficiencies Bile helps digest fats and absorb fat-soluble vitamins (A, D, E, K). Blocked bile flow can cause poor absorption, leading to fatty stools, weight loss, night blindness, bone weakness, nerve problems, and bleeding. Treatment involves fixing the cause and giving vitamin supplements. Special diets with medium-chain fats may help. 7. Gallstone Complications Gallstones blocking bile ducts can cause: Quick diagnosis and treatment, often by surgery or endoscopy, prevent these problems. 8. Progression to Cirrhosis and Liver Cancer Chronic jaundice from long-term liver disease can lead to cirrhosis—scarring that reduces liver function. Cirrhosis may cause portal hypertension, fluid buildup, bleeding, brain effects, and liver cancer. Early care can slow progression. Advanced disease may require transplantation. 9. Psychosocial and Quality of Life Implications Chronic jaundice with fatigue, itching, or brain changes can lower quality of life. Patients often feel depressed or anxious and may withdraw socially. Mental health support, counseling, and education improve treatment success and well-being. 10. Mortality Risk Untreated or late-treated jaundice from liver failure, cancer, or blood crises can be fatal. Death risk rises with late diagnosis, delayed treatment, or severe infections. This highlights the need for early recognition and comprehensive medical care. Conclusion Jaundice complications range from mild discomfort to life-threatening organ failure. What seems like simple yellow skin can quickly become a medical emergency if the cause is not treated. Careful monitoring, early diagnosis, and active treatment help prevent severe outcomes. Healthcare providers must act promptly and guide patients through comprehensive care. Patients and families should know warning signs and seek help early to improve chances of recovery. [Next: Back to Overview →]

Complications of Jaundice Read More »

Illustration of a man with severe headache and a brain graphic showing inflammation, symbolising Japanese encephalitis

Japanese Encephalitis

Japanese encephalitis is a serious viral brain infection spread by infected mosquitoes. It mainly occurs in Asia and the Western Pacific. Though not well known outside these areas, it is the leading cause of viral encephalitis in Asia, causing thousands of cases each year. The virus responsible, called Japanese encephalitis virus (JEV), belongs to the Flavivirus family, which also includes yellow fever, Zika, and dengue viruses. Japanese encephalitis is a zoonotic disease. This means it naturally cycles between animals and mosquitoes, with humans becoming infected by chance. Most people infected with JEV show no symptoms. However, about 1 in 250 develop severe illness. This usually means inflammation of the brain, called encephalitis, which can cause coma, long-term disability, or death. Children under 15 years old are affected most, especially where vaccination is low. Survivors may suffer lasting problems like learning difficulties, seizures, or paralysis. The virus spreads silently between mosquitoes and animal hosts, mainly pigs and wading birds. These animals do not show illness but carry the virus. Humans get infected when bitten by an infected mosquito but do not spread the virus further. Humans are dead-end hosts. They cannot keep the infection cycle going but can suffer severe effects. In recent years, changes such as more rice farming, pig rearing, and shifting climates have helped the disease spread to wider areas. It now affects parts of Australia, Pakistan, and urban edges of Asia. The World Health Organization (WHO) estimates over 3 billion people live in areas at risk of Japanese encephalitis. Transmission and Reservoirs The main mosquito spreading JEV is Culex tritaeniorhynchus. These mosquitoes breed in still water, common in rice fields and flooded farms. When they bite infected pigs or birds, they pick up the virus. Pigs are important amplifying hosts because they develop high virus levels without becoming sick. This allows mosquitoes to become infected again after biting pigs. Humans do not spread the virus. So, controlling Japanese encephalitis means focusing on mosquitoes, vaccination, and managing contact with animals, not stopping human-to-human spread. Disease Presentation Over 99% of JEV infections cause no symptoms or only mild signs like fever or headache. Severe illness causes acute encephalitis syndrome (AES). Patients may suddenly develop high fever, confusion, seizures, movement problems, and coma. The death rate in symptomatic cases is 20% to 30%. Among survivors, up to 50% may have lasting brain damage. The incubation period is 5 to 15 days. This is the time from infection to symptoms. Without treatment, death can occur within days of symptom start. At-Risk Groups Certain people face higher risks of Japanese encephalitis: Many countries have lowered disease rates with vaccination campaigns. However, millions remain unprotected due to cost, logistics, or politics. Global Impact and Prevention Around 68,000 clinical cases of Japanese encephalitis occur worldwide each year. Most cases happen in India, China, Nepal, Vietnam, and Southeast Asia. Yet, the disease could spread to new areas because of: The good news is that Japanese encephalitis is preventable. A safe, effective vaccine exists and is used in many endemic countries. Other prevention steps include: Importance of Awareness Despite its impact, Japanese encephalitis is often overlooked, especially outside endemic areas. Travellers and health workers may underestimate the risk. Stronger surveillance, public education, and international cooperation are vital to reduce disease spread. Raising awareness about how the virus spreads, its symptoms, and dangers helps protect high-risk groups. Early diagnosis and treatment improve outcomes. Although no specific antiviral exists, supportive care can save lives. [Next: Causes of Japanese Encephalitis →]

Japanese Encephalitis Read More »

Close-up of a mosquito on human skin, the primary cause of Japanese encephalitis transmission

Causes of Japanese Encephalitis

Japanese encephalitis is caused by the Japanese encephalitis virus (JEV), a single-stranded RNA virus in the Flavivirus genus. This virus is related to dengue, Zika, and yellow fever. While the virus itself causes the disease, several other factors help it spread. These include mosquitoes, animals, human behaviour, and environmental conditions. Unlike infections that spread from person to person, Japanese encephalitis moves through a complex cycle involving animals and mosquitoes. Understanding the causes of Japanese encephalitis means looking at each step in this transmission chain—from the virus itself to the places and behaviours that let it thrive. The Virus: Japanese Encephalitis Virus (JEV) The Japanese encephalitis virus mainly targets the brain. After a mosquito bite, the virus multiplies in nearby tissues and then enters the bloodstream. In most people, the immune system clears it quickly. But in rare cases, the virus crosses into the brain and causes encephalitis—serious inflammation that can lead to death or lasting damage. JEV survives in nature through a zoonotic cycle, meaning it spreads among animals and mosquitoes. Humans are not part of this natural cycle, making them accidental hosts. Mosquitoes: The Main Vectors of Japanese Encephalitis The Culex tritaeniorhynchus mosquito plays the biggest role in spreading JEV. These mosquitoes bite at night and breed in standing water like: Several traits make Culex mosquitoes excellent virus carriers: After biting an infected animal, the mosquito stores the virus in its saliva. When it bites a human, it injects the virus into the bloodstream. Amplifying Hosts: Pigs and Wading Birds Pigs are key amplifiers of Japanese encephalitis. When a mosquito bites an infected pig, the virus multiplies to high levels in the pig’s blood. Other mosquitoes feeding on the same pig can then pick up the virus and spread it again. This is especially risky in rural areas where pigs live near rice fields and homes. Pigs breed fast and are often raised in large groups, increasing the risk of viral spread. Wading birds, such as egrets and herons, are natural virus reservoirs. They help the virus survive between seasons and carry it across long distances. Unlike pigs, birds can fly far and bring JEV into new areas. Humans as Dead-End Hosts Humans can get Japanese encephalitis through a mosquito bite, but they do not spread the virus further. The level of virus in human blood is too low to infect another mosquito. This makes humans “dead-end hosts.” Although humans don’t continue the cycle, the virus can cause serious illness or death in people. Because human infection is accidental, outbreaks depend on the presence of infected mosquitoes and animals—not human-to-human spread. Environmental and Climate Factors The environment plays a major role in the spread of Japanese encephalitis. Key factors include: a. Rainy Season and Standing WaterMosquito numbers increase during and after heavy rains. Flooded fields and stagnant pools become ideal mosquito breeding grounds. Outbreaks often occur in the rainy season. b. Rice FarmingRice paddies hold water for long periods and attract both mosquitoes and pigs. This creates a hotspot for viral transmission. c. Warm Temperatures and High HumidityHot weather speeds up how fast the virus multiplies inside mosquitoes. Humid conditions also help mosquitoes live longer and bite more often. d. Deforestation and Urban ExpansionClearing forests for farms or buildings forces animals, mosquitoes, and people to live closer together. This increases the chance of human exposure to infected mosquitoes or birds. Human Activity and Risk Factors Some daily habits and social issues also raise the risk of Japanese encephalitis, including: Rapid urban growth without good sanitation may also lead to new mosquito habitats, especially in crowded informal settlements. Travel and the Spread Beyond Endemic Areas Travellers visiting affected regions can also get infected. The risk is highest during the rainy season and in rural areas. Farming, camping, or hiking outdoors for long periods increases exposure. Though global spread is rare, migrating birds or mosquitoes could carry JEV to new areas. The World Health Organization advises vaccination for travellers spending a month or more in high-risk areas—or less time if visiting rural zones with known outbreaks. Conclusion The causes of Japanese encephalitis are complex. They involve a virus, mosquitoes, animals, humans, and the environment. Unlike common infections that spread easily between people, this disease needs many steps to keep going. Stopping the spread means breaking this chain. This can be done by: Most importantly, wide access to vaccines and good public health planning can prevent serious outbreaks and save lives. [Next: Symptoms of Japanese Encephalitis →]

Causes of Japanese Encephalitis Read More »

Cartoon of a man sweating and holding his head in pain, indicating symptoms of Japanese encephalitis

Symptoms of Japanese Encephalitis

Japanese encephalitis is a viral brain infection that often presents a deceptive clinical picture, with the majority of infected individuals exhibiting no symptoms at all. In fact, up to 99% of people infected with the Japanese encephalitis virus (JEV) show no symptoms or only mild flu-like signs. But when the virus reaches the brain, symptoms can worsen quickly and become life-threatening. Knowing the symptoms of Japanese encephalitis helps people act early and get medical help in time. The symptoms of Japanese encephalitis range from mild to severe. In some, the disease starts with general signs and quickly turns into a brain infection. The virus can cause seizures, coma, and death if not treated properly. The Incubation Period and Asymptomatic Cases After a mosquito bite, the incubation period lasts 5 to 15 days. During this time, the virus multiplies in the body without causing symptoms. Most people remain unaware of the infection. In some, however, the virus crosses into the brain, leading to clinical illness. In more than 99% of cases, people experience only mild symptoms such as: These mild symptoms often resemble the common flu and usually go away on their own. Still, vulnerable people—especially children and those with weak immune systems—face a higher risk of complications. Prodromal Phase: Early Symptoms of Japanese Encephalitis In the small number of people who develop symptoms, Japanese encephalitis begins with a prodromal phase lasting 2 to 5 days. Early warning signs include: These signs can be mistaken for malaria, dengue, or the flu. However, Japanese encephalitis becomes clearer when neurological signs develop shortly afterward. Acute Encephalitic Phase Once the virus enters the brain, it triggers the acute encephalitic phase. This happens in about 1 in 250 infected people. Symptoms may appear within hours or days after the fever begins. Key signs during this stage include: a. Changes in Mental Status b. Neurological Symptoms Some patients may show Parkinson-like features such as facial stiffness, tremors, or slow movements. c. Speech and Behavior ChangesPeople may speak slowly, mumble, or stop speaking altogether. Children may become aggressive, irritable, or withdrawn. Recovery and Late Symptoms of Japanese Encephalitis If the patient survives the acute phase, symptoms may ease over a few weeks. However, full recovery is rare. Many people live with long-term effects such as: As many as 30–50% of survivors develop permanent disabilities. Recovery often needs months of physical, speech, or mental health therapy. Symptoms in Children vs Adults Children are more likely to show early warning signs such as: Adults may instead display mood changes or confusion first. Sadly, children also face a greater chance of lasting brain damage, especially when treatment is delayed. Unusual Presentations of Japanese Encephalitis Some people may have rare or unexpected symptoms, which can delay diagnosis. These include: Doctors in high-risk areas must stay alert to these rare forms—especially during mosquito season. Why Knowing the Symptoms of Japanese Encephalitis Matters There is no specific medicine to cure Japanese encephalitis. Treatment focuses on easing symptoms and preventing complications. This is why recognising early signs—especially neurological ones—is so important. Prompt medical care can save lives and limit brain damage. Raising awareness also helps. Families should know that symptoms like fever with confusion, seizures, or stiff neck mean urgent care is needed—especially in young children. Conclusion The symptoms of Japanese encephalitis range from mild or invisible to sudden and severe brain inflammation. Understanding this range helps with early detection and life-saving care. In areas where the disease is common, doctors should always consider Japanese encephalitis when patients show signs of brain infection—especially during mosquito season. Education, fast action, and vaccines are key to reducing the harm caused by this serious but preventable illness. [Next: Diagnosis of Japanese Encephalitis →]

Symptoms of Japanese Encephalitis Read More »

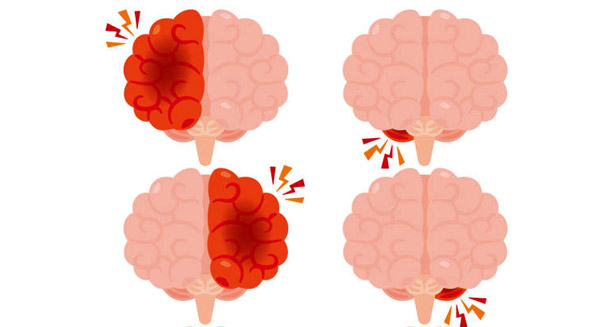
Illustration of four brains showing areas of inflammation, used to depict diagnosis of Japanese encephalitis

Diagnosis of Japanese Encephalitis

Japanese encephalitis is a challenging condition to diagnose, especially in its early stages when symptoms are vague and often resemble other common infections. As a viral disease that targets the brain, it needs quick and accurate diagnosis. This can help improve outcomes and reduce the risk of long-term brain damage. Doctors rely on clinical signs, a history of exposure, and lab tests to identify the virus. Diagnosis can be complex, especially in areas with limited resources. But early detection is vital for patient care and public health planning. There is no cure for Japanese encephalitis. So, the main goal of diagnosis is to confirm the illness, rule out similar diseases, and begin supportive treatment. It also helps track outbreaks and guide vaccine efforts in high-risk areas. Clinical Symptoms and Early Clues The first step in diagnosing Japanese encephalitis is a thorough clinical check. Doctors assess the patient’s symptoms, such as high fever, headache, confusion, seizures, and nerve problems. These signs often get worse over a few days. If coma or paralysis sets in, doctors suspect a serious brain infection. However, many other illnesses can look similar. Malaria, meningitis, and other viral infections can cause the same symptoms. So, Japanese encephalitis is usually a diagnosis of exclusion, especially in regions with many infectious diseases. A recent stay in rural or mosquito-prone areas can provide a strong clue. In children, sudden seizures and confusion without injury should raise concern. Role of Exposure and Travel History Doctors must review the patient’s exposure history to assess the risk of infection. These questions are key: These details help doctors decide whether testing is needed. In areas where the virus is common, all unexplained brain infections should be checked for Japanese encephalitis—especially in people who are unvaccinated. Testing for Japanese Encephalitis Lab tests are essential for diagnosis. The most used test is called MAC-ELISA, which looks for IgM antibodies in the blood or spinal fluid. These antibodies appear 4–8 days after symptoms begin and peak in the second week. MAC-ELISA is: But it also has limits: So, test results must be considered along with clinical signs and exposure history. Other Tests and Imaging PCR testing can detect the virus’s genetic material in blood or spinal fluid. It works best early in the illness, before symptoms of brain infection appear. PCR is accurate but costly and often only found in research labs or major cities. Doctors may also perform a lumbar puncture to check the spinal fluid. Common findings include: Though these results are not specific, they support the diagnosis if JEV antibodies or RNA are present. Brain scans can also help. MRI often shows damage in areas like the thalamus, brainstem, or basal ganglia. CT scans may show swelling or localized damage. While not diagnostic, imaging helps rule out other diseases and supports clinical suspicion. Excluding Other Illnesses Many diseases mimic Japanese encephalitis. Doctors must rule out: Comparing symptoms, lab data, and exposure helps doctors avoid misdiagnosis. Reporting and Public Health Impact Japanese encephalitis is often a notifiable disease. Confirmed cases must be reported to health authorities. This helps: Public health labs confirm diagnoses and gather data to prevent future infections. Conclusion The diagnosis of Japanese encephalitis depends on careful evaluation of symptoms, history, and lab tests. Because the early signs are vague, doctors must stay alert—especially in unvaccinated patients returning from high-risk areas. While tests like MAC-ELISA or PCR are key, the full picture—including brain scans and spinal fluid analysis—is essential. In areas with few resources, clinical signs and exposure history often guide the diagnosis. Finding the illness early helps not only the patient but the wider community. Accurate and fast diagnosis supports public health goals, slows outbreaks, and strengthens vaccine efforts against this severe yet preventable disease. [Next: Treatment of Japanese Encephalitis →]

Diagnosis of Japanese Encephalitis Read More »

Close-up of vaccine vials and syringe labeled Japanese Encephalitis for treatment and prevention

Treatment of Japanese Encephalitis

Japanese encephalitis is a potentially life-threatening condition caused by the Japanese encephalitis virus (JEV), which is transmitted by mosquitoes. While most cases are asymptomatic, a small number develop severe neurological disease that needs urgent medical attention. Since there is no specific antiviral drug for this illness, the treatment of Japanese encephalitis focuses on supportive care. The aim is to manage symptoms, avoid complications, and help the patient recover. Quick action increases the chances of survival and lowers the risk of long-term damage. In areas where the virus spreads often, treatment of Japanese encephalitis also helps reduce death rates and ease pressure on hospitals. Knowing what treatment options exist for both the early and recovery phases helps doctors, families, and decision-makers plan better. Hospital Support is Key to the Treatment of Japanese Encephalitis Because a virus causes Japanese encephalitis, antibiotics do not work. So far, no antiviral drug has shown consistent success in trials. This makes supportive hospital care the main method of treatment. Doctors monitor vital signs, manage each symptom, and work to stop new problems from appearing. a. First Steps to Stabilise the Patient Care begins with keeping the airway, breathing, and blood flow stable. Many patients need: b. Monitoring Brain Health The virus can cause swelling in the brain. So, doctors watch for: If brain pressure rises, staff may raise the bed head, use diuretics like mannitol, or start a breathing machine to ease the load on the brain. Seizure Control and Managing Unconsciousness Seizures often happen, especially in children. Treating them fast protects the brain. a. First-Line Seizure Treatment Doctors use diazepam or lorazepam right away. If that fails, they may give phenytoin, valproic acid, or phenobarbital. b. Long-Term Seizure Plans Some people develop long-term epilepsy after the illness. These patients may need daily seizure medicine. A neurologist usually guides this, using EEG scans as needed. For patients who fall into a coma, care gets more complex. They may need: Nurses also work to stop pressure sores, blood clots, and infections. Broader Recovery in the Treatment of Japanese Encephalitis Some people face movement issues like tremors or rigid muscles. Paralysis may also appear. Though no drug reverses these directly, some treatments help reduce symptoms: Recovery varies, but early rehab usually helps. Fever and vomiting often cause weight loss and low fluids. So, doctors focus on keeping energy and water levels stable: Rehabilitation and Future Care Even when patients recover physically, many still struggle with thinking or mood. Problems may include memory loss, speech trouble, or depression. So, a full rehab plan includes: The treatment of Japanese encephalitis also requires planning for life after hospital. Before sending patients home, doctors check their physical, mental, and emotional state. They build a custom care plan, which may include: New Drugs and Public Health Support Doctors continue to study medicines like ribavirin, interferon-alpha, minocycline, and IVIG. However, none are yet part of standard care. In poor regions, hospitals may not have machines or ICU beds. Here, basic care is vital. Community health workers help by: Public health teams also work after diagnosis to stop more infections. They may: These steps help reduce future outbreaks and save lives. Final Thoughts on the Treatment of Japanese Encephalitis The treatment of Japanese encephalitis focuses on support and symptom control. There is no cure yet, but good hospital care, seizure control, and rehab can greatly improve outcomes. Quick action and complete rehab help many regain function and live independently. At the same time, public health efforts are just as important. Fighting mosquitoes and increasing vaccination can reduce the spread of the virus, especially where hospitals lack resources. As travel grows and climates change, the treatment of Japanese encephalitis must remain a public health priority. [Next: Complications of Japanese Encephalitis →]

Treatment of Japanese Encephalitis Read More »

Illustration showing complications of Japanese Encephalitis including fever, vomiting, seizures, and neurological symptoms

Complications of Japanese Encephalitis

Japanese encephalitis is a serious neuroinvasive disease that can lead to a broad spectrum of complications, especially in individuals who develop severe encephalitic illness. Although most people infected with the virus do not show symptoms, those who do often face grave outcomes. About 20–30% of symptomatic cases result in death, while 30–50% of survivors live with long-term disabilities. These statistics show just how devastating the complications of Japanese encephalitis can be for patients and healthcare systems alike. The effects of this mosquito-borne illness do not end with the initial infection. Many survivors face ongoing issues that impact their brain, mood, and ability to function daily. In young children, these effects can slow growth, school progress, and overall well-being. Learning about these complications helps doctors, families, and health planners prepare better care and support. Neurological Effects in the Complications of Japanese Encephalitis The most common complications of Japanese encephalitis involve the nervous system. The virus inflames parts of the brain like the thalamus, brainstem, basal ganglia, and spinal cord. When these areas are damaged, patients can develop serious neurological problems. Motor Problems:Many survivors have trouble moving. They may experience: These issues can make walking or self-care difficult. Some people need physiotherapy for life or devices like crutches or wheelchairs. Seizures and Epilepsy:Seizures are another common issue. Patients may have: Treatment includes anti-seizure medication and regular check-ups with a neurologist. Cranial Nerve Issues:If the virus affects cranial nerves, it can lead to: These complications often require speech therapy or even surgery. Cognitive and Psychological Complications of Japanese Encephalitis Another group of complications of Japanese encephalitis involves mental functions. Damage to the brain can impair thinking and learning, especially in children. Cognitive Challenges:Survivors might face: In children, these issues often lead to poor school performance. Adults may find it hard to return to work, especially if their job involves planning or decision-making. Emotional and Behavioural Changes:The illness and its effects can also impact mood and behaviour. Survivors may develop: These symptoms often need therapy, medication, or both. Support for families is also important, as caregivers can struggle to manage behavioural changes at home. Senses, Speech, and Development in Japanese Encephalitis Survivors Speech and Swallowing Problems:Damage to the brain’s speech centres or throat muscles may cause: Speech therapy helps many children and adults improve these skills. Some may need communication devices. Hearing and Vision Loss:A few survivors lose hearing or vision. This might be due to nerve damage or brain processing issues. They may experience: Hearing aids or glasses often help. It’s vital to test these senses during recovery, especially in school-aged children. Fatigue and Sleep Problems:Even after recovery, many people feel tired or struggle to sleep. This may result from: Managing sleep and energy levels includes lifestyle changes and, in some cases, medication. Broader Effects and Prevention of Japanese Encephalitis Complications Delayed Development in Children:Young children who survive may experience delays in: They benefit from early screening and tailored care. A team of doctors, therapists, and educators can help improve outcomes. Impact on Families and Finances:Families often face high emotional and financial costs. Ongoing care for a disabled child or adult can lead to: Support like financial aid, caregiver training, and respite care can ease the burden. Risk of Death:About one in three severe cases results in death. Death often happens within the first week due to: In very severe cases, palliative care can help keep the patient comfortable. Families also need support through grief and loss. Prevention and Early Action:Many complications of Japanese encephalitis can be reduced by: Ongoing care includes regular check-ups, therapy, school or job support, and counselling. Outlook for Survivors of Japanese Encephalitis The complications of Japanese encephalitis are serious and long-lasting. From physical and mental issues to emotional and financial struggles, the effects can touch every part of life. But with early care and proper support, many survivors improve. Raising awareness, boosting access to care, and strengthening public health efforts—especially in high-risk areas—can help reduce the damage this illness causes. Vaccination, mosquito control, and health education remain the most powerful tools to prevent these life-changing complications. [End of Article – Back to Overview]

Complications of Japanese Encephalitis Read More »

Scroll to Top