Mental Matters

Author name: admin

Speech therapist working with a child using mirror exercises

Treatment of Dysarthria

Treatment of Dysarthria The treatment of dysarthria depends on the underlying cause, the severity of the symptoms, and the individual’s communication needs. While the condition cannot always be cured—especially in progressive neurological diseases—speech therapy can significantly improve clarity, confidence, and communication ability. Most importantly, dysarthria can be managed with the right strategies and support systems in place. Speech-language therapy is the cornerstone of treatment. A therapist works with the patient to strengthen the muscles involved in speech, improve breath control, and teach compensatory techniques to make speech more understandable. Exercises may include practising slow, deliberate speech, repeating specific sounds, or using exaggerated mouth movements to increase clarity. One key focus in the treatment of dysarthria is pacing. Many individuals benefit from slowing down their speech and using pauses to allow for better articulation. Breathing techniques also help, particularly for those who run out of breath while speaking. Posture adjustments and vocal exercises may improve volume and reduce strain. In moderate to severe cases, assistive communication tools can be introduced. These may include alphabet boards, picture communication systems, or electronic speech-generating devices. For individuals who cannot speak at all, such tools are essential for maintaining independence and social connection. Mobile apps and text-to-speech technology have become increasingly accessible and are particularly useful in South African contexts where traditional speech therapy may be limited. Treatment of Dysarthria When dysarthria is caused by a reversible condition—such as a medication side effect, infection, or injury—treatment of the underlying cause may lead to full or partial recovery of speech. For instance, adjusting medication or controlling blood sugar levels in diabetic neuropathy can improve muscle function. In cases of stroke, early rehabilitation offers the best chance of regaining speech abilities. Group therapy sessions and support groups also play an important role in the treatment process. Practising with others helps reduce anxiety and encourages real-world application of speech techniques. Emotional support is vital, especially when individuals feel socially isolated or embarrassed by their condition. Family involvement enhances treatment success. Caregivers and loved ones can learn techniques to support effective communication, such as giving extra time to respond, using visual cues, or reducing background noise during conversation. Educating those around the individual creates a more supportive environment. In South Africa, access to speech therapy varies between public and private sectors. NGOs and community-based rehabilitation centres help provide services in underserved areas, but many people still lack consistent care. Expanding public awareness about dysarthria and investing in speech-language therapy infrastructure are important steps toward inclusive healthcare. While not all forms of dysarthria can be completely resolved, many people experience significant improvement. With personalised therapy, patience, and practical tools, individuals can enhance their communication and regain a strong sense of agency. [Next: Complications of Dysarthria →]

Treatment of Dysarthria Read More »

Complications of Dysarthria

Complications of Dysarthria

Complications of Dysarthria The complications of dysarthria can affect every aspect of a person’s life, especially if the condition is not managed early or effectively. Although the physical impact is on speech, the consequences often extend to emotional health, social interaction, education, and employment. If left untreated, dysarthria can lead to isolation, frustration, and a reduced quality of life. The most immediate complication is reduced intelligibility. When speech becomes difficult to understand, basic conversations can be stressful and tiring for both the speaker and the listener. This may lead people to withdraw from social situations, avoid phone calls, or refuse to speak in public. The constant need to repeat themselves can be emotionally draining. Another serious concern is aspiration. In some cases of dysarthria, especially when the muscles used for swallowing are affected, food or liquids can enter the airway instead of the oesophagus. This can lead to choking or lung infections such as aspiration pneumonia. For this reason, speech therapists often assess swallowing during the initial evaluation and recommend safe eating strategies when needed. Common Complications Academic and occupational complications are also common. Children with untreated dysarthria may fall behind in school due to communication barriers. They may struggle to answer questions verbally, participate in class discussions, or make friends. Adults may find it difficult to retain or find employment, especially in roles that require clear verbal communication. In some cases, dysarthria contributes to early retirement or underemployment. Mental health challenges often arise alongside speech difficulties. Anxiety, embarrassment, and depression are frequently reported, particularly when individuals feel misunderstood or excluded. These emotional effects can intensify the communication difficulties, creating a cycle of stress and silence. Access to psychological support and speech therapy is essential to breaking this cycle. In families and relationships, dysarthria can lead to miscommunication and tension. Partners, children, or caregivers may misinterpret a person’s silence or frustration as unwillingness to communicate. Education and counselling for both the individual and their support network are important to maintain healthy, understanding relationships. Complications of Dysarthria In South Africa, access to consistent therapy and specialised care is limited in many regions, especially rural areas. This increases the risk of long-term complications, particularly when individuals are discharged from hospital after a stroke or brain injury without proper follow-up. Delayed therapy often results in permanent communication loss that could have been minimised. Technology can help reduce some of the complications. Assistive communication devices, speech apps, and voice training tools provide alternative means of expression, especially when used early. Community-based programmes and local support groups also offer vital assistance, helping individuals remain engaged in daily life. With the right intervention and ongoing support, the complications of dysarthria can be managed or avoided. Early treatment, inclusive communication strategies, and emotional care ensure that those affected can continue to participate meaningfully in their families, communities, and professions. [Next: Back to Overview →]

Complications of Dysarthria Read More »

Three women with dwarfism sitting on a bench outdoors

Dwarfism

Dwarfism Dwarfism is a medical or genetic condition that results in significantly shorter stature than average. People with this condition typically reach an adult height of 4 feet 10 inches (147 cm) or less. Though this can vary depending on the type and cause. While the term may sound clinical. Many people within the community prefer “short stature” or “little person” as respectful alternatives, depending on personal and cultural preferences. There are over 300 known conditions that can cause condition, but the most common is achondroplasia. This genetic disorder affects bone growth. Leading to short limbs, a normal-sized torso, and specific facial features such as a prominent forehead. Other causes include growth hormone deficiency and genetic syndromes that impact skeletal development. Proportionate and disproportionate forms of dwarfism exist, depending on whether the entire body is small or only certain parts. People with dwarfism can lead healthy, fulfilling lives. However, they may face medical complications, mobility challenges, and social stigma. Access to appropriate healthcare, adaptive technologies, and inclusive environments helps improve quality of life. In South Africa, individuals with dwarfism may experience additional challenges due to uneven healthcare access and limited public awareness, particularly in rural or underserved areas. Dwarfism Despite the medical definition, dwarfism is not a disease or a condition to be “cured.” It’s a form of human diversity. Many individuals take pride in their identity and advocate for greater representation, accessibility, and equal treatment. With the right support, people with short stature can thrive in education, employment, sports, and family life. Raising awareness and promoting inclusion—especially in schools, workplaces, and healthcare systems—is key to ensuring people with dwarfism are treated with dignity and given equal opportunities. [Next: Causes of Dwarfism →]

Dwarfism Read More »

Genetic inheritance illustration showing causes of dwarfism

Causes of Dwarfism

Causes of Dwarfism The causes of dwarfism vary widely and can be genetic, hormonal, or related to unknown developmental factors. Most cases result from genetic mutations that affect bone or cartilage development. Achondroplasia is the most common cause of dwarfism, accounting for approximately 70% of all cases. A mutation in the FGFR3 gene causes achondroplasia, restricting bone growth, especially in the arms and legs. It is an autosomal dominant condition, meaning that just one copy of the altered gene can cause the disorder. Interestingly, most children with achondroplasia are born to average-height parents, with the gene mutation occurring spontaneously. Another genetic cause is diastrophic dysplasia, a rarer condition that affects cartilage and bone development, leading to clubfoot, limited joint mobility, and scoliosis. Spondyloepiphyseal dysplasia congenita (SEDc) is another rare skeletal disorder linked to dwarfism that affects the spine and long bones. Each of these conditions results in disproportionate body proportions and may require specific medical management. Not all causes of dwarfism are skeletal. Some individuals have proportionate short stature, where the body is small but well-proportioned. This can result from hormonal conditions like growth hormone deficiency or pituitary gland disorders. In these cases, the bones grow slowly but evenly. Treatment with growth hormone therapy can help in some instances, particularly if started early. Intrauterine Growth Restriction In rare cases, intrauterine growth restriction (IUGR), metabolic disorders, or malnutrition during early development can cause dwarfism. While these are less common, they highlight the importance of maternal and early childhood health, especially in countries with limited access to nutrition and healthcare. In South Africa, limited access to prenatal care and diagnostic services in rural areas can delay the identification of the underlying cause. Early diagnosis is important for managing symptoms and planning supportive care. Genetic testing and consultation with a specialist are often needed to confirm the cause and provide accurate information for families. Causes of Dwarfism It’s important to understand that the causes of dwarfism are not related to lifestyle choices, parenting, or anything that could have been prevented. Most conditions occur spontaneously or are inherited genetically. Blame or stigma associated with short stature is harmful and unsupported by science. Knowing the underlying cause helps healthcare professionals manage potential complications and offer guidance tailored to the individual’s needs. While a diagnosis may present challenges, many people with dwarfism live full, independent lives, especially when supported by informed medical care and inclusive communities. [Next: Symptoms of Dwarfism →]

Causes of Dwarfism Read More »

Smiling baby with short limbs sitting in a car seat

Symptoms of Dwarfism

Symptoms of Dwarfism The symptoms of dwarfism depend on whether the condition is proportionate or disproportionate, and on the specific underlying cause. However, the most common symptom is significantly shorter stature compared to age-matched peers. People with dwarfism often have distinct body proportions, medical challenges, or physical traits that become apparent in early childhood. In disproportionate dwarfism, such as achondroplasia, the torso is typically of average size while the limbs are shorter than usual. The head may appear larger, and the forehead may be prominent. The bridge of the nose may be flatter, and the fingers can be short and wide, often with a gap between the middle and ring fingers (sometimes called a “trident hand”). These physical signs usually become more noticeable as the child grows. Proportionate dwarfism involves a generalised slowing of growth, where the entire body is small but remains in proportion. It is often caused by hormonal conditions, such as growth hormone deficiency. In these cases, infants may have a normal appearance at birth but begin to fall behind in growth charts during infancy or early childhood. Other possible symptoms include delayed puberty, slow muscle development, and fatigue. Skeletal dwarfism may include complications such as bowed legs, spinal curvature (kyphosis or lordosis), joint stiffness, and limited mobility. Some children experience frequent ear infections due to narrow ear canals, and vision problems can also occur. Adults with certain forms of dwarfism may face issues like arthritis, back pain, or breathing difficulties due to a smaller chest cavity. Not all symptoms are physical. Social and emotional challenges can emerge due to teasing, stigma, or accessibility issues. People with dwarfism often face discrimination, particularly in settings that lack awareness or accommodation. Psychological support and inclusive environments are important for healthy self-esteem and emotional development. In South Africa, identifying these symptoms early may depend on access to paediatric services, growth monitoring, and diagnostic imaging. In communities where growth charts are not routinely used, the signs of dwarfism may be missed until later stages. Education for health workers and parents is essential to ensure early recognition and appropriate referral to specialists. Symptoms of Dwarfism Despite the challenges, many people with dwarfism do not see their condition as a limitation. Early diagnosis and supportive care, including physiotherapy, orthopaedic management, and educational access, make a significant difference in development and independence. Recognising the symptoms of dwarfism enables families and professionals to respond with appropriate medical care, support, and long-term planning. With early intervention and understanding, individuals with dwarfism can lead successful, self-directed lives. [Next: Diagnosis of Dwarfism →]

Symptoms of Dwarfism Read More »

Child with short stature sitting at a table with parents and a doctor

Diagnosis of Dwarfism

Diagnosis of Dwarfism The diagnosis of dwarfism often begins with noticing that a child is significantly shorter than expected for their age. Paediatricians typically monitor a child’s growth on standardised growth charts. If height and weight consistently fall below the third percentile, or if growth slows noticeably over time, further investigation is warranted. In most cases, the initial signs of dwarfism appear during infancy or early childhood. A thorough physical examination provides clues to the type of dwarfism. Disproportionate body features—such as shorter arms and legs with a normal-sized torso—may suggest skeletal dysplasia, like achondroplasia. In contrast, proportionate dwarfism results in overall small stature with no significant difference between limb and trunk lengths. The presence of facial features, joint problems, or spinal curvature also helps guide diagnosis. Doctors will usually start with a full family and medical history. Knowing whether parents or siblings have short stature helps determine if the child’s growth pattern is familial or potentially pathological. A review of birth history, developmental milestones, and any previous illnesses also forms part of the diagnostic process. Imaging Tests To confirm the diagnosis of dwarfism, imaging tests such as X-rays are often ordered. These help assess bone shape and growth plate development. In skeletal dysplasias, characteristic changes in bone structure are typically visible. For suspected hormonal causes—like growth hormone deficiency—blood tests and a growth hormone stimulation test may be used to evaluate hormone levels. Genetic testing plays a vital role in identifying the specific cause. For conditions like achondroplasia, a mutation in the FGFR3 gene is commonly detected. Genetic counselling is recommended for families when a heritable condition is diagnosed, especially if they are considering future pregnancies. In South Africa, the availability of advanced diagnostic tools such as genetic testing or growth hormone assays can be limited, especially in rural clinics. Referral to paediatric endocrinologists or genetic specialists may be delayed. However, increasing awareness among healthcare providers and the expansion of tertiary services in major cities is improving early diagnosis. Diagnosis of Dwarfism Prenatal diagnosis is possible in some cases. Ultrasound scans can detect short limb length or other skeletal abnormalities from the second trimester onwards. In families with a known genetic condition, tests like amniocentesis or chorionic villus sampling can confirm the diagnosis during pregnancy. An early diagnosis of dwarfism allows for timely intervention, education planning, and appropriate medical management. It also helps families adjust, access support networks, and understand what to expect. The goal is not only to treat medical issues but also to foster healthy development and long-term well-being. [Next: Treatment of Dwarfism →]

Diagnosis of Dwarfism Read More »

Child with short stature sitting at a table with parents and a doctor

Treatment of Dwarfism

Treatment of Dwarfism The treatment of dwarfism focuses on managing associated health issues, promoting development, and supporting independence. While there is no cure for most forms of dwarfism, early intervention, proper medical care, and social support can significantly improve quality of life. Treatment plans vary depending on whether the dwarfism is caused by a skeletal condition or a hormonal deficiency. In cases of growth hormone deficiency—one of the causes of proportionate dwarfism—growth hormone therapy may be effective. Administered as daily injections, this treatment can help stimulate growth and increase final adult height. Success depends on early diagnosis and consistent monitoring, often under the supervision of a paediatric endocrinologist. However, growth hormone is not effective in skeletal dysplasias like achondroplasia. For disproportionate forms of dwarfism, the focus shifts to managing physical complications. Orthopaedic care is often required to address spinal curvature, bowed legs, joint pain, and limited mobility. Some children may need surgery to correct bone alignment, relieve pressure on the spinal cord, or straighten the legs. Physiotherapy helps improve strength, posture, and flexibility. Supportive therapies are also part of the treatment of dwarfism. Occupational therapy can assist with fine motor skills and adaptive techniques for daily tasks. Speech and language therapy may be needed, especially for children with hearing loss or delayed language development. Assistive devices such as customised furniture, step stools, or adapted vehicles can help individuals with short stature maintain independence at home, school, and work. Ensuring that children have equal access to education through inclusive classrooms and disability accommodations is essential. Surgery to lengthen the limbs is available but controversial. Limb-lengthening involves breaking bones and slowly extending them with external fixators. While it can significantly increase height, the process is painful, lengthy, and carries risks of complications. It is not widely recommended and remains a deeply personal choice for those who consider it. In South Africa, access to multidisciplinary care may vary. Urban centres offer better availability of specialists and therapies, while rural areas often face shortages. NGOs and advocacy groups play a crucial role in filling these gaps by providing support, equipment, and community outreach. Treatment of Dwarfism Mental and emotional support is another vital component. Children with dwarfism may face bullying, exclusion, or self-esteem challenges. Psychological counselling and participation in support groups help build confidence and resilience. Ultimately, the goal of treatment of dwarfism is to empower individuals to lead full, independent lives. With the right combination of healthcare, therapy, education, and community support, people with dwarfism can thrive in all aspects of life. [Next: Complications of Dwarfism →]

Treatment of Dwarfism Read More »

Woman with dwarfism and man in wheelchair talking in a modern building

Complications of Dwarfism

Complications of Dwarfism The complications of dwarfism vary depending on the underlying cause, but many individuals face health, physical, and social challenges throughout their lives. Early diagnosis and ongoing care can help manage these complications and reduce their long-term impact. One of the most common physical complications in disproportionate dwarfism, such as achondroplasia, is spinal stenosis. This narrowing of the spinal canal can compress the spinal cord, leading to pain, weakness, or difficulty walking. In severe cases, surgery may be needed to relieve pressure and restore mobility. Kyphosis (curved upper back) and lordosis (swayback) are also common and may require physical therapy or bracing. Joint pain and arthritis often appear earlier in life for people with dwarfism. The uneven stress on joints can lead to discomfort, reduced mobility, and the need for orthopaedic interventions. Bowed legs and hip abnormalities may require corrective surgery, particularly in growing children. Ear infections are another frequent issue. The structure of the Eustachian tubes in people with achondroplasia often leads to fluid build-up and recurrent infections. If untreated, this can result in hearing loss, which in turn can delay speech and language development. Regular hearing tests and ENT assessments are essential. Breathing issues Breathing issues, particularly sleep apnoea, can also occur due to a smaller airway and facial structure. Sleep studies may be recommended to diagnose and manage this condition, especially if snoring, fatigue, or interrupted breathing are present. In proportionate dwarfism, such as growth hormone deficiency, complications may include delayed puberty, fatigue, and reduced bone density. Without proper hormone management, long-term growth and development can be significantly affected. Beyond physical concerns, people with dwarfism may face social and psychological complications. These include bullying, discrimination, and barriers to employment or education. Lack of accessibility in buildings, transportation, or public spaces can further isolate individuals and reduce their independence. Emotional challenges like anxiety, depression, or low self-esteem may arise if support systems are lacking. Complications of Dwarfism In South Africa, navigating public spaces can be especially difficult for individuals with dwarfism, as many facilities are not adapted for short stature. This includes counters, toilets, transport systems, and classrooms. While disability rights are enshrined in the Constitution, practical implementation still falls short in many regions. Financial limitations and healthcare inequalities can also delay treatment and increase the risk of complications. Without access to physiotherapists, audiologists, and orthopaedic surgeons, many issues go unaddressed until they become severe. Understanding the complications of dwarfism helps families, caregivers, and health professionals take proactive steps. Early intervention, inclusive planning, and community education are key to reducing barriers and promoting health and well-being for people with dwarfism across all stages of life. [Next: Back to Overview →]

Complications of Dwarfism Read More »

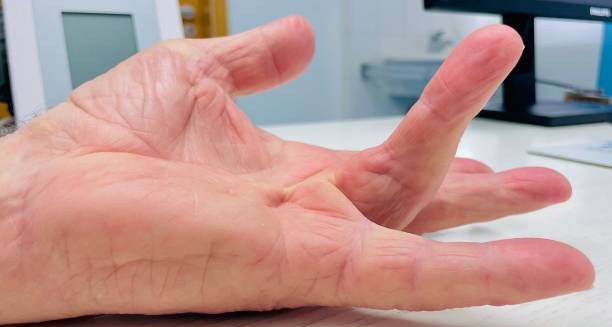
Hand affected by Dupuytren’s contracture with bent finger and tightened tissue

Dupuytren’s Contracture

Dupuytren’s Contracture Dupuytren’s contracture is a progressive condition that affects the connective tissue in the palm of the hand. Over time, this condition causes the fingers—most commonly the ring and little fingers—to curl inward towards the palm. Dupuytren’s contracture develops gradually and is not usually painful, but it can significantly reduce hand function and affect a person’s ability to grip or perform everyday tasks. The condition begins with the thickening of the fascia—a layer of connective tissue under the skin of the palm. As the tissue tightens and shortens, it pulls the fingers into a bent position. People with Dupuytren’s contracture may first notice a firm lump or nodule in their palm. As the disease progresses, fibrous cords form beneath the skin, eventually drawing the fingers into a fixed, bent position. Although the exact cause is unknown, genetics play a key role. The condition is more common in individuals of Northern European descent and often runs in families. Men over the age of 50 are most frequently affected. While less common in South Africa’s black population, Dupuytren’s contracture is still diagnosed among various demographic groups and should not be overlooked in clinical assessments. Risk factors include a family history of the condition, diabetes, epilepsy, excessive alcohol use, and smoking. However, many people with no obvious risk factors still develop the condition. Contrary to popular belief, repetitive hand use or injury is not a proven cause, although such factors may worsen symptoms in some people. Dupuytren’s Contracture Early stages may not require treatment, but as the contracture worsens, intervention may be needed. If left unmanaged, severe Dupuytren’s contracture can lead to permanent hand disability, making activities like writing, shaking hands, or opening a bottle difficult or impossible. Recognising the signs early and seeking medical advice can slow progression and preserve hand function. With modern treatments and therapies, many people regain significant mobility and reduce the impact of the condition on daily life. [Next: Causes of Dupuytren’s Contracture →]

Dupuytren’s Contracture Read More »

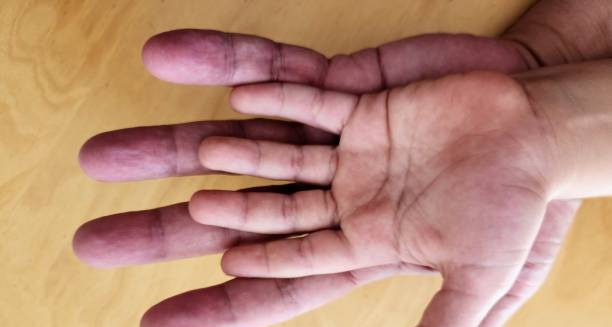
Comparison of normal and affected hands showing signs of Dupuytren’s contracture

Causes of Dupuytren’s Contracture

Causes of Dupuytren’s Contracture The causes of Dupuytren’s contracture are not fully understood, but research shows a strong link to inherited traits. It is widely accepted that genetics play a central role, as the condition often runs in families and is more prevalent among people of Northern European descent. If a close relative has the condition, there is a higher chance of developing it. One of the main causes of Dupuytren’s contracture is believed to be genetic mutations affecting the connective tissue in the palm. These changes cause the fascia to thicken and form fibrous cords over time, leading to the contracture. While the underlying mechanisms remain under investigation, scientists believe the condition is part of a broader group of fibromatoses—disorders involving abnormal growth of connective tissue. Certain lifestyle and medical factors may increase the risk or speed up progression. These include diabetes, epilepsy, excessive alcohol consumption, and smoking. While these are not direct causes, they are consistently found in higher rates among individuals with the condition. In South Africa, where diabetes rates are rising and access to early screening may be limited in some areas, these risk factors warrant attention. Men are more likely to develop the condition than women, and symptoms typically appear after age 40. However, some younger individuals may also develop early signs, particularly if they carry a strong genetic predisposition. The condition tends to be more aggressive in younger patients, with faster progression and more severe finger involvement. Although repetitive hand movements or manual labour were once considered possible triggers, studies now suggest that they are not primary causes of Dupuytren’s contracture. However, trauma or injury to the hand may worsen symptoms or bring an existing condition to medical attention sooner. Causes of Dupuytren’s Contracture Hormonal imbalances may also play a role. Some researchers suggest that testosterone may influence disease progression, which could explain why men are more commonly affected. However, hormonal treatments are not currently used in management due to limited supporting evidence. Another factor worth noting is the use of certain medications, particularly those used to manage epilepsy. Long-term use of anticonvulsant drugs like phenytoin has been associated with higher incidence, although the relationship is still debated. Understanding the causes of Dupuytren’s contracture helps identify at-risk individuals and encourages early monitoring. While prevention may not be possible due to its genetic basis, controlling lifestyle risk factors—such as smoking and blood sugar levels—can help slow the progression or delay onset in some cases. [Next: Symptoms of Dupuytren’s Contracture →]

Causes of Dupuytren’s Contracture Read More »

Scroll to Top