Mental Matters

Author name: admin

Hands holding a red heart-shaped object symbolising cardiac care

Treatment of Brugada Syndrome

Treatment of Brugada Syndrome Treatment of Brugada syndrome aims to prevent sudden cardiac death by controlling arrhythmias and reducing triggers. The main approaches in treatment of Brugada syndrome include lifestyle modifications, medication, and, in high-risk cases, an implantable cardioverter-defibrillator (ICD). The first line of defence is identifying and avoiding known triggers. PDoctors advise patients to avoid specific medications that can worsen Brugada ECG patterns. This includes some antiarrhythmics, tricyclic antidepressants, antihistamines, and anaesthetics. Patients should review a complete list of risky medications with their cardiologist. Fever management is crucial. Fever can unmask or exacerbate ECG changes and trigger dangerous arrhythmias. Doctors recommend giving antipyretics like paracetamol at the first sign of fever, especially for children with known Brugada syndrome. Doctors often recommend an ICD for high-risk patients, such as those with a history of cardiac arrest, fainting, or a spontaneous type 1 ECG pattern. This small device continuously monitors the heart’s rhythm and delivers a shock if it detects a life-threatening arrhythmia. It does not prevent arrhythmias from occurring but effectively treats them when they do. Doctors may use quinidine, an antiarrhythmic drug, in some cases to reduce arrhythmia episodes. Doctors often consider quinidine for patients who cannot get an ICD or who experience frequent shocks from their device. Lifestyle changes include avoiding excessive alcohol, staying well hydrated, managing stress, and ensuring good sleep. These steps help lower the chances of triggering dangerous arrhythmias. Treatment of Brugada Syndrome For asymptomatic patients with a Brugada ECG pattern but no history of fainting or family history of sudden death, careful monitoring may be sufficient. These individuals are generally not given ICDs unless their risk profile changes. Regular follow-ups with a cardiologist, possibly a specialist in inherited cardiac conditions, are essential. Treatment plans should be updated based on new symptoms, family screening results, or evolving risk factors. Successful treatment of Brugada syndrome focuses on prevention, education, and readiness — giving patients the tools to manage their condition and reduce life-threatening risk. [Next: Complications and Recovery from Brugada Syndrome →]


Treatment of Brugada Syndrome Read More »

Woman clutching chest in pain while sitting on a couch

Complications and Recovery from Brugada Syndrome

Complications and Recovery from Brugada Syndrome Complications and recovery from Brugada syndrome depend on the severity of the condition, how early it is diagnosed, and how effectively it is managed. The most serious complications of Brugada syndrome include sudden cardiac arrest, persistent arrhythmias, and psychosocial effects from living with a high-risk heart condition. The greatest concern is sudden cardiac death, often during rest or sleep. This can occur without warning, particularly in people who haven’t been diagnosed or treated. Fortunately, in those with ICDs, life-threatening arrhythmias can be successfully interrupted, preventing death. Another complication is psychological distress. People living with Brugada syndrome may experience anxiety about their heart health, especially if they’ve had an ICD shock or know others in their family who’ve died from the condition. Counselling or support groups can help address these concerns and improve quality of life. ICDs themselves can cause complications. These include inappropriate shocks (when the device fires unnecessarily), infection at the implantation site, and lead dislodgement. Despite these risks, the benefits of ICDs often outweigh the drawbacks in high-risk individuals. Medication side effects — particularly from quinidine — can include gastrointestinal issues, dizziness, or heart rhythm disturbances, so regular monitoring is required. Complications and recovery from Brugada Syndrome Recovery and long-term outlook vary. Many people with Brugada syndrome remain asymptomatic throughout life and never experience a cardiac event. Others, especially those with previous symptoms or a family history of sudden death, may require lifelong follow-up and ongoing treatment. Children with the condition require special care, including fever management and monitoring during illnesses, since their risk is often related to elevated body temperatures. Key to managing complications and recovery from Brugada syndrome is early detection, avoiding known triggers, and maintaining routine cardiac follow-up. With proper care, most individuals can live healthy, fulfilling lives with minimal disruption. Back to Overview

Complications and Recovery from Brugada Syndrome Read More »

Farmer interacting closely with a cow in a pasture

Brucellosis

Brucellosis – Overview Brucellosis is a bacterial infection that spreads from animals to humans, usually through unpasteurised dairy products, direct contact with infected animals, or inhaling airborne bacteria. This condition condition affects various organs in the body and can cause long-lasting fever, joint pain, fatigue, and even complications in the liver, heart, or nervous system if left untreated. Brucella bacteria cause the disease and commonly infect livestock like cattle, goats, sheep, pigs, and camels. Humans can become infected by drinking contaminated milk, handling infected meat, or coming into contact with animal secretions through open wounds or mucous membranes. It is considered an occupational hazard for farmers, veterinarians, abattoir workers, and lab technicians. Brucellosis occurs worldwide, especially in regions where animal vaccination programmes are lacking or where raw dairy consumption is common. These include parts of Africa, the Middle East, Asia, Latin America, and the Mediterranean. Brucellosis Because it mimics many other illnesses, this can be difficult to diagnose. Symptoms may be acute or develop gradually and include fever, night sweats, weakness, weight loss, and joint or muscle pain. Without proper treatment, the infection can become chronic and affect multiple body systems. Although not spread from person to person, brucellosis is a serious public health concern due to its potential for chronic disability and economic impact on livestock production. With timely diagnosis and antibiotics, most people make a full recovery. [Next: Causes of Brucellosis →]

Brucellosis Read More »

Veterinarian injecting a cow during livestock vaccination

Causes of Brucellosis

Causes of Brucellosis Causes of brucellosis centre around the transmission of Brucella bacteria from animals to humans. The leading causes of brucellosis include consuming unpasteurised dairy products, direct contact with infected animals, and occupational exposure in veterinary and agricultural settings. Brucella bacteria live in the reproductive organs, milk, and other bodily fluids of infected animals. Humans most often contract the disease by ingesting unpasteurised milk, cheese, or yoghurt from infected goats, sheep, or cows. In many rural areas, pasteurisation is not routine, increasing the risk of transmission. Another significant cause is direct contact with animals or their secretions. Farmers, butchers, and veterinarians may handle placentas, aborted foetuses, or infected blood without adequate protective gear. The bacteria enter the body through small skin wounds, cuts, or mucous membranes in the eyes, nose, or mouth. People can also inhale brucellosis bacteria in certain environments, such as laboratories or farms. Laboratory technicians handling Brucella cultures and slaughterhouse workers exposed to aerosolised particles face a higher risk of infection. Airborne transmission, while rare in the general public, is a known risk in occupational settings. The disease rarely spreads between people, but transmission can occasionally occur through blood transfusion, sexual contact, or from mother to baby during birth or breastfeeding. Causes of Brucellosis Animals become infected by eating contaminated feed, licking aborted foetal tissue, or coming into contact with contaminated environments. Infected livestock often show few signs, making the bacteria difficult to detect without specific testing. In regions where animal vaccination programmes are not well enforced and where people consume raw dairy, the causes of brucellosis are deeply rooted in both agricultural and cultural practices. Prevention focuses on animal health, food safety, and occupational hygiene. [Next: Symptoms of Brucellosis →]

Causes of Brucellosis Read More »

Woman lying in bed appearing feverish and fatigued

Symptoms of Brucellosis

Symptoms of Brucellosis Symptoms of brucellosis can vary widely and may appear suddenly or develop slowly over time. The most common symptoms of brucellosis include intermittent fever, night sweats, joint pain, fatigue, and muscle aches. Because the condition mimics many other illnesses, it is often misdiagnosed in its early stages. One of the earliest and most noticeable symptoms is an undulating fever — meaning it rises and falls throughout the day. The fever may be low-grade or spike to 39–40°C, often accompanied by chills and profuse night sweats with a distinctive “wet hay” odour in some cases. Joint and muscle pain are also common, particularly in the lower back, knees, hips, and wrists. Inflammation of joints (arthritis) or spinal discs (spondylitis) may develop, especially in chronic cases. This symptom is frequently mistaken for rheumatic conditions or other musculoskeletal disorders. Fatigue and weakness may become debilitating. Many patients report feeling exhausted for weeks or months, even after the fever subsides. This prolonged tiredness can interfere with work, daily responsibilities, and mental wellbeing. Other symptoms include headache, loss of appetite, weight loss, irritability, and abdominal discomfort. Enlarged liver or spleen (hepatosplenomegaly) is sometimes found on physical examination or imaging. Symptoms of Brucellosis In men, brucellosis can cause inflammation of the testicles (orchitis), which may lead to infertility if untreated. Rare complications include inflammation of the heart lining (endocarditis), nervous system involvement (neurobrucellosis), or inflammation of the eyes (uveitis). The chronic form of brucellosis — where symptoms persist or recur for more than a year — is especially challenging. It may present with vague, fluctuating complaints and lead to emotional distress or misdiagnosis as depression or chronic fatigue syndrome. Recognising symptoms of brucellosis early allows for prompt treatment and prevents complications. Anyone with persistent fever, joint pain, or fatigue who has travelled to or lives in an at-risk area should seek medical advice and disclose any contact with livestock or unpasteurised food. [Next: Diagnosis of Brucellosis →]

Symptoms of Brucellosis Read More »

Syringe labelled brucellosis held by gloved hands

Diagnosis of Brucellosis

Diagnosis of Brucellosis Diagnosis of brucellosis requires a combination of clinical evaluation, laboratory testing, and a detailed patient history. An accurate diagnosis of brucellosis is vital. As the disease can mimic other infections or autoimmune conditions, delaying treatment if not correctly identified. Doctors begin by reviewing symptoms and asking about risk factors such as occupation (e.g. farming, veterinary work). Recent travel to endemic areas, and consumption of unpasteurised dairy products. People with prolonged fever, muscle pain, and fatigue — especially in rural or agricultural settings — should be evaluated for brucellosis. Physical examination may reveal fever, enlarged lymph nodes, joint tenderness, or hepatosplenomegaly. These findings are non-specific, so further testing is needed. Blood cultures are the most definitive diagnostic tool. Isolating Brucella bacteria from the blood confirms the infection, though it may take several days to grow in the lab. In chronic cases, the bacteria may be harder to detect. Furthermore, requiring repeated cultures or sampling from infected tissues or bone marrow. Serological tests such as the standard agglutination test (SAT), ELISA, or Coombs test measure antibodies to Brucella and help detect both acute and chronic infections. Rising antibody levels in repeat tests can confirm active infection. PCR (polymerase chain reaction) testing, though not widely available, offers rapid detection by identifying Brucella DNA. It is useful in complicated or advanced cases. Diagnosis of Brucellosis Additional tests like full blood counts, liver function tests, or inflammatory markers (ESR, CRP) can support the diagnosis and monitor disease severity, though they are not specific to brucellosis. Imaging studies such as ultrasound, CT scan, or MRI may be used to identify complications — such as abscesses, joint damage, or inflammation of internal organs. A timely diagnosis of brucellosis ensures appropriate treatment, reduces the risk of chronic complications, and improves the likelihood of full recovery. Doctors should always consider brucellosis in patients with fever of unknown origin and relevant exposure history. [Next: Treatment of Brucellosis →]

Diagnosis of Brucellosis Read More »

Patient receiving intravenous treatment for brucellosis

Treatment of Brucellosis

Treatment of Brucellosis Treatment of brucellosis focuses on eliminating the bacteria, relieving symptoms, and preventing recurrence. Because Brucella bacteria are hardy and slow-growing, effective treatment of brucellosis requires a combination of antibiotics taken for several weeks. The standard therapy includes doxycycline (an oral antibiotic) taken for at least six weeks, usually combined with an initial course of streptomycin injections or rifampicin taken orally for the first few weeks. This dual approach helps prevent relapses, which are common with shorter or incomplete treatment courses. In cases where streptomycin is not suitable, rifampicin may be used as the second drug alongside doxycycline for six weeks. This regimen is preferred in areas with limited access to injectable medications or in outpatient settings. For children, pregnant women, or those with specific contraindications, alternative antibiotics such as trimethoprim-sulfamethoxazole may be considered, always under specialist supervision. Severe or complicated cases — involving the nervous system, heart, bones, or genitals — require longer treatment, often up to 12 weeks or more. In these cases, intravenous antibiotics may be administered, followed by extended oral therapy. Painkillers and anti-inflammatory medication can help manage fever, joint pain, and fatigue during treatment. Bed rest is recommended during the acute phase, especially in patients with high fever or complications. Hospitalisation may be needed for those with severe disease, serious complications, or individuals unable to take oral antibiotics reliably. Treatment of Brucellosis Patients should complete the full course of medication even if symptoms improve early. Incomplete treatment increases the risk of relapse, which is a common challenge in managing brucellosis. Follow-up is important. Doctors will monitor symptom resolution, repeat blood tests, and assess for any lingering complications over several months. Proper treatment of brucellosis ensures most people recover fully, although fatigue and joint pain may persist for a while. Early diagnosis and adherence to antibiotic regimens are key to successful outcomes. [Next: Complications and Recovery from Brucellosis →]

Treatment of Brucellosis Read More »

Woman resting in a hospital bed during recovery from brucellosis

Complications and Recovery from Brucellosis

Complications and Recovery from Brucellosis Complications and recovery from brucellosis depend on how early the disease is diagnosed and how effectively it is treated. While most people recover completely, untreated or chronic cases can lead to serious complications and recovery from brucellosis challenges that affect multiple organ systems. One of the most common complications is relapse. This happens in up to 10–20% of cases, often due to incomplete treatment or poor adherence to antibiotic regimens. Symptoms such as fever, fatigue, and joint pain may return within months. Osteoarticular complications are frequent. These include arthritis, sacroiliitis (inflammation of the pelvic joints), or spondylitis (spinal infection). These conditions can cause persistent back pain and may require extended antibiotic therapy and physiotherapy. Neurobrucellosis — involving the brain or spinal cord — is a rare but serious complication. It can lead to meningitis, encephalitis, or nerve damage, and may result in seizures or long-term neurological problems. Endocarditis (infection of the heart valves) is the leading cause of death in brucellosis patients. It requires intensive antibiotic treatment and sometimes surgical valve replacement. Other complications include hepatitis, orchitis (testicular inflammation), abscess formation in the liver or spleen, and chronic fatigue. Complications and Recovery from Brucellosis Recovery from uncomplicated brucellosis typically takes a few weeks, although full energy levels may return more slowly. Patients are advised to rest, hydrate well, and avoid strenuous activity until cleared by their doctor. Preventing relapse is a key part of recovery. This means completing the full course of antibiotics, attending follow-up appointments, and reporting any returning symptoms early. Emotional support is also important. Chronic brucellosis can lead to depression or anxiety, particularly when symptoms linger or affect work and family life. With proper care, most individuals overcome complications and recovery from brucellosis successfully. Prevention remains the best strategy — through safe food practices, animal vaccination, and occupational safety in high-risk settings. Back to Overview

Complications and Recovery from Brucellosis Read More »

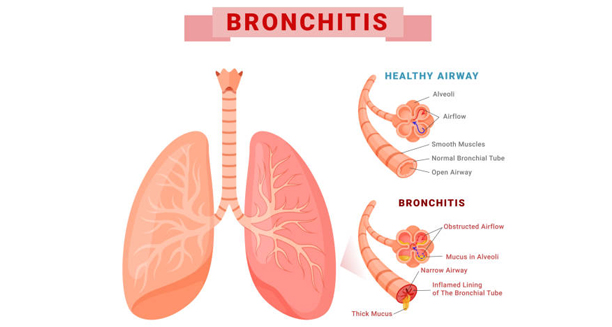
Medical illustration showing healthy lungs versus lungs affected by bronchitis

Bronchitis

Bronchitis – Overview This condition bronchitis is a condition where the lining of the bronchial tubes — the airways that carry air to and from the lungs — becomes inflamed. This condition causes a persistent cough, production of mucus (sputum), chest discomfort, and sometimes shortness of breath. It can be acute, lasting a few days to weeks, or chronic, which persists over months and often recurs. Acute bronchitis is usually caused by a viral infection, such as a cold or flu. It commonly affects people of all ages and typically resolves on its own. The chronic version, on the other hand, is a long-term condition often linked to smoking or exposure to air pollutants, and is one form of chronic obstructive pulmonary disease (COPD). In both types, the inflammation of the airway linings leads to excess mucus production, which irritates the lungs and triggers coughing. Acute bronchitis is more prevalent in colder months and may follow an upper respiratory tract infection. Chronic is more common in adults, especially smokers. Bronchitis The hallmark symptom is a persistent cough, which may produce clear, yellow, or greenish mucus. Other symptoms include fatigue, wheezing, chest tightness, and low-grade fever. While the acute version is self-limiting, the chronic condition requires long-term management. Most people with bronchitis recover without complications. However, in vulnerable groups — such as the elderly, infants, or people with weakened immune systems — the condition can lead to more serious respiratory illnesses like pneumonia. [Next: Causes of Bronchitis →]

Bronchitis Read More »

Doctor examining chest X-ray to assess lung inflammation and bronchitis cause

Causes of Bronchitis

Causes of Bronchitis Causes of bronchitis vary depending on whether the condition is acute or chronic. The most common causes of bronchitis include viral infections, smoking, air pollution, and exposure to irritants like dust or chemical fumes. Understanding the cause helps determine the best treatment and prevent future episodes. Acute bronchitis is usually caused by viruses such as rhinovirus, influenza, parainfluenza, or respiratory syncytial virus (RSV). These viruses infect the nose, throat, and then travel down to the bronchi, triggering inflammation. Because it’s viral, antibiotics are not effective unless there’s a secondary bacterial infection. Bacterial infections are a less common cause of acute bronchitis. Mycoplasma pneumoniae, Chlamydia pneumoniae, and Bordetella pertussis (which causes whooping cough) are examples of bacteria that may lead to bronchitis, particularly in people with compromised immunity. Chronic bronchitis is almost always linked to long-term irritation of the lungs. The main culprit is cigarette smoke. Smokers inhale harmful substances that damage the bronchial linings and reduce the lungs’ ability to clear mucus, making them prone to persistent inflammation and infection. Causes of bronchitis Exposure to environmental pollutants such as smog, dust, or industrial chemicals can also cause chronic irritation. People working in mining, farming, or manufacturing are at higher risk. Repeated bouts of acute bronchitis, particularly if poorly treated or combined with ongoing irritant exposure, can eventually lead to chronic bronchitis. Other risk factors include passive smoking, weak immune systems, gastro-oesophageal reflux disease (GORD), and underlying conditions such as asthma or allergic rhinitis. Recognising the causes of bronchitis is essential for both treatment and prevention. Avoiding smoking, reducing exposure to pollutants, and managing infections early can lower the risk of bronchitis, especially in high-risk individuals. [Next: Symptoms of Bronchitis →]

Causes of Bronchitis Read More »

Scroll to Top