Mental Matters

Author name: admin

Diagnosis of Labial Fusion

Diagnosis of Labial Fusion

Diagnosis of labial fusion is typically straightforward and non-invasive, relying heavily on physical examination and a careful review of the patient’s symptoms and medical history. In most cases, this condition is recognised during routine check-ups or when parents express concerns about their child’s urinary patterns, genital appearance, or hygiene difficulties. Because diagnosis of labial fusion involves sensitive areas and young patients, the clinician’s approach must be both skilled and compassionate to avoid causing discomfort or distress. Labial fusion, also known as labial adhesions or labial agglutination, refers to the partial or complete joining of the labia minora in young girls or, rarely, postmenopausal women. Understanding the age group and context plays a vital role in diagnosis. In children, this condition often appears between three months and six years of age. In adults, it may result from hormonal deficiencies, especially oestrogen loss, or from inflammatory conditions. Medical History in the Diagnosis of Labial Fusion The first step in diagnosis of labial fusion involves taking a thorough medical history. Clinicians often ask caregivers about unusual urinary symptoms like dribbling, urgency, infections, or trouble with toilet training. They may also ask about hygiene habits, previous infections, or episodes of genital irritation. In older children or adults, questions may include discomfort during urination, itching, or pain when wearing tight clothing. After gathering history, the next part of diagnosis of labial fusion includes a gentle visual exam of the external genital area. In young children, the exam usually works best when the child lies on her back with knees bent or in the frog-leg position. The clinician will look at the vulva to see if the labia minora are partly or fully stuck together. A thin, pale line of tissue joining the labia at the midline—often from the back end near the anus up toward the clitoris—is a common sign. Physical Signs Supporting the Diagnosis of Labial Fusion In partial fusion, both the vaginal opening and urethral meatus may still be visible, and urine can flow without issue. However, in complete fusion, these openings are hidden. Often, only a small pinhole remains for urine to pass. The degree of adhesion is important because it guides the next steps in care. It also helps doctors rule out other conditions like imperforate hymen or urogenital sinus disorders. Doctors must also tell the difference between normal anatomical variations and true labial fusion. In newborns and infants, the labia minora may look close together due to maternal hormones. This is normal and usually goes away on its own. Similarly, mild adhesions that don’t cause problems with hygiene or function may just need monitoring. Clinical judgement is key to avoid unnecessary treatment when simple observation is enough. Diagnosing Labial Fusion in Postmenopausal Women In postmenopausal women, diagnosis of labial fusion can be more complicated. Conditions like lichen sclerosus or other vulval skin diseases may appear at the same time. In these cases, doctors also check for skin changes, ulcers, or scarring. If there is any concern about a hidden illness or cancer, a biopsy may be needed. Still, in most situations, a simple visual exam combined with the patient’s history is enough. Sometimes, parents bring their child to the doctor fearing sexual abuse because the genitals look different. Here, understanding the diagnosis of labial fusion is essential to avoid misjudging the case. Trained professionals can usually tell the difference. Labial fusion presents as a smooth, thin adhesion with no signs of injury, bleeding, or trauma. Additional Tools in the Diagnosis of Labial Fusion Doctors rarely need imaging tests when diagnosing labial fusion. But if the child can’t urinate properly or has complications, an ultrasound might help. This scan checks the bladder or kidneys for issues like urine backup or leftover urine after urination. These problems are rare and usually happen only with complete fusion. Lab tests are not often required either. However, if a child keeps getting urinary infections, a urine test and culture may be helpful. If bacteria are found, doctors can treat the infection at the same time as the fusion. Another key part of diagnosis of labial fusion is addressing emotional concerns. The exam must be gentle. Clear communication and calm explanations help ease fear for both child and caregiver. Many parents worry that labial fusion might affect future fertility or sexual development. Reassurance and accurate information can reduce stress and build trust. Clinicians should also write down important details such as the extent of the fusion, whether the openings are visible, if there are symptoms, and whether the condition causes complications. These notes help track progress over time, especially if doctors choose to wait and monitor or start treatment. In summary, diagnosis of labial fusion relies on taking a good history and doing a simple exam. Most of the time, no scans or invasive tests are needed. A caring, informed approach helps identify the condition, rule out other issues, and guide the best treatment plan. The goal is always to restore normal anatomy, ensure comfort, and support the child and family with kindness. [Next: Treatment of Labial Fusion →]


Diagnosis of Labial Fusion Read More »

Treatment of Labial Fusion

Treatment of Labial Fusion

Treatment of labial fusion is typically straightforward and non-invasive, particularly when identified early. In most cases, labial fusion can be managed with little intervention, especially if it causes no symptoms. However, if there are issues such as trouble urinating, discomfort, or hygiene problems, active care becomes necessary. The main goal of the treatment of labial fusion is to restore normal anatomy, improve urination, and lower the risk of future problems. The first step is to decide whether treatment is even needed. Labial fusion is a harmless condition and often gets better with time as a child grows. If there are no symptoms and a partial opening is still visible, doctors may simply recommend watching and waiting. During this period, parents are advised to keep the area clean and avoid rough wiping, which can irritate the skin and make things worse. When Treatment of Labial Fusion Becomes Necessary When symptoms are present or the labia are fully fused, treatment of labial fusion usually starts with oestrogen cream. This cream helps separate the labia by thickening and maturing the skin. Doctors often prescribe conjugated oestrogen or oestriol cream, applied once or twice a day for 2 to 4 weeks. Correct use of the cream is very important. Caregivers should apply a small amount with a clean finger or cotton swab. The cream should be gently rubbed along the line where the labia are stuck—never forced open. Over time, the tissue softens and separates naturally. It’s also crucial not to overuse the cream. Too much can cause mild side effects, like skin irritation, darkening of the skin, or even slight breast development, which usually goes away after treatment stops. In most cases, oestrogen cream works well. More than 80% of children treated this way see full separation. However, the fusion may return in up to 30% of cases. This often happens when irritants remain, or hygiene continues to be poor. To help prevent this, doctors recommend gentle cleaning with warm water, avoiding scented products, and using barrier creams like petroleum jelly after separation. Additional Options in the Treatment of Labial Fusion If the condition doesn’t respond to oestrogen, a mild steroid cream like hydrocortisone might be used. This cream reduces swelling and helps break down the tissue that holds the labia together. Steroids should only be used under medical guidance, as overuse can thin the skin or make it more sensitive. In rare cases, when other treatments fail or serious problems arise—like urinary retention or frequent infections—a minor surgery may be needed. Surgical treatment of labial fusion is simple and done in a clinic. The doctor carefully separates the labia with a blunt tool, often under local anaesthetic. The procedure is quick and generally painless for children. After surgery, care at home is essential. Doctors usually suggest using oestrogen cream or petroleum jelly for a few weeks to prevent the labia from fusing again. They may also advise parents to gently pull the labia apart during cleaning routines, which keeps the tissue open as it heals. Tailoring Treatment of Labial Fusion for Older Patients In older girls and postmenopausal women, hormonal changes can affect treatment. In these cases, oestrogen cream remains useful, but hormone replacement pills may also help if vaginal dryness or other symptoms are present. If a skin condition like lichen sclerosus is found, doctors must treat that as well. One key part of treatment of labial fusion—often forgotten—is emotional support. For young children, any exam or treatment involving the genitals can feel scary. Parents and healthcare workers should explain each step in a calm, age-appropriate way. This helps the child feel safe and not ashamed. For older patients, counselling or support groups may help ease anxiety or self-esteem concerns. Preventing future fusion is an important part of long-term care. Teaching caregivers about gentle cleaning, avoiding irritants, and watching for early signs of fusion can stop the issue from returning. Keeping the area dry and avoiding wet clothing also helps reduce irritation. Raising awareness among general practitioners and paediatricians is vital. When they understand the condition, they can make the right decisions and avoid unnecessary referrals or treatments. In conclusion, treatment of labial fusion works well when done with care and clear guidance. Oestrogen creams are the main treatment, supported by good hygiene and sometimes surgery. Most children recover fully and continue to grow up healthy and confident. [Next: Complications of Labial Fusion →]

Treatment of Labial Fusion Read More »

Complications of Labial Fusion

Complications of Labial Fusion

Complications of labial fusion can vary depending on the severity of the adhesion, the person’s age, and whether treatment is given correctly. In many cases, labial fusion is harmless and resolves on its own or with simple treatment. However, if left untreated or if it returns repeatedly, it can cause both physical and emotional problems. Understanding the complications of labial fusion helps ensure early diagnosis, proper care, and long-term success. Urinary Tract Infections and Urinary Obstruction The most common issue is a urinary tract infection (UTI). When the labia minora stick together, they can block the vaginal or urethral openings. This can trap urine or make urination difficult. Trapped urine creates a warm, moist environment where bacteria can grow, leading to UTIs. Symptoms may include painful urination, frequent urination, bedwetting in toilet-trained children, fever, or general discomfort. If these infections are not treated quickly, they can affect kidney health. Another problem is poor urine flow. When the fusion is nearly complete, the urine stream may be weak or misdirected. This can lead to dribbling, urine leakage after peeing, or trouble emptying the bladder. Some children may strain to urinate, which can cause bladder problems such as instability or incontinence over time. Discomfort, Inflammation, and Skin Problems Children with labial fusion often experience discomfort in the genital area. This can be due to trapped urine or natural secretions, which may cause redness or irritation. The skin can become inflamed and fragile. As a result, small tears may form during normal activities like walking or playing. These can be painful and may lead to slight bleeding, which often alarms caregivers. Emotional and Psychological Effects Complications of labial fusion can also affect emotional health. Younger children may cry or show discomfort when urinating or during hygiene routines. Older girls may feel embarrassed or anxious, especially if the fusion continues into puberty. They might worry about their body or feel different from their peers. This emotional stress can impact their confidence and how they view their bodies. Recurrence and Repeat Treatments One of the most common long-term issues is recurrence. Even after successful treatment, the fusion can return. This is more likely if factors like low estrogen, poor hygiene, or irritation are not addressed. Repeated cases may need more courses of estrogen cream or other treatments. Although recurrence is not harmful, it can frustrate families and reduce their trust in the treatment process. Misdiagnosis and Over-Treatment Sometimes, doctors unfamiliar with labial fusion may mistake it for other conditions. These include birth defects, infections, or even signs of trauma. This can lead to unnecessary tests, referrals, or concern. Accurate diagnosis is essential to avoid causing extra stress for the family. Treatment Side Effects and Rare Surgical Needs Topical estrogen creams are usually safe, but overuse or incorrect use can cause side effects. These may include breast swelling, vaginal discharge, or skin darkening. These effects are temporary and mild, but they may still worry caregivers. If treatment is stopped too early, the fusion may not fully resolve. In rare cases, surgery may be needed. This usually happens when creams do not work or when the fusion causes severe blockage or ongoing infections. Surgery is often simple and successful, but like any procedure, it carries small risks such as infection, injury, or scarring. Good follow-up care is key to avoid re-fusion or healing problems. Social Challenges and School Difficulties Social issues can also arise. Children who leak urine or have repeated infections may feel embarrassed. They may avoid school, sports, or time with friends. These struggles can affect their mood and confidence. Early treatment and sensitive care can help protect their emotional well-being. Complications in Postmenopausal Women Labial fusion is less common in older women, but it can still occur after menopause. The drop in estrogen can cause the labia to stick together. This may lead to pain, trouble with hygiene, or pain during sex. These issues can affect relationships and quality of life. Scarring and Caregiver Strain If the fusion is not treated, or if infections keep coming back, the tissue may scar. Scar tissue is tougher and less flexible, which can make future treatment harder and more painful. Finally, caregivers may feel overwhelmed. Caring for a child with labial fusion involves daily cleaning, applying medicine, and talking about private topics. Some caregivers may feel unsure or unsupported. This stress can affect family dynamics and reduce their confidence in managing the condition. Conclusion Complications of labial fusion can range from mild irritation to more serious issues like urinary problems, repeated infections, and emotional distress. Fortunately, most of these can be prevented or treated with proper care. A complete approach that includes physical, emotional, and social support offers the best results for both the child and their family. [Next: Back to Overview →]

Complications of Labial Fusion Read More »

Overview of Kyphosis

Overview of Kyphosis

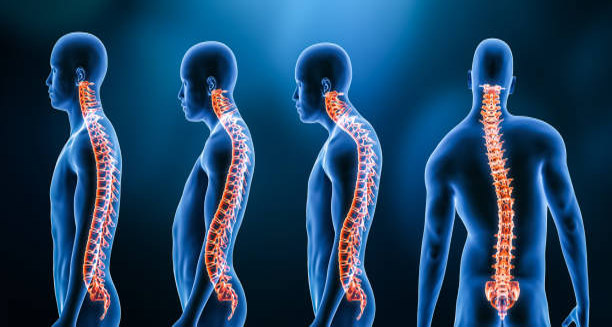
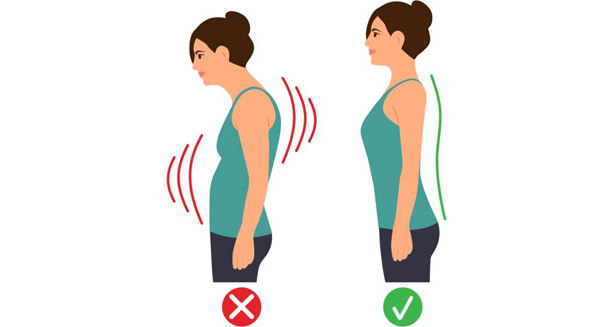
The overview of kyphosis begins with an understanding of this postural and structural condition that affects the natural curvature of the spine. Kyphosis often shows up as a forward rounding of the upper back. The overview of kyphosis includes people of all ages, but it happens more often in teens and older adults. Mild cases usually do not cause any symptoms. However, more serious cases can bring pain, stiffness, and daily limits in movement. This condition causes a strong outward bend in the upper spine, making the back look hunched. This curve might be flexible or stiff. That depends on what caused it. It’s important to tell the difference between normal posture and harmful kyphosis that needs medical care. Some people develop it slowly over time. Others get it suddenly because of an injury, illness, or their genes. Types and Causes in the Overview of Kyphosis Many types of kyphosis exist, and each type has its own cause and path. The most common one is postural kyphosis. It often shows up in teenagers because of slouching or sitting badly. This kind usually doesn’t involve bone problems. People can often fix it with exercises and better posture. In contrast, Scheuermann’s kyphosis shows up during the teen years too, but the spine bones develop in an uneven way. This type often needs more treatment. Another type, congenital kyphosis, is already present at birth. It happens when the spine doesn’t form correctly in the womb. Sometimes, surgery is needed early in life. For older people, kyphosis often happens because of bone thinning, or osteoporosis. Weak bones can break or collapse, causing the spine to round. This version, called osteoporotic kyphosis, can raise the chance of spine fractures and even affect breathing. Other conditions, such as arthritis, infections, or spine tumours, can also cause the spine to curve more. Symptoms and Emotional Impact in the Overview of Kyphosis People usually first notice kyphosis when they see a hump or curve in the upper back. Some feel very tired or stiff. Others find it hard to stand straight for a long time. Even when there’s no pain, bad posture can cause muscle strain, pinched nerves, or breathing trouble in worse cases. In more serious cases, kyphosis can lower someone’s ability to move or live fully. It might also lower their self-esteem because of how they look. This is especially true for kids and teens. A visible spine curve can lead to worry, low confidence, or sadness. Sadly, doctors might miss these emotional signs. That’s why it’s important to treat both the body and the mind. Diagnosis and Treatment in the Overview of Kyphosis Doctors find out if someone has kyphosis by doing a physical check, asking about health history, and taking scans. X-rays show the spine curve clearly. MRI or CT scans can look deeper into soft tissues or nerve problems. Getting the right diagnosis helps doctors decide if the kyphosis comes from posture, bone shape, or another illness. Treatment depends on what kind of kyphosis someone has, how serious it is, and their age. For postural kyphosis, changes in daily habits, special exercises, and good furniture may help. But if the curve is more serious or caused by misshapen bones, people might need a back brace. In some cases, surgery is the best choice. Doctors might do spinal fusion to fix and support the spine, but healing from that takes time. Prevention and Long-Term Outlook in the Overview of Kyphosis People can lower their risk of kyphosis by keeping their spine healthy. That means sitting and standing straight, eating foods rich in calcium and vitamin D, and doing exercises that strengthen bones. Older adults should get regular bone checks. Catching osteoporosis early can stop spine breaks that lead to a hunched back. Ongoing care also matters a lot. Physical therapy can make the back and stomach muscles stronger. It also helps the spine stay flexible. Sometimes, back supports can help. Learning how to lift things safely and setting up work areas to help posture also protects the spine. The overview of kyphosis should also cover what the future may look like. Some mild cases stay the same for years. But others may slowly get worse. If no one treats serious spinal curves, it can hurt breathing, press on the stomach, or even affect the nerves. These effects make daily life much harder. Full Management in the Overview of Kyphosis To manage kyphosis well, doctors must find it early and use a full care plan. Many types of health workers may be involved—general doctors, bone specialists, physical therapists, and even mental health experts. Loved ones can help too. Patients who understand their condition are more likely to follow treatment and get better results. In the end, the overview of kyphosis shows how key it is to understand all the causes, types, and effects of this spine problem. With early care and the right support, many people with kyphosis can live full, active lives. The main goal is to find the issue soon and treat both the physical and emotional parts of it. [Next: Causes of Kyphosis →]

Overview of Kyphosis Read More »

Causes of Kyphosis

Causes of Kyphosis

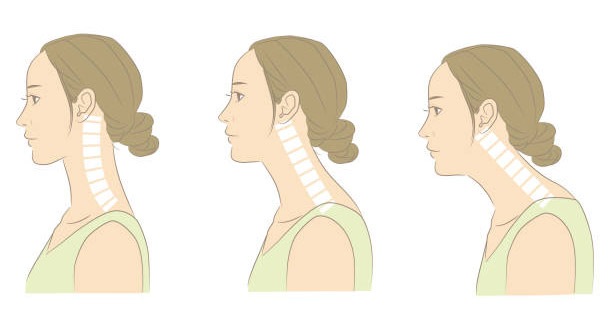
Understanding the causes of kyphosis is essential for accurate diagnosis and effective treatment planning. The causes of kyphosis vary depending on when it starts, a person’s health, and daily habits. Some people are born with spinal problems, while others develop them later. Poor posture, injuries, or age-related changes often play a role. Since kyphosis is a symptom rather than a single disease, its causes need to be looked at from both a medical and mechanical angle. A common cause is postural kyphosis, especially in teens and young adults. It usually results from poor posture or slouching. This type is flexible, meaning the back curve improves when the person stands up straight. It does not involve structural damage to the spine. In today’s digital world, longer screen time and more sitting have made postural kyphosis more common, particularly among students and office workers. A more serious form is Scheuermann’s kyphosis, which usually begins during teenage years. This condition comes from wedge-shaped bones in the spine. Unlike postural kyphosis, it causes a rigid curve that does not go away with better posture. Experts think Scheuermann’s disease may be caused by genetic or growth problems. It affects more males than females and often causes back pain. Congenital kyphosis is another cause. This form develops before birth when the spine does not form or connect properly. The result is a stiff and increasing curve that gets worse as the child grows. Without treatment, it may press on the spinal cord and cause nerve problems. Surgery is often needed, and early detection helps with better planning. Structural and Medical Causes of Kyphosis Degenerative changes are another major factor, especially in older adults. As people age, bones and discs in the spine break down. This leads to degenerative kyphosis, often seen with osteoarthritis or disc thinning. These changes make the spine lean forward. Weakened ligaments and stiff joints make the problem worse. Osteoporosis can also cause osteoporotic kyphosis. In this case, the spine weakens and collapses due to tiny fractures. These vertebrae turn wedge-shaped and create the hunched appearance. It often goes unnoticed until someone has back pain, shrinks in height, or the curve becomes obvious. Injuries can cause post-traumatic kyphosis. Accidents, falls, or sports injuries may fracture the spine. When these fractures heal poorly, they lead to a bent or curved back. Some cases also include nerve damage. Surgery may be needed if the curve is severe or causes other problems. Infections, such as spinal tuberculosis (Pott’s disease), can damage spinal bones and discs. This causes the spine to collapse, leading to kyphosis. It mostly affects people in developing areas or with weak immune systems. Quick treatment with antibiotics and sometimes surgery is important to stop the curve from worsening. Spinal Tumours Spinal tumours, either cancerous or not, can also lead to kyphosis. Tumours may press on the spine, weaken the bones, or cause the spine to collapse. In such cases, treating both the tumour and the spinal curve is necessary. Neuromuscular diseases like cerebral palsy, muscular dystrophy, and spinal muscular atrophy also contribute. These conditions weaken the muscles that support the spine. Over time, this leads to poor posture and spinal deformities. Treatment may include braces, therapy, or surgery. Sometimes, kyphosis results from medical treatments. For example, past spine surgery, radiation therapy, or poor surgical techniques can cause the spine to curve. These are called iatrogenic causes. They often need revision surgery. Lifestyle habits also play a role in the causes of kyphosis. Lack of exercise, poor sitting posture, and being overweight weaken the muscles that hold the spine upright. Over time, these habits encourage a curved back. Simple steps like moving more, sitting properly, and strengthening the back can help. In summary, the causes of kyphosis include many factors such as age, genetics, bone strength, posture, injuries, and other health conditions. Knowing the cause helps doctors create a better treatment plan. Acting early can stop the curve from getting worse and protect spinal health. [Next: Symptoms of Kyphosis →]

Causes of Kyphosis Read More »

Symptoms of Kyphosis

Symptoms of Kyphosis

Recognising the symptoms of kyphosis is crucial for early intervention and successful treatment. The symptoms of kyphosis can vary widely depending on the type, severity, and underlying cause of the condition. In some cases, the spinal curvature may be mild and cause no symptoms. In others, it can lead to physical discomfort, limited movement, and emotional challenges. That’s why understanding the full range of symptoms is important for healthcare providers, caregivers, and patients alike. Visible Signs and Spinal Curvature in Kyphosis The most noticeable symptom is an abnormal spinal curve, often described as a rounded or hunched back. This curve usually affects the upper (thoracic) spine and may cause someone to look stooped or slouched. In mild postural kyphosis, the change in appearance might only show after long periods of standing or sitting. In more severe forms, like Scheuermann’s disease or congenital kyphosis, the curve becomes stiff and permanent. Children or teens with these conditions may develop a visible hump, especially during growth spurts. Back pain is another common symptom, especially in adults. This pain often comes from extra strain on the muscles, ligaments, and discs caused by the spine’s poor alignment. Postural kyphosis may lead to dull, on-and-off pain, which worsens after sitting or standing too long. In contrast, Scheuermann’s kyphosis causes more constant pain due to its rigid curve and disc issues. Degenerative or osteoporotic kyphosis in older adults also often causes ongoing pain in the lower or mid-back. Fatigue, Height Loss, and Physical Limitations Fatigue is another symptom that may go unnoticed but plays a big role. The unusual spinal curve forces the muscles of the back and neck to work harder to keep the body upright. This added effort leads to tiredness, especially after physical activity. Some people also feel a sense of heaviness in the back, making it hard to complete everyday tasks or stay active. Loss of height is a frequent sign, particularly in older adults with osteoporotic kyphosis. As the spine curves and vertebrae compress, height gradually decreases. This often comes with a forward-leaning posture and trouble standing up straight. These visible changes may affect self-esteem, especially in teens and those concerned with their appearance. In severe or advanced cases, the symptoms of kyphosis go beyond discomfort. Movement in the upper back may become limited. Bending, twisting, or lifting can become harder. When the spine becomes very stiff, even simple tasks like dressing, tying shoes, or reaching overhead may be difficult. Neurological and Respiratory Symptoms of Kyphosis More serious symptoms may involve the nerves. If the spinal curve worsens or narrows the spinal canal, it can press on the spinal cord or nerve roots. This may cause tingling, numbness, or weakness in the arms or legs. In rare but serious cases, such as congenital or trauma-related kyphosis, pressure on the spinal cord can affect coordination or cause bladder and bowel issues. Kyphosis can also affect breathing. Severe upper back curves may pull the ribcage forward and down, limiting lung expansion. This can lead to short, shallow breaths or breathing problems during activity. In extreme cases, especially congenital kyphosis, respiratory failure can occur. Kyphosis Symptoms in Children and Emotional Impact Children with kyphosis may show signs like stiffness in the back, clumsiness, or avoiding physical play due to pain or self-consciousness. For teenagers, mental and emotional symptoms are important to watch. Those with visible spinal curves may be bullied or feel isolated. This can lead to anxiety, low self-esteem, or depression. Support from family, teachers, and mental health professionals is key in these situations. Sometimes, the symptoms of kyphosis develop slowly and are easy to overlook. This is often the case with postural kyphosis. People may think it’s just poor posture rather than a medical problem. That’s why regular check-ups—especially for teens and older adults—are important for spotting the curve early and stopping it from getting worse. The Importance of Proper Diagnosis Many symptoms of kyphosis overlap with other spine conditions like scoliosis, lordosis, or vertebral fractures. A proper physical exam and imaging tests are needed to make the correct diagnosis. Once kyphosis is diagnosed, tracking changes in symptoms over time helps show if it’s staying the same or getting worse. In conclusion, the symptoms of kyphosis range from posture changes to major physical and emotional challenges. Spotting symptoms early and treating the whole person—both physically and emotionally—can lead to better outcomes. Whether symptoms are mild or severe, early diagnosis and care make a big difference in quality of life for people living with kyphosis. [Next: Diagnosis of Kyphosis →]

Symptoms of Kyphosis Read More »

Diagnosis of Kyphosis

Diagnosis of Kyphosis

A thorough and timely diagnosis of kyphosis is essential in determining the severity of spinal curvature and identifying any underlying causes or complications. The diagnosis of kyphosis usually starts with a detailed medical history and physical exam, followed by imaging and functional tests. Accurate diagnosis helps distinguish between types—postural, congenital, Scheuermann’s, or degenerative—and guides treatment and monitoring. Doctors begin by asking about symptoms, family history, and related problems such as back pain, tiredness, or breathing trouble. Parents may notice changes in posture or height in children and teens. Knowing when symptoms began and if they are worsening helps decide if kyphosis is flexible (postural) or fixed (structural). Physical Exam and Imaging in Diagnosis of Kyphosis During the physical exam, the doctor observes the spine’s curve while the patient stands, bends forward, or lies down. In postural kyphosis, the curve often disappears when lying flat or standing straight. In structural kyphosis like Scheuermann’s or congenital types, the curve stays visible and does not correct with posture changes. The doctor also checks for uneven shoulder height, a prominent upper back, or an exaggerated spine curve. To confirm the diagnosis of kyphosis, imaging tests are needed. A side-view X-ray is the first step. It measures the Cobb angle, which shows the degree of curvature. A Cobb angle over 40 degrees usually means kyphosis. In teens, a sharp curve with wedge-shaped vertebrae may indicate Scheuermann’s disease, while a smooth curve suggests postural causes. Advanced imaging, such as MRI, may be done if doctors worry about spinal cord or nerve issues. MRI offers detailed pictures of the spinal cord, discs, and muscles, helping rule out tumors, cysts, or infections. CT scans are less common but useful for assessing congenital kyphosis or trauma-related problems. Neurological and Bone Health Evaluation Neurological exams are important if patients report numbness, tingling, or weakness. Reflexes, sensation, and muscle strength tests check for nerve or spinal cord compression. If signs of nerve damage appear, urgent imaging and referral to a spine specialist may follow. In older adults with osteoporosis or fractures, bone density tests like DEXA scans help assess fracture risk. Early detection of bone loss can guide treatment to prevent worsening kyphosis and new fractures. Pulmonary function tests may also be needed. Severe thoracic kyphosis can limit lung expansion. Spirometry or full lung function tests evaluate breathing capacity, especially in patients with shortness of breath or fatigue. Special Cases and Monitoring For children with suspected congenital kyphosis, early diagnosis is critical. These cases often progress fast and may need surgery to avoid deformity or nerve damage. Pediatric orthopaedic specialists manage diagnosis using X-rays, MRIs, and clinical checks. After confirming kyphosis, classifying the type guides treatment. Postural kyphosis tends to be mild and reversible with exercise and posture correction. Scheuermann’s kyphosis is rigid and may require bracing or surgery. Degenerative kyphosis relates to aging spine changes and needs therapy, pain relief, and bone health support. Proper classification ensures treatment matches the patient’s age, symptoms, and needs. Monitoring is key. Even after diagnosis, patients—especially growing kids—need regular follow-ups. X-rays every 6 to 12 months track changes. Adults with symptoms also require imaging to assess progression or complications. It is vital to distinguish kyphosis from other spine conditions like scoliosis (sideways curve) or lordosis (inward curve). Sometimes patients have kyphoscoliosis, combining curves. Accurate diagnosis avoids wrong treatment and unnecessary discomfort, stressing the need for specialist care in complex cases. Summary of Diagnosis of Kyphosis In summary, the diagnosis of kyphosis involves a stepwise approach with clinical exams, imaging, and functional tests. Whether postural or structural, early and accurate diagnosis allows timely treatment, prevents complications, and supports long-term spine health. Modern tools and awareness give patients a better chance at maintaining quality of life through early care and ongoing management. [Next: Treatment of Kyphosis →]

Diagnosis of Kyphosis Read More »

Treatment of Kyphosis

The treatment of kyphosis is highly dependent on the cause, degree of spinal curve, patient’s age, and whether pain or functional problems occur. Early treatment can greatly improve posture, reduce discomfort, and stop progression. This is especially true in teens during growth spurts and older adults with degenerative kyphosis. A range of treatments exist—from conservative to surgical—to manage this spinal condition. Conservative Treatment of Kyphosis Postural kyphosis, the most common and mildest form, usually starts with non-invasive care. Physical therapy focuses on strengthening the spinal extensor muscles, improving core stability, and increasing flexibility. Stretching the hamstrings, chest, and hip flexors helps correct muscle imbalances that worsen poor posture. Over time, a personalised exercise plan can reduce the curve and ease pain, particularly if started early. Postural education plays a key role too. Many patients, especially children and teens, don’t notice their poor posture habits. Physiotherapists teach proper sitting, standing, and moving techniques to keep the spine aligned. Simple changes—like adjusting desk or screen height—help prevent worsening and reduce discomfort. In rigid kyphosis forms such as Scheuermann’s disease, bracing may be necessary during adolescence. A thoracolumbosacral orthosis (TLSO) brace gently guides the spine toward a more natural curve. Patients usually wear the brace for many hours daily, sometimes up to 20 hours. Bracing works best before bones fully mature. Sticking to the schedule is vital, and doctors regularly check progress. While bracing won’t completely fix the curve, it can stop it from worsening and may avoid surgery. Pain Management and Lifestyle Changes Adults with degenerative kyphosis or Scheuermann’s disease often need pain relief. Over-the-counter medicines like paracetamol or NSAIDs help mild to moderate pain. Stronger drugs or steroid injections may ease nerve pain or inflammation, especially if nerve compression occurs. Lifestyle changes support treatment. Keeping a healthy weight lessens spinal pressure. Avoiding heavy lifting or high-impact sports prevents worsening. For elderly patients with osteoporosis-related kyphosis, getting enough calcium and vitamin D, plus medications like bisphosphonates, strengthens bones and lowers fracture risk. Fall prevention is critical since minor trauma can worsen spinal curves in these patients. Surgical Treatment of Kyphosis When conservative care fails or the curve passes 75 degrees, surgery may be needed. The most common operation is spinal fusion, which joins vertebrae using rods, screws, and bone grafts. The aim is to realign the spine, stabilise the curve, and relieve pressure on nerves or the spinal cord. Surgery suits patients with worsening deformity, severe pain, or neurological problems like weakness, numbness, or bladder issues. Before surgery, patients undergo thorough evaluations, including imaging and heart and lung tests. Recovery usually involves several hospital days and months of rehab. Risks include infection, bleeding, hardware problems, and damage to nearby spinal segments. Still, many patients see major improvements in posture, pain, and quality of life after surgery. Psychological and Follow-Up Care Kyphosis also affects mental health. Teens and young adults may suffer from low self-esteem due to their visible spine shape. Counselling or support groups can help them cope. Treating both body and mind leads to better outcomes, especially for younger people. Regular monitoring is key in the treatment of kyphosis. Whether conservative or surgical, doctors track the spinal curve and symptoms over time. Children and teens may need X-rays every six to twelve months, especially during growth spurts. Adults with pain or degeneration also require periodic scans and check-ups. Emerging Treatments and Special Cases New therapies include minimally invasive surgeries and biologics that help bone healing or fusion. These are still experimental but show promise. Also, posture-correcting devices and smart sensors are growing as tools to aid posture training. However, they do not replace medical care. Congenital kyphosis, where spinal defects exist from birth, needs early detection and often surgery in the first years of life. Specialist care by paediatric orthopaedic surgeons is vital to prevent neurological damage and manage curve progression. Summary of Treatment of Kyphosis In summary, the treatment of kyphosis depends on the individual’s age, symptoms, and spinal curve type. Many cases respond well to physiotherapy, bracing, and lifestyle changes. Others require surgery to restore function and avoid complications. Early diagnosis, education, and close follow-up form the foundation of effective care. A personalised treatment plan can improve posture, reduce pain, and enhance quality of life. [Next: Complications of Kyphosis →]

Treatment of Kyphosis Read More »

Complications of Kyphosis

Complications of Kyphosis

The complications of kyphosis can vary widely depending on the severity, type, age of onset, and whether the condition is treated early or allowed to progress. While some individuals experience only mild symptoms or cosmetic concerns, others face significant physical, psychological, and neurological issues. Understanding the complications of kyphosis is essential for early intervention, risk reduction, and long-term health management. One of the most immediate and noticeable complications is chronic back pain. The altered spinal alignment places extra stress on muscles, ligaments, and joints, causing persistent discomfort. This mechanical pain is especially common in adults with Scheuermann’s disease or degenerative kyphosis. Over time, continuous strain leads to muscle fatigue, spasms, and reduced mobility. These problems greatly impact daily activities and quality of life. Respiratory and Digestive Complications of Kyphosis Respiratory issues are another common complication. Severe kyphotic curves—especially those over 70 to 80 degrees—can compress the chest cavity. This compression limits lung expansion, causing shortness of breath, reduced exercise tolerance, and a higher chance of lung infections. Older adults with osteoporotic kyphosis may see worsening of pre-existing lung conditions like COPD, making their care more challenging. Digestive problems also arise when spinal curvature presses on the abdominal area. Pronounced kyphosis can push organs such as the stomach and intestines into unusual positions. This may cause acid reflux, feeling full quickly, and abdominal discomfort. Although less common than breathing issues, these gastrointestinal problems should not be overlooked or misdiagnosed. Neurological and Psychosocial Complications Neurological problems rank among the more serious complications of kyphosis. Extreme spinal curves can compress the spinal cord or nerve roots. This compression leads to tingling, numbness, weakness, or sharp pain in the arms or legs. In severe cases, kyphosis causes myelopathy—spinal cord compression that can result in poor coordination, trouble walking, or bladder and bowel issues. Early diagnosis and surgery often prevent permanent nerve damage. The psychosocial impact of kyphosis is frequently underestimated. Visible spinal curves can cause embarrassment, low self-esteem, and social withdrawal, especially in teenagers and young adults. Bullying and self-consciousness in social settings raise the risk of anxiety and depression. Adults may also struggle with body image and confidence, which affect relationships and emotional health. Functional Limitations and Fracture Risks Functional limitations are a major concern. As kyphosis worsens, standing for long periods, walking far, or lifting objects becomes difficult. In elderly patients, reduced mobility contributes to frailty, increased fall risk, and dependence on assistive devices or caregivers. These challenges reduce independence and lower quality of life. In older adults, kyphosis often links to a higher risk of vertebral fractures, especially when caused by osteoporosis. Vertebral wedging weakens the spine, making it prone to collapse even after minor injuries. Each fracture worsens the curvature, creating a vicious cycle of instability and complications. This risk is especially high in postmenopausal women and men with undiagnosed low bone density. Cardiovascular Effects and Progression In rare cases, kyphosis affects cardiovascular function. Severe thoracic spine curvature can restrict space for the heart, reducing its efficiency. This may worsen conditions like congestive heart failure, particularly in patients with existing heart problems. While not common, this complication matters in those with combined heart and lung disease. Kyphosis can also progress over time if untreated. Mild spinal curves often worsen during childhood or teenage growth spurts. In adults, degenerative disc disease, arthritis, and osteoporosis speed up curvature. A progressing deformity raises the risk of complications and reduces the success of treatments like bracing or physical therapy. Ultimately, surgery may become necessary. Psychological and Post-Surgical Considerations Living with a chronic spinal condition takes a psychological toll. Health anxiety, frustration with physical limits, and fear of worsening disability cause emotional distress for many. Counselling, therapy, or support groups often help build coping skills and improve mental health. Post-surgical complications should be acknowledged. Spinal fusion surgery can correct curvature and ease symptoms but carries risks like infection, bleeding, hardware failure, and damage to nearby spinal segments. Recovery is usually long, with months of rehabilitation, making surgery a major decision. Congenital Kyphosis and Economic Burden Children with congenital kyphosis—spinal defects present at birth—face early and serious complications. Rapid curve progression, neurological issues, and multiple surgeries are common. Close care from paediatric orthopaedic specialists is vital to reduce future problems. Finally, kyphosis carries a heavy economic burden. Ongoing treatments, lost income due to disability, and costs for mobility aids or home changes strain individuals and families. Insurance limits and poor access to specialists make managing kyphosis harder, especially in low-resource areas. Summary of Complications of Kyphosis In summary, the complications of kyphosis affect nearly every part of life—physical, emotional, and social. From chronic pain and lung problems to mental health issues and mobility loss, untreated or severe kyphosis has far-reaching consequences. Recognising these complications highlights why early diagnosis, regular monitoring, and personalised care are vital to reduce long-term effects and improve overall quality of life. [Next: Back to Overview →]

Complications of Kyphosis Read More »

Overview of Krabbe Disease

Overview of Krabbe Disease

Overview of Krabbe disease is crucial for raising awareness about this rare but severe neurological disorder. Krabbe disease, also called globoid cell leukodystrophy, is a genetic condition affecting the central and peripheral nervous systems. A deficiency of the enzyme galactocerebrosidase (GALC) causes the disease. This deficiency leads to harmful substances building up in the brain and spinal cord. The result is progressive damage to the myelin sheath that protects nerve cells. Understanding the overview of Krabbe disease helps with recognising early signs, getting timely diagnosis, and exploring treatments, especially where newborn screening is not common. Krabbe disease belongs to leukodystrophies—a group of disorders with abnormal development or destruction of brain white matter (myelin). The disease usually appears in infancy, often within the first six months. However, rarer late-onset forms can show up in adolescence or adulthood. In the most common infantile form, the disease progresses fast. Affected babies lose motor skills, become extremely irritable, and have feeding problems. This infantile form is the most aggressive, with life expectancy often limited to a few years if untreated. Genetics and Pathophysiology Krabbe disease follows an autosomal recessive inheritance pattern. This means a child must inherit two faulty copies of the GALC gene—one from each parent—to develop the disease. Carriers with one defective copy usually show no symptoms but can pass the gene to children. The disease affects about 1 in 100,000 live births worldwide, but rates vary by region and group. For example, some communities in Israel and people of Scandinavian descent have higher rates due to genetic clustering. From a biological viewpoint, Krabbe disease occurs because the body cannot produce enough GALC enzyme. This enzyme breaks down fatty substances called galactolipids. When these fats, especially psychosine, build up, they become toxic to oligodendrocytes—the cells that form myelin. Widespread myelin loss disrupts nerve function throughout the body. This damage slows or blocks electrical signals in the nervous system, causing the severe neurological decline seen in Krabbe disease. Symptoms and Clinical Course The overview of Krabbe disease is incomplete without symptoms and progression. In infants, early signs include excessive crying, muscle stiffness or low muscle tone (hypotonia), irritability, and sensitivity to touch. Symptoms worsen over time, leading to seizures, blindness, deafness, and eventually a vegetative state. In contrast, late-onset forms progress slowly and may cause muscle weakness, ataxia (poor coordination), and cognitive decline. While infantile Krabbe disease is usually fatal in early childhood, those with later-onset forms can live into adolescence or adulthood with serious disability. Early diagnosis is critical given the disease’s severity and rapid infant progression. Where newborn screening tests GALC enzyme activity, Krabbe disease can sometimes be found before symptoms start. Early diagnosis allows treatments like haematopoietic stem cell transplantation (HSCT) before irreversible brain damage. Unfortunately, in countries without screening, diagnosis often comes too late for effective treatment, highlighting the need for global awareness. Current Treatments and Support The overview of Krabbe disease also includes treatment options. No cure exists yet, but HSCT shows promise when done before symptoms appear. This transplant introduces healthy donor cells to produce GALC enzyme and preserve neurological function. However, HSCT carries risks and only benefits patients treated very early. For symptomatic individuals, treatment focuses on palliative care—managing pain, nutrition, seizures, and breathing support to improve quality of life. Research continues on new therapies like gene therapy and enzyme replacement. These aim to fix the genetic defect or deliver GALC enzymes directly to the nervous system. Though still experimental, these advances offer hope for future treatments. The disease also places an emotional and social burden on families. Caring for a child with progressive neurological decline demands much energy and resources. Families often need medical, psychological, and financial support. Support groups, genetic counselling, and specialised care help families cope with the challenges. Summary of Overview of Krabbe Disease In conclusion, the overview of Krabbe disease shows a complex and tragic illness marked by rapid neurological decline due to GALC enzyme deficiency. Early diagnosis, especially through newborn screening, remains the most crucial factor in improving outcomes. Early interventions like stem cell transplantation can help. As medical science advances, hope grows for better therapies. Meanwhile, raising awareness and expanding access to screening and support are vital to improving life for those affected by Krabbe disease. [Next: Causes of Krabbe Disease →]

Overview of Krabbe Disease Read More »

Scroll to Top