Mental Matters

Author name: admin

Doctor holding a liver model and medication bottle to explain treatment of jaundice in newborns

Treatment of Jaundice in Newborns

Jaundice in newborns is typically a benign and self-limiting condition; however, timely and appropriate treatment is essential to prevent complications such as acute bilirubin encephalopathy or kernicterus. The main goal of treatment is to lower high bilirubin levels before they become harmful to the brain. Most babies with jaundice in newborns only need close monitoring and general care. But in more serious cases, doctors need to take medical action. This section explains the treatment options for jaundice in newborns. It covers when to start therapy, which methods are used, and how plans may differ based on the cause and severity. A clear and organised approach helps protect newborns, especially those who have other health problems. Determining the Need for Treatment Before starting any treatment, doctors check if it’s needed by doing the following: Doctors start treatment if bilirubin levels go near or above the limits. These limits are lower for babies who are sick or born early because their bodies are more sensitive to bilirubin. Phototherapy in Jaundice in Newborns Phototherapy is the most common and effective way to treat jaundice in newborns. This treatment shines blue light on the baby’s skin. The light changes bilirubin into a form that leaves the body in urine and stool, even without help from the liver. Types of Phototherapy Phototherapy is safe and does not hurt. But babies under phototherapy must be checked often: Exchange Transfusion for Severe Jaundice In very rare and serious cases of jaundice in newborns, if phototherapy fails or bilirubin is dangerously high, doctors may perform an exchange transfusion. This involves slowly removing the baby’s blood and replacing it with donated blood to: Exchange transfusion is risky and needs skilled care in an intensive unit. Doctors choose this only when: Even though the procedure has risks (such as infection or bleeding), it can save lives when used correctly. Using IVIG in Jaundice in Newborns If a baby has jaundice from immune problems like Rh or ABO mismatch, IVIG may be given through a vein. IVIG works by: When given early, IVIG helps lower bilirubin well. Doctors often use it along with phototherapy. Feeding Support for Jaundice in Newborns Good feeding plays a key role in treating jaundice in newborns, especially in less severe cases. Hydration helps bilirubin leave the body in pee and poop. Feeding also triggers more bowel movements, which clears bilirubin from the gut. Tips for Breastfed Babies Tips for Formula-fed Babies If breastfeeding is the cause, better milk flow and feeding techniques usually fix the problem. In breast milk jaundice (caused by things in the milk that slow bilirubin breakdown), the issue may last longer but rarely needs stopping breastfeeding. Treating the Cause of Jaundice in Newborns If a specific illness causes jaundice in newborns, treating that illness is key: Detailed testing helps find the cause and shape treatment beyond just managing symptoms, especially when a type called conjugated jaundice is suspected. Monitoring After Treatment After going home, babies treated for jaundice in newborns need regular checks to make sure: If jaundice lasts longer than two weeks in full-term babies, doctors will check for more serious problems. Follow-ups include: Parental Support and Home Care Teaching parents is a big part of care for jaundice. Parents should: Parents also need to know when to seek help. Signs like deep sleepiness, high-pitched crying, poor feeding, or stiff/floppy limbs may mean the baby is in danger from bilirubin. In some places, babies can get phototherapy at home with doctor supervision. This option helps in mild cases and avoids hospital stays. Conclusion: Jaundice in Newborns The treatment of jaundice in newborns ranges from simple blue-light therapy to more serious steps like blood exchange or IVIG. The key to good care is spotting the problem early, acting quickly, and keeping track of the baby’s progress. When health workers follow proper treatment plans and parents understand how to help, most babies recover well from jaundice in newborns. A complete and careful approach gives every baby the best chance at a healthy start. [Next: Complications of Jaundice in Newborns →]
Treatment of Jaundice in Newborns Read More »

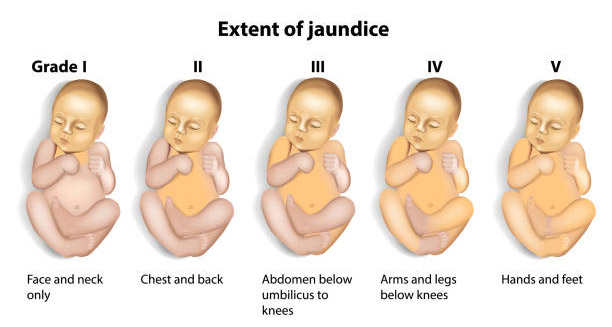
Illustration showing the extent of jaundice in newborns from Grade I to Grade V based on body coverage

Complications of Jaundice in Newborns

While many cases of jaundice in newborns are mild and resolve without lasting effects, it is crucial to recognise that serious complications can occur when the condition is severe, prolonged, or left untreated. Elevated bilirubin levels, especially when not monitored or managed appropriately, can have toxic effects on an infant’s developing brain and body. These complications range from reversible concerns such as feeding difficulties to permanent neurological impairments like kernicterus. Understanding the potential complications of jaundice in newborns helps to underscore the importance of timely diagnosis, vigilant monitoring, and appropriate treatment. This section explores the range of complications, from common short-term issues to rare but serious long-term outcomes. Acute Bilirubin Encephalopathy (ABE) One of the most serious complications of jaundice in newborns is acute bilirubin encephalopathy. This condition happens when too much unconjugated bilirubin enters the brain, especially in areas like the basal ganglia and brainstem. Signs and Symptoms of ABE include: These symptoms may start mildly and grow worse without treatment. Quick recognition and urgent care can prevent long-term harm. Kernicterus and Lasting Brain Damage If acute bilirubin encephalopathy is not treated, it can lead to kernicterus. This condition causes permanent brain damage from bilirubin deposits in brain tissue. Although rare in modern hospitals, it still occurs in areas with limited resources. Neurological Effects of Kernicterus include: Kernicterus is lifelong. Affected children often need therapy, special education, and long-term care. Preventing kernicterus by treating jaundice early is the best approach. Feeding Problems and Dehydration In moderate jaundice, babies may feed poorly. Sleepy infants may not latch or suck well. Low fluid intake slows bilirubin removal, which worsens jaundice. Effects of Poor Feeding: Teaching parents how to spot dehydration—such as fewer wet nappies or dry mouths—can help prevent these issues. Anaemia as a Complication Certain causes of jaundice in newborns—like Rh or ABO incompatibility—can break down red blood cells quickly, leading to anaemia. This reduces oxygen delivery to tissues. Signs of Anaemia may include: In serious cases, doctors may need to give blood transfusions. Anaemia can also make recovery longer and raise other health risks. Prolonged Neonatal Jaundice If jaundice lasts more than two weeks in full-term babies (or three in preemies), it is called prolonged neonatal jaundice. Though often harmless, it may also point to other conditions. Possible Underlying Issues: If jaundice lasts long or shows warning signs (pale stools, dark urine, or poor growth), doctors must investigate quickly. For example, early surgery in biliary atresia improves outcomes. Long-Term Developmental Delays Untreated or severe jaundice may affect a baby’s physical and brain development. These problems may appear months or even years later. Common Delays Linked to Jaundice: Not all delays come from jaundice, but high bilirubin levels increase the risk. Babies with severe jaundice should get regular developmental checks in early life. Hearing Loss From High Bilirubin Another possible complication of jaundice in newborns is sensorineural hearing loss. Even moderate bilirubin levels, if untreated, can damage the hearing nerve or inner ear. What to Do: Early hearing aids or implants can help speech and learning. Hearing checks are a crucial step in jaundice follow-up. Emotional Stress on Parents While not a medical effect, parental stress is a real and serious side effect of jaundice in newborns. Watching a yellow baby, hospital trips, and unfamiliar treatments can cause major anxiety. Ways to Support Parents: Involving parents in care and keeping them informed helps reduce fear and improves trust in medical advice. Conclusion The complications of jaundice in newborns can range from mild feeding troubles to serious and lifelong brain damage. Problems like kernicterus, anaemia, and developmental delays highlight why fast diagnosis and good care are so important. Most cases of newborn jaundice get better with basic care like phototherapy. Still, healthcare workers must act early, monitor closely, and educate parents well. With these steps, babies with jaundice can recover fully and thrive in the years ahead. [Next: Back to Overview →]

Complications of Jaundice in Newborns Read More »

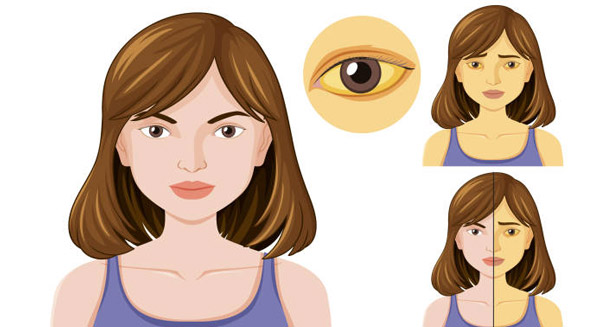
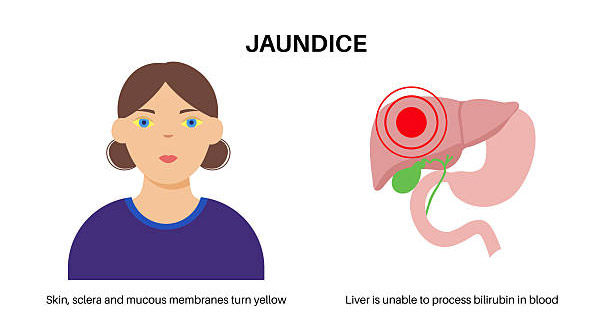
Illustration of a woman with yellow eyes and a diagram of the liver showing jaundice due to bilirubin buildup

Overview of Jaundice

Jaundice refers to a clinical condition in which the skin, the whites of the eyes, and sometimes mucous membranes develop a yellowish discolouration. This yellowing happens because bilirubin, a yellow-orange pigment formed during red blood cell breakdown, builds up in the body. Jaundice is not a disease itself but a visible symptom of an underlying problem, usually involving the liver, gallbladder, or pancreas. Recognising jaundice is important because it often signals serious internal issues needing medical attention. Bilirubin travels through the blood to the liver, where it is processed and then sent to the digestive tract via bile. Any disruption along this path—from red blood cell breakdown to bile excretion—can cause bilirubin to build up. Causes range from mild issues like dehydration or certain medicines to serious illnesses such as liver cirrhosis, hepatitis, or bile duct blockage. Newborns may also get jaundice because their livers are immature, which usually clears with time or light therapy. What Happens in the Body During Jaundice? Understanding jaundice means knowing the bilirubin cycle. Red blood cells live about 120 days. When they break down in the spleen and bone marrow, they produce unconjugated bilirubin, which does not dissolve in water. This bilirubin binds to albumin and moves to the liver. In the liver, it converts to conjugated bilirubin, which dissolves in water and flows into bile ducts. It then passes into the intestines to be excreted in stool. Any problem in this sequence—too much red blood cell breakdown, liver damage, or bile duct blockage—raises bilirubin levels in the blood. The extra bilirubin causes the skin and eye whites to turn yellow. The urine may become dark brown because the kidneys remove excess bilirubin. Stools may look pale or clay-coloured if bile flow to the intestines is reduced or blocked. Types of Jaundice Doctors classify jaundice into three main types, each with different causes and treatments: Knowing the type helps guide tests and treatments. Who Is at Risk? Jaundice can affect anyone but is more common in some groups: Older adults also face higher risk due to aging liver function and a greater chance of cancers blocking bile flow. Common Symptoms and Clinical Presentation Besides yellowing skin and eyes, jaundice may cause: Sometimes, jaundice is the only sign in mild liver problems or haemolytic anaemia. Diagnosis and Medical Evaluation Doctors diagnose jaundice by examining the skin, eyes, and mucous membranes. Blood tests measure total bilirubin and separate it into unconjugated and conjugated types. Liver function tests like ALT, AST, ALP, and GGT help locate the problem. Imaging tests such as ultrasound, CT, or MRI assess the liver and bile ducts. In difficult cases, liver biopsy or endoscopic retrograde cholangiopancreatography (ERCP) may be needed to find the exact cause. Importance of Prompt Medical Attention Ignoring jaundice can cause serious harm. Untreated bile duct blockage can lead to infections, sepsis, or permanent liver damage. Chronic liver diseases may remain hidden until jaundice appears, signaling advanced illness. Quick diagnosis and treatment prevent long-term health problems. Treatment Depends on the Underlying Cause Treatment focuses on the cause, not jaundice itself. For example: Prognosis and Outlook The outlook depends on cause, severity, and how fast treatment starts. Neonatal jaundice usually clears quickly with little treatment. Liver failure or cancer-related jaundice can have a poor prognosis. Early detection, lifestyle changes (like reducing alcohol), and following treatment improve chances of recovery. Preventive Strategies To reduce jaundice risk: Public health efforts and early screening also help control jaundice in high-risk areas. Conclusion Overview of jaundice shows it is a symptom with many causes—from mild to life-threatening. Yellow skin and eyes may seem minor but often warn of serious problems. Quick medical evaluation, accurate diagnosis, and treatment focused on the cause are key to better outcomes and preventing complications. Understanding jaundice helps patients and doctors act quickly to manage this important sign and improve health for all ages. [Next: Causes of Jaundice →]

Overview of Jaundice Read More »

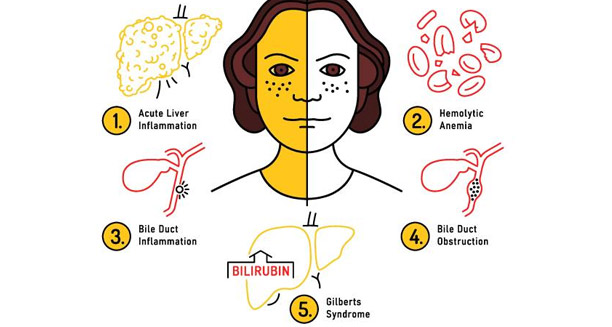
Infographic showing various medical causes of jaundice including liver inflammation, anaemia, and bile duct issues

Causes of Jaundice

Jaundice develops when there is an imbalance in the body’s ability to process and eliminate bilirubin, the yellow pigment formed during the normal breakdown of red blood cells. This imbalance causes bilirubin to build up in the blood. As a result, the skin and eyes turn yellow. Jaundice can come from many different causes, from harmless to very serious. Knowing these causes helps with quick diagnosis and proper treatment. Doctors group the causes of jaundice into three main types: pre-hepatic (before the liver), hepatic (inside the liver), and post-hepatic (after the liver). Each type shows a different way bilirubin builds up in the body. 1. Pre-Hepatic Causes (Before the Liver) Pre-hepatic jaundice happens when the body breaks down red blood cells too fast. This floods the liver with unconjugated bilirubin. The liver cannot handle it all, so bilirubin rises in the blood. a. Haemolytic AnaemiasSome inherited or acquired diseases increase red blood cell breakdown and cause jaundice. These include: b. InfectionsSome infections, such as malaria, sepsis, or typhoid fever, destroy red blood cells quickly. Malaria is a common cause in certain areas. c. Blood Transfusion ReactionsIf blood is given that does not match, the immune system attacks red cells, causing rapid breakdown and jaundice. d. Autoimmune Haemolytic AnaemiaHere, the immune system mistakenly destroys red blood cells early. Pre-hepatic jaundice mostly raises unconjugated bilirubin. It usually does not cause dark urine because bilirubin has not passed through the liver yet. 2. Hepatic Causes (Within the Liver) Hepatic jaundice happens when the liver itself cannot process or get rid of bilirubin. The liver may be inflamed, damaged, or not working well. This stops it from changing unconjugated bilirubin to conjugated bilirubin or from moving bilirubin into bile ducts. a. HepatitisViral hepatitis (A, B, C, D, or E) is a common cause worldwide. Liver cells get inflamed and stop working well. Hepatitis may be sudden or long-lasting. Patients often feel tired, have belly pain, and raised liver enzymes. b. Alcoholic Liver DiseaseDrinking too much alcohol over time damages the liver. This leads to fatty liver, hepatitis, or cirrhosis. All these can cause jaundice. c. Non-Alcoholic Fatty Liver Disease (NAFLD)This condition is linked to obesity, diabetes, and high cholesterol. If it gets worse, it may cause inflammation (NASH) and cirrhosis, leading to jaundice. d. Drug-Induced Liver InjurySome medicines and herbal products harm the liver. Common examples are: e. Liver Cancer and MetastasesPrimary liver cancer or cancer spreading from other organs (like colon or breast) can harm liver function and cause jaundice. f. Inherited Liver DisordersSome genetic diseases affect bilirubin metabolism, such as: These usually show in childhood or adolescence. In hepatic jaundice, both conjugated and unconjugated bilirubin can be high. Urine may darken due to conjugated bilirubin in the blood. 3. Post-Hepatic Causes (After the Liver) Post-hepatic or obstructive jaundice happens when bile flow from the liver to the intestines is blocked. This causes conjugated bilirubin to back up into the blood. a. GallstonesGallstones often block the bile duct. When a stone gets stuck, bile cannot leave the liver. This leads to jaundice, dark urine, pale stools, and sometimes fever or pain called biliary colic. b. Pancreatic CancerCancer in the pancreas, especially near the bile duct, can press on the duct and cause jaundice. This jaundice usually develops slowly. Weight loss and itching often come with it. c. CholangiocarcinomaThis cancer starts in the bile ducts themselves. It can block bile flow and cause symptoms like other obstructive causes. d. Benign Biliary StricturesNon-cancerous narrowing of bile ducts may follow surgery, pancreatitis, or injury. e. Primary Sclerosing Cholangitis (PSC)This autoimmune disease causes ongoing inflammation and scarring of bile ducts. PSC often occurs with ulcerative colitis and raises the risk of bile duct cancer. Post-hepatic causes raise conjugated bilirubin. They cause dark urine, pale stools, and itching all over the body. 4. Neonatal Jaundice Jaundice in newborns is common and mostly harmless. It happens because the liver is immature and cannot process bilirubin well. Most cases get better within two weeks, but some need treatment. a. Physiological JaundiceSeen in up to 60% of newborns, this peaks around days 3–5 and usually clears on its own. b. Breastfeeding JaundiceIf a baby drinks little milk, dehydration can increase bilirubin levels. c. Breast Milk JaundiceCertain breast milk components may slow bilirubin breakdown but usually cause no harm. d. Haemolytic Disease of the NewbornThis happens when mother’s antibodies attack the baby’s red cells, often due to Rh incompatibility. It is serious and may require blood exchange or light therapy. 5. Other Rare Causes Some less common causes can also lead to jaundice: These causes are rare but should be checked for in certain areas or unusual cases. Conclusion The causes of jaundice cover a wide range, from mild and temporary to severe and deadly. Knowing if jaundice is pre-hepatic, hepatic, or post-hepatic helps with diagnosis and treatment plans. Quick tests like blood work, scans, and sometimes biopsy can find the cause and stop problems like liver failure or infection. Treating jaundice means fixing the cause: slowing red cell breakdown, helping the liver, or clearing bile duct blocks. Vaccination, clean water, and early checks help reduce jaundice in places where it happens often. [Next: Symptoms of Jaundice →]

Causes of Jaundice Read More »

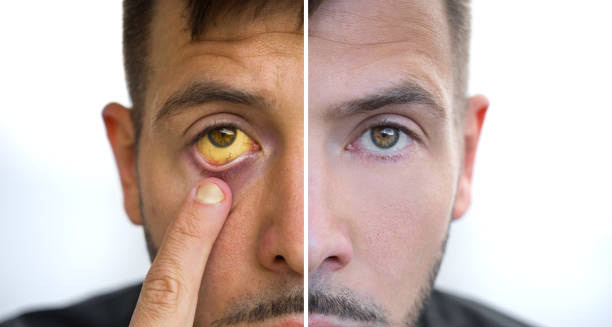
Split image showing one side of a man with yellow eyes and the other side with normal eyes, indicating symptoms of jaundice

Symptoms of Jaundice

Jaundice presents primarily as a yellowish discolouration of the skin, the sclera (whites of the eyes), and mucous membranes due to the accumulation of bilirubin in the bloodstream. Although this yellowing is the most recognisable sign, jaundice often occurs with a range of other symptoms depending on its underlying cause. These other symptoms give important clues and help doctors tell the types of jaundice apart—pre-hepatic, hepatic, or post-hepatic. They also show how serious the condition is and how quickly it needs treatment. Jaundice does not happen by itself. Usually, it shows the liver, bile ducts, or blood cells are not working properly. That is why the symptoms that come with jaundice are very important. Knowing them helps doctors spot jaundice early. It also guides the right treatment and can save lives. Visible Yellowing of the Skin and Eyes The most clear and common symptom of jaundice is yellowing of the skin and the whites of the eyes. This yellow colour shows up best in natural light. It usually starts on the face and upper body and then moves down. The yellow can be very light or dark orange-yellow, depending on how much bilirubin builds up and how long it stays high. In newborns, the yellowing often starts at the head and spreads to the chest, belly, and limbs. Doctors use this pattern along with bilirubin tests to decide if treatment is needed. In adults, the eyes often show yellowing first because the whites have no pigment. This makes the yellow colour easy to see. Dark-Coloured Urine One key symptom of conjugated jaundice—common in liver or bile duct problems—is dark urine. Patients describe it as tea-coloured, cola-coloured, or brownish. This happens because conjugated bilirubin dissolves in water and passes into urine when its blood levels rise. Dark urine often shows before the skin turns yellow. Some people may not notice it if they do not check their urine often. Still, doctors always ask about urine colour during exams. Pale or Clay-Coloured Stools Bile pigments give poop its normal brown colour. In obstructive jaundice, bile cannot reach the intestines because of blockages. As a result, stools turn pale, grey, or clay-coloured. This change is a strong sign of post-hepatic jaundice caused by gallstones, bile duct narrowing, or tumours. Sometimes stools also become greasy or smell bad. This happens if fat absorption drops because bile is missing in the gut. Generalised Itching (Pruritus) Itching, called pruritus, is a common and troubling symptom, especially in jaundice with blocked bile flow. Bile salts build up in the skin and cause intense itching. It often gets worse at night. Itching can affect any part of the body but is usually all over and very strong. This leads to scratching, skin damage, and even infections. People with long-term liver disease or bile duct blockage say itching is one of the worst symptoms. It often does not get better with antihistamines, making it harder to treat. Fatigue and Weakness Fatigue is a common symptom in jaundice, especially when caused by liver problems like hepatitis, cirrhosis, or autoimmune disease. The liver is key for energy and clearing toxins. When it gets hurt, energy drops. Patients often feel very tired, unmotivated, and mentally foggy. This can seriously affect daily life and might be blamed on other causes if jaundice is mild or new. Abdominal Pain or Discomfort Pain or discomfort in the belly often comes with jaundice, depending on the cause. In pre-hepatic jaundice caused by red blood cell breakdown, pain may be slight or missing.In hepatitis, people feel dull pain or discomfort in the right upper belly where the liver sits.In obstructive jaundice, sudden, sharp pain may mean gallstones. Slow, worsening pain could mean a tumour pressing on bile ducts. Belly swelling, fullness, or tenderness when touched can also happen with liver or bile duct problems. Nausea and Vomiting Nausea, poor appetite, and vomiting often occur with jaundice from liver illness. These symptoms show the liver’s role in digestion and detox. People with sudden hepatitis may feel sick and avoid fatty foods. Those with liver cirrhosis might have ongoing nausea that feels like indigestion. Fever and Chills Fever with jaundice usually means infection. One dangerous illness is ascending cholangitis, a bile duct infection often caused by gallstones blocking bile flow. Classic signs are: Other infections causing fever and jaundice include viral hepatitis, malaria, and leptospirosis. Chills and shaking support infection as the cause and need urgent care. Weight Loss and Anorexia Unplanned weight loss with jaundice may point to cancer. Pancreatic cancer, bile duct cancer, and liver cancer are common causes. Older adults or people who smoke, drink heavily, or have liver disease should be checked closely. Loss of appetite often comes before weight loss. It may happen because of belly discomfort, nausea, or liver problems. Confusion or Mental Changes (Hepatic Encephalopathy) In late liver disease, jaundice can come with mental changes like confusion, forgetfulness, mood swings, and less alertness. This is called hepatic encephalopathy. It happens when toxins, like ammonia, build up because the damaged liver can’t remove them. This is a medical emergency. If untreated, it can lead to coma or death. It mostly occurs in chronic liver failure or sudden liver injury. Signs in Newborns Babies with jaundice mainly show yellow skin and eyes. But some signs warn of serious problems: These may mean kernicterus, a rare but serious brain injury caused by very high bilirubin. Conclusion The symptoms of jaundice range from small changes in skin colour to serious, life-threatening problems. Yellow skin and eyes remain the key signs. Other symptoms like dark urine, pale stools, itching, and belly pain guide doctors to the cause. Early spotting of these signs, especially when combined, helps start the right treatment fast. Whether jaundice comes from infection, metabolism, blockage, or cancer, checking symptoms is crucial. People who notice yellow skin or eyes with other signs should get medical help quickly. [Next: Treatment of Jaundice →]

Symptoms of Jaundice Read More »

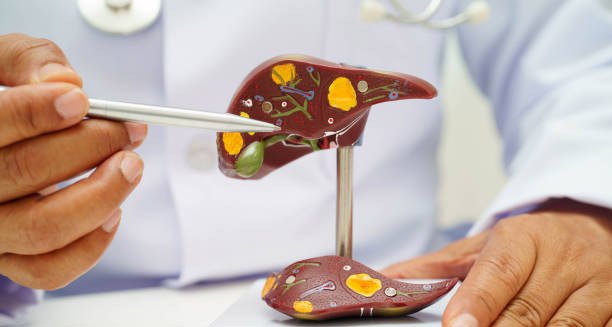
Doctor pointing at a liver model to explain the diagnosis of jaundice and bile flow issues

Diagnosis of Jaundice

Jaundice is a visible symptom that typically signals an underlying medical condition affecting the liver, bile ducts, or red blood cells. While the yellow discolouration of the skin and eyes may be easily observed, determining the cause of jaundice requires a structured diagnostic approach. Early and accurate diagnosis is vital in identifying potentially serious or life-threatening conditions such as bile duct obstruction, hepatitis, or liver cancer. Clinicians rely on a combination of medical history, physical examination, laboratory tests, and imaging studies to evaluate the origin and severity of jaundice. Understanding the mechanisms behind bilirubin metabolism is crucial to interpreting diagnostic results correctly. Bilirubin, the substance responsible for the yellowing seen in jaundice, is produced when red blood cells are broken down. It is processed in the liver and excreted through the bile ducts. A disruption at any point in this pathway may lead to bilirubin accumulation and, subsequently, jaundice. Initial Clinical Evaluation Medical History The first and most important step is a thorough medical history. Doctors ask about when the yellowing started and how long it has lasted. They check for recent travel, especially to places where hepatitis or malaria is common. They review all medicines used, including herbal remedies and over-the-counter drugs. Alcohol use is also important. Family history of liver or blood problems matters too. They ask about diet, lifestyle, and job risks, especially in healthcare, food handling, or chemical work. This information helps doctors guess the likely causes, such as viral hepatitis, alcohol damage, or blood disorders. Physical Examination Doctors perform a detailed physical exam to find clues. Yellowing of the whites of the eyes (scleral icterus) often appears before the skin changes. They feel the liver to check its size and firmness; a big, hard liver can mean cirrhosis or cancer. Tenderness in the right upper belly suggests inflammation or blockage. Signs like spider veins on the skin, red palms, and fluid in the belly point to long-term liver disease. An enlarged spleen may happen in blood disorders or portal hypertension. Laboratory Investigations Bilirubin Tests Blood tests measure total bilirubin, the overall level in the blood. Doctors check unconjugated (indirect) bilirubin, which rises in cases like haemolysis before the liver. They also measure conjugated (direct) bilirubin, which increases when the liver or bile ducts fail to remove bilirubin properly. Comparing these two types helps pinpoint the problem’s location. Liver Function Tests (LFTs) Doctors test enzymes like ALT and AST, which rise when liver cells get hurt, for example in hepatitis. ALP and GGT levels increase if bile flow is blocked. They also check albumin and clotting time (PT). Low albumin or long PT means the liver is not working well. Full Blood Count (FBC) A low haemoglobin with a high number of young red cells (reticulocytes) suggests red blood cells are breaking down. Raised white blood cells can mean infection or inflammation. Viral Hepatitis Panel Doctors test for hepatitis A, B, C, D, and E, especially if jaundice comes with tiredness, fever, or belly pain. Chronic hepatitis B and C raise the risk of cirrhosis and liver cancer. Autoimmune and Metabolic Markers Tests for anti-smooth muscle antibodies or anti-nuclear antibodies can suggest autoimmune hepatitis. Low ceruloplasmin points to Wilson’s disease. Iron tests check for haemochromatosis. Alpha-1 antitrypsin levels also help find rare causes. These tests help find treatable but uncommon liver problems. Urinalysis Urine tests are quick and useful. Dark urine with bilirubin confirms conjugated jaundice. Urobilinogen is often missing if bile flow is blocked but high if red cells break down too fast. This helps decide if the problem is in or after the liver. Stool Colour and Bile Pigments Patients may notice pale or clay-coloured stools when bile does not reach the intestines. Although this is a subjective sign, it points to obstructive jaundice and calls for more imaging tests. Imaging Techniques Ultrasound Scan Doctors usually start with an abdominal ultrasound. It is safe and easy to do. Ultrasound can spot gallstones, bile duct widening, liver lumps or cysts, and signs of cirrhosis. CT Scan (Computed Tomography) A CT scan gives detailed images of the body. It can find pancreatic cancer, bile duct tumours, and swollen lymph nodes. It helps plan surgery if needed. MRI and MRCP (Magnetic Resonance Cholangiopancreatography) MRI, especially MRCP, shows the bile ducts and pancreas clearly. Doctors use it when ultrasound results are unclear. Endoscopic Retrograde Cholangiopancreatography (ERCP) ERCP uses a flexible tube with a camera passed through the mouth to the bile ducts. It helps see blockages, remove stones, place stents, or take tissue samples. ERCP has risks and is used mainly when treatment is planned. Liver Biopsy If blood tests and scans do not show the cause, doctors may take a small piece of liver tissue. They look at it under a microscope to check inflammation, scarring, tumours, or storage diseases like Wilson’s or haemochromatosis. This test helps with unclear liver problems or chronic disease. Specialised Tests in Neonates Newborns with jaundice need specific tests like transcutaneous bilirubin measurements and blood bilirubin levels. A Coombs test checks for red cell breakdown. Blood typing of mother and baby helps find incompatibility. Early detection is key to prevent brain damage called kernicterus. Conclusion Diagnosing jaundice needs a careful mix of exam, lab tests, and imaging. By figuring out if the problem is before, in, or after the liver, doctors can find the cause and start treatment fast. Each step—from noticing yellow skin to biopsies—plays a key role. Quick diagnosis improves results and avoids problems like liver failure, infection, or brain damage in babies. Patients with jaundice must get thorough checks, especially if they have fever, confusion, or rapid weight loss. [Next: Treatment of Jaundice →]

Diagnosis of Jaundice Read More »

Stethoscope on wooden background with colourful letters spelling ‘Jaundice’

Treatment of Jaundice

Jaundice is not a disease in itself but a symptom that arises due to underlying conditions affecting the metabolism or excretion of bilirubin. As such, the treatment of jaundice focuses on identifying and managing the root cause while also addressing any complications that may arise. Because jaundice may be caused by conditions ranging from benign viral infections to life-threatening malignancies, a tailored treatment approach is crucial. In most cases, this involves a combination of medical, surgical, and supportive therapies. Importantly, the specific intervention chosen depends on whether the jaundice is pre-hepatic, hepatic, or post-hepatic, a distinction based on the site of disruption in bilirubin metabolism. Thus, the management of jaundice varies significantly across clinical presentations and is best guided by diagnostic investigations and clinical assessment. General Supportive Measures No matter the cause, certain basic steps can ease symptoms and help patients feel better. First, keeping well hydrated supports liver work and helps flush out toxins. Next, a balanced diet rich in antioxidants and low in saturated fats can ease liver stress. For patients with chronic liver disease, doctors may recommend special diets, such as low-protein meals for those with hepatic encephalopathy. Avoiding alcohol is vital because it can harm liver cells and worsen jaundice. Also, stopping medicines that can hurt the liver, like high doses of paracetamol, some antibiotics, and statins, can prevent further damage. These basic steps build a foundation while doctors treat the underlying cause more specifically. Treatment of Pre-Hepatic Jaundice Pre-hepatic jaundice happens when the body destroys red blood cells too fast, making the liver unable to keep up with processing bilirubin. Management of Haemolysis First, doctors find and remove the cause, which might be certain drugs, infections, or immune reactions. They then treat blood disorders like sickle cell anemia, thalassemia, or hereditary spherocytosis. These may need blood transfusions, iron removal treatments, or even bone marrow transplants. For autoimmune haemolytic anaemia, doctors often use corticosteroids or, sometimes, immunosuppressants or spleen removal surgery. Infections like malaria get treated with anti-malarial drugs and supportive care. If the case is severe, patients may need hospital stays to stabilize their condition and manage anemia. Treatment of Hepatic Jaundice Hepatic jaundice occurs when liver cells get damaged or stop working well. The most common causes include viral hepatitis, alcoholic liver disease, drug damage, and cirrhosis. Viral Hepatitis Hepatitis A and E usually get better on their own. Treatment involves rest, fluids, and avoiding anything that harms the liver. Hepatitis B and C might need antiviral medicines. For chronic cases, long-term treatment reduces the virus and stops the liver from getting worse. Doctors regularly check liver function with blood tests to track recovery or decline. Alcoholic Hepatitis Stopping alcohol use is key for healing and long-term liver health. Patients also need good nutrition and vitamin support, especially thiamine, folate, and B vitamins. Corticosteroids may help reduce inflammation in severe cases, but doctors watch patients closely because this treatment can be risky. Non-Alcoholic Fatty Liver Disease (NAFLD) Weight loss and lifestyle changes are the main treatments. Diet and exercise help most. Managing other health problems like diabetes, high blood pressure, and high cholesterol slows the disease. Autoimmune Hepatitis Doctors treat this with immune-suppressing drugs, usually corticosteroids plus azathioprine. Drug-Induced Liver Injury Doctors stop the harmful drug right away. For paracetamol overdose, they use N-acetylcysteine as an antidote. Supportive care helps, and in severe cases, liver transplantation might be needed. Treatment of Post-Hepatic (Obstructive) Jaundice This type happens when bile ducts get blocked, stopping bilirubin from leaving the body. Gallstones Doctors use a procedure called ERCP to remove stones blocking the common bile duct. Often, they remove the gallbladder surgically to stop stones from coming back. Tumours (e.g., pancreatic cancer, cholangiocarcinoma) Doctors place stents to keep bile ducts open and relieve blockage. If the tumor can be removed, surgery is done. Advanced or inoperable tumors may get chemotherapy or radiotherapy. Biliary Strictures or Infections These conditions might need antibiotics, bile drainage, or surgery depending on severity. Phototherapy in Neonatal Jaundice Newborn jaundice is common and usually harmless, but very high bilirubin levels can cause brain damage called kernicterus. Phototherapy This treatment changes bilirubin into a form the body can easily get rid of. Hospitals use blue lights or fiber-optic blankets. Phototherapy is safe and effective but needs close monitoring to prevent dehydration or overheating. Exchange Transfusion Doctors use this when phototherapy doesn’t work. They replace the baby’s blood with donor blood to quickly lower bilirubin. Liver Transplantation In severe liver failure, cirrhosis, or liver cancer, a liver transplant can save a life. Doctors decide who qualifies based on health scores like MELD and overall condition. After transplant, patients need lifelong medicines to stop rejection and regular check-ups. Surgical techniques and care have improved outcomes greatly. Treatment of Underlying Metabolic or Genetic Disorders Sometimes jaundice comes from rare inherited problems. Examples include: Early diagnosis and treatment of these rare causes are vital to stop permanent damage. Managing Complications of Jaundice Doctors often need to treat problems caused by jaundice too. Hepatic Encephalopathy Doctors use lactulose, rifaximin, and diet changes to manage this brain condition. Ascites Salt restriction, diuretics, and sometimes fluid removal help control fluid buildup in the belly. Coagulopathy Vitamin K or plasma transfusions may help when blood doesn’t clot well. Pruritus Doctors relieve itching with cholestyramine, ursodeoxycholic acid, and antihistamines. Regular check-ups and patient education help prevent worsening and hospital visits. Conclusion The treatment of jaundice needs a clear understanding of its cause. It ranges from simple care and lifestyle changes to surgery and liver transplants. Quick action saves lives in acute cases, while chronic problems need long-term care from many specialists. New tests and treatments have improved patient outcomes. Still, fast diagnosis, correct treatment, and ongoing care remain the keys to success. [Next: Complications of Jaundice →]

Treatment of Jaundice Read More »

Illustration of a woman showing progression from healthy skin to yellowing due to jaundice and potential complications

Complications of Jaundice

Jaundice may initially appear to be a benign symptom—simply the yellowing of the skin and eyes—but it can lead to or signify serious underlying health complications. While mild forms, especially in newborns or during short viral infections, often resolve on their own, severe or prolonged jaundice can cause major problems. The complications depend on the cause, how long jaundice lasts, and how quickly treatment starts. If untreated, jaundice can cause permanent organ damage, chronic illness, or even death. Since jaundice often signals liver, bile duct, or blood disorders, most complications come from these diseases. Understanding these risks helps doctors prevent issues early and monitor high-risk patients well. 1. Hepatic Encephalopathy Hepatic encephalopathy (HE) is a serious brain condition that happens in advanced liver disease. It occurs when toxins like ammonia build up because the liver cannot remove them. This can happen in jaundice caused by liver failure or cirrhosis. Symptoms include confusion, mood changes, drowsiness, tremors, and poor coordination. HE needs urgent treatment, including medications like lactulose and rifaximin, and sometimes intensive care. Repeated episodes may mean a liver transplant is necessary. 2. Kernicterus (in Neonates) Kernicterus is a severe brain injury caused by very high levels of bilirubin crossing into a newborn’s brain. It is a feared complication but can be prevented with proper monitoring. Signs include poor feeding, high-pitched crying, muscle stiffness, seizures, hearing loss, and cerebral palsy. Treatments include phototherapy and, if needed, blood exchange. Delays can cause lifelong disability or death. 3. Coagulopathy and Bleeding Tendencies The liver makes clotting factors. In liver diseases causing jaundice, this function can fail, leading to coagulopathy—where blood does not clot well. This causes easy bruising, bleeding in the gut, brain hemorrhage, or excessive bleeding after injuries or surgery. Doctors monitor clotting tests and may give vitamin K or plasma. Severe cases might need a liver transplant. 4. Chronic Pruritus and Skin Infections In jaundice caused by bile flow blockage, bile salts build up in the skin and cause severe itching (pruritus). Constant scratching can lead to skin damage and infections. This itching affects sleep and mood. Treatments include antihistamines, bile acid binders, and sometimes bile duct drainage to relieve blockage. 5. Renal Dysfunction Advanced liver failure can cause hepatorenal syndrome (HRS), a type of kidney failure without kidney damage. Symptoms include low urine output, low blood pressure, and rising kidney markers. Treatment includes medicines to improve blood flow, albumin infusions, and dialysis while waiting for a liver transplant. 6. Malabsorption and Nutritional Deficiencies Bile helps digest fats and absorb fat-soluble vitamins (A, D, E, K). Blocked bile flow can cause poor absorption, leading to fatty stools, weight loss, night blindness, bone weakness, nerve problems, and bleeding. Treatment involves fixing the cause and giving vitamin supplements. Special diets with medium-chain fats may help. 7. Gallstone Complications Gallstones blocking bile ducts can cause: Quick diagnosis and treatment, often by surgery or endoscopy, prevent these problems. 8. Progression to Cirrhosis and Liver Cancer Chronic jaundice from long-term liver disease can lead to cirrhosis—scarring that reduces liver function. Cirrhosis may cause portal hypertension, fluid buildup, bleeding, brain effects, and liver cancer. Early care can slow progression. Advanced disease may require transplantation. 9. Psychosocial and Quality of Life Implications Chronic jaundice with fatigue, itching, or brain changes can lower quality of life. Patients often feel depressed or anxious and may withdraw socially. Mental health support, counseling, and education improve treatment success and well-being. 10. Mortality Risk Untreated or late-treated jaundice from liver failure, cancer, or blood crises can be fatal. Death risk rises with late diagnosis, delayed treatment, or severe infections. This highlights the need for early recognition and comprehensive medical care. Conclusion Jaundice complications range from mild discomfort to life-threatening organ failure. What seems like simple yellow skin can quickly become a medical emergency if the cause is not treated. Careful monitoring, early diagnosis, and active treatment help prevent severe outcomes. Healthcare providers must act promptly and guide patients through comprehensive care. Patients and families should know warning signs and seek help early to improve chances of recovery. [Next: Back to Overview →]

Complications of Jaundice Read More »

Illustration of a man with severe headache and a brain graphic showing inflammation, symbolising Japanese encephalitis

Japanese Encephalitis

Japanese encephalitis is a serious viral brain infection spread by infected mosquitoes. It mainly occurs in Asia and the Western Pacific. Though not well known outside these areas, it is the leading cause of viral encephalitis in Asia, causing thousands of cases each year. The virus responsible, called Japanese encephalitis virus (JEV), belongs to the Flavivirus family, which also includes yellow fever, Zika, and dengue viruses. Japanese encephalitis is a zoonotic disease. This means it naturally cycles between animals and mosquitoes, with humans becoming infected by chance. Most people infected with JEV show no symptoms. However, about 1 in 250 develop severe illness. This usually means inflammation of the brain, called encephalitis, which can cause coma, long-term disability, or death. Children under 15 years old are affected most, especially where vaccination is low. Survivors may suffer lasting problems like learning difficulties, seizures, or paralysis. The virus spreads silently between mosquitoes and animal hosts, mainly pigs and wading birds. These animals do not show illness but carry the virus. Humans get infected when bitten by an infected mosquito but do not spread the virus further. Humans are dead-end hosts. They cannot keep the infection cycle going but can suffer severe effects. In recent years, changes such as more rice farming, pig rearing, and shifting climates have helped the disease spread to wider areas. It now affects parts of Australia, Pakistan, and urban edges of Asia. The World Health Organization (WHO) estimates over 3 billion people live in areas at risk of Japanese encephalitis. Transmission and Reservoirs The main mosquito spreading JEV is Culex tritaeniorhynchus. These mosquitoes breed in still water, common in rice fields and flooded farms. When they bite infected pigs or birds, they pick up the virus. Pigs are important amplifying hosts because they develop high virus levels without becoming sick. This allows mosquitoes to become infected again after biting pigs. Humans do not spread the virus. So, controlling Japanese encephalitis means focusing on mosquitoes, vaccination, and managing contact with animals, not stopping human-to-human spread. Disease Presentation Over 99% of JEV infections cause no symptoms or only mild signs like fever or headache. Severe illness causes acute encephalitis syndrome (AES). Patients may suddenly develop high fever, confusion, seizures, movement problems, and coma. The death rate in symptomatic cases is 20% to 30%. Among survivors, up to 50% may have lasting brain damage. The incubation period is 5 to 15 days. This is the time from infection to symptoms. Without treatment, death can occur within days of symptom start. At-Risk Groups Certain people face higher risks of Japanese encephalitis: Many countries have lowered disease rates with vaccination campaigns. However, millions remain unprotected due to cost, logistics, or politics. Global Impact and Prevention Around 68,000 clinical cases of Japanese encephalitis occur worldwide each year. Most cases happen in India, China, Nepal, Vietnam, and Southeast Asia. Yet, the disease could spread to new areas because of: The good news is that Japanese encephalitis is preventable. A safe, effective vaccine exists and is used in many endemic countries. Other prevention steps include: Importance of Awareness Despite its impact, Japanese encephalitis is often overlooked, especially outside endemic areas. Travellers and health workers may underestimate the risk. Stronger surveillance, public education, and international cooperation are vital to reduce disease spread. Raising awareness about how the virus spreads, its symptoms, and dangers helps protect high-risk groups. Early diagnosis and treatment improve outcomes. Although no specific antiviral exists, supportive care can save lives. [Next: Causes of Japanese Encephalitis →]

Japanese Encephalitis Read More »

Close-up of a mosquito on human skin, the primary cause of Japanese encephalitis transmission

Causes of Japanese Encephalitis

Japanese encephalitis is caused by the Japanese encephalitis virus (JEV), a single-stranded RNA virus in the Flavivirus genus. This virus is related to dengue, Zika, and yellow fever. While the virus itself causes the disease, several other factors help it spread. These include mosquitoes, animals, human behaviour, and environmental conditions. Unlike infections that spread from person to person, Japanese encephalitis moves through a complex cycle involving animals and mosquitoes. Understanding the causes of Japanese encephalitis means looking at each step in this transmission chain—from the virus itself to the places and behaviours that let it thrive. The Virus: Japanese Encephalitis Virus (JEV) The Japanese encephalitis virus mainly targets the brain. After a mosquito bite, the virus multiplies in nearby tissues and then enters the bloodstream. In most people, the immune system clears it quickly. But in rare cases, the virus crosses into the brain and causes encephalitis—serious inflammation that can lead to death or lasting damage. JEV survives in nature through a zoonotic cycle, meaning it spreads among animals and mosquitoes. Humans are not part of this natural cycle, making them accidental hosts. Mosquitoes: The Main Vectors of Japanese Encephalitis The Culex tritaeniorhynchus mosquito plays the biggest role in spreading JEV. These mosquitoes bite at night and breed in standing water like: Several traits make Culex mosquitoes excellent virus carriers: After biting an infected animal, the mosquito stores the virus in its saliva. When it bites a human, it injects the virus into the bloodstream. Amplifying Hosts: Pigs and Wading Birds Pigs are key amplifiers of Japanese encephalitis. When a mosquito bites an infected pig, the virus multiplies to high levels in the pig’s blood. Other mosquitoes feeding on the same pig can then pick up the virus and spread it again. This is especially risky in rural areas where pigs live near rice fields and homes. Pigs breed fast and are often raised in large groups, increasing the risk of viral spread. Wading birds, such as egrets and herons, are natural virus reservoirs. They help the virus survive between seasons and carry it across long distances. Unlike pigs, birds can fly far and bring JEV into new areas. Humans as Dead-End Hosts Humans can get Japanese encephalitis through a mosquito bite, but they do not spread the virus further. The level of virus in human blood is too low to infect another mosquito. This makes humans “dead-end hosts.” Although humans don’t continue the cycle, the virus can cause serious illness or death in people. Because human infection is accidental, outbreaks depend on the presence of infected mosquitoes and animals—not human-to-human spread. Environmental and Climate Factors The environment plays a major role in the spread of Japanese encephalitis. Key factors include: a. Rainy Season and Standing WaterMosquito numbers increase during and after heavy rains. Flooded fields and stagnant pools become ideal mosquito breeding grounds. Outbreaks often occur in the rainy season. b. Rice FarmingRice paddies hold water for long periods and attract both mosquitoes and pigs. This creates a hotspot for viral transmission. c. Warm Temperatures and High HumidityHot weather speeds up how fast the virus multiplies inside mosquitoes. Humid conditions also help mosquitoes live longer and bite more often. d. Deforestation and Urban ExpansionClearing forests for farms or buildings forces animals, mosquitoes, and people to live closer together. This increases the chance of human exposure to infected mosquitoes or birds. Human Activity and Risk Factors Some daily habits and social issues also raise the risk of Japanese encephalitis, including: Rapid urban growth without good sanitation may also lead to new mosquito habitats, especially in crowded informal settlements. Travel and the Spread Beyond Endemic Areas Travellers visiting affected regions can also get infected. The risk is highest during the rainy season and in rural areas. Farming, camping, or hiking outdoors for long periods increases exposure. Though global spread is rare, migrating birds or mosquitoes could carry JEV to new areas. The World Health Organization advises vaccination for travellers spending a month or more in high-risk areas—or less time if visiting rural zones with known outbreaks. Conclusion The causes of Japanese encephalitis are complex. They involve a virus, mosquitoes, animals, humans, and the environment. Unlike common infections that spread easily between people, this disease needs many steps to keep going. Stopping the spread means breaking this chain. This can be done by: Most importantly, wide access to vaccines and good public health planning can prevent serious outbreaks and save lives. [Next: Symptoms of Japanese Encephalitis →]

Causes of Japanese Encephalitis Read More »

Scroll to Top