Mental Matters

Author name: admin

Iron-rich foods like eggs, dried fruits, oats, and legumes arranged around the symbol 'Fe' for iron

Treatment of Iron Deficiency Anaemia

The treatment of iron deficiency anaemia centres on two primary goals: restoring adequate iron levels in the body and identifying and addressing the underlying cause of the deficiency. To fix the problem for good, doctors need to do more than just add iron. They must also find out what caused the iron levels to drop. Without this, the anaemia could come back. Luckily, this condition is easy to treat and prevent when handled early and in a way that suits each person. Treatment usually includes iron supplements, diet changes, and managing blood loss. In some cases, it may involve medical or surgical care. The exact plan depends on how bad the anaemia is, the person’s age, medical background, and how quickly they need iron levels restored. Oral Iron Supplementation for Iron Deficiency Anaemia The most common and cheapest way to replace iron is by taking iron pills. These usually come in forms like ferrous sulphate, ferrous fumarate, or ferrous gluconate. Ferrous sulphate is the most used. People often take: To get the best results, people should take the tablets: Haemoglobin levels usually start to rise within 2–3 weeks. Full recovery takes about 2–3 months. Even after levels go back to normal, iron tablets should continue for several more months to fill up body stores. Common side effects include: These side effects often improve by adjusting the dose or changing the type of pill. Slow-release tablets may help with stomach issues but don’t absorb as well. Intravenous Iron Therapy Doctors use IV iron when: IV iron types include iron sucrose, ferric carboxymaltose, and iron dextran. These are often given in clinics and raise iron levels in days or weeks. Modern IV iron is safe for most people. Mild reactions, like a warm feeling or dizziness, may happen. Serious allergic reactions are rare but need fast care. Blood Transfusion and Iron Deficiency Anaemia Doctors use blood transfusions when: Transfusions help right away, but they do not fix the iron shortage. People still need iron treatment afterward to stop it from coming back. Treating the Underlying Cause of Iron Deficiency Anaemia To avoid repeat problems, it’s key to find out why iron levels dropped. Just giving iron won’t help for long. Here are common causes and treatments: In many young women, heavy bleeding and not eating enough iron are the main causes. Spotting this helps avoid unnecessary tests. Dietary Management for Iron Deficiency Anaemia Iron from food also helps treat and stop anaemia. People should eat both animal and plant-based iron foods. Foods with haem iron (easier to absorb): Foods with non-haem iron: Non-haem iron is harder to absorb. Eating it with foods high in vitamin C, like oranges or tomatoes, improves uptake. On the other hand, calcium, tea, and some grains block absorption, so they should be eaten at different times. Monitoring and Follow-Up in Iron Deficiency Anaemia After starting treatment, doctors need to check if it’s working. Blood tests usually happen: Once iron levels are steady, people might get tested every 6–12 months. This is more important for those with long-term health issues or a high chance of relapse. Doctors also check how the person feels. They look for signs like more energy, clearer thinking, better stamina, and improved skin and hair. These changes often help people stay motivated and stick to their plan. Iron Deficiency Anaemia Treatment Summary The treatment of iron deficiency anaemia needs more than just adding iron. A full plan must also fix the cause, support healing, and stop it from happening again. With iron tablets or IV therapy, good food, and treatment of the cause, most people get better. They can return to a normal, healthy life. Regular checks and education help keep iron levels steady and avoid serious problems. [Next: Complications of Iron Deficiency Anaemia →]

Treatment of Iron Deficiency Anaemia Read More »

Medical professional holding blood vials and transfusion equipment for anaemia-related treatment

Complications of Iron Deficiency Anaemia

While often overlooked as a simple nutritional shortfall, iron deficiency anaemia can have far-reaching consequences when left untreated. The complications of iron deficiency anaemia can start with mild problems, like tiredness or trouble focusing. But over time, they can become more serious. These include problems with the heart, brain, growth, and immune system. When the body doesn’t get enough oxygen, every part can suffer. That’s why early diagnosis and treatment are so important. How bad the complications get depends on several things. These include how long the anaemia has lasted, how severe it is, and whether doctors treat the root cause. Long-term anaemia can wear the body down, especially in people who already have health problems. Cardiovascular Problems from Anaemia One of the most serious effects of iron deficiency anaemia is its impact on the heart. When red blood cells carry less oxygen, the heart has to work harder to get oxygen to the body. This extra work can cause: If this continues for too long, it may become life-threatening. Treating iron levels early helps prevent damage to the heart. Effects on Thinking and Mood Iron helps the brain grow and function. It helps carry oxygen and build brain chemicals. When iron is low, people may struggle to think clearly or feel good emotionally. In children: In adults: Replacing iron usually helps. But in children, long delays in treatment can lead to lasting effects. Complications of Iron Deficiency Anaemia in Pregnancy Pregnant women need more iron for both themselves and their baby. Without enough, serious problems can happen, such as: Low iron during pregnancy also affects the baby’s brain and body development. That’s why doctors check for anaemia during check-ups and give iron supplements when needed. Weakened Immunity and More Infections The immune system needs iron to work well. Without it, people get sick more often and stay sick longer. This is especially true for children, older adults, and those with weak immune systems. Low iron can cause: In areas with diseases like malaria or TB, complications of iron deficiency anaemia make fighting these infections even harder. Physical Tiredness and Poor Performance One of the first signs of anaemia is constant tiredness. When blood can’t carry enough oxygen, the body slows down. This can cause: People who work physically demanding jobs or play sports may notice slower recovery and more injuries. For some, the tiredness can feel like a long-term illness. Delayed Growth and Development in Kids Children who don’t get enough iron may not grow or develop properly. They may: While most of these problems improve with iron and a healthy diet, some effects may last if the anaemia goes untreated for too long. Skin, Mouth, and Nail Changes Iron helps keep skin, nails, and the inside of the mouth healthy. When iron is low, these parts can show early signs of problems. These include: While these signs aren’t dangerous, they can affect self-esteem. Most improve once iron levels go up. Unusual Cravings and Restless Legs Complications of iron deficiency anaemia can include odd symptoms linked to the brain and nerves. These problems often improve with iron treatment, though some may need extra support. Existing Conditions Get Worse People with long-term illnesses like kidney problems, cancer, or heart failure often get anaemia too. When that happens, their overall health can decline faster. For example: Fixing iron levels helps people handle their other health problems better. Higher Risk of Death and Illness When severe and untreated, anaemia can raise the risk of death. This is most serious in: Sometimes, anaemia is the first sign of a hidden, serious illness like cancer. Delaying treatment makes these conditions harder to find and treat. Summary of Complications of Iron Deficiency Anaemia The complications of iron deficiency anaemia affect nearly every part of the body. They range from tiredness and thinking problems to heart failure, infections, and slow growth in kids. Most of these problems can be prevented or reversed with early testing, the right treatment, and regular follow-ups. Spreading awareness—especially among high-risk groups—is key to lowering the global burden of this preventable health issue. [End of Article – Back to Overview]

Complications of Iron Deficiency Anaemia Read More »

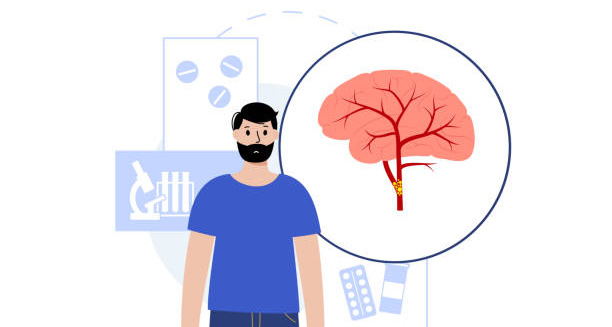
Illustration of a man with a zoomed-in view of increased pressure in the brain’s blood vessels

Overview of Intracranial Hypertension

Overview of Intracranial Hypertension Intracranial hypertension is a medical condition characterised by increased pressure within the skull, often due to an imbalance in the production and absorption of cerebrospinal fluid (CSF) or a blockage in its circulation. The skull holds the brain, blood, and CSF inside a hard, fixed space. When pressure rises above normal—usually over 20 mmHg in adults—it squeezes brain tissue, affects brain function, and can lead to serious problems if not treated. There are two main types of intracranial hypertension: idiopathic (also called primary) and secondary. Idiopathic intracranial hypertension has no clear cause, but it is strongly linked to risk factors like obesity and hormone changes. It affects women of childbearing age more often. In contrast, secondary intracranial hypertension comes from a known problem, such as a brain tumour, head injury, infection, or side effects from medicine. Although this condition is rare, it can greatly affect a person’s life. People often deal with strong and ongoing headaches, blurry or double vision, nausea, and a whooshing sound in the ears (called pulsatile tinnitus). In more serious cases, intracranial hypertension may cause swelling of the optic nerve. This can lead to lasting vision loss if doctors don’t treat it quickly. The symptoms can start off mild but tend to get worse, making quick medical care important. What Happens Inside the Brain with Intracranial Hypertension Doctors and researchers are still studying exactly how intracranial hypertension works. But they know that anything that upsets the normal flow of CSF can lead to too much pressure in the skull. CSF cushions the brain, carries away waste, and brings in nutrients. The body makes it and reabsorbs it all the time. If that cycle gets blocked—because of too much fluid, not enough absorption, or something in the way—then pressure builds up. This condition, especially idiopathic intracranial hypertension, often affects women between the ages of 20 and 45. It’s most common in women who are overweight or have gained weight quickly. Hormones, especially oestrogen, seem to play a role, although experts are still looking for clear proof. On the other hand, secondary intracranial hypertension can affect anyone, no matter their age or gender. It’s usually caused by something more obvious, like a growth, infection, or injury. How Intracranial Hypertension Is Diagnosed and Treated Doctors often find it hard to diagnose intracranial hypertension because its signs look like those of other conditions. Migraines, cluster headaches, or brain tumours can have similar symptoms. So, a full diagnosis usually needs a few steps. These include a physical exam, scans like MRI or CT, a spinal tap, and eye checks. The spinal tap is key because it shows the pressure of the CSF and helps rule out infections or bleeding. Treatment has three main goals: to lower the pressure, protect the eyes, and treat any root cause. When the condition is mild, simple steps like losing weight, eating better, or drinking less fluid might help. Doctors often prescribe medicines like acetazolamide to lower CSF production, or diuretics to reduce fluid levels. For tougher cases, surgery might be needed. Procedures like optic nerve sheath fenestration or a CSF shunt can ease the pressure and save vision. Living with Intracranial Hypertension Dealing with intracranial hypertension can be hard on both the body and mind. The symptoms often come and go, and the risk of vision problems can cause stress and fear. Many people find it tough to work, stay social, or do daily tasks. Still, with early care, smart planning, and regular check-ups with neurologists and eye doctors, many people can live full, active lives. Researchers are working hard to better understand intracranial hypertension. They aim to improve how it’s diagnosed and treated. New studies focus on going beyond symptoms to find treatments that deal with the cause. Support groups are also helping more people. They raise awareness and give patients a place to connect with others who understand. In conclusion, intracranial hypertension is a serious but treatable problem. It needs quick care and long-term follow-up. Whether idiopathic or secondary, it can harm the brain and eyes if ignored. More awareness—both among doctors and the public—can lead to earlier diagnosis, better care, and improved lives for those affected. [Next: Causes of Intracranial Hypertension →]

Overview of Intracranial Hypertension Read More »

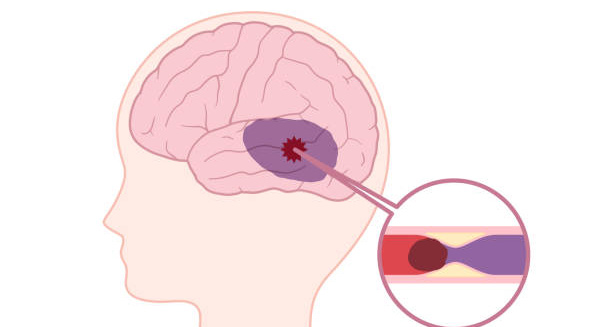
Medical illustration of a brain with blocked blood flow causing increased pressure

Causes of Intracranial Hypertension

Intracranial hypertension occurs when the pressure inside the skull increases beyond normal levels. This heightened pressure builds up because of changes in the balance of brain tissue, fluid, or blood. Since the skull is a closed space, even small changes can cause problems. Understanding the causes of intracranial hypertension is very important. The reason for the pressure matters, especially when deciding how to treat it. In many cases, the condition is either idiopathic (with no clear cause) or secondary (caused by a known issue). How Intracranial Pressure Rises Pressure often rises when the body makes too much cerebrospinal fluid (CSF), when CSF can’t drain properly, or when brain tissue or blood volume increases. Experts sort these causes into two groups: idiopathic intracranial hypertension (IIH) and secondary intracranial hypertension. Causes of Intracranial Hypertension: Idiopathic “Idiopathic” means that doctors can’t find a specific disease causing the problem. Even though the exact reason is unknown, certain risk factors appear often. One major link is obesity, especially in women of childbearing age. People who are overweight and recently gained more weight have a much higher chance of developing IIH. While the exact reason is unclear, changes in hormone levels, pressure in the belly and chest, and blocked brain vein drainage all seem to play a role. Hormonal changes may also increase the risk. This is especially true for changes involving oestrogen. The high number of IIH cases in women before menopause supports this idea. Conditions like polycystic ovary syndrome (PCOS), which affects hormone balance and body weight, are often seen in people with IIH. Some experts believe that genetics might be involved too. A family history could affect how the body handles CSF or brain vein drainage. This might make some people more likely to get the condition. Several medicines might also trigger or worsen IIH. These include: While these usually cause secondary intracranial hypertension, they sometimes play a role in idiopathic cases. Causes of Intracranial Hypertension: Secondary Secondary intracranial hypertension happens when doctors find a clear reason. These causes vary a lot and include problems like brain swelling, blocked veins, infections, and toxins. These issues can raise CSF levels or cause swelling, which increases pressure in the skull. One serious cause is a brain tumour. Tumours take up space and push on brain structures. This reduces room for fluid and blood, which quickly raises pressure. Headaches, vomiting, and vision problems often follow. Another critical cause is cerebral venous sinus thrombosis (CVST). In CVST, a blood clot forms in the brain’s veins, stopping blood from draining. This builds up pressure. CVST happens in people with clotting disorders, during pregnancy, or after head injuries or infections. Hydrocephalus is another problem. It causes too much fluid to build up in the brain. Reasons include birth defects, infections like meningitis, or blockages from cysts or tumours. Infections such as meningitis and encephalitis cause swelling in the brain and nearby tissues. This blocks CSF flow and stops fluid from being absorbed, which raises pressure even more. Head trauma is also a big cause. Injuries can cause bleeding, swelling, or blocked fluid flow. In these cases, pressure rises quickly and can become life-threatening. Other Medical Causes of Intracranial Hypertension Some health problems like liver or kidney failure and very high blood pressure also affect brain pressure. These problems change how fluid moves in the body, which can reach the brain. Certain substances can also raise pressure if misused. These include: In children, birth defects such as Arnold-Chiari malformation, Dandy-Walker syndrome, and craniosynostosis often cause pressure buildup. These problems affect how the brain and skull grow or how fluid moves. Autoimmune diseases like lupus or sarcoidosis can also raise brain pressure. These conditions cause swelling in brain tissues or blood vessels, which adds to the problem. Even outside forces can play a role. Things like high altitude or very hard physical activity sometimes raise pressure for a short time. These symptoms usually go away on their own but still feel very real to the person affected. Summary of the Causes of Intracranial Hypertension In short, the causes of intracranial hypertension depend on whether the problem is idiopathic or secondary. Idiopathic cases link mostly to obesity, hormone changes, and possibly genetics. Secondary cases result from more obvious issues like tumours, infections, vein clots, head injuries, or medications. Getting the right diagnosis is key. Once doctors know what’s causing the pressure, they can choose the best treatment. By fixing the root problem—whether it’s a health condition or lifestyle issue—pressure inside the skull can go down, and people can feel much better. [Next: Symptoms of Intracranial Hypertension →]

Causes of Intracranial Hypertension Read More »

Woman holding her head in pain due to severe headache

Symptoms of Intracranial Hypertension

Intracranial hypertension refers to elevated pressure inside the skull, and its symptoms can range from subtle to severe, depending on the cause, duration, and degree of pressure increase. The symptoms of intracranial hypertension often mimic other neurological or systemic conditions, which can lead to delayed diagnosis if not carefully assessed. Early recognition of these signs is crucial for preventing long-term damage, especially in cases where vision or brain function may be at risk. The most common and often earliest symptom of intracranial hypertension is a persistent and throbbing headache. Unlike tension headaches or migraines, these headaches tend to worsen when lying down, during physical activity, or after waking up. Lying flat slows down blood drainage from the brain, which makes the pressure go up. These headaches usually affect the whole head and don’t go away easily with normal painkillers. Many people describe it as a heavy or bursting pain. Vision Problems and Pulsatile Tinnitus in Intracranial Hypertension Vision problems are also very common. A serious one is brief vision blackouts or dimming, especially when standing up quickly. These short episodes may only last a few seconds but can happen often. Double vision and blurry eyesight can also occur. If the pressure stays high, it may cause the optic nerves to swell, which can lead to vision loss that does not get better. Another key symptom of intracranial hypertension is pulsatile tinnitus. This means hearing a whooshing or pulsing sound in the ears that matches the heartbeat. It usually happens due to blood flow changes near the ear. While not harmful by itself, it can be very annoying and upsetting. Nausea and vomiting often come along with the headaches. This happens because the brain’s vomiting centre feels the pressure. These symptoms tend to be worse in the mornings. In children, vomiting may be one of the only signs of trouble, and it should always be taken seriously. Other Physical and Sensory Symptoms of Intracranial Hypertension Many people also feel neck pain or stiffness. This pain usually spreads to the back of the head or neck. It often feels worse after coughing, sneezing, or straining. Some people mistake it for muscle tension or poor posture, but it’s actually linked to pressure moving down the spine. Double vision, or diplopia, happens when the sixth cranial nerve is squeezed by the pressure. This nerve helps control how the eyes move side to side. When it stops working properly, the eyes don’t line up, and vision splits into two images. Tilting the head can help a little, but it’s not a fix. Light and sound sensitivity are also frequent. These problems can feel like migraine symptoms. Bright lights, loud noises, and busy places can quickly feel overwhelming, making everyday life harder. Thinking problems are easy to miss but are part of the symptoms of intracranial hypertension. People often find it hard to focus or remember things. Their thinking may feel slower than normal. This can affect school, work, and daily tasks. Even though these issues aren’t as visible as headaches or vision problems, they cause just as much trouble over time. Intracranial Hypertension in Children and Severe Cases In children, the symptoms of intracranial hypertension don’t always look the same. Babies might show a bulging soft spot on the head. Their heads may grow too fast. They might also be cranky or develop more slowly than expected. Older kids may say they have headaches or blurry vision. But without a careful check-up, it’s easy to miss the real cause. In serious or fast-moving cases, people can become confused or even pass out. Some may feel very sleepy, act strangely, or lose awareness. These signs mean the pressure in the brain has become very dangerous. If this happens and doctors don’t act fast, it can lead to brain tissue being pushed into places it shouldn’t go. This is called herniation, and it can be deadly. In cases of idiopathic intracranial hypertension, the symptoms of intracranial hypertension tend to come and go. People may feel okay for a while, then have flare-ups. Weight gain, hormone changes, or some medicines can make symptoms worse. Because of this, keeping a symptom diary can help both the patient and the doctor track the changes and decide what treatment works. Emotional and Hidden Symptoms of Intracranial Hypertension The symptoms of intracranial hypertension can also affect a person’s mood. Chronic pain, vision problems, and brain fog can make people feel anxious or sad. Some may stop going out or feel afraid to leave the house, especially if they can’t see well or feel off-balance. These emotional struggles are just as real and need just as much care. Some people, especially early on, may have no clear symptoms. Doctors may only spot the problem during a regular eye check. If the eye doctor sees swelling in the optic nerve, it might be the first sign of intracranial hypertension. Finding it this early can help avoid major problems later. In summary, the symptoms of intracranial hypertension affect many parts of the body and mind. Headaches, vision changes, ringing in the ears, and trouble thinking are key warning signs. But every symptom matters. Women of childbearing age, people who are overweight, or anyone with past head injuries should pay close attention to any signs. Getting help early can prevent vision loss, brain damage, and other lasting problems. [Next: Diagnosis of Intracranial Hypertension →]

Symptoms of Intracranial Hypertension Read More »

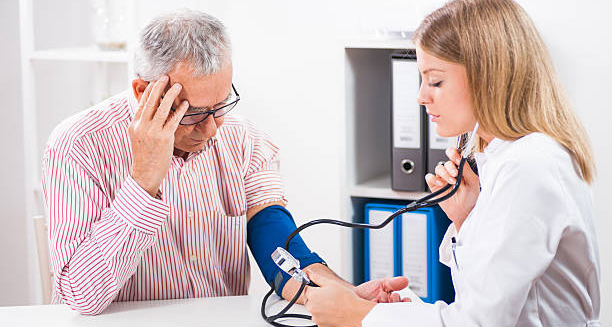
Doctor measuring blood pressure of an elderly man with a headach

Diagnosis of Intracranial Hypertension

Intracranial hypertension is a serious medical condition that needs careful tests to confirm it, find any causes, and start the right treatment. Doctors use a mix of medical history, physical exams, eye checks, brain scans, and spinal fluid tests to diagnose it. Quick and accurate diagnosis helps prevent complications, especially permanent vision loss and brain damage. Medical History and Symptoms The first step is to take a detailed medical history. The doctor asks about symptoms like ongoing headaches, vision problems, nausea, ringing in the ears, or changes in thinking. They want to know if symptoms started suddenly or slowly, how long they last, and if they get worse at certain times or positions. The doctor also asks about risk factors such as obesity, recent weight gain, pregnancy, or use of medicines that can raise pressure, like tetracyclines, retinoids, or hormone treatments. Physical and Neurological Exam Next, the doctor performs a thorough physical and neurological exam. They look for signs of high pressure, especially swelling of the optic disc called papilloedema. This is the most reliable sign of raised intracranial pressure. Doctors use an ophthalmoscope to check for it. If papilloedema is found, it strongly suggests intracranial hypertension. They also check for nerve problems such as sixth cranial nerve palsy, which causes double vision, abnormal eye movements, or lowered consciousness. These signs may show the condition is severe or worsening fast. Brain Imaging Tests Many symptoms of intracranial hypertension can be caused by other problems like brain tumors, migraines, infections, or blood vessel issues. Therefore, brain imaging is very important. MRI scans are usually the first test. MRI can rule out tumors, hydrocephalus, blood clots, or birth defects. It may also show subtle signs of idiopathic intracranial hypertension, such as flattening of the back of the eye, swelling of optic nerve sheaths, empty sella, or narrowing of venous sinuses. If blood clots in brain veins are suspected, doctors use MR venogram (MRV) or CT venogram (CTV). These scans check the veins that drain blood from the brain. Blocked veins can raise pressure and must be found and treated. Venograms provide detailed views that standard MRI or CT might miss. Lumbar Puncture (Spinal Tap) A key test for diagnosis is the lumbar puncture. This involves inserting a needle into the lower spine to collect cerebrospinal fluid (CSF). Doctors measure the opening pressure of CSF. In adults, pressure above 20 cm H₂O (or 25 cm H₂O in obese people) is high. The fluid is also checked for infection, bleeding, or inflammation. If the CSF is normal but pressure is high, and scans show no other cause, doctors may diagnose idiopathic intracranial hypertension (IIH). For children, the normal pressure ranges differ, and doctors consider age, weight, and other health issues when interpreting results. Children may need sedation for scans and lumbar puncture. Infants with a bulging soft spot on the head or unusually large head size might be suspected of raised pressure before testing. Eye Exams Patients with vision problems need thorough eye exams. Eye specialists may perform: These tests show how much the optic nerve is affected and help track changes over time. OCT is a non-invasive scan that can detect early swelling before symptoms appear. Lumbar Drain Trial Sometimes, doctors do a lumbar drain trial, where they remove some spinal fluid temporarily to see if symptoms improve. Improvement in headaches or vision after fluid removal supports the diagnosis of intracranial hypertension and helps guide treatment decisions, like shunt surgery. Diagnostic Criteria and Differential Diagnosis After tests, doctors classify the condition as idiopathic or secondary intracranial hypertension based on cause. Diagnosing IIH requires meeting criteria known as the modified Dandy criteria: Doctors must also rule out other conditions that look similar, such as: Careful evaluation ensures the right diagnosis, especially in tricky cases. Summary Diagnosing intracranial hypertension requires teamwork and many tests: medical history, physical exam, brain scans, lumbar puncture, and eye checks. Quick and correct diagnosis is key to guiding treatment, watching for changes, and preventing serious problems like vision loss or brain herniation. Awareness of this condition, especially in young women with idiopathic cases, leads to earlier care and better results. [Next: Treatment of Intracranial Hypertension →]

Diagnosis of Intracranial Hypertension Read More »

Surgeons performing a medical procedure under magnification lights

Treatment of Intracranial Hypertension

The treatment of intracranial hypertension focuses on lowering high pressure inside the skull, easing symptoms, protecting vision, and preventing lasting problems. The approach depends on whether the condition is idiopathic (with no clear cause) or secondary (caused by another issue). Treatments range from lifestyle changes and medicines to surgery. Quick action is key to protect the brain and optic nerves from damage caused by long-term pressure. Idiopathic vs Secondary Intracranial Hypertension In idiopathic intracranial hypertension (IIH), the goal is to lower cerebrospinal fluid (CSF) pressure and keep vision normal. For secondary intracranial hypertension, doctors treat the root cause—such as brain tumors, infections, injuries, or blood flow problems—while also managing the high pressure. Lifestyle Modifications One of the most important steps in treating intracranial hypertension, especially in IIH, is weight control. Many studies show that even small weight loss can lower CSF pressure and reduce symptoms. Overweight patients are encouraged to follow a healthy diet and exercise regularly. Sometimes medical weight loss programs or weight-loss surgery may be needed, especially when fast results are required or other methods fail. Patients are also advised to avoid things that raise pressure, including: These lifestyle steps support medical and surgical treatments but usually do not work alone. Medicines to Lower Pressure The first-choice drug for intracranial hypertension is acetazolamide. This medicine lowers CSF production in the brain, helping to reduce pressure and ease headaches and vision problems. Doctors adjust the dose based on how well symptoms improve and side effects. Common side effects include tingling in fingers or toes, tiredness, stomach upset, and changes in taste. If acetazolamide does not work well or causes problems, topiramate may be used. It also lowers CSF production and can help with weight loss and headaches. However, topiramate may slow thinking, affect mood, or cause kidney stones in some people. In severe cases, doctors might add furosemide, a diuretic that increases fluid loss to reduce pressure further. It is sometimes combined with acetazolamide for better effect. Patients taking these drugs need regular tests to check electrolyte balance and kidney health. Corticosteroids reduce inflammation but are usually avoided long-term because they can cause fluid retention, weight gain, and increased pressure. They may be used briefly in emergencies or when inflammation is part of the problem. Managing Headaches and Vision For ongoing headaches, treatment may include painkillers or migraine medicines like amitriptyline or propranolol. It is important to avoid overusing pain medication, which can cause more headaches. Protecting vision is crucial. Patients need regular eye exams. If vision worsens, more aggressive treatment may be needed. Some patients require optic nerve sheath fenestration (ONSF), a surgery that makes a small cut in the membrane around the optic nerve to relieve pressure. This procedure can save vision in one or both eyes, especially if vision loss happens quickly. Surgical Treatments If other treatments fail or vision is at risk, surgery may be necessary. A common surgery is CSF shunting. A tube (ventriculoperitoneal or lumboperitoneal shunt) diverts fluid from the brain or spine to the belly, where the body absorbs it. Shunts work well but can block, get infected, or need repeated surgery. Venous sinus stenting is a newer method used in patients with blocked veins in the brain. A stent opens the narrowed vein to improve blood flow and lower pressure. This is usually for patients who do not respond to medicine and have clear vein blockage on scans. Therapeutic lumbar punctures can temporarily reduce CSF volume and relieve symptoms. Sometimes repeated punctures are done until a permanent treatment is ready. However, this is not a long-term solution and can cause infections or leaks. Treating Secondary Intracranial Hypertension When intracranial hypertension is caused by another problem, treating that issue is the priority: Fixing the main cause often improves pressure without long-term pressure-specific treatment. Team Care and Ongoing Monitoring Treating intracranial hypertension usually involves a team, including neurologists, eye doctors, surgeons, and dietitians. Regular check-ups are needed to track symptoms, eye health, and adjust treatment. People with IIH may need lifelong care and should learn to monitor symptoms, take medicine properly, and follow healthy habits. Women planning pregnancy need special care. Managing weight before pregnancy and close monitoring during pregnancy is important, as hormonal and fluid changes can worsen intracranial pressure. Conclusion The treatment of intracranial hypertension requires a mix of lifestyle changes, medicines, and sometimes surgery. Tailoring treatment to the cause and symptom severity offers the best results. With early diagnosis and teamwork, many patients can find relief and avoid the serious effects of uncontrolled pressure. [Next: Complications of Intracranial Hypertension →]

Treatment of Intracranial Hypertension Read More »

MRI brain scan showing highlighted pressure area with medical pointer

Complications of Intracranial Hypertension

If left untreated or poorly managed, intracranial hypertension can cause many complications. Some of these can be permanent and life-threatening. The complications of intracranial hypertension depend on the cause, how fast it develops, and how well it is treated. While idiopathic cases may stay stable or get better with lifestyle and medical care, progressive or secondary types have a much higher risk of long-term damage. Understanding these complications helps with early detection, active management, and stopping permanent harm. Vision Loss Due to Intracranial Hypertension One of the most serious complications is permanent vision loss. Increased pressure inside the skull squeezes the optic nerves, causing swelling called papilloedema. If this swelling is not treated, it damages the nerve fibres that control vision. This leads to worsening vision loss, blurry sight, and eventually complete blindness in one or both eyes. This problem is common in idiopathic intracranial hypertension (IIH) and often happens slowly, so patients may not notice the decline until it is too late. Vision damage from papilloedema is usually permanent once the nerves are badly harmed, which makes early diagnosis and strong treatment critical. Chronic Headaches and Their Impact Chronic, painful headaches are another serious issue. Headaches are a main symptom of intracranial hypertension, but they can get worse and harder to treat if the pressure stays high. These headaches greatly affect quality of life. They can cause sleep problems, poor focus, and limit work or social activities. Patients may depend on painkillers, risking medication-overuse headaches. This cycle makes pain worse and limits treatment options. Neurological Problems from High Pressure In severe cases, high pressure can harm brain function. It may reduce blood flow to important brain areas, causing problems like memory loss, slow thinking, and trouble concentrating. Patients may also suffer from mood problems like anxiety and depression because of their condition. If the pressure remains high for a long time, serious symptoms such as confusion, altered awareness, or loss of consciousness can occur. These signs need emergency treatment as they show serious brain damage. Brain Herniation: A Life-Threatening Risk Brain herniation is a deadly complication of intracranial hypertension. This happens when pressure forces brain tissue to move from its normal place, pushing on vital areas like the brainstem. Brain herniation causes fast loss of consciousness, abnormal pupil reactions, loss of breathing control, and death if not treated quickly. Though rare, it is more likely in acute cases caused by trauma, tumors, or bleeding. This danger highlights the need for quick pressure control in hospitals and clinics. Shunt Malfunction After Surgery Surgical treatments like ventriculoperitoneal (VP) or lumboperitoneal (LP) shunts help reduce pressure but can have problems. Shunts may get blocked, infected, or drain too much cerebrospinal fluid. Shunt failure causes symptoms to return quickly and often requires more surgery. This happens especially in children or patients with long-term IIH. Overdrainage can cause low pressure inside the skull, leading to severe headaches and brain sagging. Risks of Optic Nerve Sheath Fenestration Patients who get optic nerve sheath fenestration (ONSF) to save vision face risks too. Possible issues include bleeding, infection, and damage to eye structures. While ONSF can protect sight, it does not fix the root cause of pressure and often needs other treatments to control pressure long term. Venous Sinus Stenting Complications Venous sinus stenting is a newer treatment for IIH with blocked venous flow. Risks include vein injury, stent moving out of place, or blood clots. Though rare, these problems require close monitoring. Doctors must carefully weigh the benefits and risks before choosing this option, especially in borderline cases. Psychological Effects of Intracranial Hypertension An often overlooked complication is the heavy mental strain it causes. Living with symptoms like vision problems, ringing ears, and pain can lead to depression, anxiety, and social withdrawal. Patients may stop doing activities they once enjoyed, feel low self-worth, or believe others don’t understand their “invisible” illness. These emotional struggles can be as hard as the physical problems and usually need counseling or mental health support as part of care. Impact on Children’s Development In children, high intracranial pressure can harm brain growth. This may cause learning difficulties, movement delays, and behaviour problems. Detecting these problems early in kids is very important because symptoms may be unclear or missed. Risk of Recurrence After Treatment Even after successful treatment through lifestyle changes, medicines, or surgery, intracranial hypertension can come back. Recurrences may happen due to weight gain, hormone changes (especially in women), or stopping medication. Each new episode carries the same risks as before, such as vision loss and brain problems. Long-term follow-up with regular vision tests, imaging, and symptom checks is necessary. Additional Risks in Secondary Intracranial Hypertension When intracranial hypertension comes from infection, injury, or cancer, extra complications may occur. For example, brain tumors can cause seizures or weakness depending on their location. Infections like meningitis may bring serious problems like septic shock or organ failure alongside high pressure. Pregnancy-Related Concerns Women of childbearing age face special risks during pregnancy. Although IIH usually does not harm the baby, the extra strain can worsen symptoms. Managing pressure during pregnancy needs careful drug choices and teamwork between neurologists, obstetricians, and eye doctors. Without good care, both mother and baby may have complications. Summary The complications of intracranial hypertension cover a wide range and can be very serious. They affect vision, brain function, mental health, and even survival. Permanent blindness, brain herniation, chronic pain, and emotional distress are only a few examples. Surgery helps but has risks, and pressure can come back after treatment. Early diagnosis, regular check-ups, and a team approach to care can reduce or prevent many problems. Patients and doctors must stay alert to achieve the best results.

Complications of Intracranial Hypertension Read More »

Anxious woman lying awake in bed at night, staring at the ceiling

Overview of Insomnia

Insomnia is a widespread sleep disorder affecting millions globally. It causes persistent trouble falling asleep, staying asleep, or waking too early without the ability to return to sleep. Even when people have enough time to rest, insomnia prevents them from feeling refreshed, leading to fatigue, irritability, and difficulty functioning during the day. While occasional sleeplessness is normal, chronic insomnia requires medical help and treatment to avoid serious long-term health effects. Insomnia is not just one condition but a complex disorder with varied symptoms. Some people lie awake for hours before falling asleep, others wake often during the night, or feel their sleep isn’t deep or restorative. It usually develops gradually, starting with a few poor nights and becoming a chronic problem that harms both mental and physical health. Sleep is essential for life, and ongoing disruption affects nearly every body system. There are two main types: Insomnia is also classified by duration: Age and gender influence insomnia. It is more common in older adults due to changes in sleep patterns, more health problems, and medication use. Women experience higher rates, especially during hormonal changes in pregnancy, perimenopause, and menopause. Children and teens also face growing insomnia rates linked to academic pressure, screen time, and anxiety. Insomnia significantly impacts mental health. It’s strongly linked to depression and anxiety, disrupting brain chemicals and emotional recovery. Poor sleep worsens mood disorders, creating a cycle of distress. Early treatment can prevent this decline. Physiologically, chronic insomnia weakens immune function, raises inflammation, and increases stress hormones like cortisol. It heightens risks for high blood pressure, diabetes, heart disease, and obesity. Sleep is vital for cell repair and metabolism; without it, overall health deteriorates. Cognitive functions such as concentration, memory, and decision-making also suffer. On a societal level, insomnia contributes to accidents, injuries, and lost productivity. Sleep deprivation slows reactions, impairs judgement, and affects mood, reducing effectiveness at work and home. Employers and health systems now recognise insomnia as a serious public health concern. Modern lifestyles and technology have increased insomnia worldwide. Evening exposure to smartphones and computers emits blue light, which disrupts melatonin and circadian rhythms. Irregular schedules, long work hours, and stress further disturb sleep cycles, especially among young adults and city dwellers. Despite its prevalence, many do not seek help, underestimating insomnia’s severity or expecting it to improve alone. This often leads to harmful coping habits like excess caffeine, alcohol, or daytime naps, worsening the problem. Untreated insomnia can become deeply rooted and harder to fix. The positive news is insomnia is treatable. Current approaches focus on identifying causes and promoting healthy sleep habits. Cognitive Behavioural Therapy for Insomnia (CBT-I) is the best long-term treatment, offering lasting benefits without medication side effects. Drugs are available but usually reserved for short-term or specific cases due to risks like dependency. In summary, insomnia is a multifaceted condition affecting mind, body, and life quality. It often requires a mix of behavioural and medical treatment to overcome. With awareness, early diagnosis, and personalised care, most people can improve their sleep and health. As research advances, so will support for those challenged by insomnia. [Next: Causes of Insomnia →]

Overview of Insomnia Read More »

Tired man lying awake in bed at night with a fatigued expression

Causes of Insomnia

Insomnia is a complex condition with many possible causes, including biological, psychological, environmental, and behavioural factors. Understanding the causes of insomnia is key to diagnosis and treatment. Usually, it is not caused by just one thing. Instead, several issues combine to stop the body from falling or staying asleep. Short-term insomnia may happen due to temporary stress or lifestyle changes, while long-term insomnia often has deeper causes. Stress and Mental Health The most common cause of insomnia is stress. Daily worries about work, school, money, or relationships can cause the mind to race at night. This mental alertness makes it hard to relax and fall asleep. Even after the stress passes, the body may stay on high alert at bedtime, keeping sleep problems going. People prone to anxiety or perfectionism often find stress triggers insomnia. Mental health disorders also play a big role. Anxiety, including generalised anxiety disorder (GAD), panic disorder, and PTSD, often cause sleep problems. People with anxiety struggle to stop worrying enough to sleep, and their sleep is usually light and broken. Depression can cause early waking or too much sleep, both linked to imbalanced sleep patterns. Sometimes insomnia causes mental health issues, or mental health problems cause insomnia—they often worsen each other. Medical Conditions Medical problems frequently cause insomnia. Chronic pain from arthritis, fibromyalgia, migraines, or back pain makes it hard to get comfortable. Breathing problems like asthma or COPD can cause coughing or shortness of breath at night. Acid reflux, heart failure, and brain diseases such as Parkinson’s or Alzheimer’s also disturb sleep. Other less obvious issues, like overactive bladder, thyroid problems, or allergies, may cause frequent awakenings or discomfort. Medications and Substances Many medications affect sleep. Antidepressants, corticosteroids, beta-blockers, and some blood pressure drugs can interfere with sleep. Stimulants for ADHD delay falling asleep. Caffeine and nicotine also keep people awake. Alcohol may help people fall asleep at first, but it breaks up sleep later in the night and lowers sleep quality. Poor Sleep Habits Bad sleep habits often cause insomnia. Irregular bedtimes, doing exciting activities before bed, or using screens in bed can hurt sleep. Blue light from phones or computers stops the body from making melatonin, the sleep hormone. Sleeping and waking at different times daily, napping too much, or using the bedroom for work or TV weakens the brain’s link between the bedroom and sleep, making it harder to fall asleep. Circadian Rhythm Issues Disruptions to the body’s internal clock also cause insomnia. This clock controls when we feel sleepy or awake and depends on light and meal times. Shift work, jet lag, and irregular sleep schedules often cause insomnia. Shift workers sleep during the day and work at night, which goes against their natural rhythm. Teens and young adults sometimes have delayed sleep phase syndrome, meaning they feel like sleeping and waking later than usual, causing sleep loss on school or workdays. Hormonal Changes Hormone shifts affect sleep, especially in women. Menstruation, pregnancy, and menopause bring changes that disrupt rest. Hot flashes and night sweats in menopause cause repeated waking. Pregnancy brings discomfort from weight gain, pain, or baby movements. Hormones also change brain chemicals that control sleep, making it harder to fall or stay asleep. Environmental Factors The sleep environment impacts insomnia more than many realise. Noise, light, temperature, and an uncomfortable bed all reduce sleep quality. City dwellers face noise, street lights, and temperature changes from heating or air conditioning. Creating a quiet, dark, and cool bedroom helps promote good sleep. Sleep-Related Disorders Some disorders mimic insomnia. Restless legs syndrome (RLS) causes an urge to move legs with unpleasant feelings at night. Obstructive sleep apnea (OSA) leads to breathing stops during sleep, causing repeated waking without memory of it. Treating these problems is key to restoring good sleep. Age and Genetics Sleep changes with age. Older adults sleep lighter, wake earlier, and have less deep sleep. They also take more medications and often have medical issues, making sleep worse. While some sleep decline is normal with age, persistent insomnia needs attention. Genetics can also play a role. Some people inherit a higher chance of insomnia. Though genes alone don’t cause it, they combine with lifestyle and environment to increase risk. Summary In summary, insomnia has many causes, and each person’s reasons are different. Stress, mental health, medical issues, habits, environment, and biology all affect sleep. Careful evaluation of these factors helps create the best treatment plan. By tackling the root causes, people with insomnia can regain control of their sleep and enjoy a healthier, more energized life. [Next: Symptoms of Insomnia →]

Causes of Insomnia Read More »

Scroll to Top