Mental Matters

Health & Wellness

Complications of Krabbe Disease

Complications of Krabbe Disease

Complications of Krabbe disease often arise as the condition progresses, profoundly impacting both the individual’s quality of life and the overall course of the illness. Because Krabbe disease is a rare, inherited neurodegenerative disorder, it causes damage to the protective myelin sheath surrounding nerve cells in the brain and throughout the nervous system. As a result, the complications of Krabbe disease affect a wide range of bodily functions, often leading to severe physical, neurological, and developmental consequences. One of the earliest and most distressing complications is developmental regression. Infants who initially meet early milestones—such as smiling, holding up their heads, or cooing—may begin to lose these abilities as the disease advances. This loss usually cannot be reversed and may happen quickly. For parents, watching their child lose skills is very painful. Therefore, emotional support and counselling are vital alongside medical care. Muscle Weakness and Feeding Issues Severe muscle weakness and stiff muscles (spasticity) are common problems. As the disease harms motor nerves, patients lose control of their muscles. This leads to tight muscles, stiffness, and painful spasms. Many affected individuals eventually become unable to move and need wheelchairs or full-time care, especially in infantile cases. Feeding and swallowing difficulties also occur often. These problems can cause poor nutrition, dehydration, and a serious lung infection called aspiration pneumonia. Many children with Krabbe disease need feeding tubes to get enough food safely. This method can increase the risk of infections and requires careful care. Breathing Problems and Seizures Respiratory problems are among the most dangerous complications of Krabbe disease. Weak breathing muscles make it hard for patients to breathe well. They are more likely to get chest infections. Pneumonia often causes hospital stays and is a leading cause of death. Poor muscle control also reduces the body’s ability to clear mucus, raising the risk of blocked airways. Seizures happen frequently as the disease worsens. These seizures range from short staring spells to full convulsions and can occur many times a day. Some patients develop epilepsy that does not respond well to medication. Managing seizures in Krabbe disease takes careful balancing of medicines and close monitoring. Sensory Loss and Cognitive Decline The complications of Krabbe disease also include loss of senses. Many children lose their vision and hearing early on. This loss causes isolation and makes communication very hard, especially for those who cannot speak yet. Hearing loss can become complete, and vision may fade to total blindness. This makes assistive devices and special therapies necessary. Cognitive decline is another major concern. Early treatment with stem cell transplant may protect some brain function in patients without symptoms yet. However, most children suffer worsening mental ability. As the brain’s white matter breaks down, memory, attention, learning, and language skills fade. Older patients may show signs like confusion, personality changes, and memory loss that resemble dementia. Orthopaedic and Incontinence Issues Children with advanced disease often face bone and muscle problems because of long immobility and uneven muscle strength. These include joint stiffness (contractures), curved spine (scoliosis), hip dislocation, and weak bones. While physiotherapy and braces can help, the disease usually causes worsening problems despite treatment. Incontinence is common as patients lose bladder and bowel control. They may need diapers or catheters. This loss of independence affects hygiene and skin health. It also adds emotional stress to both patients and caregivers. Ensuring comfort and dignity is an important goal in long-term care. Communication Loss and Life Expectancy In later stages, many patients cannot speak, gesture, or respond to others. This situation is very hard for families emotionally. Early in the disease, alternative communication tools—like eye-tracking devices or picture boards—may help. However, these aids often lose effectiveness as the disease advances. One of the most tragic complications of Krabbe disease is shortened life expectancy. Infantile Krabbe disease usually leads to death by age two or three, though some live longer with intensive care. Juvenile and adult forms progress more slowly but still shorten life and cause severe disability. For these patients, problems build up over time, reducing quality of life and independence. Emotional and Financial Burden Besides medical issues, complications of Krabbe disease cause heavy emotional and financial stress. Caregivers often stop working to provide full-time care, which lowers household income and strains relationships. Medical equipment, medicines, therapies, and travel to specialist centres can be very expensive. Many caregivers face exhaustion, anxiety, depression, and burnout. Support groups and mental health services are essential. Palliative care becomes vital as the disease advances. It aims to relieve suffering, keep the patient comfortable, and support families through the emotional challenges. Palliative teams help manage pain, breathing troubles, and distressing symptoms. They also guide end-of-life decisions and provide grief counselling. Early diagnosis and treatment, especially with stem cell transplants, can delay or reduce some complications. This makes newborn screening programs very important. Detecting Krabbe disease before symptoms appear gives the best chance to improve outcomes and lessen long-term problems. In conclusion, the complications of Krabbe disease affect nearly every body system and cause severe physical and emotional hardship. From muscle weakness and seizures to breathing failure and mental decline, the disease creates ongoing challenges. Yet, with early care, teamwork among specialists, and supportive therapies, some patients may enjoy better quality of life and longer survival. Families need compassionate care, clear information, and emotional support as they face this difficult journey. [Next: Back to Overview →]


Complications of Krabbe Disease Read More »

Overview of Knocked-Out Tooth

Overview of Knocked-Out Tooth

A knocked-out tooth is a dental emergency that occurs when a tooth is completely displaced from its socket due to trauma or injury. Whether it results from a sports accident, fall, or unexpected blow to the face, a knocked-out tooth can be both physically painful and emotionally distressing. Prompt action can make the difference between saving the tooth and losing it permanently, making it essential for individuals to understand the importance of timely care, proper handling, and immediate intervention. When a tooth gets knocked out—called avulsion—the surrounding nerves, blood vessels, and ligaments tear away. This breaks the natural connection between the tooth and jaw, leaving the root exposed and vulnerable to damage. Unlike a chipped tooth, which stays in the mouth, a knocked-out tooth ends up outside the body—on the ground or in another object. This injury happens in all age groups but is most common in children and teens involved in sports or rough play. Time-Sensitive Care for a Knocked-Out Tooth Time is critical. A knocked-out tooth must return to its socket as soon as possible. The ideal window is within 30 minutes to one hour. The faster this happens, the better the chance of the tooth surviving. Until reimplantation, the tooth must stay moist. Milk, saline, or even saliva can keep the cells alive and protect the delicate ligament that helps it reattach. Two types of teeth can be knocked out: adult (permanent) and baby (primary) teeth. Treatment depends on which one it is. Dentists will usually try to reimplant permanent teeth. However, reimplanting baby teeth is not advised, as it might harm the growing permanent teeth underneath. This difference makes it important to know which type of tooth has been lost, especially in young children. Long-Term Effects of a Knocked-Out Tooth A missing tooth does more than change a smile. It can hurt self-esteem, especially when the tooth is near the front. The empty space can also affect speech, chewing, and bite alignment. Over time, nearby teeth may shift into the gap, leading to more dental problems. If reimplantation fails or isn’t possible, several options exist. Dental implants, bridges, and partial dentures can fill the space. While these work well, they can be expensive and emotionally draining. Preventative steps—like mouthguards for sports, helmets, and safe environments—can lower the risk of losing a tooth. Risk Factors and Community Awareness Besides accidents, some health issues increase the risk of a knocked-out tooth. For example, gum disease can weaken tooth support, making it easier for a tooth to dislodge. People with braces may also face higher risk, as teeth may be looser during movement. Being aware of these risks and working with a dentist can help prevent serious problems. Education is key. Schools, sports teams, and community centers should teach people what to do when a tooth gets knocked out. Knowing to handle the tooth by the crown (not the root), rinse it gently without scrubbing, and get to a dentist quickly can save a tooth. Future Outlook for Knocked-Out Tooth Treatment Even with fast and proper care, not every knocked-out tooth can be saved. Several factors affect the outcome—how the tooth was handled, time outside the mouth, socket condition, and the person’s dental health. In some cases, reimplanted teeth fail to reattach or develop infections. These may need more treatment or removal later. New treatments are under study. Regenerative dentistry uses stem cells, growth factors, and special materials to rebuild damaged tooth tissue. While still experimental, this research offers hope for better results in the future. Aftercare also matters. Dentists monitor reimplanted teeth with X-rays and checkups to spot problems early. One risk is root resorption, where the body slowly breaks down the tooth root. This can happen months or years later, so follow-up is vital. Children and teens with a knocked-out tooth might also need emotional support. Losing a tooth can hurt their confidence and affect how they interact with others. Encouraging open discussion and replacing the tooth quickly can help them adjust and feel better. In summary, a knocked-out tooth is a serious dental emergency that requires immediate attention. Whether it results from a sporting mishap, a playground accident, or a simple fall, the clock starts ticking the moment the tooth leaves the socket. Proper handling, preservation, and professional dental care can dramatically improve the chances of saving the tooth and restoring normal oral function. Beyond the physical consequences, the event can impact self-esteem, emotional health, and financial resources. By understanding the importance of prompt action and prevention, individuals and communities can be better prepared to handle such emergencies with confidence and care. [Next: Causes of Knocked-Out Tooth →]

Overview of Knocked-Out Tooth Read More »

Causes of Knocked-Out Tooth

Causes of Knocked-Out Tooth

A knocked-out tooth is most commonly caused by sudden physical trauma, but there are a variety of other contributing factors that can increase the risk of tooth avulsion. While a knocked-out tooth may happen in an instant, there are many ways it can occur. Some causes are sudden, like a fall or impact. Others develop over time, such as poor dental health. Knowing the causes of knocked-out tooth injuries helps prevent them and prepares people to respond quickly. 1. Sporting Injuries Sports injuries are the top cause of knocked-out teeth in kids and adults. Contact sports like rugby, hockey, and boxing carry high risk. Even non-contact sports such as skateboarding or cycling can lead to falls or crashes. These impacts often strike the face, pushing teeth out of the socket. Athletes who skip mouthguards are much more likely to lose a tooth. A strong blow during play, especially to the front teeth, can knock them out completely. 2. Accidental Falls Falls are another major cause, especially in children and older adults. Young kids fall when they run, jump, or climb. Their balance is still developing, which makes them more likely to get hurt. Older adults may have weak bones or poor balance, making them prone to falls. When someone falls onto a hard surface—especially with their mouth open—the impact can knock out a tooth easily. 3. Motor Vehicle Accidents Car crashes often cause serious injuries, and dental trauma is common. A person’s head can hit the steering wheel, dashboard, or airbag during a crash. Even with safety gear, the force can be strong enough to knock out teeth. High-speed crashes and rollovers make this even more likely. Dental injuries often happen alongside cuts, bruises, and broken bones. 4. Physical Violence or Assault Sadly, violence is another cause of knocked-out teeth. Fights, assaults, or abuse that involve punches or kicks to the face can knock out a tooth. These injuries often come with cuts, bruises, or broken facial bones. Victims of domestic violence or mugging are especially at risk. In such cases, both medical and dental care are needed quickly. 5. Risks at Work Jobs in construction, factories, or workshops often carry a higher risk of dental injury. Falling tools, flying objects, or equipment failure can all lead to trauma. Workers who slip or get hit in the face may suffer tooth avulsion. Wearing safety gear like helmets or face shields can lower the risk on the job. Common Everyday Causes of Knocked-Out Tooth Some causes of tooth loss come from daily activities. As new transport methods and play styles become popular, risks increase. 6. Bike or Scooter Crashes With more people riding bikes and e-scooters, crashes are becoming more common. When riders fall or hit something, their face often hits the ground. If they aren’t wearing helmets, the chance of tooth injury goes up. Falling on the pavement or being hit by a handlebar can knock out a tooth on impact. 7. Dental Problems and Weak Teeth Poor dental health makes teeth easier to knock out. Gum disease, bone loss, and deep cavities weaken the tooth’s support. In these cases, even a minor bump might cause the tooth to fall out. Infections and decay also loosen teeth over time. Without care, they may come out on their own or from mild trauma. 8. Braces and Orthodontic Treatment Braces slowly shift teeth, which can make them feel loose. This is normal during treatment, but it also makes teeth easier to knock out. People with braces should wear a mouthguard during sports or rough play. That helps protect both the tooth and the hardware. 9. Teeth Grinding (Bruxism) Grinding teeth at night wears down the tooth and its support system. Over time, this makes it easier for a tooth to be knocked out. Bruxism alone may not cause avulsion, but it increases the risk when another injury occurs. Mouthguards or stress reduction can help manage this condition and protect the teeth. Less Common But Important Causes of Knocked-Out Tooth Other health issues and habits may also raise the risk, even if they are less obvious. 10. Genetic or Bone Conditions Some people have dental traits that raise their risk. Thin roots or fragile bones, whether from birth or health problems like Ehlers-Danlos or osteogenesis imperfecta, make teeth more vulnerable. In these cases, even a small hit may cause a tooth to fall out. These people need extra dental care and protection during activity. 11. Poor Oral Hygiene and Diet Not brushing and flossing well allows plaque to build up. Over time, this leads to gum disease and weakens the teeth. A lack of vitamins like calcium and vitamin D also harms the bones. These conditions don’t knock out teeth right away but make the teeth easier to dislodge later. 12. Playground Injuries and Rough Play Children playing on slides, swings, or trampolines can fall or bump into others. These playful settings often lead to face injuries. Even a simple collision during a game can be enough to cause a tooth avulsion in kids. Parents should watch children during rough play and consider mouthguards for contact-heavy activities. Understanding the causes of a knocked-out tooth is vital for both prevention and early response. While it may not always be possible to avoid sudden accidents, adopting practical safety measures—such as wearing mouthguards, ensuring proper dental care, and using protective equipment—can drastically reduce the likelihood of experiencing this painful and often costly dental emergency. Being aware of the risk factors and high-risk situations empowers individuals and families to act proactively and protect their oral health in everyday life. [Next: Symptoms of Knocked-Out Tooth →]

Causes of Knocked-Out Tooth Read More »

Symptoms of Knocked-Out Tooth

Symptoms of Knocked-Out Tooth

A knocked-out tooth is a clear and sudden dental emergency that presents with a number of immediate and follow-up symptoms. Noticing the symptoms of knocked-out tooth injuries early helps with faster treatment and better results. The most obvious sign is the missing tooth, but many other symptoms show up too. These signs often point to damage around the area and a need for urgent dental help. The signs can include pain, bleeding, swelling, and injury to the soft tissues. Sometimes, these symptoms grow worse over time, especially if there’s an infection or bone damage. Whether the tooth is partly out or fully gone, knowing the symptoms quickly helps avoid more problems. 1. Obvious Missing Tooth The most visible symptom is the sudden gap where the tooth used to be. This is easy to notice, especially if a front tooth is lost. The area often bleeds and may show soft tissue or root fragments. The gap might also feel sharp or rough because nearby teeth no longer offer support. 2. Strong Pain in the Area A knocked-out tooth usually causes strong, sharp pain right away. The pain gets worse if you touch the area, breathe through your mouth, or drink something cold. Nerves inside the gum and socket become exposed when the tooth comes out. This pain can spread to the jaw or sinuses and may last for hours. 3. Bleeding That Keeps Coming Bleeding is very common after a tooth is knocked out. Blood vessels in the socket break, which causes steady bleeding. Pressure can slow it down, but if it continues for too long, it might mean deeper damage. Sometimes the bleeding starts again later, especially if the person talks, eats, or brushes near the area. 4. Swelling and Bruises Soon after the injury, the gum and nearby skin may start to swell. The body sends blood to the area to protect and heal it. In more serious cases, bruises can appear on the gums, cheeks, or lips. This often happens after a fall or blow to the face. The swelling can also make it hard to close the mouth or speak clearly. Symptoms of Knocked-Out Tooth Can Include Partial Avulsion Not every injury knocks the tooth out completely. Sometimes it stays partly in place but feels loose or tilted. This is called partial avulsion. The tooth might still be connected by nerves or tissue. Moving the tooth on your own can cause more harm. In these cases, pain comes and goes and is often worse when biting or chewing. 6. Cuts and Soft Tissue Injuries Often, a knocked-out tooth comes with cuts on the lips, tongue, or gums. The impact that removes the tooth can tear soft tissue. These cuts bleed and sting. They also make it harder to keep the area clean. If the injury came from a hard object, like pavement or sports gear, the damage may be worse. These cuts can get infected if not treated properly. 7. Numbness or Tingling Some people feel numbness or tingling in the mouth or jaw after the injury. This could be from shock, nerve pressure, or nerve damage. While short-term numbness can go away on its own, if it lasts, it may mean a deeper nerve problem. Any ongoing numbness in the lips, chin, or tongue needs a dental check. 8. Headaches or Pain Beyond the Mouth Sometimes, the pain spreads. It might move to the jaw, temples, or ears. This is more common after major trauma, like a car crash or sports hit. Headaches may also come from tension or stress. If pain spreads, doctors may need to check for more serious problems like concussion or jaw fractures. 9. Trouble Talking or Chewing Losing a tooth makes it harder to speak and eat. The bite pattern changes, and chewing becomes tricky. Speaking clearly can also be hard, especially if a front tooth is gone. Until the tooth is treated or replaced, these problems may continue. Late Symptoms of Knocked-Out Tooth If the area isn’t kept clean, infection may set in. This can cause a bad taste or smell in the mouth. It might happen a few days after the injury. Other signs of infection include pus, fever, or swelling that gets worse. These symptoms need quick treatment. Following care steps and keeping the mouth clean helps avoid them. 11. Emotional Effects A missing tooth can affect more than just the body. It often causes emotional distress, especially when it’s a front tooth. People may feel shy, embarrassed, or lose confidence. Kids and teens might feel upset or withdrawn. These feelings are real and should not be ignored. Cosmetic dental care may help restore both the smile and confidence. Recognising the symptoms of a knocked-out tooth is vital for timely and effective management. From visible bleeding and intense pain to subtle numbness and swelling, the signs of this dental emergency often appear quickly and demand immediate action. Being informed about these symptoms allows individuals and caregivers to respond promptly, improve the chances of successful reimplantation, and reduce the risk of infection or long-term damage. [Next: Diagnosis of Knocked-Out Tooth →]

Symptoms of Knocked-Out Tooth Read More »

Diagnosis of Knocked-Out Tooth

Diagnosis of Knocked-Out Tooth

A prompt and accurate diagnosis of knocked-out tooth injuries is critical in determining the best course of treatment and optimising outcomes. Dentists must act fast and make clear decisions. Quick action gives the best chance to put the tooth back in place and avoid long-term problems. The diagnosis of knocked-out tooth cases involves checking if the tooth is fully out and also looking at the condition of nearby tissues and other injuries. First Steps in Diagnosis of Knocked-Out Tooth The process starts with asking questions about the injury. Dentists want to know when and how it happened and how the tooth was handled and stored. Time is very important. A tooth should go back in within 30 to 60 minutes. After that, the living cells on the root start to die, which makes treatment harder and the outcome less certain. Next, the dentist looks inside the mouth. They check the empty socket carefully. Signs of bleeding, cuts, or broken bone are noted. They also make sure no parts of the tooth remain inside the gums. Swelling or cuts around the area help show how bad the injury is. If the tooth is brought in, it gets examined too. The dentist checks if the tooth is whole or broken. A key part of the diagnosis of knocked-out tooth cases is looking at the root. Any soft tissue still attached should stay in place. These fibres help the tooth reattach later. A tooth kept in milk, saline, or spit has a better chance of success than one left dry or cleaned with harsh products. Using X-Rays and Scans for Full Evaluation After the mouth and tooth are checked, X-rays help finish the diagnosis. Dentists may use periapical or panoramic X-rays to look at the bone and confirm the tooth is fully out. These images also help spot other problems like broken bone, tooth fragments left behind, or nearby teeth pushed into the jaw. In more serious cases, a cone-beam CT scan may be used for a clearer picture. If the injury involved a hard hit to the face or head, doctors may order more tests. These help rule out things like a concussion, jaw fracture, or neck injury. For children, dentists must find out if the tooth is a baby tooth or a permanent one. The diagnosis of knocked-out tooth in kids must be done with care. Putting a baby tooth back can damage the growing adult tooth underneath, so it is usually not done. Dentists also check the patient’s general health. If the tooth hit the ground or dirt, and the patient hasn’t had a tetanus shot recently, a booster may be needed. This step is part of caring for the whole patient, not just the mouth. Classifying and Planning Based on Diagnosis of Knocked-Out Tooth Once all the checks and images are done, the dentist confirms and records the diagnosis. They group the case by how much time has passed, how the tooth was stored, and the patient’s age and dental health. This helps them decide on the next step. They might choose to reimplant the tooth right away, plan for root treatment, or talk about long-term options. If putting the tooth back in is not possible, the diagnosis still guides what to do next. Dentists may suggest a space maintainer, braces to close the gap, or implants later after healing. The diagnosis also helps set the schedule for follow-up care. Regular X-rays help catch problems like root damage, tooth fusion, or infection. The dentist also considers how the injury affects the patient emotionally. This is especially true for kids and teens. The diagnosis phase is a good time to talk with the patient and their family. Offering support and honest advice helps reduce fear and keeps the patient willing to return for more care. Education and Best Practices in Diagnosis of Knocked-Out Tooth This step is also a chance to teach patients what to do if it happens again. Many people don’t know that a knocked-out tooth can often be saved. Teaching them to hold the tooth by the crown, not the root, and to store it in milk or spit, can make a huge difference. Giving simple, clear advice helps them respond better if it ever happens again. New dental guidelines, like those from the International Association of Dental Traumatology (IADT), give clear steps for handling dental injuries. These rules help dentists all over the world make better decisions and give the best care. To sum up, the diagnosis of knocked-out tooth injuries involves much more than spotting a missing tooth. Dentists take a full history, do a careful exam, use X-rays, and consider the patient’s overall health. The sooner and more thoroughly this is done, the better the result. A strong diagnosis leads to fast, effective care that keeps the patient’s mouth healthy and looking good in the long run. [Next: Treatment of Knocked-Out Tooth →]

Diagnosis of Knocked-Out Tooth Read More »

Treatment of Knocked-Out Tooth

Treatment of Knocked-Out Tooth

Treatment of Knocked-Out Tooth A successful treatment of knocked-out tooth injuries requires rapid, evidence-based action tailored to the condition of the tooth and the time elapsed since avulsion. The main goal of treatment of knocked-out tooth injuries is to put the tooth back in place and keep nearby tissues healthy. Acting quickly gives the tooth a better chance of survival and helps prevent later dental problems. Timing Matters Most in Treatment of Knocked-Out Tooth Time is the most important factor. Replacing the tooth within 15 to 60 minutes gives the best results. In clinics or hospitals, dentists try to put the tooth back right away if it’s clean and whole. Before doing that, they rinse it with saline or milk to get rid of dirt. They never scrub it, as that can damage the delicate cells on the root. The tooth is placed back in the socket with care, making sure it’s facing the right way. A dentist then uses a flexible splint to hold it in place with nearby teeth. This splint stays for about two weeks, giving the ligament time to heal and stick back to the bone. During this time, patients may get antibiotics to stop infections. Doctors also check tetanus shots, especially if the injury happened in a dirty place. Sometimes reimplantation cannot happen right away. If the tooth was left dry too long or kept in the wrong way, other steps are needed. The tooth might be soaked in fluoride solution first. This slows down damage to the root. But if the root is badly harmed or the area shows signs of infection, the dentist might suggest long-term options instead. Special Considerations for Baby and Adult Teeth Young children with baby teeth usually don’t get reimplantation. Putting a baby tooth back can hurt the growing adult tooth underneath. In these cases, the treatment of knocked-out tooth focuses on easing pain, stopping infection, and keeping the space open for adult teeth to come in correctly. For permanent teeth, a root canal is often needed after reimplantation. If the pulp inside the tooth dies, the dentist removes it to prevent more problems. The timing of the root canal depends on things like root development and how soon the tooth was reimplanted. Sometimes, the root canal is done as early as 7 to 10 days later to lower the risk of infection or root damage. If the tooth cannot be reimplanted or the attempt fails, long-term fixes are needed. These may include bridges, partial dentures, or dental implants. Teens usually get temporary fixes first. Later, when jaw growth finishes, they can get implants. These solutions help keep the mouth looking good and working well for eating and talking. Long-Term Support and Patient Education Supportive care plays a big role too. Patients should eat soft foods, clean their mouths well, and use an antibacterial mouth rinse like chlorhexidine to avoid infection. Follow-up visits help the dentist check how the tooth is healing. They also look for problems like tooth-to-bone fusion or root damage. In tough cases, like when many teeth are knocked out or the jawbone is broken, a team of experts may need to help. This may include oral surgeons and other dental specialists. They may use surgery, special scans, or detailed treatment planning. Working together helps protect both function and appearance. Teaching patients what to do is key. Many people don’t know that quick and proper action can save a knocked-out tooth. Families should learn to handle the tooth by the crown, not the root. They should store it in milk or saliva, not water. Dentists should always give clear first-aid tips for dental injuries, both in person and in writing. Prevention and Follow-Up in Treatment of Knocked-Out Tooth Preventing tooth injuries helps too. Wearing mouthguards during sports—especially rough ones like rugby or hockey—can protect teeth. For people with front teeth that stick out, braces or other dental work might help lower the risk of trauma. These steps reduce the number of cases and make treatment of knocked-out tooth easier in the future. Ongoing care is just as important. Even if the tooth heals well at first, patients must return for regular check-ups. These may include exams, X-rays, and tests to see if the tooth pulp is still alive. Any later problems, like root damage or changes in the pulp, need quick attention. The final result depends not only on the first treatment but also on good long-term care. Dental groups like the International Association of Dental Traumatology (IADT) offer clear rules for how to handle these cases. Their guides help dentists act fast and follow proven steps to get the best outcome. In short, the treatment of knocked-out tooth cases needs fast action and careful planning. It includes first steps like putting the tooth back, using splints, and giving antibiotics. Later steps involve root canal treatment, possible tooth replacement, and regular check-ups. When handled properly, many knocked-out teeth can be saved and work well for years. [Next: Complications of Knocked-Out Tooth →]

Treatment of Knocked-Out Tooth Read More »

Knocked-Out Tooth

Complications of Knocked-Out Tooth

The complications of knocked-out tooth injuries can vary significantly depending on the immediacy and quality of treatment provided after the initial trauma. Early reimplantation and proper handling greatly reduce the risk of long-term problems. But even with good care, the complications of knocked-out tooth situations can still create serious problems for dental health and function. Root Resorption and Tooth Damage The most common complication is root resorption. This happens when the body breaks down the tooth’s root because of injury or swelling. There are two main types. Inflammatory resorption often occurs with infection. Replacement resorption, or ankylosis, causes the tooth to fuse with the bone and lose its natural movement. Both types put the long-term survival of the tooth at risk, especially if diagnosis is delayed. Another issue is damage from infection. If the tooth was not cleaned well before reimplanting, or the supporting tissue was harmed, bacteria may enter. This can cause the inner pulp to die. A root canal may be needed, and if not treated, infection can spread to nearby teeth or bone. Gum and Soft Tissue Concerns Gum injuries are also a concern. During trauma or when the tooth is placed back, the soft tissue can get cut, bruised, or pushed out of place. If the tissue doesn’t heal well, gum recession may happen. This leaves the root exposed and can lead to decay. Poor healing can also affect how the gums look, especially on front teeth. Tooth discoloration is another problem. A reimplanted tooth may become darker over time. This often happens if the pulp dies or if bleeding occurred inside the tooth. Even though it may still be usable, dark teeth often need cosmetic help like bleaching or veneers. Jaw Growth and Development Issues In children and teens, a bigger problem can be how it affects jaw growth. If a tooth is lost or fuses too early, it can stop the normal development of the jaw. This may lead to a sunken face or crooked nearby teeth. Tooth loss in kids can also affect chewing, speaking, and confidence. When Reimplantation Fails Sometimes the tooth does not reattach well. This failure can happen if the tooth was kept dry too long, stored wrong, or handled poorly. When this happens, the person may need a fake tooth like a bridge, denture, or implant. These treatments work well but cost more, take longer, and may not suit young patients. Emotional and Social Impact The emotional effects can be strong, too. Losing a front tooth from injury can hurt a person’s confidence. Children may feel shy or stop smiling. Teens might avoid social events or struggle at school. Even adults may find that it affects work or relationships. Pain, Sensitivity, and Healing Trouble Some people have long-term pain or sensitivity. This might happen from nerve injury, poor alignment, or swelling. Pain can show up during chewing, with hot or cold foods, or without a reason. In some cases, the tooth must be removed and replaced. If the tooth becomes loose again after treatment, that is also a problem. This can happen if the splint is not done right or if the person bites down too hard too soon. Loose teeth do not heal well and are at risk of damage again. That’s why patients must follow advice on food, brushing, and follow-up visits. Less Common But Serious Problems Other problems include sinus issues with upper teeth, reactions to splinting tools, or allergies to antibiotics or numbing agents. These problems can delay recovery and need extra care. The complications of knocked-out tooth also include bite changes over time. As nearby teeth move, bite problems and jaw pain may begin. TMJ issues may also develop. Preventing these changes needs regular checks, dental advice, and fast replacement of missing teeth. Financial Stress and Costs Money issues are also a hidden problem. Even with insurance, emergency visits, x-rays, follow-ups, root canals, and replacements can cost a lot. This stress increases if many teeth are hurt or long-term care is needed. Importance of Fast and Proper Care In summary, the complications of knocked-out tooth range from minor local issues to bigger problems like pain, bite changes, and emotional stress. The best outcomes happen with quick treatment, the right steps, and long-term care. Not every lost tooth can be saved. But knowing what can go wrong helps patients and dentists make smart choices that protect health and smiles. [Next: Back to Overview →]

Complications of Knocked-Out Tooth Read More »

Overview of Knock Knees

Overview of Knock Knees

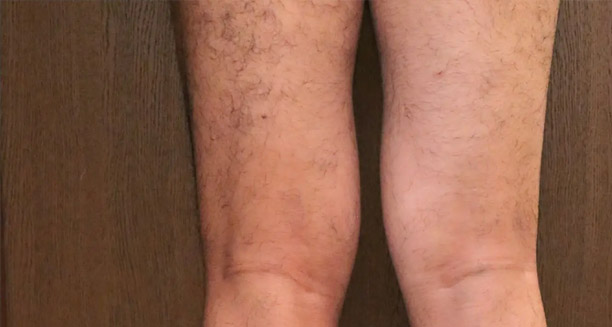
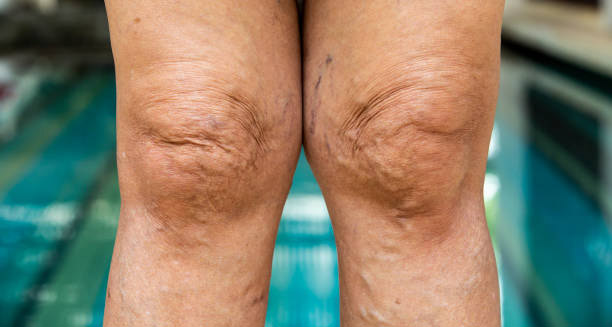
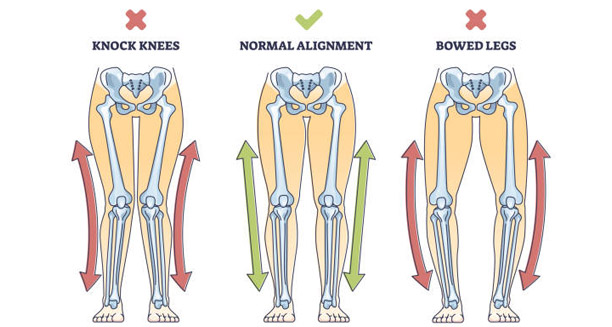
Knock knees is a condition where the knees angle inward and touch each other when the legs are straight. People with knock knees often show a noticeable gap between their ankles when standing with their knees together. Medically, this is called genu valgum. This alignment issue is common in young children and usually corrects itself as they grow. However, when knock knees persist into adolescence or adulthood, it may signal an underlying problem or imbalance needing medical care. The term “knock knees” describes a musculoskeletal deviation where the thigh bone (femur) angles inward, causing the knees to meet even when feet are apart. Mild cases often cause no harm and improve naturally. But severe cases can cause pain, limit movement, and strain joints. Sometimes both legs are equally affected. Other times, one leg shows worse knock knees, causing uneven walking and issues in the hips or spine. Overview of Knock Knees: Development and Impact In early childhood, knock knees are usually part of normal bone growth. Between ages two and five, many children go through a phase of genu valgum. This phase helps position joints properly and supports balance while learning to walk and run. Most children’s legs straighten by age seven or eight. If knock knees continue past this age or appear suddenly in older kids or adults, they may indicate conditions like bone diseases, injury, obesity, or genetic disorders. Understanding the overview of knock knees helps not just with clinical care but also with emotional support. Even when no physical symptoms exist, visible leg differences can lower confidence and cause social discomfort, especially in teens. Untreated knock knees may increase risks for arthritis, unstable knees, or chronic pain later on. Overview of Knock Knees: Types and Diagnosis There are two main forms of knock knees: physiological and pathological. Physiological knock knees occur naturally during growth and usually need no treatment. Pathological knock knees come from abnormal growth, illness, injury, or genetic issues and may require medical evaluation. Doctors assess knock knees by observing leg alignment and considering factors like age, growth patterns, and medical history. In adults, pain or difficulty walking can lead to further tests such as X-rays or MRIs. These help check bone shape, joint damage, and soft tissue problems like muscle weakness or loose ligaments. When knock knees persist or cause functional problems, treatments range from physical therapy and braces to weight management and surgery. Treatment aims to improve joint use, ease pain, and prevent future joint damage—not just fix the appearance. Overview of Knock Knees: Biomechanics and Public Health Biomechanically, knock knees change how weight and pressure spread across the knee joint. This uneven load can cause runner’s knee (patellofemoral pain), strain on inner knee ligaments, or early arthritis. Over time, these problems can limit mobility and cause pain, especially in active people or those with demanding jobs. In some places with limited healthcare, knock knees may go undiagnosed or untreated. Malnutrition, vitamin D deficiency, and diseases like rickets contribute to persistent knock knees in children. Public health efforts focusing on nutrition and early care can help prevent these issues. Modern orthopaedics and physiotherapy have improved outcomes. Guided growth surgery can correct deformities in children with open growth plates. Adults with severe knock knees might benefit from bone realignment surgery (osteotomy) or, in extreme cases, knee replacement. Overview of Knock Knees: Living with the Condition Having knock knees does not always limit daily life. Many with mild to moderate knock knees stay active and healthy without treatment. Regular exercise, balanced nutrition, proper shoes, and good posture help reduce discomfort and slow progression. However, those with pain, balance problems, or movement limits should see a doctor for support and monitoring. Early diagnosis and care can improve results and quality of life. In summary, the overview of knock knees shows it can range from a normal childhood phase to a serious adult condition. Knowing its causes, effects, and treatments helps individuals and caregivers decide when to watch, when to act, and how to protect long-term joint health. Early professional evaluation makes a strong difference for people affected by this common orthopedic issue. [Next: Causes of Knock Knees →]

Overview of Knock Knees Read More »

Symptoms of Knock Knees

Symptoms of Knock Knees

Symptoms of knock knees can vary widely depending on the age of the individual, the severity of the condition, and any underlying medical causes. While mild knock knees in young children are usually part of normal growth, more serious or lasting cases can cause pain and movement problems. These symptoms can also limit daily activities. Knowing the symptoms of knock knees helps with early detection, proper care, and avoiding long-term joint problems. Symptoms of knock knees in children In children younger than seven, knock knees often occur naturally. This is part of how their bones grow and shift. The most noticeable sign is how the knees look. When a child stands straight with feet together, the knees touch, but the ankles remain apart. This is called genu valgum. It usually fixes itself with time. These children often do not have pain or trouble moving. They can run, walk, and play just like other kids. When knock knees don’t improve But when the angle of the knees stays the same or becomes worse after early childhood, the symptoms of knock knees become clearer. One early sign is a strange walking style. Affected people might swing their legs outward while walking. Sometimes the knees rub together, which can feel uncomfortable or look awkward. These signs are often more obvious during sports or long walks. Knee pain is another common symptom. This pain often appears on the inner or outer side of the knee. Because the knees are not straight, pressure shifts to one side more than the other. Over time, this uneven load causes strain. The knee may swell or feel sore. The pain often gets worse with activity. In children, the pain might be mild and easy to miss. But teens and adults might feel stronger, long-lasting pain that disrupts their daily lives. Knock knees may affect other body parts In serious or untreated cases, the symptoms of knock knees may affect other parts of the lower body. The poor knee alignment changes the way the body moves. This can lead to pain in the hips, ankles, or lower back. Some people feel hip tightness or unsteady ankles. Others say their legs feel weak or give out when active. These changes happen because the body is trying to adjust. It shifts how it moves to balance the uneven knees. Muscle tiredness and weakness can also happen. The thigh and calf muscles must work harder to keep balance. This extra effort leads to faster tiredness. Kids may avoid playing or sports due to discomfort or being shy about how they look. Adults may feel sore after walking or standing for a long time. More signs of knock knees in everyday life Another clue is how shoes wear out. Knock knees make the legs turn inward. This causes the inside edges of shoes to wear down faster. This uneven shoe wear shows how the body weight is not balanced. Even people without pain may notice this early sign. It helps spot knock knees before worse symptoms begin. Swelling or puffiness around the knees may also be present. This happens if the joint is inflamed, especially in those with other health issues like juvenile arthritis or past injuries. Swelling may come and go. It gets worse with activity and better with rest. The knee may feel sore, warm, or look red. Severe symptoms of knock knees In more serious cases—especially when knock knees come from bone disease, injury, or genetic conditions—the legs may look very misaligned. Sometimes one leg is worse than the other. This can make walking harder and raise the chance of falls. It may also wear down the joints and limit physical ability. Social symptoms are also important, especially for teens and adults. People who have visible knock knees may feel embarrassed or have low self-esteem. They might avoid group sports or other public activities. These feelings are often overlooked but can greatly affect mental health. Symptoms of knock knees in adults The symptoms of knock knees in adults tend to be more serious than in kids. Adults may get knock knees from arthritis, past injury, or another health problem. These cases may include stiff joints, less ability to move, grinding sounds in the knees, and worsening movement over time. Some adults find it hard to squat, kneel, or rise from a chair without pain. Adults who had knock knees as children may notice their symptoms worsen over the years. This can happen due to joint wear and tear. Without treatment, the joints can slowly break down. This may lead to cartilage loss and the need for joint replacement later in life. Early care helps manage symptoms of knock knees In short, the symptoms of knock knees can range from mild changes in walking to serious pain, weak muscles, and joint damage. Younger children may just have a cosmetic issue. Older people may struggle with pain and movement. Spotting the symptoms of knock knees early—especially when they last beyond the normal age for correction or appear in adulthood—is key. A healthcare check-up can help find the cause and start treatment. This prevents long-term issues and helps people stay active and healthy. [Next: Diagnosis of Knock Knees →]

Symptoms of Knock Knees Read More »

Diagnosis of Knock Knees

Diagnosis of Knock Knees

Diagnosis of knock knees involves a comprehensive evaluation that takes into account the individual’s medical history, physical appearance, gait pattern, and any underlying conditions contributing to the alignment issue. A doctor starts by talking through the person’s symptoms and past health problems. They then look at the body’s structure and how the person walks. Each case is different, especially in children and adults. That’s why a personal approach helps make the diagnosis clear and guides the right treatment plan. Diagnosis of Knock Knees in Young Children In babies and toddlers, slightly bent or knock-kneed legs often form part of normal growth. Paediatricians usually spot this during regular check-ups. If the leg position seems typical for the child’s age and the child shows no signs of pain or walking problems, doctors usually just keep an eye on things. At this stage, they mainly rely on what they see and how the child grows over time. No advanced scans or tests are needed unless something seems off. As children grow older, especially after age seven, or if teenagers or adults show signs of knock knees, doctors dig deeper. They want to know if the condition is caused by illness, keeps getting worse, or is linked to something else. A full medical history is taken to look for root causes. These might include poor nutrition, past injuries, bone problems, infections, or family history. For example, if close family members had rickets or Blount’s disease, doctors will take a closer look. Physical Exam and Gait Analysis for Diagnosis of Knock Knees Next comes a physical exam. The doctor watches how the person stands and walks. They may ask the person to put their feet together. If the knees touch but the ankles stay far apart—more than 8 to 10 centimetres—it often points to a strong case of knock knees. The doctor also checks if one leg is longer, whether the hips move well, and if there’s any swelling, pain, or muscle weakness. Sometimes a gait test is done to see how the person walks. This is helpful when knock knees change how someone moves. In special clinics, labs use motion sensors to track walking. These results help doctors decide if braces, therapy, or even surgery might be needed. Imaging and Lab Tests in the Diagnosis of Knock Knees To confirm the diagnosis of knock knees, X-rays are usually the first choice. These scans show how the bones line up. Doctors often take the X-rays while the person is standing to see how their legs carry their weight. They measure the angle between the thigh bone and the shin to see how severe the bend is. If the case looks more complicated, doctors may order extra tests like MRIs or CT scans. These give a better look at the soft parts inside the knee, like cartilage and ligaments. They’re especially helpful if the person feels pain or has swelling. An MRI can show early signs of joint wear, damaged cartilage, or fluid inside the knee. Blood tests usually aren’t needed. But if a doctor suspects the knock knees are caused by another illness, they might check blood levels of calcium, vitamin D, or signs of infection or inflammation. In rare cases, a genetic test might be done if doctors think the problem runs in the family. Monitoring and Special Tools for Diagnosis of Knock Knees For kids and teens, tracking growth over time is important. Regular check-ups help spot if the knees are getting better, staying the same, or getting worse. If the angle gets worse, doctors may act early to avoid future problems. Growth charts and bone age scans from hand X-rays can help measure changes during childhood. Photos can also be useful. Parents might be asked to take pictures of their child standing in the same way over time. These pictures help doctors spot changes without needing repeated X-rays. In adults, especially those with knee pain or joint wear, the focus shifts. The doctor still checks for knock knees but also looks at how the problem affects walking, balance, and joint health. Movement tests, squats, and balance checks give clues about what’s going on. Classifying Severity in the Diagnosis of Knock Knees Once doctors are sure about the diagnosis of knock knees, they decide how serious it is—mild, moderate, or severe. This step helps guide treatment. Mild cases might only need regular checks or exercise. Severe ones could require braces or surgery. In short, the diagnosis of knock knees needs a full check—talking to the patient, watching how they move, taking X-rays, and sometimes doing lab tests. Finding the problem early makes it easier to treat. Whether the goal is to help a child grow properly or ease pain in adults, a clear diagnosis leads to better care and less chance of long-term joint damage. [Next: Treatment of Knock Knees →]

Diagnosis of Knock Knees Read More »

Scroll to Top